This study compares health-related quality of life between long-term breast cancer survivors with and without lymphedema and examines clinical factors associated with poorer quality-of-life outcomes.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Health-Related Quality of Life and Associated Factors in Long-Term Breast Cancer Survivors With and Without Lymphedema: A Cross-Sectional Study
In This Article
Summary
Abstract
Breast cancer-related lymphedema is a common long-term complication of breast cancer treatment that may continue to affect survivors well beyond active treatment. This study compared health-related quality of life between long-term breast cancer survivors with and without lymphedema and examined factors associated with poorer quality of life in a hospital-based cross-sectional study. Women who had undergone definitive breast cancer surgery at least 5 years earlier were recruited from outpatient and follow-up services at Shaoxing People's Hospital. Lymphedema status was determined using predefined criteria based on symptom duration and objective upper-limb measurements. Health-related quality of life was assessed using the Functional Assessment of Cancer Therapy-Breast (FACT-B), the EQ-5D-5L, and the EQ visual analogue scale (EQ-VAS). Clinical, treatment-related, and symptom-related variables were collected for adjusted analyses. Among 268 long-term breast cancer survivors, 69 were classified as having lymphedema and 199 as not having lymphedema. Participants with lymphedema had lower breast cancer-specific and generic health-related quality-of-life scores than those without lymphedema. In adjusted analyses, lymphedema status and pain remained independently associated with lower FACT-B total scores. These findings indicate that lymphedema remains associated with poorer health-related quality of life in long-term breast cancer survivors and support continued symptom-oriented surveillance during survivorship.
Introduction
Breast cancer remains the most frequently diagnosed malignancy in women, and continued gains in detection and treatment have enlarged the population living beyond the initial disease episode1. As survival improves, the clinical focus necessarily extends beyond recurrence and mortality to the long-term conditions that shape daily life after treatment. Some of these conditions are apparent during active care, whereas others emerge later, persist over time, and become increasingly important as survivorship extends over years rather than months.
Breast cancer-related lymphedema belongs to the latter category. It is a chronic treatment-related condition that may develop shortly after surgery or remain clinically evident many years later, particularly in women exposed to more extensive axillary treatment or regional irradiation2. Its reported frequency varies widely across studies, in part because case definitions differ and because different diagnostic approaches do not identify completely overlapping patient populations3. In this study, diagnostic classification combined symptom duration with standardized bilateral circumference and estimated limb-volume measurements, while alternative causes of arm swelling were excluded. Although this variability complicates comparisons across studies, it does not obscure the underlying clinical point that lymphedema remains one of the most persistent survivorship burdens after breast cancer treatment.
The condition is also not evenly distributed across survivors. Higher body mass index, axillary lymph node dissection, nodal irradiation, and multimodal treatment have repeatedly been associated with an increased risk of lymphedema4. Long-term follow-up data further suggest that this burden does not simply disappear with time; rather, a meaningful proportion of survivors continue to experience arm swelling or related symptoms several years after diagnosis5. The consequences extend beyond physical manifestations. Ongoing management costs, compression needs, clinic visits, work disruption, and treatment access can create broader practical, financial, and social burdens6.
This is clinically important because lymphedema is closely associated with health-related quality of life. Women with breast cancer-related lymphedema have been shown to report poorer quality of life than those without lymphedema, particularly in areas related to physical functioning, daily activities, and treatment-related discomfort7. That burden is often accompanied by fatigue, which may further impair functional recovery and overall health perception in survivorship populations already coping with upper-limb morbidity8. Among Chinese breast cancer survivors, lymphatic pain and related symptom burden have also received increasing attention, suggesting that the lived experience of lymphedema extends beyond visible swelling alone9.
Despite these findings, an important knowledge gap remains. Much of the literature has focused on incidence and risk prediction or on mixed survivorship populations without distinguishing long-term survivors from those who are relatively close to treatment. Earlier studies in Chinese women suggested that lymphedema after breast cancer treatment was associated with poorer quality of life, but evidence regarding long-term breast cancer survivors from hospital-based cross-sectional studies remains limited10. This gap is clinically relevant because long-term survivors often experience less acute treatment toxicity but continue to face chronic functional limitations, self-management demands, and cumulative survivorship burden.
The present study was therefore designed to compare health-related quality of life between long-term breast cancer survivors with and without breast cancer-related lymphedema in a hospital-based Chinese cross-sectional study and to examine the factors associated with quality-of-life impairment in this population.
Access restricted. Please log in or start a trial to view this content.
Protocol
This single-center cross-sectional study was conducted at Shaoxing People’s Hospital through the breast surgery outpatient clinic, survivorship follow-up clinic, and hospital follow-up registry. The protocol was approved by the institutional ethics committee of Shaoxing People’s Hospital before recruitment began (approval no. JX20250291). All participants provided written informed consent before enrollment. The study was carried out in accordance with the Declaration of Helsinki and local regulations governing research involving human participants.
Study design and setting
The study was designed to compare health-related quality of life in long-term breast cancer survivors with and without breast cancer-related lymphedema and to examine factors associated with impaired quality of life. For this study, long-term survivorship was operationally defined as survival for 5 years or more after definitive breast cancer surgery. Recruitment was conducted from January 2023 through December 2024 at Shaoxing People’s Hospital. Eligible survivors were identified from outpatient schedules and the hospital follow-up database. All 268 participants completed a single in-person study visit, and no participant underwent a second clinical study visit. When clarification of a missing questionnaire response or verification of a chart variable was required, a supplementary telephone contact was permitted within 14 days; this administrative clarification did not involve repeat clinical assessment and did not constitute an additional study visit. Group classification was determined from the study-day clinical assessment together with chart review and was not redefined during the follow-up contact period. The study workflow is shown in Figure 1.
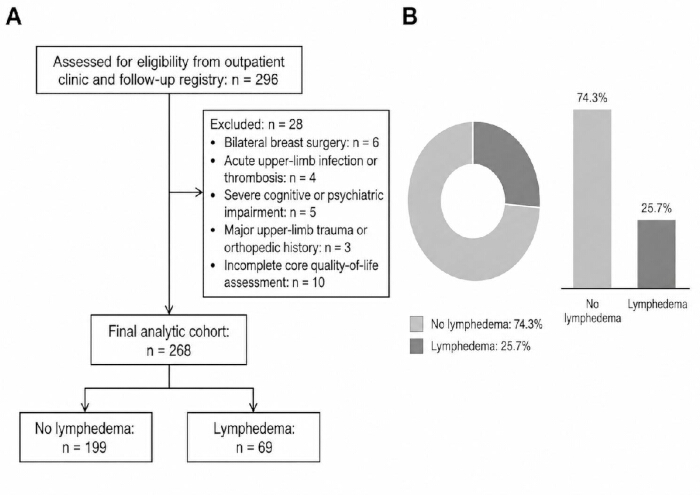
Figure 1. Study flow and final analytic grouping. (A) Flow diagram showing participant screening, eligibility assessment, reasons for exclusion, and inclusion in the final analytic cohort. A total of 296 participants were assessed for eligibility, 28 were excluded, and 268 participants were included in the final analysis. (B) Distribution of participants in the final analytic cohort, comprising 199 participants without breast cancer-related lymphedema (BCRL; 74.3%) and 69 participants with BCRL (25.7%). Group assignment was based on the predefined study criteria combining symptom duration and objective upper-limb assessment.Please click here to view a larger version of this figure.
Participant identification and eligibility screening
Participants were eligible if they were women aged 18–75 years, had pathologically confirmed unilateral primary breast cancer, had completed primary cancer treatment, had undergone definitive breast surgery at least 5 years earlier, had no evidence of local recurrence, distant metastasis, or second primary malignancy within the previous 6 months, were able to complete the questionnaires independently or with neutral reading assistance, and provided written informed consent. Participants were excluded if they had bilateral breast surgery, known primary lymphedema, major prior upper-limb trauma or orthopedic surgery affecting arm volume, acute cellulitis at the time of assessment, upper-extremity deep vein thrombosis, severe cardiac or renal edema, thyroid-related edema, or another medical condition likely to cause arm swelling independent of breast cancer treatment. Participants were also excluded if they had undergone a major upper-limb procedure within the previous 3 months or were unable to complete the core assessments because of severe cognitive or psychiatric impairment. Screening was completed in two stages. A research assistant first reviewed the electronic medical record for preliminary eligibility. Final confirmation was then made on site by a breast surgeon or a trained specialist nurse. When a discrepancy arose between chart review and direct assessment, the on-site clinical assessment was used for the final eligibility decision.
Sample size planning
The primary multivariable analysis used health-related quality of life as the dependent variable. The study prespecified 12 candidate predictors. A minimum of 15 evaluable participants per predictor was used as the planning rule, giving a minimum analytic sample of 180 participants. Allowing for incomplete questionnaires, post-screening exclusions, and missing covariate data, the recruitment target was set at a minimum of 210 participants. The final analysis set included participants who completed group classification and at least one core quality-of-life outcome.
Group classification for breast cancer-related lymphedema
Participants were assigned to either the lymphedema group or the non-lymphedema group using objective arm measurements, symptom duration, and the exclusion of alternative causes of swelling. Group assignment was completed before questionnaire scoring. The study protocol prespecified classification according to the presence or absence of BCRL. Objective measurements were used to confirm case status and were not intended to establish formal mild, moderate, or severe lymphedema stages.
Pre-measurement preparation
Participants rested in a seated position for 10 min before measurement. Vigorous upper-limb exercise was avoided during the preceding 12 h. Intensive edema-directed treatment, including manual lymphatic drainage, was not performed within 2 h before measurement. Participants who routinely used compression sleeves were asked to remove them at least 2 h before assessment, when clinically tolerable. If this was not possible, the reason was documented. A single study-day measurement did not overrule an established clinical history of persistent lymphedema documented in the medical record.
Circumference measurement procedure
Bilateral arm circumferences were measured by two trained research nurses using a non-stretch flexible measuring tape and recorded to the nearest 0.1 cm. Participants were assessed in a relaxed upright position with both arms resting naturally beside the trunk and the elbows gently extended. Circumference was measured at five predefined matched levels referenced to the olecranon: the wrist crease, 10 cm distal to the olecranon, the olecranon level, 10 cm proximal to the olecranon, and 15 cm proximal to the olecranon. Each level was measured twice. If the difference between the two readings was greater than 0.5 cm, a third measurement was obtained immediately. The final value was the mean of the two closest readings. Measurements were performed during fixed clinic time windows (08:30–11:30 or 14:00–16:30).
Diagnostic threshold for lymphedema
Breast cancer-related lymphedema was diagnosed after excluding acute infection, venous thrombosis, cancer recurrence, and systemic causes of edema. A participant was classified as having lymphedema when swelling-related symptoms had persisted for at least 3 months and either of the following objective criteria was present: a circumference difference of 2.0 cm or greater between the affected and contralateral arm at one or more predefined matched sites, or an estimated limb-volume increase of 10% or greater in the affected arm relative to the contralateral side11. Limb volume was estimated from the five circumference values by constructing four truncated-cone segments and summing the segment volumes12. Participants with a prior hospital diagnosis of breast cancer-related lymphedema remained in the lymphedema group if current symptoms or signs were still present, even when swelling was partially controlled at the study visit. The prespecified case definition required swelling-related symptoms to persist for at least 3 months. The protocol did not establish or retain a separate early-lymphedema analytic group for individuals with more recent swelling; therefore, the available dataset could not support an early-lymphedema subgroup comparison.
Symptom confirmation
After arm measurement, the assessor recorded heaviness, tightness, numbness, reduced range of motion, and difficulty related to wearing sleeves or bracelets or performing routine arm activities. Symptom onset and symptom duration were also recorded. For the descriptive analysis, an unweighted symptom-count score was calculated from five prespecified findings: heaviness, tightness, numbness, reduced range of motion, and difficulty wearing sleeves or bracelets or performing routine arm activities. Each finding was coded as absent (0) or present (1), giving a total score of 0–5. Symptom burden was categorized as low (0–1), moderate (2–3), or high (4–5). Participants with symptoms but without objective findings meeting the predefined diagnostic threshold were not classified as having lymphedema in the primary analysis. This symptom-count classification was used only for exploratory descriptive analysis and should not be interpreted as a standardized clinical measure of lymphedema severity.
Clinical and sociodemographic data collection
Clinical data were abstracted from the electronic medical record and verified with the participant when necessary. Variables included age, marital status, education, employment, insurance status, affected side, pathological stage, breast surgery type, axillary lymph node dissection, sentinel lymph node biopsy, chemotherapy, radiotherapy, endocrine therapy, targeted therapy, and time since surgery. Height and weight were measured on site. Height was recorded to the nearest 0.1 cm and weight to the nearest 0.1 kg. Body mass index was calculated as weight divided by height squared (kg/m2). Body mass index categories followed the Chinese adult classification: <18.5 kg/m2 for underweight, 18.5–23.9 kg/m2 for normal weight, 24.0–27.9 kg/m2 for overweight, and ≥28.0 kg/m2 for obesity13. Time since surgery was calculated from the date of definitive breast cancer surgery to the date of the study visit and recorded in months. If there was disagreement between participant recall and the medical record, the medical record was used. Detailed information on current lymphedema-directed treatment, including compression use, manual lymphatic drainage, rehabilitation participation, and treatment duration, was not systematically captured and was therefore not included as an analytic covariate.
Health-related quality-of-life assessment
Health-related quality of life was the primary study outcome. A breast cancer-specific instrument and a generic health-status instrument were administered in Chinese. Questionnaires were completed in a quiet room after the clinical assessment. Neutral reading assistance was provided when needed. Assessors were not permitted to comment on symptom severity, probable group assignment, or expected responses during questionnaire administration.
FACT-B
The primary breast cancer-specific outcome was the Functional Assessment of Cancer Therapy-Breast (FACT-B), Version 4. The scale contains 37 items, each scored from 0 to 4. Reverse-scored items were recoded according to the FACIT scoring manual14. The total score ranges from 0 to 148, with higher scores indicating better health-related quality of life. When more than 50% of items within a subscale were completed, the subscale score was prorated according to FACIT scoring guidelines. When completion fell below that threshold, the subscale score and any dependent total score were treated as missing. The validated simplified Chinese version of the FACT-B was administered in this study15.
EQ-5D-5L and EQ-VAS
Generic health status was assessed using the EQ-5D-5L, which includes five dimensions with five response levels each: mobility, self-care, usual activities, pain/discomfort, and anxiety/depression. Participants also completed the EQ visual analogue scale (EQ-VAS), scored from 0 to 10016. The EQ-5D-5L utility index was calculated using the Chinese value set17. If any EQ-5D-5L dimension was missing, the utility index was not calculated. Missing EQ-VAS responses were retained as missing only for that variable. The officially developed Chinese EQ-5D-5L descriptive system was used18.
Assessment of covariates potentially associated with quality of life
Additional variables were collected to capture symptom burden, psychological status, physical activity, and social support.
Pain intensity:
Pain in the affected arm, axilla, or ipsilateral chest wall during the previous 7 days was assessed using an 11-point numeric rating scale, ranging from 0 (no pain) to 10 (worst imaginable pain). For descriptive analyses, pain was categorized as mild (1–3), moderate (4–6), and severe (7–10), with a score of 0 reported separately.
Anxiety and depressive symptoms:
The Hospital Anxiety and Depression Scale (HADS) was used to assess anxiety and depressive symptoms19. Each subscale ranges from 0 to 21. Scores of 0–7 were classified as normal, 8–10 as borderline abnormal, and 11 or higher as indicating clinically relevant symptom burden. Continuous scores were used in the primary regression models. The validated Chinese version for cancer populations was administered20.
Physical activity:
The International Physical Activity Questionnaire-Short Form (IPAQ-SF) was used to assess physical activity during the previous 7 days21. Total activity was calculated in metabolic equivalent (MET)-minutes/week using the standard scoring algorithm. Activity below 600 MET-min/week was classified as insufficient. Values of 600 MET-min/week or greater were classified as meeting the basic recommended level. Implausible responses were checked once with the participant. Unresolved inconsistencies were treated as missing. The Chinese short-form version has demonstrated acceptable reliability and validity22.
Social support:
Social support was assessed using the Social Support Rating Scale (SSRS)23. Total scores range from 12 to 66, with higher scores indicating greater perceived support. For descriptive presentation, support was categorized as low (<23), moderate (23–44), and high (>44). Continuous scores were retained for regression analysis. The SSRS was originally developed for use in Chinese populations; therefore, a separate translated-version citation was not required.
Field implementation and quality control
All research nurses received standardized training before formal recruitment. Training covered participant approach, informed consent, anatomical positioning, arm-measurement technique, questionnaire administration, and data-entry procedures. A 10-participant pilot run was completed before formal enrollment, and pilot cases were excluded from the final dataset. Paper questionnaires were checked immediately after completion. Blank items were identified using a neutral prompt, and participants were allowed to decide whether to answer them. No directional prompting was permitted. All data were entered independently by two staff members. Automated and manual checks were then performed for score ranges, impossible values, treatment-history inconsistencies, abnormal circumference values, and date conflicts. Suspected errors were resolved by reviewing the original paper forms and medical records. If the correct value could not be confirmed, the original entry was retained and flagged. During the early recruitment phase, paired duplicate arm measurements were reviewed weekly to detect systematic measurement drift between assessors.
Statistical analysis
The analysis set included all participants with completed group classification and at least one core quality-of-life outcome. Normally distributed continuous variables were summarized as mean ± standard deviation and compared using the independent-samples t test. Non-normally distributed continuous variables were summarized as median and interquartile range and compared using the Mann–Whitney U test. Categorical variables were summarized as counts and percentages and compared using the Pearson chi-square test or Fisher’s exact test, as appropriate. The primary outcomes were the FACT-B total score, the EQ-5D-5L utility index, and the EQ-VAS score. Group differences between participants with and without lymphedema were examined first. Multivariable linear regression was then fitted with the FACT-B total score as the primary dependent variable. Prespecified candidate predictors were age, body mass index, time since surgery, axillary lymph node dissection, radiotherapy, chemotherapy, lymphedema status, pain score, HADS anxiety score, HADS depression score, physical activity, and social support. Variables with P < 0.10 in univariable analyses were eligible for entry into the multivariable model. Clinically important variables could be retained regardless of the univariable threshold. Multicollinearity was assessed before final model fitting, and a variance inflation factor greater than 5 was considered evidence of relevant collinearity. All tests were two-sided, and P < 0.05 was considered statistically significant. When the proportion of missing data for variables required in a specific model was less than 5%, complete-case analysis was used. When a key covariate had 5% or greater missingness, multiple imputation by chained equations was performed using 20 imputed datasets, and estimates were pooled using Rubin’s rules. Outcome variables were not imputed24.
Data management and confidentiality
The participant identification file and the analytic dataset were stored separately. The identification file was password protected and accessible only to the principal investigator and the designated data manager. The analysis dataset contained study codes, group classification, measurement results, questionnaire scores, and de-identified clinical variables only. Electronic files were stored on a hospital server with controlled access and retained for at least 5 years after study completion. No identifiable data were released outside the institution without additional ethics approval.
Access restricted. Please log in or start a trial to view this content.
Results
Study cohort and group classification
A total of 268 long-term breast cancer survivors were included in the final analysis after completion of group classification and availability of at least one core health-related quality-of-life outcome. Among them, 69 participants (25.7%) met the predefined criteria for breast cancer-related lymphedema, whereas 199 participants (74.3%) were classified as not having lymphedema. All 69 participants classified as having lymphedema met the pr...
Access restricted. Please log in or start a trial to view this content.
Discussion
The present study found that breast cancer-related lymphedema was associated with poorer health-related quality of life among long-term breast cancer survivors. This pattern was observed across the breast cancer-specific measure, the generic utility-based measure, and the self-rated health scale, rather than being limited to a single outcome instrument. Previous studies have likewise shown that the burden of lymphedema may persist for many years after breast cancer treatment, even after survivors have completed active tr...
Access restricted. Please log in or start a trial to view this content.
Disclosures
Conflicts of Interest:
The authors declare that they have no conflicts of interest.
Acknowledgements
The authors acknowledge the support of the Zhejiang Province Traditional Chinese Medicine Science and Technology Project (No. 2024ZL1136), the Zhejiang Medicine and Health Science and Technology Project (No. 2024KY1704), and the Zhejiang Medicine and Health Science and Technology Project (No. 2024KY467). The authors also thank the Department of Breast and Thyroid Surgery, Shaoxing People's Hospital, for its support during the conduct of this study.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| EQ-5D-5L questionnaire with EQ-VAS, Chinese version | EuroQol Research Foundation | EQ-5D-5L, Chinese (China), paper self-complete version | Generic health-status instrument comprising the five-dimension descriptive system and the EQ visual analogue scale (EQ-VAS). The registered Chinese (China) version was administered, and utility index scores were calculated using the Chinese EQ-5D-5L value set. |
| FACIT scoring guidelines | FACIT.org / FACITtrans, LLC | FACT-B Version 4 scoring template, revised 11 June 2013 | Used for reverse scoring, prorating eligible incomplete subscales, and calculating FACT-B domain and total scores according to the Version 4 scoring instructions. |
| FACT-B questionnaire, Chinese version | FACIT.org / FACITtrans, LLC | FACT-B, Version 4, Simplified Chinese | Breast cancer-specific health-related quality-of-life questionnaire containing 37 items. The Simplified Chinese Version 4 was used consistently for all participants. |
| Flexible circumference measuring tape | seca GmbH & Co. KG | seca 201 | Non-stretch flexible circumference-measuring tape with millimeter graduation. Used for duplicate bilateral upper-limb circumference measurements at predefined matched anatomical levels. |
| Hospital Anxiety and Depression Scale (HADS), Chinese version | GL Assessment / Mapi Research Trust | HADS, Chinese version | Fourteen-item instrument comprising seven-item anxiety and depression subscales. The Chinese version was used consistently for all participants. |
| International Physical Activity Questionnaire-Short Form (IPAQ-SF), Chinese version | IPAQ Research Committee | IPAQ-SF, Chinese, short self-administered form, last 7 days; scoring protocol revised November 2005 | Chinese short-form physical-activity questionnaire covering the previous 7 days. MET-min/week was calculated using the standardized IPAQ scoring protocol. |
| Portable stadiometer | seca GmbH & Co. KG | seca 213 | Portable free-standing stadiometer used to measure standing height to the nearest 0.1 cm. |
| Social Support Rating Scale (SSRS), Chinese version | Xiao Shuiyuan, original developer | SSRS, 10-item Chinese scale, 1994 | Chinese social-support instrument containing 10 items covering objective support, subjective support, and utilization of support. Scoring followed the original method described by Xiao Shuiyuan. |
| Spreadsheet software | Microsoft Corporation | Microsoft Excel for Microsoft 365 | Used for independent double data entry, range checking, identification of inconsistencies, and data reconciliation before statistical analysis. |
| Stand-on digital floor scale | seca GmbH & Co. KG | seca 813 | Digital flat scale with 200 kg capacity and 100 g graduation. Used to measure body weight to the nearest 0.1 kg. |
| Statistical analysis software | IBM Corporation | IBM SPSS Statistics, Version 29.0 | Used for descriptive statistics, between-group comparisons, multivariable linear regression, multicollinearity assessment, complete-case analyses, and statistical data checks. |
References
- Giaquinto AN, et al. Breast cancer statistics 2024. CA Cancer J Clin. 2024;74(6):477-95.
- Sharifi N, Ahmad S. Breast cancer-related lymphedema: a critical review on recent progress. Surg Oncol. 2024;56:102124.
- Hing JX, et al. Defining breast cancer-related lymphedema (BCRL) prevalence and risk factors: a pragmatic approach to lymphedema surveillance. Ann Acad Med Singap. 2024;53(2):80-9.
- Matsumoto A, et al. Database study of risk factors for breast cancer-related lymphedema: a statistical analysis of 2359 cases over 10 years. Surg Today. 2025;55:685-92.
- Ren Y, et al. Burden of lymphedema in long-term breast cancer survivors by race and age. Cancer. 2022;128(23):4119-28.
- Yarmohammadi H, Soltanipur M, Shahrabi Farahani M, Hosseini SE, Sheikhi Z. Financial burden of lymphedema among breast cancer survivors in Iran: a qualitative study. J Med Vasc. 2024;49(5-6):203-10.
- Turgay T, Günel Karadeniz P, Maralcan G. Quality of life for women with breast cancer-related lymphedema: the importance of collaboration between physical medicine and rehabilitation and general surgery clinics. Arch Breast Cancer. 2021;8(2):119-26.
- Acikgoz Orhan S, Ozsaker E. Lymphedema, fatigue, and quality of life in breast cancer survivors with axillary lymph node dissection. Lymphat Res Biol. 2025;23(2):107-14.
- Shen A, et al. When obesity meets lymphedema: interaction effects on lymphatic pain among Chinese breast cancer survivors. Clin Breast Cancer. 2026;26(2):36-44.
- Mak SS, et al. Lymphedema and quality of life in Chinese women after treatment for breast cancer. Eur J Oncol Nurs. 2009;13(2):110-5.
- Armer JM, et al. Lymphedema symptoms and limb measurement changes in breast cancer survivors treated with neoadjuvant chemotherapy and axillary dissection: results of American College of Surgeons Oncology Group (ACOSOG) Z1071 (Alliance) substudy. Support Care Cancer. 2019;27(2):495-503.
- Brorson H, Höijer P. Standardised measurements used to order compression garments can be used to calculate arm volumes to evaluate lymphoedema treatment. J Plast Surg Hand Surg. 2012;46(6):410-5.
- Group of China Obesity Task Force. Body mass index reference norm for screening overweight and obesity in Chinese adults. Zhonghua Liu Xing Bing Xue Za Zhi. 2004;25(2):97-102.
- Brady MJ, et al. Reliability and validity of the Functional Assessment of Cancer Therapy-Breast quality-of-life instrument. J Clin Oncol. 1997;15(3):974-86.
- Wan C, et al. Validation of the simplified Chinese version of the FACT-B for measuring quality of life for patients with breast cancer. Breast Cancer Res Treat. 2007;106(3):413-8.
- Herdman M, et al. Development and preliminary testing of the new five-level version of EQ-5D (EQ-5D-5L). Qual Life Res. 2011;20(10):1727-36.
- Luo N, et al. Estimating an EQ-5D-5L value set for China. Value Health. 2017;20(4):662-9.
- Luo N, et al. Developing the Chinese version of the new 5-level EQ-5D descriptive system: the response scaling approach. Qual Life Res. 2013;22(4):885-90.
- Zigmond AS, Snaith RP. The Hospital Anxiety and Depression Scale. Acta Psychiatr Scand. 1983;67(6):361-70.
- Li Q, et al. The Chinese version of hospital anxiety and depression scale: psychometric properties in Chinese cancer patients and their family caregivers. Eur J Oncol Nurs. 2016;25:16-23.
- Craig CL, et al. International physical activity questionnaire: 12-country reliability and validity. Med Sci Sports Exerc. 2003;35(8):1381-95.
- Macfarlane DJ, Lee CC, Ho EYK, Chan KL, Chan DTS. Reliability and validity of the Chinese version of IPAQ (short, last 7 days). J Sci Med Sport. 2007;10(1):45-51.
- Xiao SY. Theoretical basis and research application of the Social Support Rating Scale. J Clin Psychiatry. 1994;4(2):98-100.
- Sterne JAC, et al. Multiple imputation for missing data in epidemiological and clinical research: potential and pitfalls. BMJ. 2009;338:b2393.
- Jørgensen MG, Toyserkani NM, Hansen FG, Bygum A, Sørensen JA. The impact of lymphedema on health-related quality of life up to 10 years after breast cancer treatment. NPJ Breast Cancer. 2021;7:70.
- Anbari AB, Wanchai A, Armer JM. Breast cancer-related lymphedema and quality of life: a qualitative analysis over years of survivorship. Chronic Illn. 2021;17(3):257-68.
- Togawa K, et al. Self-reported symptoms of arm lymphedema and health-related quality of life among female breast cancer survivors. Sci Rep. 2021;11:10701.
- Qiu JM, et al. Lymphatic pain in breast cancer survivors: an overview of the current evidence and recommendations. Women Child Nurs. 2024;2(2):33-8.
- Chachaj A, et al. Physical and psychological impairments of women with upper limb lymphedema following breast cancer treatment. Psychooncology. 2010;19(3):299-305.
- Boyages J, et al. Axillary treatment and chronic breast cancer-related lymphedema: implications for prospective surveillance and intervention from a randomized controlled trial. JCO Oncol Pract. 2023;19(12):1116-24.
- Che Bakri NA, et al. Impact of axillary lymph node dissection and sentinel lymph node biopsy on upper limb morbidity in breast cancer patients: a systematic review and meta-analysis. Ann Surg. 2023;277(4):572-80.
- Li H, et al. Analysis of the risk factors of breast cancer-related lymphedema and construction and evaluation of a prediction model. Lymphat Res Biol. 2023;21(6):565-73.
- Rafn BS, Christensen J, Larsen A, Bloomquist K. Prospective surveillance for breast cancer-related arm lymphedema: a systematic review and meta-analysis. J Clin Oncol. 2022;40(9):1009-26.
- Shah C, Asha W, Vicini F. Current diagnostic tools for breast cancer-related lymphedema. Curr Oncol Rep. 2023;25(3):151-4.
- Wong HCY, et al. Multinational Association of Supportive Care in Cancer (MASCC) clinical practice guidance for the prevention of breast cancer-related arm lymphoedema (BCRAL): international Delphi consensus-based recommendations. EClinicalMedicine. 2024;68:102441.
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
This article has been published
Video Coming Soon