This study evaluates compound acid chemical peeling in patients with moderate acne vulgaris. In the split-face trial of 30 patients, treatment reduced Global Acne Grading System scores, skin redness, porphyrins, and expression of IL-1α, IL-6, IL-17, TGF-β, and TLR2. Skin microbiome diversity decreased, especially Staphylococcus, with no adverse events reported during follow-up.
Research Article
Efficacy of Compound Acid Chemical Peeling in Patients with Moderate Acne: A Prospective Study with Comprehensive Facial Evaluation
* These authors contributed equally
In This Article
Summary
Abstract
Compound acid chemical peeling is widely used to treat acne vulgaris (AV), but the biological mechanisms underlying its clinical effects remain incompletely understood. We hypothesized that compound acid chemical peeling would improve acne severity and would be associated with changes in the skin microbiome and a reduction in local inflammatory responses in patients with moderate AV. This study aimed to investigate the clinical, microbiological, and inflammatory effects of compound acid peeling in this population. We carried out a prospective, split‑face, randomized trial enrolling 30 patients with moderate AV. One hemiface received compound acid peeling twice weekly for 3 weeks (6 total sessions), followed by a 9‑week observation period. The contralateral hemiface received no treatment for the first 3 weeks and then underwent the same peeling protocol for 3 weeks, with a 6‑week follow‑up. Outcome measures included the Global Acne Grading System (GAGS), patient self‑assessment, standardized facial imaging, skin biopsy with immunohistochemistry, bacterial DNA extraction, PCR amplification, and 16S rRNA gene sequencing. Patients showed a statistically significant improvement in GAGS scores (P < 0.001). Facial imaging analysis revealed reductions in redness and porphyrin readings. Immunohistochemical staining for interleukin (IL)-1α, IL-6, IL-17, transforming growth factor-β (TGF-β), and toll-like receptor 2 (TLR2) was reduced. Skin microbiome alpha diversity decreased, with a notable decrease in the relative abundance of Staphylococcus (P < 0.05). Throughout the study, no adverse events were reported. Compound acid peeling was effective and well-tolerated during the observation period and was associated with changes in the skin microbiome and local inflammatory marker staining.
Introduction
Acne vulgaris (AV), commonly known as acne, is a chronic inflammatory skin disorder primarily affecting hair follicles and sebaceous glands. It is characterized by the development of papules, pustules, nodules, and cysts, predominantly on the face, chest, and back. While acne mostly affects teenagers and young adults, it can arise at any age, with a global prevalence estimated to be between 70% and 87% among individuals aged 12 to 24 years1,2. Notably, acne can persist into adulthood, especially in females, with an increasing incidence observed in individuals aged 25 years and older. The development of acne is influenced by multiple factors, including heightened sebum production3, follicular hyperkeratinization4, bacterial colonization5, and inflammation6. Cutibacterium acnes (C. acnes) and Staphylococcus epidermidis (S. epidermidis) are two key bacteria in the skin microbiota that play crucial roles in regulating the inflammatory response. The balance between C. acnes and S. epidermidis was found to be critical for maintaining a normal inflammatory response in the skin5. When the balance between these two is disrupted, it activates inflammation-related markers that trigger acne.
Current acne treatment strategies include both topical and systemic options aimed at addressing different facets of the condition. These include topical retinoids, benzoyl peroxide7, topical antibiotics, and systemic agents such as oral antibiotics and isotretinoin for more severe cases8. In recent years, chemical peeling has emerged as a promising treatment for acne. This technique involves the application of specific acids to exfoliate the skin, enhance skin texture, and diminish the appearance of acne lesions and scars9. Commonly used acids in chemical peeling include alpha-hydroxy acids (AHAs), such as glycolic acid, and beta-hydroxy acids (BHAs), such as salicylic acid. These acids operate through various mechanisms, including reducing inflammation and preventing comedone formation. In particular, compound acid formulations, which combine multiple acid types or varying concentrations of a single acid, have garnered attention for their potential therapeutic benefits. The primary advantage of compound acids is their ability to simultaneously target multiple pathways involved in acne pathogenesis10.
Clinical research examining the effectiveness of compound acid peeling for acne has shown promising outcomes, including significant reductions in acne severity and lesion counts, as well as improvements in skin texture, in patients receiving treatment11. Although previous studies have reported the clinical benefits of chemical peels for acne, most available evidence has focused on single-acid formulations or clinical outcomes such as lesion counts and acne severity. While it is hypothesized that the combination of exfoliating, anti-inflammatory, and antimicrobial properties of these acids contributes to their efficacy, the precise molecular pathways involved remain to be fully elucidated. To our knowledge, this is the first study to investigate the effect of compound acids on skin microbiota composition and inflammatory responses in individuals with moderate acne.
Protocol
The study protocol was reviewed and approved by the Ethics Committee of the First Affiliated Hospital of Chongqing Medical University (No. 2024-020-01). The study was prospectively registered with the National Medical Research Registry, China (registration number: MR-50-24-036087; registration date: September 6, 2024). Written informed consent was obtained from all participants before enrollment, including consent for the publication of de-identified facial photographs. The study was conducted in accordance with the Declaration of Helsinki.
Study design
This was a 12‑week, split‑face, randomized, prospective clinical study. The compound acid peel used in this study consisted of AHA (4%), salicylic acid (2%), and azelaic acid (1.5%), with a total acid concentration of approximately 7.5%. The pH of the formulation was 3.6. Prior to initiating the study, the allocation of participants to the treatment and control arms was determined using a random sequence generated in a spreadsheet by a blinded statistician and implemented by a blinded doctor. The treatment side received compound acid peeling twice weekly for 3 weeks (six sessions total). The treatment area was gently cleansed with a mild, non-oily cleanser and dried completely, then the peel was applied in a thin, uniform layer (~2 mL per hemiface). The formulation was applied in a standardized sequence from the forehead and temples to the cheeks, nose, perioral region, and chin, while avoiding the eyelids, lips, mucosal surfaces, and damaged skin. The product was left in contact with the skin for 15 min, then neutralized with water. The clinical endpoint was mild, uniform erythema with tolerable tingling or warmth and without excessive burning, edema, blistering, or extensive frosting. After removal, a soothing and moisturizing mask was applied for 15 min.
Participants were instructed to avoid irritating topical products, exfoliation, picking, and direct sun exposure and to use broad-spectrum sunscreen during the daytime. This 3‑week treatment phase was followed by a 9‑week follow‑up period. The control side received no intervention during the first 3 weeks. After this initial waiting period, the control side was given the same 3‑week compound acid peeling course, followed by a 6‑week follow‑up. Five sessions per hemiface were administered by trained medical personnel at the hospital, whereas one session per hemiface was performed by the participant at home under standardized instructions provided by the investigators. The participant was provided with standardized written and verbal instructions regarding the amount and distribution of the product, the application sequence and treatment area, the prescribed exposure time, and the removal procedure. A schematic overview of the study design and experimental workflow is presented in Figure 1.
Patient recruitment
Thirty patients aged 18–60 years with a clinical diagnosis of moderate acne vulgaris (AV) were enrolled in the study. Eligible participants were of any sex and met the diagnostic criteria for moderate AV, corresponding to grade 2 (31–50 lesions, including comedones, papules, and pustules) or grade 3 (51–100 lesions, including numerous papules and pustules, occasional large inflammatory lesions, and fewer than three nodules). Patients were excluded if they had photosensitive skin or had used photosensitizing medications within the preceding 4 weeks; had a history of intense sun exposure within the preceding month or anticipated substantial sun exposure within 1 month after treatment; had scarring, active infection, or non-healing wounds at the treatment site; had a diagnosed immunodeficiency disorder; had severe cardiac, hepatic, or renal dysfunction; or had a documented psychiatric illness. All 30 eligible participants completed the study and were included in the final analysis.
Outcome assessments
Objective evaluations
Erythema and porphyrin analysis
Under standardized environmental conditions (fixed temperature, humidity, and lighting), a facial imaging system was used to capture images of the bilateral forehead, cheeks, jawline, and other affected areas at baseline and at each follow-up. This system allowed objective quantification of erythema intensity and porphyrin levels.
Microbiota sampling and immunohistochemistry
Skin microbiome profiling was performed on microbial swabs collected from the treated side before treatment and at week 3. Microbial DNA was extracted from the swabs with the specified extraction kit, following the manufacturer’s protocol, and the recovered DNA was then quantified. The bacterial 16S rRNA region was amplified with the universal primers 341F (5’-CCTACGGGNGGCWGCAG-3’) and 805R (5’-GACTACHVGGGTATCTAATCC-3’). Amplification began with denaturation at 98 °C for 30 s, followed by 32 cycles of 98 °C for 10 s, 54 °C for 30 s, and 72 °C for 45 s. A final extension was carried out at 72 °C for 10 min.
PCR amplicons were purified using the specified beads and quantified prior to library assessment. Product quality was evaluated using a bioanalyzer and quantitative PCR kit, after which eligible amplicons were pooled for sequencing. The demultiplexed raw reads were processed by first removing primer sequences with Cutadapt. Paired-end reads were assembled in FLASH, and fqtrim was used to exclude reads with quality scores below 20, lengths below 100 bp, or ambiguous bases accounting for more than 5% of the sequence. Clean tags that passed quality filtering were retained for downstream analysis. Chimeras were removed with Vsearch, and DADA2 was used to denoise the remaining reads and generate amplicon sequence variants (ASVs).
Species annotation was completed in QIIME2 with the feature-classifier plugin against the SILVA and NT-16S databases. QIIME2 was also used to calculate alpha and beta diversity. Bacterial composition was evaluated from relative-abundance profiles. Differences in genus-level abundance were tested using the Wilcoxon test, with P < 0.05 considered significant. Linear discriminant analysis effect size was performed with nsegata-lefse, using LDA ≥3.0 and P < 0.05 as the thresholds.
Among the enrolled participants, 10 patients were randomly selected for immunohistochemical analysis of inflammatory mediators, including IL-1α, IL-6, IL-17, TGF-β, and TLR2. Skin biopsy samples (2 mm) were collected from active acne lesions at baseline (week 0) and week 3 after disinfection with iodophor. Samples were fixed in 4% paraformaldehyde, embedded in paraffin, and cut into 4‑μm sections. Paraffin-embedded sections (4 μm) were deparaffinized and rehydrated. Antigen retrieval was performed using EDTA buffer (pH 9.0) with microwave heating. Endogenous peroxidase was quenched with 3% H2O2, after which sections were treated with 3% goat serum to reduce nonspecific antibody binding. The sections were then incubated with the primary antibodies overnight at 4 °C: IL-1α (1:400), IL-6 (1:400), IL-17A (1:400), TGF-β (1:400), and TLR2 (1:300). Subsequently, sections were incubated with a Polymer-HRP secondary antibody kit for 30 min at room temperature, followed by DAB chromogen detection and hematoxylin counterstaining. Negative controls were incubated with PBS instead of primary antibodies. Images were acquired using a digital scanner at 400× magnification. Five fields were randomly selected per section, and scoring was performed by two blinded dermatologists.
Subjective evaluations
Investigator global assessment
At baseline and week 12, a dermatologist blinded to treatment allocation assessed acne severity over the entire face using the Global Acne Grading System (GAGS).
Patient self‑assessment
At the end of the treatment and follow-up period, participants rated their perceived clinical improvement using a four-point self-assessment scale. The scores were defined as follows: 0, no improvement or worsening; 1, mild improvement; 2, moderate improvement; and 3, obvious improvement.
Blinded outcome assessment
To reduce assessment bias, a dermatologist blinded to treatment allocation independently evaluated clinical improvement using baseline photographs.
Safety monitoring
Adverse events were evaluated at every follow‑up visit to assess treatment safety.
Statistical analysis
Before study initiation, the sample size was estimated to detect a change in the whole-face GAGS score from baseline to week 12. The sample size calculation was based on a pilot study of compound acid peeling, assuming a standardized within-participant effect size of 0.60, a two-sided significance level of 0.05, and 80% power, 24 evaluable participants were required. Allowing for 20% attrition, the target enrollment was 30 participants.
Statistical analysis was conducted using statistical software and graphing software (see Table of Materials). Continuous data were described according to their distribution. Variables that were approximately normally distributed were reported as the mean ± standard deviation, whereas non-normally distributed variables were summarized as the median with interquartile range or range, as appropriate. Categorical data were expressed as counts and percentages.
Data distribution was evaluated using the Shapiro-Wilk test and supported by visual review of histograms and Q-Q plots. Because the sample size was small and several variables did not follow a normal distribution, the primary analyses were performed using nonparametric tests. Primary outcomes, including GAGS scores, red area, and porphyrin levels, were analyzed using the paired Wilcoxon signed-rank test.
Effect sizes and 95% confidence intervals were calculated for the primary clinical outcomes. For paired nonparametric comparisons, the matched-pairs rank-biserial correlation was used as the effect-size measure. Spearman's rank correlation was applied to evaluate relationships between continuous or ordinal variables. Statistical tests were two-sided, and results were considered significant at P < 0.05.
Microbiome analyses were performed on treatment-side samples collected from the same participants. Alpha diversity was evaluated using the Shannon and Simpson indices. Changes in alpha-diversity indices between baseline and post-treatment samples were assessed using the paired Wilcoxon signed-rank test.
The bacterial community composition was summarized by relative abundance at the phylum, family, and genus levels. Taxa with low abundance or low prevalence were retained for descriptive analysis. Differences in the relative abundance of specific taxa between baseline and post-treatment samples were evaluated using paired nonparametric tests. For microbiome analyses, taxon-level testing was exploratory, and unadjusted P values are reported. All tests were two-sided, with a significance threshold of P < 0.05.
Results
Baseline patient characteristics
Thirty patients were enrolled and completed all study procedures. Baseline demographic and clinical characteristics were summarized in Table 1.
VISIA skin analysis
Treatment with compound acid peeling led to visible improvement in acne lesions on both hemifaces. VISIA analysis confirmed meaningful reductions in erythema and porphyrin levels at week 12 follow-up. The red area score fell from 32.34 ± 6.32 at baseline to 18.34 ± 8.32 at week 12, indicating reduced cutaneous inflammation. Porphyrin values decreased from 34.24 ± 9.53 to 17.34 ± 8.43 (P < 0.05). Representative changes in erythema are shown in Figure 2.
Clinical efficacy outcomes
At week 12, whole-face GAGS scores were significantly lower compared with baseline (P < 0.001; Figure 3). Patient self‑assessment results showed that 3.3% of patients rated their improvement as mild (score 1), 83.3% as moderate (score 2), and 13.3% as obvious (score 3) (Table 2). Blinded investigator assessment yielded nearly identical results: 83.3% moderate improvement and 16.7% obvious improvement. No adverse events, including post‑inflammatory hyperpigmentation, blistering, crusting, scaling, hypertrophic scarring, or keloid formation, were observed.
Changes in skin microbiota α‑diversity
Compound acid peeling was associated with a significant reduction in the Shannon and Simpson indices (P < 0.05; Figure 4), indicating decreased within-sample microbial diversity after treatment.
Modulation of skin microbiota structure
Sequencing of the 16S rRNA gene indicated that the skin microbiota in patients with AV was primarily composed of five main phyla: Proteobacteria, Actinobacteria, Firmicutes, Bacteroidetes, and Cyanobacteria (Figure 5A). The relative abundance of Proteobacteria showed a significant increasing trend after treatment (P < 0.05).
At the family level, dominant taxa included Burkholderiaceae, Staphylococcaceae, Corynebacteriaceae, and Neisseriaceae (Figure 5B). The relative abundances of Cutibacterium (formerly Propionibacterium) and Staphylococcus were both significantly reduced post‑treatment (P < 0.05). Spearman correlation analysis for the top 30 most abundant genera is displayed in Figure 6.
Inflammatory marker expression
Immunohistochemical staining showed lower staining of IL‑1α, IL‑6, IL‑17, TGF‑β, and TLR2 in treated skin lesions compared with baseline (Figure 7).
Compound acid peeling was an effective and well-tolerated intervention for moderate acne vulgaris during the observation period. The clinical improvement was accompanied by changes in the skin microbiome and reduced inflammatory marker staining. Further research is warranted to clarify the precise molecular crosstalk between microbial modulation and immune regulation following peeling, with the goal of refining therapeutic protocols for routine clinical use.
Data Availability:
The datasets generated and/or analyzed during the current study are not publicly available due to participant privacy and ethical restrictions, but are available from the corresponding author upon reasonable request.
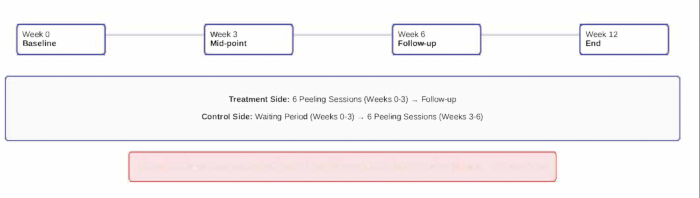
Figure 1. Schematic overview of the study design and experimental workflow. Abbreviations: GAGS = Global Acne Grading System; IHC = immunohistochemistry. Please click here to view a larger version of this figure.
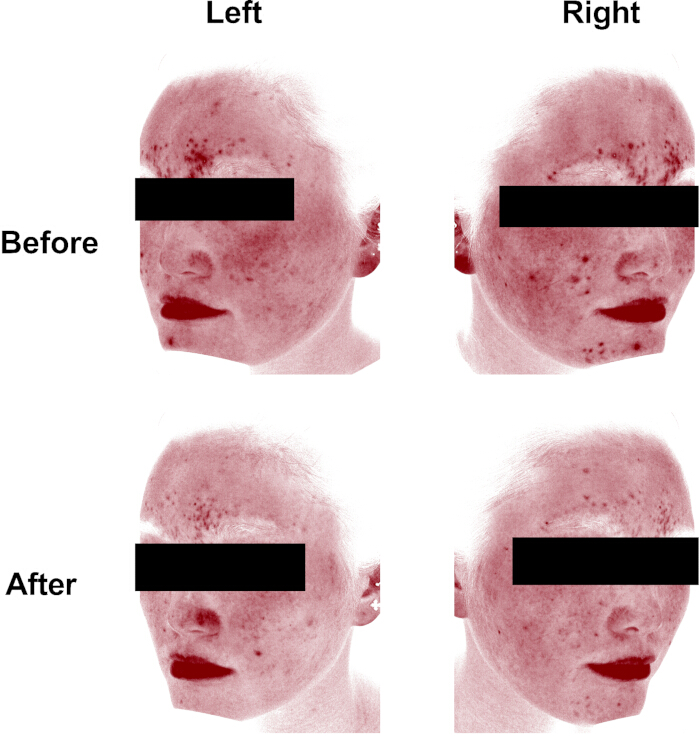
Figure 2. Erythema assessment of the left and right hemifaces. (A) Baseline and (B) week 12 in a 25-year-old female patient. Please click here to view a larger version of this figure.
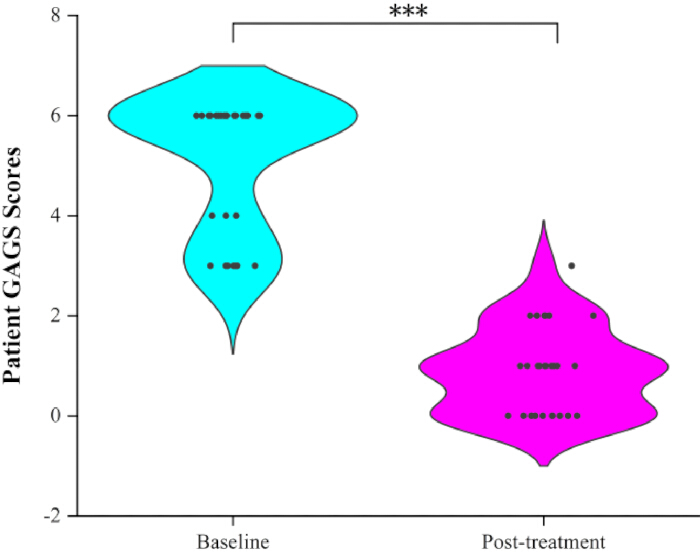
Figure 3. Whole-face GAGS scores at baseline and week 12 (n = 30). Groups were compared using the paired Wilcoxon signed-rank test; ***P < 0.001. Abbreviation: GAGS = Global Acne Grading System. Please click here to view a larger version of this figure.
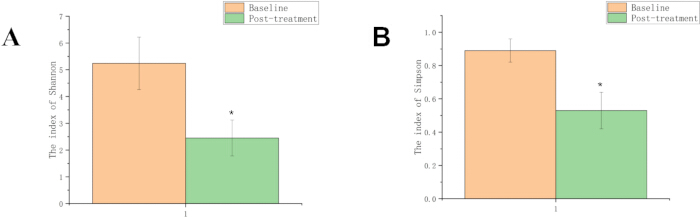
Figure 4. Diversity indices before and after treatment. (A) Shannon and (B) Simpson diversity indices (n = 30). Data are presented as medians, and error bars represent interquartile ranges (IQR). Groups were compared using the paired Wilcoxon signed-rank test; P = 0.021. Please click here to view a larger version of this figure.

Figure 5. Relative abundance of bacteria before and after treatment (n = 30). (A) Bacterial phyla and (B) families before and after treatment. Differences in relative abundance were evaluated using the paired Wilcoxon signed-rank test. The relative abundance of Proteobacteria increased significantly post-treatment (P = 0.024). Please click here to view a larger version of this figure.
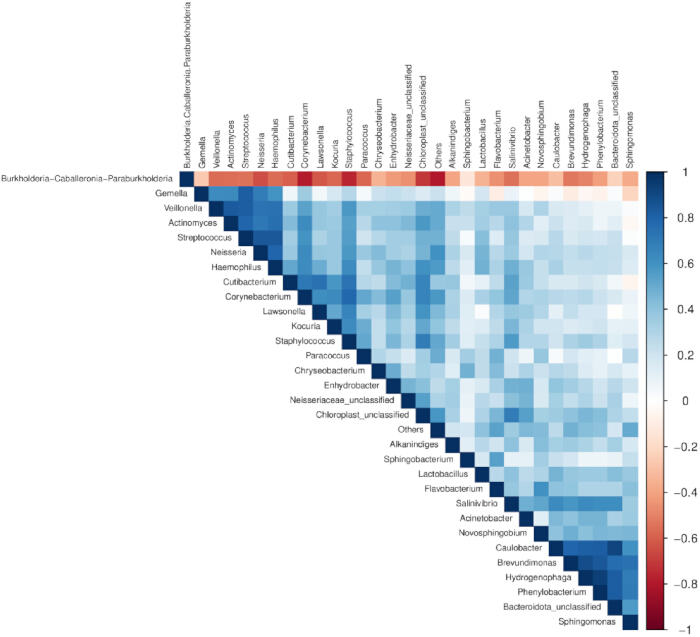
Figure 6. Spearman correlation heatmap for the 30 most abundant genera. The color scale ranges from -1 to 1. Please click here to view a larger version of this figure.
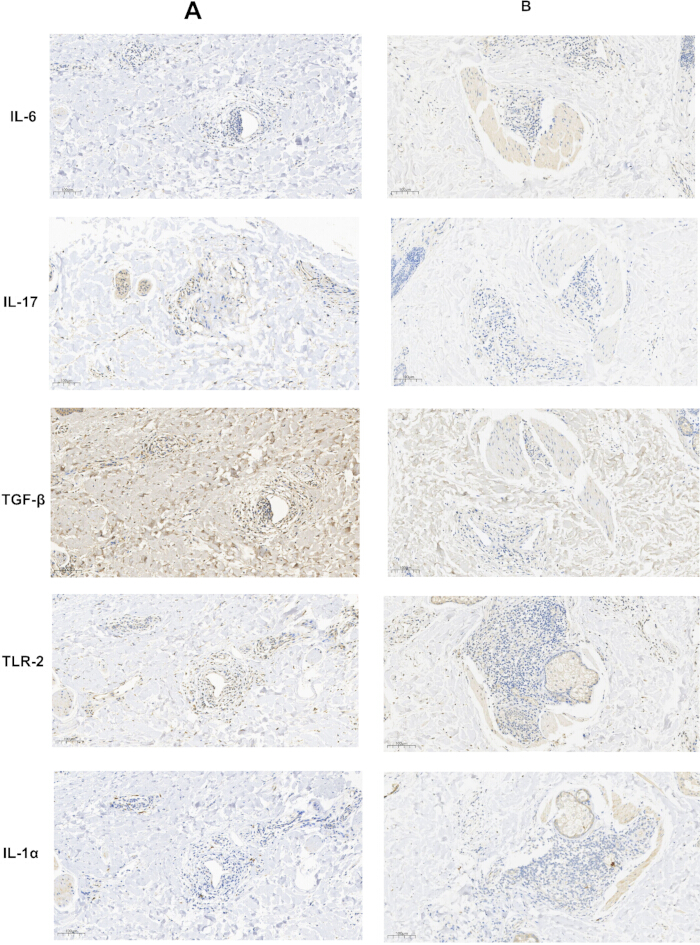
Figure 7. Representative immunohistochemical staining (A) Baseline and (B) week 3 after treatment in the 10-patient biopsy subgroup. Rows show IL-6, IL-17, TGF-β, TLR2, and IL-1α. Scale bars = 100 µm. Abbreviations: IL = interleukin; TGF-β = transforming growth factor-β; TLR2 = toll-like receptor 2. Please click here to view a larger version of this figure.
| Parameter | Mean ± SD (median; range) or n (%) |
| Age (years) | 23.77 ± 6.50 (18–42) |
| Sex | |
| Female | 18 (62%) |
| Male | 12 (38%) |
| Fitzpatrick skin type | |
| III | 22 (73%) |
| IV | 8 (27%) |
| Disease duration (months) | 29.80 ± 9.56 |
Table 1: Baseline characteristics of patients with acne vulgaris. Values are shown as mean ± SD (range) or n (%). Abbreviations: n = number of participants; SD = standard deviation.
| Measure | 0 (no improvement or worse) | 1 (mild improvement) | 2 (moderate improvement) | 3 (obvious improvement) | Mean ± SD |
| Patients (n) | 0 | 1 | 25 | 4 | 2.10 ± 0.40 |
Table 2: Patient self-assessment scores. Abbreviations: n = number of participants; SD = standard deviation.
Discussion
Our findings offer novel insights into the therapeutic effects of compound acid peeling treatment in the management of moderate AV. After the treatment, patients showed a notable improvement in their GAGS scores. Improvements were also noted in the VISIA scores, specifically for the red area and porphyrin. Additionally, the expression levels of key inflammatory markers, including IL-1α, IL-6, IL-17, TGF-β, and toll-like receptor 2, were reduced in the skin tissue following treatment. Moreover, there was a decline in both the richness and evenness of the cutaneous microbiome, accompanied by a significant reduction in the proportion of Staphylococcus. Notably, no adverse reactions were observed throughout the study. These improvements suggest that the compound acid peeling treatment not only effectively reduces visible acne lesions but also addresses the underlying inflammation that often accompanies acne.
The cutaneous microbiome plays a critical role in acne development, and the imbalance of this microbial community can exacerbate acne. Previous studies have shown that acne-prone skin often has an overgrowth of C. acnes and a reduction in beneficial bacteria. This microbial imbalance contributes to inflammation and sebum production, further accelerating acne progression. Previous literature highlights the increase of Proteobacteria in acne-affected skin and its potential relationship with acne development. Proteobacteria are associated with skin conditions due to their ability to trigger inflammatory pathways, thus exacerbating acne12,13. An increase in this bacterial group may reflect a shift in the skin microbiome, potentially linked to treatment-induced changes targeting acne-related bacteria or to alterations in the skin environment following the reduction of acne lesions.
Furthermore, the reduction in the Shannon and Simpson indices after treatment indicates that compound acid peeling may effectively simplify the microbial complexity of the skin. This shift towards a more stable microbial environment could contribute to the therapeutic success of the treatment. The observed dominance of certain bacterial phyla further supports the notion that acne treatment may be accompanied by microbial modulation14. The increase in Proteobacteria could reflect a shift in the microbial community structure due to treatment effects, consistent with previous studies15,16. This phylum includes various bacteria, some of which are known to be associated with skin conditions. An increase in this group may indicate a response to treatment or may relate to changes in the skin environment following the reduction of acne lesions17.
Inflammation plays a central role in the pathogenesis of acne. When Cutibacterium acnes (formerly Propionibacterium acnes) overgrows in the hair follicles, it triggers an immune response that results in the release of pro-inflammatory cytokines such as IL-1α, IL-6, and IL-177,18. This inflammation contributes to the formation of acne lesions like papules, pustules, and cysts. Chronic inflammation can also lead to scarring and skin damage, making it a key target in acne treatment. TGF-β is involved in various skin repair processes19, while TLR-2 is associated with the immune response to skin pathogens20. The analysis showed that post-treatment, the staining intensity of these inflammatory factors was significantly lower, indicating a reduction in their expression levels21. This anti-inflammatory effect may enhance the skin's healing response and could be a key mechanism by which compound acid peeling exerts its therapeutic benefits22,23.
The pathogenesis of acne vulgaris is closely linked to dysregulated interactions between C. acnes and host immune responses. Notably, virulent strains of C. acnes act as key microbial drivers of inflammation by activating TLR-2/4 signaling in keratinocytes and sebocytes24,25, which triggers downstream pro-inflammatory cascades characterized by elevated IL-1α, IL-6, IL-17, and TGF-β. Consistent with this mechanism, our results revealed a significant reduction in C. acnes abundance following compound chemical peel treatment. Importantly, this microbial shift was paralleled by decreased tissue expression of TLR-2 and its associated cytokines (IL-1α, IL-6, IL-17, TGF-β) in perilesional skin biopsies, suggesting that the therapeutic efficacy of compound chemical peeling may be partially attributable to suppression of C. acnes-mediated TLR-2/4 hyperactivation. These findings show that microbial and inflammatory changes occurred in parallel after treatment; causal relationships require further study.
A lower GAGS score indicates reduced acne severity among patients. These results support the efficacy of the treatment in managing AV and suggest that it is well-received by patients. The alignment between self-assessment and clinical assessment may indicate that the measure is valid and reliable for future studies.
Regarding the mechanism of compound acid peeling treatments, these therapies offer a multifaceted approach to acne management. Compound acid formulations, whose active ingredients include α-hydroxy acid, salicylic acid, and azelaic acid, may exert complementary anti-acne effects by targeting multiple pathogenic factors. α-hydroxy acid may promote epidermal exfoliation, reduce corneocyte adhesion, and improve abnormal follicular keratinization, thereby helping to relieve follicular obstruction and comedone formation24. Salicylic acid is a lipophilic beta-hydroxy acid that can enter the follicular unit and exert keratolytic, comedolytic, and anti-inflammatory effects. Azelaic acid may further contribute through its effects on keratinization, microbial growth, and cutaneous inflammation. In AV, abnormal keratinocyte desquamation results in follicular obstruction, creating an environment conducive to comedone and inflammatory lesion formation. By promoting exfoliation and reducing excess sebum production, compound acid treatments can help alleviate these blockages. Additionally, the anti-inflammatory properties of these acids reduce cytokine expression and inhibit inflammatory pathways, including those involving TLR2 and TGF-β25. This results in less inflammation and improved skin appearance. Additionally, the compound acid promotes epidermal cell turnover, helping eliminate dead skin cells and renew skin tissue. This process improves the overall texture and smoothness of the skin, helping reduce post-inflammatory hyperpigmentation, a common outcome of acne lesions. The treatment also appears to help restore microbial balance by reducing the overgrowth of C. acnes, addressing microbial dysbiosis and its inflammatory effects.
However, this study has limitations, including a small sample size, a brief follow-up period, and the possible influence of a "time effect" on the findings. The control group, which did not receive treatment during the initial 3 weeks, might have experienced natural improvement over time, potentially affecting the results. Hemiface-specific clinical severity data were not recorded before crossover; therefore, the whole-face GAGS results cannot be interpreted as a direct treated- versus control-hemiface comparison. To confirm the long-term efficacy and safety of this treatment, further research with extended follow-up periods and more comprehensive control groups is essential.
Disclosures
The authors have no conflicts of interest to declare.
Acknowledgements
This research was supported by the National Natural Science Foundation of China (No. 82573987).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Agilent 2100 Bioanalyzer | Agilent, USA | ||
| AMPure XP beads | Beckman Coulter Genomics, Danvers, MA, USA | ||
| Biopsy punch | 2 mm | ||
| Compound acid peel | XIMEIEN | A363 | Alpha-hydroxy acid 4%, salicylic acid 2%, and azelaic acid 1.5%; total nominal active-acid concentration approximately 7.5%; PH: 3.6, 12 g |
| cutadapt (v1.9) | removing sequencing primers | ||
| DADA2 | denoising and generating amplicon sequence variants | ||
| DNA cleanup beads | Vazyme | VAHTS DNA Clean Beads; used to purify PCR products | |
| DNA extraction kit | TIANGEN | DP302-02 | DNA Kit for skin tissue |
| DNA quantification assay kit | Invitrogen | Quant-iT PicoGreen dsDNA Assay Kit | |
| Facial imaging system | VISIA system; model/version not supplied | ||
| FLASH (v1.2.8) | merging paired-end reads | ||
| fqtrim (v0.94) | trimming reads containing >5% N records | ||
| llumina library quantitative kits | Kapa Biosciences, Woburn, MA, USA | ||
| Immunohistochemistry antibodies | Proteintech; Youpin Biology | 66148-1-Ig; YP-Ab-01185; YP-Ab-04780; YP-Ab-16022; YP-Ab-01522; YP-Ab-15931 | Supplied descriptions: IL-17A monoclonal antibody; TLR2 polyclonal antibody; TGF-β mouse monoclonal antibody (1F12); IL-6 polyclonal antibody; IL-1α polyclonal antibody |
| Iodophor | Lierkang, Shandong, China | Used to disinfect biopsy sites | |
| KF-PRO-120 digital scanner | Jiangfeng Bio | ||
| Light microscope | Used to examine immunohistochemistry sections | ||
| nsegata-lefse | LDA effect size | ||
| NT-16S | alignment database | ||
| Paired-end sequencing platform | Illumina (LC-Bio Technology Co., Ltd., Hangzhou, China) | NovaSeq 6000 SP Reagent Kit | Paired-end 250-bp sequencing |
| Paraffin | Used to embed biopsy samples | ||
| Paraformaldehyde | 4% solution used to fix biopsy samples | ||
| PCR primers 338F and 806R | 338F: 5′-ACTCCTACGGGAGGCAGCA-3′; 806R: 5′-GGACTACHVGGGTWTCTAAT-3′ | ||
| Post-peel mask | XIMEIEN | C85Y | Soothing and moisturizing mask; 28 mL × 6 pieces |
| QIIME2 | sequence alignment of species annotation | ||
| Qubit | Invitrogen, USA | DNA quantification | |
| Sequencing reagent kit | Illumina | NovaSeq 6000 SP Reagent Kit | Used for paired-end sequencing |
| SILV A | alignment database | ||
| Software, graphing | Origin Software Inc. | Origin 2021 | Graphing software |
| Software, statistical | IBM | SPSS 27.0 | Statistical analysis software |
| Vsearch software (v2.3.4) | filtering chimeric sequences |
References
- Machiwala AN, Kamath G, Vaidya TP. Knowledge, belief, and perception among youths with acne vulgaris. Indian J Dermatol. 2019;64(5):389-91.
- Tayel K, Attia M, Agamia N, Fadl N. Acne vulgaris: prevalence, severity, and impact on quality of life and self-esteem among Egyptian adolescents. J Egypt Public Health Assoc. 2020;95(1):30.
- Cong TX, et al. From pathogenesis of acne vulgaris to anti-acne agents. Arch Dermatol Res. 2019;311(5):337-49.
- Erdei L, et al. TNIP1 regulates Cutibacterium acnes-induced innate immune functions in epidermal keratinocytes. Front Immunol. 2018;9:2155.
- Grech I. Susceptibility profiles of Propionibacterium acnes isolated from patients with acne vulgaris. J Glob Antimicrob Resist. 2014;2(1):35-8.
- Podwojniak A, et al. Acne and the cutaneous microbiome: a systematic review of mechanisms and implications for treatments. J Eur Acad Dermatol Venereol. 2025;39(4):793-805.
- Argenziano G, et al. Review: expert opinion on antibiotics and antibiotic resistance in dermatology. Dermatol Pract Concept. 2024;14(4):e2024282.
- Li Y, et al. Acne treatment: research progress and new perspectives. Front Med (Lausanne). 2024;11:1425675.
- Măgerușan ȘE, Hancu G, Rusu A. A comprehensive bibliographic review concerning the efficacy of organic acids for chemical peels treating acne vulgaris. Molecules. 2023;28(20):7219.
- Calvisi L. Efficacy of a combined chemical peel and topical salicylic acid-based gel combination in the treatment of active acne. J Cosmet Dermatol. 2021;20 Suppl 2:2-6.
- Shao X, et al. Effect of 30% supramolecular salicylic acid peel on skin microbiota and inflammation in patients with moderate-to-severe acne vulgaris. Dermatol Ther (Heidelb). 2023;13(1):155-68.
- Kistowska M, et al. Propionibacterium acnes promotes Th17 and Th17/Th1 responses in acne patients. J Invest Dermatol. 2015;135(1):110-8.
- Jahns AC, et al. An increased incidence of Propionibacterium acnes biofilms in acne vulgaris: a case-control study. Br J Dermatol. 2012;167(1):50-8.
- Thompson KG, et al. Comparison of the skin microbiota in acne and rosacea. Exp Dermatol. 2021;30(10):1375-80.
- Li CX, et al. Skin microbiome differences relate to the grade of acne vulgaris. J Dermatol. 2019;46(9):787-90.
- Guo Z, et al. New insights into the characteristic skin microorganisms in different grades of acne and different acne sites. Front Microbiol. 2023;14:1167923.
- Boyanova L. Cutibacterium acnes, formerly Propionibacterium acnes: friend or foe? Future Microbiol. 2023;18:235-44.
- ElAttar Y, et al. Study of interleukin-1 beta expression in acne vulgaris and acne scars. J Cosmet Dermatol. 2022;21(10):4864-70.
- Tan JKL, Stein Gold LF, Alexis AF, Harper JC. Current concepts in acne pathogenesis: pathways to inflammation. Semin Cutan Med Surg. 2018;37(3S):S60-2.
- Rodighiero E, et al. Do acne treatments affect insulin-like growth factor-1 serum levels? A clinical and laboratory study on patients with acne vulgaris. Dermatol Ther. 2020;33(3):e13439.
- Huang L, et al. Association of different cell types and inflammation in early acne vulgaris. Front Immunol. 2024;15:1275269.
- Platsidaki E, Dessinioti C. Recent advances in understanding Propionibacterium acnes (Cutibacterium acnes) in acne. F1000Res. 2018;7:1953.
- Esen M. Effect of isotretinoin treatment on inflammatory and hematological parameters in patients with acne vulgaris. Cutan Ocul Toxicol. 2024;43(1):27-32.
- Handog EB, Datuin MS, Singzon IA. Chemical peels for acne and acne scars in Asians: evidence-based review. J Cutan Aesthet Surg. 2012;5(4):239-46.
- Lekakh O, et al. Treatment of acne vulgaris with salicylic acid chemical peel and pulsed dye laser: a split-face, rater-blinded, randomized controlled trial. J Lasers Med Sci. 2015;6(4):167-70.