This article presents an intraventricular cannulation and tracer infusion protocol tailored for dynamic contrast-enhanced MRI (DCE-MRI) studies in rodents. The protocol enables continuous tracer delivery during image acquisition, allowing whole-brain mapping of tracer transport and its clearance from the brain within a single, uninterrupted imaging session.
Method Article
Imaging Cerebrospinal Fluid Transport by Contrast-Enhanced Magnetic Resonance Imaging via Intraventricular Infusion in Rodents
In This Article
Summary
Abstract
Intraventricular (ICV) cannulation enables the delivery of exogenous tracers or therapeutic agents directly into the lateral ventricle, the origin of the cerebrospinal fluid (CSF) circulation pathway. Infused molecules are transported by CSF bulk flow through the ventricular compartments to the subarachnoid space and subsequently enter the brain parenchyma via the perivascular space. However, conventional ICV cannulation methods typically use ferromagnetic cannulas, which are incompatible with MRI studies and therefore require infusion to be performed outside the scanner and removal of the cannula prior to imaging. The time required for animal transport and imaging setup often results in the loss of the initial, and arguably most critical, phase of tracer transport. Here, we describe an MRI-compatible ICV cannulation and infusion protocol for rodents that supports continuous, in-scanner tracer delivery during dynamic MRI acquisition. The infusion line is constructed entirely from non-magnetic materials, enabling uninterrupted image acquisition within a single session. This approach is well-suited for dynamic contrast-enhanced MRI studies of CSF dynamics, glymphatic transport, solute clearance, and intrathecal drug delivery.
Introduction
The brain is one of the most metabolically active and dynamic organs in the body, continuously generating waste products that must be efficiently cleared to maintain normal neural function1. The accumulation of metabolic wastes is a hallmark of neurodegeneration and brain aging2. The glymphatic system plays a central role in this clearance process, facilitating the removal of metabolic by-products and toxic wastes through bulk cerebrospinal fluid (CSF) flow and the exchange of CSF with interstitial fluid (ISF)3,4,5, a process facilitated by the aquaporin-4 (AQP4) water channels located on the astrocytic endfeet6. A substantial understanding of CSF dynamics has been gained by studying the transport of various CSF tracers. Dynamic contrast-enhanced MRI (DCE-MRI) using gadolinium-based contrast agents (GBCAs) is particularly well suited for brain-wide evaluation of tracer transport7,8. The clinical relevance of this approach has been demonstrated by translational work in humans. Intrathecal administration of GBCAs followed by serial MRI was used to assess CSF dynamics in the human brain9. Subsequent work demonstrated brain-wide tracer transport followed by overnight clearance10. This approach was recently applied to reveal impaired periarterial tracer transport in subjects with reduced intracranial pressure-volume reserve capacity, as well as in patients with idiopathic normal-pressure hydrocephalus11. These studies establish DCE-MRI of CSF tracer transport as a clinically translatable approach and motivate the development of rigorous, reproducible preclinical methods for mechanistic investigation of the regulation of CSF dynamics and waste clearance.
Intra-cisterna magna (ICM) cannulation is commonly used in glymphatic studies for tracer delivery12. However, only approximately 20% of the GBCAs delivered via this route are transported into the brain parenchyma, with the majority draining directly into the spine or lymphatics8. This approach also carries a risk of damaging the cerebellum or brainstem, and securing the cannula for longitudinal studies remains technically challenging. Intraventricular (ICV) cannulation has emerged as a more robust alternative13,14,15. A recent study demonstrated its reproducibility and key advantages in delivering fluorescent tracers, including stable cannula fixation that allows free animal movement and supports repeated tracer injections in longitudinal studies13.
Despite these advantages, existing ICV cannulation protocols are not directly compatible with MRI studies16. Because ICV cannulation requires penetration of the brain parenchyma, it typically uses ferromagnetic cannulas that give rise to severe susceptibility artifacts in MRI images. As a result, tracer infusion must be performed outside the scanner, with the cannula removed prior to transferring the animal for imaging. A typical workflow involves acquiring a baseline scan, removing the animal for cannulation and tracer infusion, and then repositioning the animal for subsequent dynamic scans. This interrupted workflow precludes continuous, baseline-referenced acquisition and introduces repositioning misalignment that can confound voxel-wise kinetic analysis. More importantly, because the early uptake phase is typically the most dynamic yet transient portion of the tracer kinetics, performing animal transfer and scanner setup during this window results in the loss of the most informative data.
Here, we present a protocol that addresses these limitations by integrating an MRI-compatible ICV infusion line with in-scanner contrast-agent delivery capability that allows continuous dynamic MRI acquisition in rodents. This approach enables quantitative, whole-brain mapping of CSF tracer transport within a single, uninterrupted imaging session. This protocol is well-suited for studying brain-wide CSF dynamics, glymphatic transport, and solute-clearance kinetics. Although described here for adult rats, the protocol can be adapted for mice with appropriate adjustments of cannulation coordinates and infusion parameters15.
Protocol
The protocol described below was approved by the Institutional Animal Care and Use Committee (IACUC) of Case Western Reserve University (A-3145-01-2023-0015), in accordance with the Guide for the Care and Use of Laboratory Animals and the Public Health Service Policy on Humane Care and Use of Laboratory Animals. The reagents and the equipment used are listed in the Table of Materials.
1. Preparation of infusion line
- Cut a 30-mm segment of copper cannula and a 2-m length of polyethylene (PE) tubing using serrated scissors.
- Under a microscope, gently flare one end of the PE tubing with a 30 G needle, then insert the copper cannula into the expanded end and secure the junction with cyanoacrylate adhesive. Connect the opposite end of the PE tubing to a 30 G needle.
NOTE: Copper is highly ductile; take care not to collapse the lumen during cutting. Avoid deforming the cannula or puncturing the tubing during assembly. The length of the PE tubing should allow placement of the syringe pump outside the scanner’s fringe field. - Fill the cannula-tubing assembly with degassed tracer solution and connect it to a 50 µL Hamilton syringe. Wrap the syringe tip with polytetrafluoroethylene (PTFE) thread-seal tape to prevent leakage. Use caution to avoid introducing air bubbles during this process.
- Mount the Hamilton syringe onto the syringe pump and withdraw an additional 30 µL of tracer solution into the syringe.
2. Cannulation procedure
- Weigh the rat and anesthetize it with an intraperitoneal injection of ketamine (90 mg/kg) and xylazine (10 mg/kg). Confirm adequate anesthetic depth by the toe pinch reflex. Supplement with one-third of the initial dose if necessary and recheck before proceeding.
- Shave the head and neck, remove loose hair, and sterilize exposed skin with 70% ethanol pads.
- Secure the rat in a stereotaxic frame and place a heating pad covered with absorbent paper beneath the animal. Apply ophthalmic ointment to both eyes to prevent corneal drying.
- Adjust the nose clamp to level the skull. Make a midline incision and retract the skin with four hemostat clips to expose the bregma and lambda. Apply 3% hydrogen peroxide to the skull to clear residual periosteum and enhance landmark visibility.
NOTE: Accurate skull leveling is critical for reproducible cannula placement. As a practical quality control measure, compare the mediolateral (ML) and dorsoventral (DV) coordinates at bregma and lambda: if the skull is properly leveled, the difference between the two landmarks should not exceed 0.2 mm in either ML or DV axis. - Mount the electric drill with a fine drill bit to the stereotaxic arm and ensure the arm is firmly locked.
- Position the drill bit at bregma, then move 0.7 mm posterior and 1.4 mm lateral to the right. Lower the drill bit until it contacts the skull surface and record the DV coordinate.
- Under microscope observation, advance the drill in 0.1 mm increments. Stop immediately upon breach of the skull (typical skull thickness in adult rats is 0.3–0.4 mm).
- Replace the drill with the pre-loaded cannula on the stereotaxic arm. Advance the infusion pump briefly until fluid just emerges from the cannula tip, confirming an unobstructed fluid path.
- Ensure the cannula is mounted perpendicular to the skull surface, then align it over the burr hole. Advance the cannula at 0.1 mm/s to a final target depth of 3.5 mm below the dural surface.
- Apply a drop of tissue adhesive at the cannula-skull interface. Once cured, close the scalp incision with sutures and gently bend the copper cannula parallel to the skull surface to avoid contact with the MRI coil.
3. MRI setup and dynamic acquisition
- Place the volume transmitter coil at the isocenter of the scanner.
- Transfer the animal to an MRI-compatible cradle in the prone position. Connect the physiological monitoring system, including the respiratory sensor and rectal temperature probe. Turn on the circulating warm water bath to maintain body temperature at ~37 °C.
- Maintain proper anesthesia throughout the scanning session using supplemental isoflurane delivered via nose cone. Adjust isoflurane concentration between 0.25% and 1.0% to maintain a respiratory rate of 50–70 breaths/min.
NOTE: Ketamine-xylazine anesthesia administered before cannulation surgery will provide residual sedation during the initial transfer to the MRI cradle. Introduce isoflurane gradually and monitor respiration rate continuously during the scan.
CAUTION: Isoflurane is a volatile agent that poses an inhalation hazard; use active scavenging and minimize personnel exposure. - Place the infusion pump outside the magnet fringe field, set the infusion rate to 1 µL/min and the infusion duration to 20 min, corresponding to a total infusion volume of 20 µL. Carefully arrange and secure the infusion line along the cradle to prevent tension and displacement.
CAUTION: Ferromagnetic objects can become dangerous projectiles when placed near an MRI scanner. Keep all MRI-incompatible equipment outside the fringe field. - Mount the surface array coil directly over the dorsal skull, centered on the brain. Place a small piece of absorbent paper between the coil and the incision site to absorb any wound seepage.
- Advance the cradle into the magnet until the brain is at the isocenter. Verify that the infusion line and physiological monitoring leads remain unobstructed.
- Perform the initial scanner setup and acquire anatomical images to confirm successful cannula placement.
- After acquiring baseline images, start the infusion pump and the dynamic scan simultaneously, and continue acquisition for a total of 3 h (see Table 1 for acquisition details).
Results
The surgical workstation is configured to allow precise positioning of the drill to target the lateral ventricle (0.7 mm posterior and 1.4 mm lateral to bregma; Figure 1A,D). The infusion line consists of a 30-mm copper cannula, a 2-m segment of PE tubing, and a 30 G needle connected to a Hamilton syringe (Figure 1B). The extended tubing length allows the syringe pump to be placed outside the scanner's fringe field. Following burr-hole drilling, the pre-loaded infusion line is mounted on the stereotaxic arm, and the cannula is advanced into the lateral ventricle to a depth of 3.5 mm below the dural surface (Figure 1C). Once secured, the cannula is bent parallel to the skull surface to prevent contact with the MRI coil (Figure 1E).
Successful ICV cannulation can be confirmed from anatomical images that clearly resolve the ventricular system and cannula track, allowing direct visualization of the cannula tip within the ventricular lumen in both sagittal (Figure 2A) and axial (Figure 2B) views. These images also allow exclusion of animals with off-target cannula placement from DCE-MRI scans, including under-insertion, when the tip terminates within the corpus callosum, and over-insertion, when the tip extends into the thalamus. The spatiotemporal distribution of the tracer in DCE-MRI scans may provide additional confirmation of accurate cannula placement, as off-target placements deliver tracer into brain parenchyma, producing kinetics inconsistent with ventricular tracer propagation.
For DCE-MRI scans, ICV infusion of contrast agents is initiated after baseline acquisition, and dynamic image acquisition can last up to 3 h or longer (Figure 2C). Figure 2D shows representative 3D T1-weighted images acquired at different time points following contrast agent infusion. By the end of the 20-min infusion, enhancement is already apparent within the infused (ipsilateral) lateral ventricle, the third and fourth ventricles, and the cisterna magna, reflecting rapid bulk-flow propagation of the tracer through the ventricular-subarachnoid pathway. Signal enhancement is also observed in the parenchyma surrounding the ipsilateral lateral ventricle, suggesting tracer transport into periventricular tissue across the ependymal membrane.
More quantitative evaluation of contrast agent transport can be obtained using parametric mapping techniques, such as T1 and T2 mapping using magnetic resonance fingerprinting (MRF; Figure 3). Across intrathecal compartments, T1 decreases rapidly during infusion, propagating from the ipsilateral lateral ventricle to the third and fourth ventricles, with the cisterna magna exhibiting a slight delay in the onset of T1 shortening. ICV-administered contrast agents also demonstrate extensive penetration into the brain parenchyma, with periventricular regions (proximal) showing earlier and more pronounced T1 reduction, whereas more distal regions exhibit delayed and reduced T1 reduction. With a 3-h scan protocol, clearance of contrast agent from the brain parenchyma can also be evaluated from the kinetics of T1 recovery. Together, this protocol supports dynamic monitoring of major phases of CSF tracer transport, including rapid ventricular distribution, intrathecal propagation, parenchymal uptake, and subsequent clearance, within a single continuous MRI session.
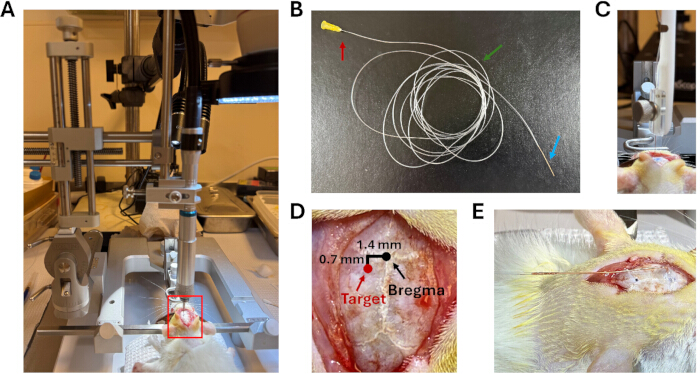
Figure 1: Surgical setup and infusion line assembly for MRI-compatible ICV cannulation. (A) Surgical workstation. An electric drill is positioned over the operative field for burr-hole drilling. (B) Assembled infusion line, comprising a 30 G needle (red arrow), a 2-m polyethylene tubing segment (green arrow), and a 30-mm copper cannula (blue arrow). (C) Pre-loaded infusion line mounted on the stereotaxic arm for cannula implantation. (D) Coordinates for cannula implantation. (E) Final appearance before closure; the copper cannula is bent parallel to the skull surface to avoid contact with the MRI coil. Please click here to view a larger version of this figure.
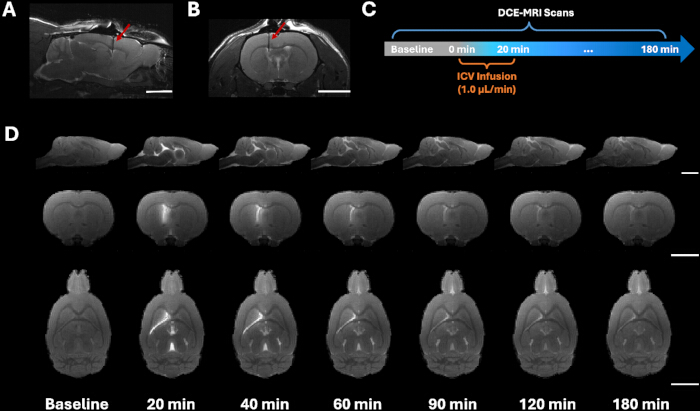
Figure 2: Cannula placement and dynamic monitoring of contrast agent transport following ICV infusion. (A,B) Visualization of cannula placement (red arrows) in anatomical images in the sagittal and axial views, respectively. (C) Schematic of the imaging protocol. (D) Representative 3D T1-weighted images at selected time points in the sagittal (top), axial (middle), and coronal (bottom) views. Scale bars, 5 mm. Please click here to view a larger version of this figure.
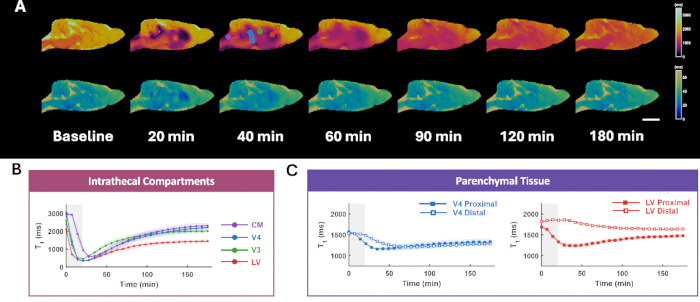
Figure 3: Quantitative assessment of tracer transport by magnetic resonance fingerprinting (MRF). (A) T1 (top) and T2 (bottom) maps reconstructed from 3D MRF data at selected time points following ICV infusion. Scale bar, 5 mm. (B) Mean T1 time courses in intrathecal compartments, including the ipsilateral lateral ventricle (LV), third ventricle (V3), fourth ventricle (V4), and cisterna magna (CM). The shaded gray region indicates the 20-min infusion period. (C) Mean T1 time courses in parenchymal tissue proximal and distal to V4 and ipsilateral LV. Locations of the ROIs for time courses are shown in (A). Please click here to view a larger version of this figure.
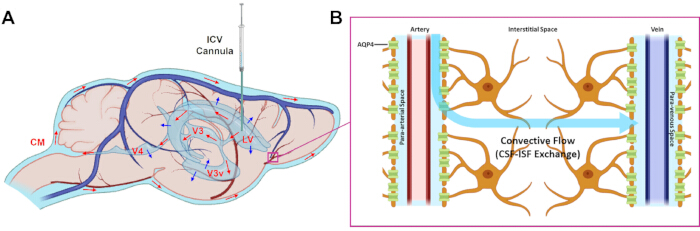
Figure 4: Schematics of CSF tracer transport following ICV infusion. (A) Sagittal view depicting tracer infusion via ICV cannula and its subsequent bulk-flow distribution through the ventricular system to the subarachnoid space (red arrows), as well as its transport across the ependymal membrane into the adjacent brain parenchyma (blue arrows). LV: lateral ventricle; V3: third ventricle; V3v: ventral third ventricle; V4: fourth ventricle; CM: cisterna magna. (B) Magnified schematic of the boxed area in (A) depicting the CSF-ISF exchange pathway. CSF enters the parenchyma along the para-arterial space, facilitated by aquaporin-4 water channels (AQP4) expressed on astrocytic endfeet, moves by convective flow through the interstitial space, and exits via the para-venous space into the draining vein. Please click here to view a larger version of this figure.
| Parameters | DCE-MRI (3D FLASH) | 3D MRF |
| Sequence type | T1-weighted 3D FLASH | 3D MRF (stack-of-spirals) |
| TR / TE (ms) | 20.0 / 2.7 | 10.0 / 2.0 |
| Flip angle | 10° | Variable (variable-flip-angle schedule) |
| Magnetization preparation | None | Inversion or T2 preparation (6 of 8 segments) |
| Field of view | 36 × 24 × 24 mm³ | 60 × 60 mm² (in-plane); 15 mm (through-plane) |
| Matrix size | 144 × 96 × 96 | 300 × 300 (in-plane); 30 (through-plane) |
| Spatial resolution | 0.25 mm isotropic | 0.2 × 0.2 mm² (in-plane); 0.5 mm (through-plane) |
| Temporal resolution | 3 min/frame | 7 min/frame |
| k-space trajectory | Cartesian | Stack-of-spirals trajectories; 48 interleaves for full sampling |
| Acceleration | None (single average) | 48-fold (24× in-plane, 2× through-plane) |
| Note | All imaging experiments were performed on a 9.4 T Bruker BioSpin system operating on the ParaVision 360 v3.4 platform. An 86-mm quadrature volume coil was used as the transmitter and a 4-channel surface array coil was used as the receiver. | |
Table 1: MRI acquisition parameters.
Discussion
The protocol described here integrates ICV cannulation with in-scanner infusion and dynamic MRI acquisition, enabling quantitative whole-brain assessment of CSF tracer transport within a single imaging session. The values, as well as the limitations, of ICV infusion are best evaluated in comparison with ICM infusion. ICM infusion avoids trans-parenchymal cannulation and is therefore less invasive. However, because the cisterna magna lies mid-stream in the CSF circulation pathway, ICM infusion, especially at higher infusion rates, can induce a transient reversal of the pressure gradient driving CSF circulation17. More importantly, ICM-administered tracers are rapidly distributed to the downstream subarachnoid space and subsequently, the perivascular space. Although AQP4 channels at the endfeet of astrocytes facilitate CSF-ISF exchange, these channels are not permeable to GBCAs given their large molecular size. As a result, ICM-administered tracers show significantly reduced contrast enhancement in the parenchyma compared to ICV infusion15, making ICM infusion less suitable for studying solute clearance from the brain. ICV infusion addresses these limitations by delivering tracers near endogenous CSF production sites13,14. Moreover, the pressure and concentration gradients during ICV infusion favor the direct transport of tracers across the ependymal layer13,14,15, enabling the use of these tracers as markers for waste clearance (Figure 4).
Several technical details are critical for reproducible outcomes. Accurate skull leveling is essential for consistent targeting of the lateral ventricle, as the margin for error in cannula placement is very small given the ventricle's small size. Assembly of a clog-free, leak-free infusion line is equally important. Air bubbles or partial occlusions can alter the infusion profile and compromise the interpretation of early-phase kinetics; in the worst-case scenario, a large bubble may completely obstruct the line, leading to experimental failure. Common issues during MRI setup include leakage at the syringe-needle junction, which can be mitigated by PTFE thread-seal tape, and tension on the infusion line during cradle insertion, which can be avoided by securing the tubing along the cradle to prevent pulling or kinking.
The target coordinates and insertion depth presented here were optimized for 12-week-old Wistar rats and may require adjustments for other ages and strains. ICV infusion can be performed on mice with appropriate modifications to account for the smaller body weight and ventricular size15. Infusion rate and total volume can be adjusted according to the physicochemical properties of the tracer, including molecular size and relaxivity; however, given the small volume of ventricular compartments, higher infusion rates may significantly increase ventricular pressure and should therefore be used with caution. Additionally, the copper cannula used in the current study provides the column strength needed to penetrate the dura and traverse the parenchyma in a single, straight pass. Its ductile properties also make it easy to bend, which is advantageous in space-limited coil configurations18. RF-induced heating is minimal given the short embedded length of the cannula. However, excessive degradation of copper can release free copper ions that give rise to neurotoxicity; therefore, a copper cannula is likely unsuitable for chronic implantation. For coil configurations that can accommodate a protruding cannula, silica or PEEK catheters provide adequate mechanical strength for insertion while avoiding these toxicity concerns14,19,20.
The contrast agent used here (Gd-DOTA) has a molecular weight of 558.65 Da, which is several-fold larger than endogenous metabolic solutes such as lactate (90 Da) and glucose (180 Da), yet far smaller than the larger protein-based aggregates of interest in neurodegeneration, such as amyloid-β monomers (~4.5 kDa) or tau (~45–65 kDa). This makes GBCAs reasonable proxies for small-molecule solute clearance kinetics, but findings should not be directly extrapolated to the clearance of larger macromolecular solutes. Furthermore, because AQP4 water channels are not permeable to GBCAs, findings cannot be directly extrapolated to CSF-ISF exchange that is facilitated by AQP4s.
In the current study, the cannulation procedure was immediately followed by an imaging session for the purpose of demonstrating feasibility. It is worth noting that cannula implantation may elicit an inflammatory response that can suppress glymphatic function13, and a 24-h waiting period would allow recovery of glymphatic function to baseline levels21. Investigators should take this factor into consideration when designing studies aimed at probing glymphatic function. Furthermore, a previous study reported that CSF influx is higher under ketamine/xylazine than under isoflurane anesthesia18. Accordingly, the current protocol uses ketamine/xylazine for initial induction. However, a single dose of ketamine/xylazine is insufficient to maintain stable anesthesia for the full duration of the combined cannulation and imaging protocol. The anesthesia regimen used here was adapted from a previous study that used dexmedetomidine with low-dose isoflurane22. It represents a trade-off between maintaining physiological stability over a prolonged protocol and minimizing anesthesia-related suppression of glymphatic function.
Despite the advantages, ICV infusion has some limitations. Given the small volume of cranial CSF (~300 µL)23, only a limited volume of tracers can be infused. Furthermore, the infusion rate (1 µL/min) is comparable to the CSF production rate (~1.6 µL/min)23,24; therefore, a transient increase in ventricular pressure is expected during infusion. Reducing the infusion volume or rate may partially mitigate this issue; however, a smaller tracer volume may compromise detection sensitivity, while a slower infusion rate prolongs the total infusion time without fully attenuating the pressure increase. Therefore, caution is warranted when interpreting tracer transport dynamics during the infusion period, though this limitation does not preclude reliable characterization of the subsequent distribution and clearance phases. Taken together, this MRI-compatible ICV infusion protocol offers a practical and adaptable platform for capturing the full time-course of CSF tracer transport in vivo, opening new avenues for studying CSF dynamics, solute clearance, and their disruption in disease.
Disclosures
The authors have no conflicts of interest to disclose.
Acknowledgements
This work was supported by the National Institutes of Health under award numbers R01NS124206 and RF1AG094791. The content is solely the responsibility of the authors and does not necessarily represent the official views of the National Institutes of Health. Figure 4 is created with BioRender.com.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 30 G x 1 in. Hypodermic Needle with Plastic Hub | Exel | 26439 | |
| 50 µL, Gastight Syringe, Luer Tip (LT) | Hamilton | 80901 | |
| Anatomical Narrow Forceps | Fine Science Tools | 11003-12 | |
| Artificial CSF | TOCRIS | 3525 | |
| Attane Isofluran 1000 mg/g | ScanVet | 55226 | |
| Copper Capillary Tube 0.32 mm OD × 0.16 mm ID | Nippon Tokushukan Mfg. Co., Ltd. | C1220-11-109 | |
| Copper Clip | IEUYO | FEBA 1801 | |
| Cotton Swab | Puritan | 868-WCS | |
| Dotarem (gadoterate meglumine) Injection, 0.5 mmol/mL | Guerbet | NDC 67684-2001-1 | |
| Drill | Foredom | Model SR | |
| Drill Bit | Fine Science Tools | 19007-05 | |
| Drill Holder | Stoelting | 51630 | |
| Dumont Medical Forceps | Fine Science Tools | 11252-00, 11253-20 | |
| Eye Ointment | Rugby | NDC 0536 | |
| E-Z Anesthesia EZ-7000 Classic System | E-Z Systems | EZ-7000 | |
| Graefe Forceps | Fine Science Tools | 11052-10,11152-10 | |
| Heating Pad | Braintree Scientific | 5381 | |
| High Temperature Cautery Kit | Fine Science Tools | 18010-00 | |
| Ketaminol Vet 100 mg/mL (ketamine) | Intervet International BV | 511519 | |
| KWIK-SIL Silicone Adhesive, Low Toxicity, Kit | World Precision Instruments | KWIK-SIL | |
| Needle 5/8 in. single use, sterile, 26 G | BD | 305115 | |
| Polyethylene Tubing 0.61 mm OD × 0.28 mm ID | Scandidact | SKU252 | |
| Rompin Vet 20 mg/mL (xylazine) | KVP Pharma + Veterinär Produkte GmbH | 148999 | |
| Scalpel Blades | Fine Science Tools | 10023-00 | |
| Scissors | Fine Science Tools | 91460-11, 14007-14 | |
| Spatula | Fine Science Tools | 10090-13 | |
| Stereotaxic Frame | Stoelting | 51600U | |
| Surgical Needle Holder | AgnTho’s | 12502-12 | |
| Syringe Pump | New era pump system | NE-4000 | |
| Xylocain 20 mg/mL (lidocaine) | AstraZeneca | 158543 |
References
- Balasubramanian V. Brain power. Proc Natl Acad Sci U S A. 2021;118:e2107022118.
- Mattson MP, Arumugam TV. Hallmarks of brain aging: adaptive and pathological modification by metabolic states. Cell Metab. 2018;27:1176-1199.
- Iliff JJ, Wang M, Liao Y, Plogg BA, Peng W, Gundersen GA, et al. A paravascular pathway facilitates CSF flow through the brain parenchyma and the clearance of interstitial solutes, including amyloid β. Sci Transl Med. 2012;4. doi:10.1126/scitranslmed.3003748.
- Nedergaard M. Garbage truck of the brain. Science. 2013;340:1529-1530.
- Benveniste H, Lee H, Volkow ND. The glymphatic pathway: waste removal from the CNS via. cerebrospinal fluid transport. Neuroscientist. 2017;23:454-465.
- Mestre H, Hablitz LM, Xavier AL, Feng W, Zou W, Pu T, et al. Aquaporin-4-dependent glymphatic solute transport in the rodent brain. eLife. 2018;7:e40070.
- Iliff JJ, Lee H, Yu M, Feng T, Logan J, Nedergaard M, et al. Brain-wide pathway for waste clearance captured by contrast-enhanced MRI. J Clin Invest. 2013;123:1299-1309.
- Benveniste H, Lee H, Ozturk B, Chen X, Koundal S, Vaska P, et al. Glymphatic cerebrospinal fluid and solute transport quantified by MRI and PET imaging. Neuroscience. 2021;474:63-79.
- Eide PK, Ringstad G. MRI with intrathecal MRI gadolinium contrast medium administration: a possible method to assess glymphatic function in human brain. Acta Radiol Open. 2015;4:2058460115609635.
- Ringstad G, Valnes LM, Dale AM, Pripp AH, Vatnehol SAS, Emblem KE, et al. Brain-wide glymphatic enhancement and clearance in humans assessed with MRI. JCI Insight. 2018;3:e121537.
- Eide PK, Ringstad G. Functional analysis of the human perivascular subarachnoid space. Nat Commun. 2024;15:2001.
- Xavier ALR, Hauglund NL, von Holstein-Rathlou S, Li Q, Sanggaard S, Lou N, et al. Cannula implantation into the cisterna magna of rodents. J Vis Exp. 2018;(135):57378.
- Gahn-Martinez D, Giannetto MJ, Chang E, Beam N, Tobin P, Plá V, et al. Chronic intraventricular cannulation for the study of glymphatic transport. eNeuro. 2025;12:ENEURO.0537-24.2025.
- Decker Y, Müller A, Proulx ST. Contrast agent clearance dynamics and diffusion in the mouse brain after ventricular administration. Adv Sci (Weinh). 2025;12:2501502.
- Zhu Y, Zhu J, Ni C, Chen A, Li L, Gao Y, et al. Impact of infusion conditions and anesthesia on CSF tracer dynamics in mouse brain. Fluids Barriers CNS. 2026;23:23.
- DeVos SL, Miller TM. Direct intraventricular delivery of drugs to the rodent central nervous system. J Vis Exp. 2013;(75):50326.
- Ding G, Chopp M, Li L, Zhang L, Davoodi-Bojd E, Li Q, et al. MRI investigation of glymphatic responses to Gd-DTPA infusion rates. J Neurosci Res. 2018;96:1876-1886.
- Stanton EH, Persson NDÅ, Gomolka RS, Lilius T, Sigurðsson B, Lee H, et al. Mapping of CSF transport using high spatiotemporal resolution dynamic contrast-enhanced MRI in mice: effect of anesthesia. Magn Reson Med. 2021;85:3326-3342.
- Berger ML, Reither H, Schmid RW, Lassmann H. Manufacture and use of fused silica cannulas for intracerebral injections in freely moving rats. J Neurosci Methods. 1989;27:225-234.
- Zhang J, Tian W, Chen J, Yu J, Zhang J, Chen J. The application of polyetheretherketone (PEEK) implants in cranioplasty. Brain Res Bull. 2019;153:143-149.
- Plá V, Bork P, Harnpramukkul A, Olveda G, Ladrón-de-Guevara A, Giannetto MJ, et al. A real-time in vivo. clearance assay for quantification of glymphatic efflux. Cell Rep. 2022;40:111320.
- Benveniste H, Lee H, Ding F, Sun Q, Al-Bizri E, Makaryus R, et al. Anesthesia with dexmedetomidine and low-dose isoflurane increases solute transport via. the glymphatic pathway in rat brain when compared with high-dose isoflurane. Anesthesiology. 2017;127:976-988.
- Chiu C, Miller MC, Caralopoulos IN, Worden MS, Brinker T, Gordon ZN, et al. Temporal course of cerebrospinal fluid dynamics and amyloid accumulation in the aging rat brain from three to thirty months. Fluids Barriers CNS. 2012;9:3.
- Karimy JK, Kahle KT, Kurland DB, Yu E, Gerzanich V, Simard JM. A novel method to study cerebrospinal fluid dynamics in rats. J Neurosci Methods. 2015;241:78-84.
Reprints and Permissions
This article has been published
Video Coming Soon