An exploratory machine-learning (ML) framework using perioperative data was evaluated to predict contrast-induced encephalopathy (CIE) after neurointerventional procedures. The Naive Bayes model showed the most balanced descriptive performance, and contrast-to-eGFR ratio (CGR) was identified as an important candidate predictor for individualized risk assessment.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Machine-Learning Prediction of Contrast-Induced Encephalopathy After Neurointerventional Procedures
* These authors contributed equally
In This Article
Summary
Abstract
CIE is a rare yet severe complication following neurointerventional procedures, for which reliable noninvasive predictive tools remain lacking. This study aimed to develop and validate a ML model for predicting CIE using perioperative clinical and procedural data, and to evaluate the predictive value of the CGR for CIE. This was a single-center retrospective study that consecutively enrolled 161 patients who underwent neurointerventional procedures in the Department of Neurosurgery at the Northern Theater General Hospital between January 2024 and December 2025. Candidate perioperative predictors of CIE were identified using univariate analysis combined with LASSO regression. Based on the selected variables, five ML models—Naive Bayes, support vector machine (SVM), k-nearest neighbors (KNN), LightGBM, and multilayer perceptron (MLP)—were trained and optimized. Model performance was comprehensively evaluated using the area under the receiver operating characteristic curve (AUC), and decision curve analysis (DCA). Among the evaluated models, the Naive Bayes model showed the most favorable descriptive performance in the internal test set, with an AUC of 0.952 (95% CI: 0.843–1.000), a sensitivity of 100%, and a specificity of 90.3%; however, these metrics should be interpreted cautiously because the dataset was markedly imbalanced and the internal test cohort was small and contained only a very limited number of CIE events. The DCA results suggested potential clinical net benefit across selected threshold probabilities. Feature-importance analysis indicated that CGR was among the highest-ranked candidate predictors associated with CIE risk in this dataset. The Naive Bayes model evaluated in this study may provide a preliminary risk-stratification framework for perioperative assessment of CIE after neurointerventional procedures. CGR emerged as an important predictive feature and may aid individualized risk stratification. Further external validation is warranted before clinical application.
Introduction
Over the past two decades, minimally invasive interventional techniques have fundamentally transformed the treatment paradigm for cerebrovascular diseases1. Neurointerventional procedures—with their advantages of high efficacy and minimal invasiveness—have become important treatment options for selected cerebrovascular disorders2. However, as the complexity of interventional procedures increases, so do the doses of contrast agents used during procedures, the injection pressures, and the duration of contrast-agent exposure. Consequently, contrast-agent–related complications have gradually come under increasing scrutiny3,4,5,6,7. CIE, an acute, transient neurological dysfunction induced by iodinated contrast media (ICM), has been increasingly recognized as a clinically relevant complication, particularly in complex neurointerventional procedures. The typical clinical manifestations of CIE usually appear within minutes to 24 h after contrast-agent exposure and include alterations in consciousness (such as somnolence, delirium, or coma), cortical blindness, focal neurological deficits (such as hemiparesis or aphasia), and seizures4,5,6. Although most cases of CIE are self-limiting and symptoms typically resolve within 48 to 72 h, some patients may experience persistent neurological impairment. Severe cases may even lead to death due to massive cerebral edema4,7. This unpredictability of outcomes underscores the urgent need to develop a reliable tool for early risk prediction during the perioperative period.
As the volume of clinical data continues to increase, traditional statistical methods are increasingly inadequate when dealing with high-dimensional medical data that exhibit multicollinearity. Moreover, univariate analyses or simple logistic regression models often fail to capture the complex, nonlinear interactions among variables. ML offers a new dimension for addressing these challenges8. ML algorithms—such as SVM, gradient boosting machines (LightGBM), and MLP—can automatically identify latent patterns in high-dimensional feature spaces and construct nonlinear models with powerful predictive capabilities8,9,10,11. However, while pursuing prediction accuracy, the “black-box” nature of these algorithms, characterized by their lack of interpretability, often raises concerns regarding trust in medical decision-making12,13. In contrast, the Naive Bayes algorithm, with its simple probabilistic logic and inherent interpretability, demonstrates unique advantages in small-sample clinical studies14,15. By evaluating the posterior probability contribution of each predictor variable to the outcome event, the Naive Bayes model not only ensures predictive performance but also provides clinicians with intuitive decision support insights. Furthermore, to quantitatively assess the imbalance between contrast agent load and individual clearance capacity, this study innovatively introduces the contrast agent-to-eGFR ratio (CGR) as a core feature. For patients with lower renal functional reserve, even moderate doses of contrast agents can result in extremely high CGR values, which may increase susceptibility to CIE. CGR may provide a clinically intuitive composite measure integrating contrast-agent burden and renal-clearance capacity, although its incremental predictive value requires further validation. By incorporating this integrated biomarker, this study aimed to develop a predictive framework that more closely reflects the pathophysiological reality.
In summary, this study aimed to develop and validate an ML-based CIE prediction model using perioperative clinical and procedural variables16. The specific objectives include: (1) introducing and evaluating CGR as an exploratory composite index; (2) constructing and comparing the performance of five ML models—Naive Bayes, SVM, KNN, LightGBM, and MLP; and (3) identifying the optimal model. Given the limited number of CIE events, the model comparison was considered exploratory and hypothesis-generating. Ultimately, this study may provide a preliminary risk-stratification framework for CIE in neurointerventional practice, but it should not be used as a standalone clinical decision-making tool without external validation. The conceptual basis of CGR and its relationship with contrast exposure and renal clearance are illustrated in Figure 1A. The overall study workflow, including data preprocessing, train/test splitting, feature selection, and model development, is summarized in Figure 1B. The comparative evaluation framework of the five ML models is presented in Figure 1C.
Access restricted. Please log in or start a trial to view this content.
Protocol
The study protocol was reviewed and approved by the Ethics Committee of the General Hospital of Northern Theater Command (Approval No. Ethics Y (2026) 75). Although the clinical data were derived from patients treated between January 2024 and December 2025, the present study was conducted as a retrospective analysis of existing clinical records. The ethics approval obtained in 2026 covered retrospective data extraction, de-identification, analysis, and publication of these previously collected clinical data. No prospective intervention or patient enrollment was performed before ethics approval. The requirement for written informed consent was waived because of the retrospective observational study design. All procedures were conducted in accordance with the Declaration of Helsinki, and all clinical data were de-identified before analysis. The present analysis was conducted as part of an approved retrospective neurointerventional clinical-data research project. The materials and equipment required for the procedures described below are summarized in the Table of Materials.
Patient enrollment and CIE determination
Potentially eligible patients were identified by querying the electronic medical record system for patients treated in the Department of Neurosurgery at the General Hospital of Northern Theater Command between January 2024 and December 2025. The initial search was restricted by admission date, department, cerebrovascular disease diagnosis, and neurointerventional procedure records. The detailed patient screening and cohort allocation workflow is illustrated in Figure 2. Patients were eligible for inclusion if they met all the following criteria: (1) age between 30 and 80 years; (2) diagnosis of cerebrovascular disease requiring neurointerventional evaluation or treatment; (3) availability of complete clinical records and laboratory-test results; and (4) postoperative head CT examination performed within 3 days after surgery.
Patients were excluded if they had incomplete clinical or imaging data, did not undergo endovascular intervention, had severe preoperative neurological deficits (modified Rankin Scale score ≥4), demonstrated acute cerebral infarction on preoperative diffusion-weighted imaging, had chronic kidney disease stage G4 or higher according to the Kidney Disease: Improving Global Outcomes (KDIGO) criteria, or had severe cardiovascular disease. The inclusion and exclusion criteria were applied sequentially. After the initial electronic search, each candidate record was manually reviewed to confirm eligibility and to document the reason for exclusion when applicable. After screening, eligible patients were randomly assigned to training and test cohorts at an 8:2 ratio, including a training cohort (n = 128) and a test cohort (n = 33). Stratified random sampling was used to maintain a consistent distribution of CIE and non-CIE cases between the two cohorts.
The diagnosis of CIE was primarily based on the temporal association between symptom onset and cerebrovascular intervention procedures, combined with exclusionary imaging assessment. Two independent cerebrovascular intervention specialists reviewed the postoperative clinical records, symptom-onset time, neurological manifestations, and postoperative imaging findings for all suspected cases. Disagreements were resolved through discussion until consensus was reached. Patients were considered compatible with CIE if newly developed cortical blindness, altered consciousness (including somnolence, delirium, or coma), seizure, or focal neurological deficits such as hemiparesis or aphasia occurred within 24 h after completion of the neurointerventional procedure.
After symptom onset, alternative causes capable of producing similar neurological manifestations were excluded by reviewing postoperative CT or MRI images together with the clinical course. Postoperative head CT was performed using the institutional standard non-contrast cranial CT protocol. The essential acquisition parameters included tube voltage of 80 kVp, tube current of 260 mA, slice thickness of 0.5 mm, and standard axial reconstruction. Images were reviewed on brain and bone windows by experienced clinicians. Acute intracranial hemorrhage, subarachnoid hemorrhage, intracerebral hemorrhage, newly developed large-area cerebral infarction, seizure-related changes, infection, and metabolic disturbances were considered during differential diagnosis. Post-symptom CT examinations typically demonstrated focal or diffuse cerebral edema and high-density shadows involving the cortex, subcortical regions, or subarachnoid space, mimicking hemorrhagic lesions. MRI findings usually demonstrate cortical swelling, particularly involving the temporoparietal occipital cortex. In some patients, however, CT or MRI examinations showed no obvious abnormalities despite compatible clinical manifestations.
Perioperative variable acquisition and CGR construction
General demographic data, including age, sex, and body weight, were extracted from structured fields in the electronic medical record system. Clinical history variables, including smoking history, alcohol consumption history, hypertension, diabetes mellitus, and coronary heart disease, were extracted from admission notes, past medical history records, and discharge diagnoses, and were cross-checked for consistency. Laboratory data were extracted from the laboratory information system. For each patient, the first venous blood sample collected after admission and before the neurointerventional procedure was used. The extracted laboratory variables included serum creatinine, estimated glomerular filtration rate (eGFR), total cholesterol, and triglyceride levels. eGFR was calculated using the Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) creatinine-based equation and was obtained from the hospital laboratory information system.
Because procedural complexity, contrast-agent exposure, and lesion location may influence blood–brain barrier disruption and contrast-agent retention during neurointerventional procedures, perioperative procedural variables were also incorporated into the predictive framework. Procedure-related variables included lesion location, procedure type, procedural duration, contrast-agent type, and total contrast volume. Lesion location and procedure type were determined from operative reports and angiographic records. Procedural duration was defined as the time from arterial puncture to completion of the neurointerventional procedure. Total contrast volume was defined as the cumulative volume of iodinated contrast agent administered from the beginning to the end of the procedure. The contrast agents used in this study were nonionic ICA, including iodixanol (320 mg of iodine/mL), administered according to institutional clinical practice. All neurointerventional procedures included in this study were performed under digital subtraction angiography guidance by an experienced neurointerventional team at the study center. All procedures were performed using the transfemoral arterial approach. During the intervention, patients received intraoperative anticoagulation with heparin, and activated clotting time was maintained within the target range of 250–300 s. Vital signs were continuously monitored throughout the procedure.
Therapeutic interventions, including aneurysm embolization, angioplasty, and stent placement, were performed according to lesion characteristics and operator judgment. Appropriate microcatheters, coils, stents, or balloons were selected according to procedural requirements. During angiographic imaging and intervention, contrast agents were administered either through high-pressure injection or manual constant-rate infusion. Contrast agent type and total contrast volume were extracted from procedural records and cross-checked with anesthesia or nursing records when available. Records with inconsistent or incomplete contrast-volume information were reviewed manually before inclusion in the final analytical dataset.
All procedure-related variables, including procedural duration, therapeutic intervention type, device usage, and contrast-agent administration records, were systematically reviewed and verified for completeness and consistency before analysis. To quantitatively evaluate the imbalance between contrast-agent burden and renal-clearance capacity, the CGR was established as a core predictive variable and calculated according to the following equation:
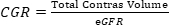 (1)
The total contrast volume was recorded in mL, and eGFR was recorded in mL/min/1.73 m2. The eGFR value used for CGR calculation was the preoperative eGFR value obtained from the first venous blood sample collected after admission and before the neurointerventional procedure. For each patient, CGR was calculated after verifying both total contrast volume and eGFR. The numerator was total contrast volume in mL, and the denominator was eGFR in mL/min/1.73 m2. The same calculation rule was applied to all patients before model development.
Feature selection and ML workflow
To ensure analytical robustness, all clinical and laboratory variables underwent systematic quality control procedures before analysis. The missing data proportion was calculated for each candidate variable before model development. In the final analytical dataset, no missing values were observed among the included predictors or outcome labels; therefore, no variable was excluded because of missingness, and multiple imputation was not required. The detailed missing data summary is provided in Supplementary Table 1.
All candidate predictor variables were initially evaluated using univariate analyses to assess their associations with the occurrence of CIE. Statistical methods were selected according to the distribution characteristics of the data. Variables with normal distribution were expressed as mean ± standard deviation and compared using the independent samples t-test. Variables with non-normal distribution were expressed as median (interquartile range, IQR) and analyzed using the Mann–Whitney U test. Categorical variables were presented as frequencies and percentages and analyzed using the chi-square test or Fisher’s exact test. Statistical significance was defined as p < 0.05.
The entire dataset was randomly divided into training and test cohorts at an 8:2 ratio before model development. To minimize overfitting and reduce multicollinearity, least absolute shrinkage and selection operator (LASSO) regression combined with 10-fold cross-validation was applied for feature selection. Feature selection, hyperparameter tuning, and model development were performed using the training cohort only to avoid data leakage. The internal test cohort was not used during imputation-parameter estimation, feature selection, hyperparameter tuning, or model training, and was used only once for final performance evaluation. Hyperparameter optimization was conducted using a grid search strategy with 10-fold cross-validation within the training cohort. Specifically, the training cohort was randomly divided into 10 mutually exclusive subsets. During each iteration, nine subsets were used for model training, and the remaining subset was used for validation. This process was repeated 10 times to ensure that each subset served as the validation cohort exactly once.
All computational analyses were performed in a Python environment. ML model development and evaluation were performed using scikit-learn. The analysis scripts used for data preprocessing, feature selection, model training, performance evaluation, and DCA were provided as supplementary code files. For model implementation, the selected features from LASSO regression were used as input variables for all candidate classifiers. Continuous variables were standardized using z-score normalization within the training cohort, and the same scaling parameters were applied to the internal test cohort. Categorical variables were encoded according to the predefined coding scheme, and the variable definitions and coding scheme are provided in Supplementary Table 2. Five classifiers were implemented: Gaussian Naive Bayes, SVM, KNN, LightGBM, and MLP. For SVM, the kernel type, regularization parameter C, and kernel coefficient gamma were tuned. For KNN, the number of neighbors and the distance-weighting strategy were tuned. For LightGBM, the number of estimators, learning rate, maximum tree depth, and number of leaves were tuned. For MLP, the hidden-layer structure, activation function, regularization parameter, and learning rate were tuned. Gaussian Naive Bayes was implemented using the specified variance smoothing setting. The optimal hyperparameter combination for each model was selected according to cross-validation performance within the training cohort. The final optimized hyperparameter combinations selected for each model are summarized in Supplementary Table 3. After hyperparameter selection, each final model was refitted on the full training cohort and evaluated once in the internal test cohort.
Comparisons of model performance
Based on the selected predictors, five ML models were developed and compared. Model performance was evaluated in both the training and test cohorts using the area under the receiver operating characteristic curve (AUC), 95% confidence interval (95% CI), sensitivity, specificity, and accuracy. Receiver operating characteristic curves were generated to compare the discriminative performance of the different models. The optimal classification threshold for each model was determined exclusively within the training cohort using the Youden index. The derived threshold was then fixed and applied unchanged to the internal test cohort for calculating threshold-dependent performance metrics.
Decision curve analysis
DCA was performed by calculating the net benefit of each model across a range of threshold probabilities and comparing the model-based strategy with two default strategies: treating all patients and treating no patients. DCA was selected because it allows simultaneous assessment of discrimination performance and potential clinical applicability in perioperative decision-making settings. To facilitate reproducibility, the complete workflow was performed in the following sequence: patient identification from the electronic medical record system, application of inclusion and exclusion criteria, CIE adjudication by two independent specialists, extraction and cross-checking of demographic, clinical history, laboratory, and procedure-related variables, CGR calculation, missing-data assessment and training-test cohort split, LASSO-based feature selection within the training cohort, hyperparameter tuning by 10-fold cross-validation, final model refitting in the full training cohort, internal test-cohort evaluation, ROC-based performance assessment, Youden-index threshold determination, and DCA.
Access restricted. Please log in or start a trial to view this content.
Results
Patient enrollment and CIE determination
A total of 161 patients who underwent neurointerventional procedures were included in this study, among whom 12 (7.5%) developed CIE, while 149 (92.5%) did not. The detailed patient screening and grouping process is shown in Figure 2. The diagnosis of CIE was established based on the temporal association between symptom onset and neurointerventional procedures, combined with exclusionary imaging findings. R...
Access restricted. Please log in or start a trial to view this content.
Discussion
CIE is a rare but potentially serious complication following neurointerventional procedures, characterized by acute neurological dysfunction that occurs shortly after exposure to contrast agents. Although the condition is typically reversible, in some cases it can lead to persistent neurological deficits or even life-threatening outcomes, underscoring the importance of early risk identification17,18,19,
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors declare no competing interests. The OnekeyAI platform was used solely as a research tool for structured data analysis and model development in this study.
Acknowledgements
This work was supported by the Liaoning Provincial Science and Technology Plan Joint Program (Key Research and Development Program Project; Grant No. 2025JH2/101800053) and the Xingliao Talent Program of Liaoning Province (Grant No. XLYC2403134). The authors also acknowledge the support of the Department of Neurosurgery, Northern Theater General Hospital, in patient-data collection and neuroimaging review.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Electronic medical-record system | Northern Theater General Hospital | Institutional clinical system | Used for retrospective data extraction Collection of demographic and clinical-history variables |
| Laboratory information system | Northern Theater General Hospital | Institutional laboratory system | Used for retrospective laboratory-data extraction Collection of serum creatinine, eGFR, lipid profile, and other laboratory data |
| Digital subtraction angiography system | Philips | Allura Xper FD 20 (with Interventional Workstation R1.3.2) | Used during routine clinical procedures Neurointerventional procedure and recording of contrast use |
| CT Scanner | Philips | Ingenuity CT | Used for postoperative imaging assessment Postoperative cranial CT evaluation |
| OnekeyAI structured-data analysis platform | OnekeyAI | 20240916 | Used as a research tool; no role in clinical decision-making Structured-data preprocessing, model construction, model evaluation, and figure generation |
| Python | Python Software Foundation | 3.7.12 | Open-source programming language Data preprocessing, statistical analysis, model development, and visualization |
| scikit-learn | scikit-learn developers | 1.0.2 | Open-source Python machine-learning library LASSO, Naive Bayes, SVM, KNN, MLP, ROC analysis, and performance metrics |
References
- Nunna R, et al. Advances in the endovascular management of cerebrovascular disease. Mo Med. 2024;121:127-135.
- Jiang B, et al. Cerebral aneurysm treatment: modern neurovascular techniques. Stroke Vasc Neurol. 2016;1:93-100.
- Allison C, et al. Contrast-induced encephalopathy after cerebral angiogram: a case series and review of literature. Case Rep Neurol. 2021;13:405-413.
- Vazquez S, et al. Incidence and risk factors for acute transient contrast-induced neurologic deficit: a systematic review with meta-analysis. Stroke Vasc Interv Neurol. 2022;2:e000142.
- Meijer FJA, et al. Contrast-induced encephalopathy: neuroimaging findings and clinical relevance. Neuroradiology. 2022;64:1265-1268.
- Quintas-Neves M, et al. Contrast-induced neurotoxicity related to neurological endovascular procedures: a systematic review. Acta Neurol Belg. 2020;120:1419-1424.
- Mariajoseph FP, et al. Clinical management of contrast-induced neurotoxicity: a systematic review. Acta Neurol Belg. 2024;124:1141-1149.
- Deo RC. Machine learning in medicine. Circulation. 2015;132:1920-1930.
- Rajkomar A, Dean J, Kohane IS. Machine learning in medicine. N Engl J Med. 2019;380:1347-1358.
- Kline A, et al. Multimodal machine learning in precision health: a scoping review. NPJ Digit Med. 2022;5:171.
- Esteva A, et al. A guide to deep learning in healthcare. Nat Med. 2019;25(1):24-29.
- Topol EJ. High-performance medicine: the convergence of human and artificial intelligence. Nat Med. 2019;25(1):44-56.
- Agrawal R, et al. Fostering trust and interpretability: integrating explainable AI (XAI) with machine learning for enhanced disease prediction and decision transparency. Diagn Pathol. 2025;20:105.
- Domingos P, Pazzani M. On the optimality of the simple Bayesian classifier under zero-one loss. Mach Learn. 1997;29:103-130.
- Sarker IH. Machine learning: algorithms, real-world applications and research directions. SN Comput Sci. 2021;2:160.
- Collins GS, et al. Transparent reporting of a multivariable prediction model for individual prognosis or diagnosis (TRIPOD): the TRIPOD statement. Br J Cancer. 2015;112(2):251-259.
- Wu B, et al. Radiological findings of contrast-induced encephalopathy following cerebral angiography: a case report. Medicine (Baltimore). 2023;102:e33855.
- Wang K, et al. Contrast-induced encephalopathy after neurointerventional procedures: a series of three cases. Case Rep Neurol Med. 2025;2025:4384841.
- Chu YT, et al. Contrast-induced encephalopathy after endovascular thrombectomy for acute ischemic stroke. Stroke. 2020;51:3756-3759.
- Leong S, Fanning NF. Persistent neurological deficit from iodinated contrast encephalopathy following intracranial aneurysm coiling: a case report and review of the literature. Interv Neuroradiol. 2012;18(1):33-41.
- Hepburn M, et al. Fatal brain injury following carbon dioxide angiography. J Stroke Cerebrovasc Dis. 2020;29:105350.
- Matsubara N, et al. Contrast-induced encephalopathy following embolization of intracranial aneurysms in hemodialysis patients. Neurol Med Chir (Tokyo). 2017;57:641-648.
- Maclean MA, et al. Contrast-induced encephalopathy and the blood-brain barrier. Can J Neurol Sci. 2025;52:85-94.
- Cristaldi PMF, et al. Contrast-induced encephalopathy and permanent neurological deficit: a case report and literature review. Surg Neurol Int. 2021;12:273.
- Babyak MA. What you see may not be what you get: a brief, nontechnical introduction to overfitting in regression-type models. Psychosom Med. 2004;66(3):411-421.
- Zevallos CB, et al. Greater intraprocedural systolic blood pressure and blood pressure variability are associated with contrast-induced neurotoxicity after neurointerventional procedures. J Neurol Sci. 2021;420:117209.
- Zevallos CB, et al. Clinical and imaging features of contrast-induced neurotoxicity after neurointerventional surgery. World Neurosurg. 2020;142:e316-e324.
- Barbieri L, et al. Contrast volume to creatinine clearance ratio for the prediction of contrast-induced nephropathy in patients undergoing coronary angiography or percutaneous intervention. Eur J Prev Cardiol. 2016;23:931-937.
- Bhat T, et al. Neutrophil to lymphocyte ratio and cardiovascular diseases: a review. Expert Rev Cardiovasc Ther. 2013;11:55-59.
- Abbott NJ, Rönnbäck L, Hansson E. Astrocyte-endothelial interactions at the blood-brain barrier. Nat Rev Neurosci. 2006;7(1):41-53.
- Simental-Mendía LE, Rodríguez-Morán M, Guerrero-Romero F. The product of fasting glucose and triglycerides as surrogate for identifying insulin resistance in apparently healthy subjects. Metab Syndr Relat Disord. 2008;6:299-304.
- Spina R, et al. Contrast-induced encephalopathy following cardiac catheterization. Catheter Cardiovasc Interv. 2017;90:257-268.
- Steyerberg EW, et al. Internal validation of predictive models: efficiency of some procedures for logistic regression analysis. J Clin Epidemiol. 2001;54(8):774-781.
Access restricted. Please log in or start a trial to view this content.