This study identifies eight mitotic catastrophe-related prognostic genes (PDGFB, LDHA, ZEB2, H2AX, FKBP4, DMD, ANXA2, S100B) in lung adenocarcinoma, establishes a risk model with acceptable predictive performance, and reveals distinct immune microenvironment characteristics between risk groups.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Identification of Mitotic Catastrophe-related Prognostic Genes in Lung Adenocarcinoma via Transcriptome Analysis
In This Article
Summary
Abstract
Lung adenocarcinoma (LUAD), the most common lung cancer subtype, exhibits a poor prognosis. Although mitotic catastrophe can be induced in LUAD, leading to cell death, the prognostic and biological significance of mitotic catastrophe-related genes (MCRGs) in this disease remains unclear. Differentially expressed genes (DEGs) associated with LUAD were screened from the TCGA-LUAD cohort, and overlapping genes were defined by intersecting DEGs with MCRGs. Candidate prognostic genes were selected via machine learning, after which a multigene prognostic model was constructed. An eight-candidate prognostic signature comprising PDGFB, LDHA, ZEB2, H2AX, FKBP4, DMD, ANXA2, and S100B was established, demonstrating acceptable predictive reliability in training with 2-year, 3-year and 5-year area under the curves (AUCs) of 0.723, 0.715, and 0.625, respectively, in the training set (bootstrap-corrected C-index: 0.699, 95% CI: 0.657-0.742) and consistent validation in GSE31210 (AUCs: 0.812, 0.766, and 0.814). Low-risk patients exhibited significantly better survival outcomes, enhanced immune infiltration, higher immune and stromal scores, increased immunophenoscores, and more active cancer immunity cycles. Significant differences in tumor mutation burden and drug sensitivity were observed between the high- and low-risk groups. Quantitative polymerase chain reaction(qPCR) validated the transcriptomic profiles of six candidate outcome-related genes in clinical samples. A nomogram incorporating the risk score and clinical stage showed good predictive performance. These findings demonstrate that the eight MCRG-related candidate genes have strong potential to predict patient outcomes and stratify risk in LUAD, with distinct immune microenvironment characteristics between risk groups.
Introduction
Lung cancer remains among the most prevalent and deadly cancers worldwide1,2. Non-small cell lung cancer (NSCLC) is dominated by lung adenocarcinoma (LUAD), which accounts for about 40% of all lung cancer cases3,4. Although significant strides have been made in operative procedures, molecularly targeted therapies, immune checkpoint inhibitors, and combination regimens, the clinical outlook for LUAD patients remains unfavorable5,6. Although pathological and imaging-based diagnostic approaches are widely used in LUAD, they have inherent limitations in capturing tumor heterogeneity and molecular characteristics. In contrast, molecular biomarker-based tumor tissue analysis can provide more comprehensive information on tumor biology and may contribute to prognostic assessment and individualized treatment strategies7. Therefore, identifying reliable molecular biomarkers remains important for improving prognostic prediction and biological understanding of LUAD.
Mitosis, an essential mechanism of cellular replication, guarantees the faithful partitioning of replicated chromosomes between two daughter cells8. Dysregulation of mitotic processes can promote uncontrolled cell proliferation, genomic instability, and tumor progression. Mitotic catastrophe (MC) defines a cell death pathway triggered upon failure of mitosis completion, typically resulting from spindle apparatus damage or defective cell cycle checkpoints9. At the morphological level, MC presents with cellular abnormalities including multinucleation, micronuclei, multipolar spindle configurations, and polyploidization10. As a mechanism for eliminating cells with severe mitotic defects, MC may contribute to the suppression of tumor progression9. The p53 deletion in A549 LUAD cells can induce mitotic catastrophe and ultimately cell death11, implying a potential link between MC and LUAD-related cellular processes. Nevertheless, the prognostic significance and biological functions of MC-related genes (MCRGs) in LUAD remain poorly elucidated.
In this research, the prognostic importance and putative biological relevance of MCRGs in LUAD were systematically interrogated utilizing data from TCGA and GEO. Candidate MCRGs were first identified through differential expression and intersection analyses. Multiple machine learning approaches screened candidate genes and established a prognostic risk signature, which was subsequently externally validated. A nomogram incorporating the risk score in conjunction with clinical characteristics was further developed to improve survival prediction. In addition, immune microenvironment characterization, somatic mutation assessment, and chemosensitivity evaluation served to examine the biological implications and clinical utility of the identified genes. Collectively, these findings demonstrate the prognostic potential of MCRGs in LUAD and may inform biomarker development and individualized management.
Access restricted. Please log in or start a trial to view this content.
Protocol
The study was conducted in accordance with the Declaration of Helsinki, and the protocol was approved by the Ethics Committee of Anhui Chest Hospital (K2025-007) on 22 April 2025. Informed consent was obtained from all subjects involved in the study.
Data extraction and normalization
Transcriptomic profiles and corresponding clinical datasets for LUAD were sourced from the TCGA and GEO cohorts. The TCGA-LUAD dataset was designated as the training set, with GSE72094, GSE31210, and GSE26939 serving as cohorts for external validation (Table 1). In addition, 900 MCRGs were collected from a previous study12(Supplementary Table 1). Transcriptome data were annotated using GENCODE v36 or the corresponding GPL platform annotation files. Probe IDs were converted into gene symbols, duplicated genes were merged using the avereps function, and only protein-coding genes were retained to generate gene-level expression matrices. For the TCGA-LUAD training set, genes with Fragments per kilobase of exon model per million mapped fragments (FPKM) < 1 in more than 50% of samples were filtered out, and the remaining expression values were log2 transformed (log2[FPKM+1]). For the GEO validation cohorts, raw expression data were downloaded, probe IDs were mapped to gene symbols using the respective platform annotation files, and multiple probes corresponding to the same gene collapsed by averaging their expression values. These datasets were log2-transformed when necessary. No cross-platform batch effect correction was applied between TCGA and GEO, as we adopted a per-cohort standardization strategy to ensure relative comparability. Specifically, for both the training and validation cohorts, gene expression values were centered and scaled (z-score transformation) using the mean and standard deviation of each dataset individually. The same Cox regression coefficients derived from the training set were then used to calculate risk scores for all cohorts. To maintain clinical applicability and avoid overfitting to any validation set, the median risk score of the training cohort was employed as a fixed cut-off to stratify patients into high and low-risk groups across all external validation cohorts. Clinical information, including age, sex, pathological stage, Tumor-Node-Metastasis (TNM) stage, histological type, survival time, survival status, and tissue type, was extracted when available. The endpoint was overall survival (OS). Samples with incomplete survival information or survival time < 30 days were excluded. Survival time was converted into years, and survival status was coded as 0 for alive and 1 for dead.
Identification and functional analyses of candidate genes
The Limma package identified differentially expressed genes (DEGs) between LUAD tumor and normal samples in the training set13. The following criteria defined DEGs: |log2FC| > 0.5 and adjusted p-value < 0.05. Subsequently, the mfuzz fuzzy clustering algorithm in the R package ClusterGVis was utilized to partition DEGs into distinct expression clusters. Gene Ontology–Biological Process (GO-BP) analysis was completed on the top five representative genes in each cluster based on their membership scores. A set of shared genes was derived by taking the intersection of DEGs with MCRGs. Functional enrichment analysis using Gene Ontology/Kyoto Encyclopedia of Genes and Genomes (GO/KEGG) assessed the biological relevance of overlapping genes. Protein–protein interaction (PPI) networks originated from the STRING database14. Only interactions with confidence scores > 0.7 remained to improve network reliability.
Prognostic genes screening
The Survival package was used to conduct an univariate Cox regression analysis to identify probable genes linked to overall survival in LUAD15. Genes with p-value < 0.05 were considered potential prognostic indicators. The TCGA-LUAD training cohort included 500 patients with complete survival data, among whom 216 (43.2%) experienced death events during follow-up. The ratio of candidate genes (n = 108) to events (n = 216) was approximately 1:2, which is acceptable for Cox regression analysis. Subsequently, Least Absolute Shrinkage and Selection Operator (LASSO) regression analysis and Extreme Gradient Boosting (XGBoost) model further selected features. Cox proportional hazards models were built with family = "cox" via the cv.glmnet function of the glmnet package. The optimal regularization parameter was identified using 10-fold cross-validation, with λ.min value representing the minimum cross-validation error, which was selected as optimal λ value. Genes with non-zero regression coefficients were extracted as candidate features. For the XGBoost model, survival time and survival status were combined as the outcome variable, with positive values assigned to death events and negative values assigned to censored cases. The parameters were set as objective = "survival: cox" and eval_metric = "cox-nloglik", with 100 iterations and a learning rate of 0.1. After model training, gene importance scores were calculated using feature gain values. The top 20 genes were retained after sorting the importance scores in descending order to reduce feature dimensionality and model complexity. Genes overlapping between the LASSO and XGBoost results were identified as candidate prognostic genes.
Construction and assessment of a prognostic model
A prognostic model was developed using multivariate Cox regression analysis of the identified candidate genes. Risk scores were individually computed as follows:
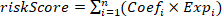 .
where Coefi refers to the coefficient for gene i, and Expi indicates the respective gene expression value. Individuals were subsequently divided into two groups: high-risk and low-risk, using the median risk score as the cutoff. Then, time-dependent receiver operating characteristic (ROC) curves were created. To assess the potential for overfitting, bootstrap internal validation with 1,000 resampling iterations was performed to calculate bias-corrected C-index and time-dependent AUCs with 95% confidence intervals. Calibration curves were generated to evaluate the agreement between predicted and observed survival probabilities at 2 years, 3 years, and 5 years. Furthermore, decision curve analysis (DCA) was performed using the ggDCA package in R to evaluate the clinical net benefit of the model at 2, 3 and 5 year time points, quantifying the potential value of the risk score in clinical decision-making across different threshold probabilities. Survival disparities between risk-stratified groups and across other clinical categories, were compared using Kaplan–Meier(KM) survival curves with log-rank testing. Furthermore, elucidating individual gene contributions to the model performance employed Shapley Additive exPlanations (SHAP) analysis for post-hoc explanatory interpretation.
Nomogram development and external validation
The relationships between the calculated risk scores and various clinical features (including gender, age, and TNM stage) were examined using Wilcoxon rank-sum or Kruskal-Wallis tests to evaluate the model's clinical applicability. To assess whether the risk score functioned as an independent prognostic factor, clinical variables, along with the risk score, were incorporated into multivariate Cox regression modeling. Then, a prognostic nomogram combining the independent clinical risk factors (e.g., Stage) and the genetic risk score constructed through the regplot R package to individualize survival probability predictions. Calibration curves were used to assess agreement of the nomogram-predicted survival probability with actual survival outcomes. Finally, the ultimate predictive capacity and generalizability of the integrated nomogram system were rigorously validated through time-dependent ROC curves and comprehensive KM clinical subgroup analyses across the cohorts.
Immune infiltration and immune subtype analyses
CIBERSORT, using the leukocyte gene (LM22) signature matrix, was used to estimate the relative proportions of 22 immune cell types to assess immune cell infiltration in LUAD patients. The relationships between prognostic gene expression levels and immunological infiltration were evaluated by Spearman correlation analysis. Immune, stromal, tumor purity, and ESTIMATE scores were derived via the ESTIMATE algorithm, and the Wilcoxon test assessed differences across risk groups. LUAD patients were assigned to six immune subtypes using the ImmuneSubtypeClassifier package16. Wilcoxon test was additionally used to compare immune subtype distributions across risk groups.
Immune checkpoint, immunophenoscore, and cancer immunity cycle analyses
In this study, the Wilcoxon rank-sum test served to assess 21 immune checkpoint genes17 across risk-stratified groups, aiming to characterize the LUAD immune landscape. Spearman correlation linked candidate prognostic genes to immune checkpoint genes. To assess differences in response to immune checkpoint inhibitors (ICIs) in LUAD patients at different risk levels, immunophenoscore (IPS) data for anti-PD-1 and anti-CTLA-4 treatments were obtained from The Cancer Immunome Atlas (TCIA)18, and the Tracking Tumor Immunophenotype (TIP)19 database was used to evaluate cancer-immunity cycle activity, comparing corresponding scores between risk groups.
Somatic mutation and drug sensitivity analysis
The TCGA mutations tool retrieved somatic mutation profiles for TCGA-LUAD cases to investigate variation in mutation patterns across risk groups. The maftools package processed and visualized mutation data. Tumor mutation burden (TMB) levels were determined for each specimen and contrasted between the two risk categories. Pharmacogenomic sensitivity analysis was conducted using the pRRophetic package according to the Genomics of Drug Sensitivity in Cancer(GDSC) database20. Half-maximal inhibitory concentration (IC50) values for anticancer drugs were predicted for each LUAD patient, and risk-group differences were quantified using the Wilcoxon rank-sum test.
Evaluation of expression levels for prognostic genes
Each dataset served to assess transcript levels of selected candidate outcome-related genes. To link gene expression with patient prognosis, optimal cutoffs were derived via the surv_cutpoint function in the survminer R package. Based on these thresholds, LUAD cases were categorized into high- and low-expression subsets for subsequent survival analysis.
Furthermore, five matched LUAD tumors and adjacent normal tissue pairs were obtained from Anhui Chest Hospital and qPCR validation was subsequently performed. Every participant provided written informed permission. Six candidate prognostic genes (PDGFB, LDHA, ZEB2, FKBP4, DMD, and S100B) were selected for qPCR validation. RNA was extracted from homogenized tissue samples using RNA extraction reagent, followed by chloroform extraction and isopropanol precipitation. The spectrophotometer enabled measurement of RNA concentration and purity. qPCR validation of the six candidate prognostic genes was performed by SYBR Green-based PCR master mix on a real-time PCR system: initial denaturation at 95 °C for 30 s, followed by 40 cycles of 95 °C for 20 s, 55 °C for 20 s, and 72 °C for 20 s. Relative expression was computed and standardized to Glyceraldehyde-3-Phosphate Dehydrogenase(GAPDH) with the 2-ΔΔCt technique. Details of all reagents and instruments are provided in the Table of Materials.
Statistical analysis
Statistical analyses were conducted using statistical computing and graphing software. The protein-protein interaction network was visualized using network-analysis software. Following normality assessment, Student’s t-test was used for normally distributed continuous variables, and the Mann-Whitney U test for non-normally distributed ones.
Access restricted. Please log in or start a trial to view this content.
Results
Candidate gene identification and functional analysis
A total of 4,915 DEGs were detected, including 2,485 down-DEGs and 2,430 up-DEGs (Figure 1A). Functional module clustering analysis classified these DEGs into six expression modules (C1-C6), among which the C1, C2, C3, and C5 modules showed relatively higher expression in tumor samples (Figure 1B). Functional annotation indicated that these modules were linked to b...
Access restricted. Please log in or start a trial to view this content.
Discussion
LUAD is among the leading forms of lung cancer and continues to pose a considerable public health burden21. MC is a cell death-related process that may contribute to clearing cells with severe mitotic abnormalities and the suppression of tumor progression22. Therefore, exploring the potential role of MCRGs in LUAD may help identify prognostic biomarkers and improve understanding of LUAD biology. The study analyzed the prognostic relevance and potential functional significan...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors declare no conflicts of interest.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| ClusterGVis | CRAN | version 0.1.2 | Gene Expression Clustering and Visualization |
| Cytoscape | Cytoscape Consortium | version 3.9.1 | Visualization of Protein Interaction Networks RRID:SCR_003032 |
| CFX384 Real-Time Quantitative Fluorescent PCR System | Bio-Rad | CFX384 Touch | qPCR reagent |
| DMD-primer | Tsingke | N/A | Forward: 5’-GCTCAACCATCGATTTGCAGCC-3’ Reverse: 5’-TTCAGCCTCCAGTGGTTCAAGC-3’ |
| FKBP4-primer | Tsingke | N/A | Forward: 5’-TGACTCCAGTCTGGATCGCAAG-3’ Reverse: 5’-CTGGTTTGCAGGTGATGTGGCA-3’ |
| GEO | NCBI | Online Tool | Obtaining the LUAD External Validation Dataset RRID:SCR_005012 |
| GAPDH-primer | Tsingke | N/A | Forward: 5’-GTCTCCTCTGACTTCAACAGCG-3’ Reverse: 5’-ACCACCCTGTTGCTGTAGCCAA-3’ |
| glmnet | CRAN | version 4.1-8 | Feature Selection in LASSO Regression RRID:SCR_015505 |
| LDHA-primer | Tsingke | N/A | Forward: 5’-GGATCTCCAACATGGCAGCCTT-3’ Reverse: 5’-AGACGGCTTTCTCCCTCTTGCT-3’ |
| limma | Bioconductor | version 3.60.6 | DEG screening RRID:SCR_010943 |
| maftools | Bioconductor | version 2.20.0 | Visualization of Somatic Mutation Data RRID:SCR_024519 |
| pRRophetic | CRAN | 0.5 | Prediction of Drug IC50 Values RRID:SCR_024417 |
| PDGFB-primer | Tsingke | N/A | Forward: 5’-GAGATGCTGAGTGACCACTCGA-3’ Reverse: 5’-GTCATGTTCAGGTCCAACTCGG-3’ |
| qPCR SYBR Green Master Mix | Vazyme | Q111-02 | qPCR reagent |
| R software | R Foundation | version 4.2.2 | Bioinformatics Analysis |
| regplot | CRAN | version 1.1 | Creating Line Charts |
| survival | CRAN | version 3.8-3 | Survival Analysis and Cox Regression RRID:SCR_021137 |
| STRING | STRING Consortium | Online Tool | Protein Interaction Network Analysis RRID:SCR_005223 |
| S100B-primer | Tsingke | N/A | Forward: 5’-GAAGAAATCCGAACTGAAGGAGC-3’ Reverse: 5’-TCCTGGAAGTCACATTCGCCGT-3’ |
| survminer | CRAN | version 0.5.0 | Survival Curve Plotting and Optimization RRID:SCR_021094 |
| TRIzol | Tiangen | DP424 | qPCR reagent |
| TCGA | NCI | Online Tool | LUAD Transcriptome and Clinical Data Acquisition RRID:SCR_003193 |
| ZEB2-primer | Tsingke | N/A | Forward: 5’-AATGCACAGAGTGTGGCAAGGC-3’ Reverse: 5’-CTGCTGATGTGCGAACTGTAGG-3’ |
References
- Asada K, et al. Multi-omics and clustering analyses reveal the mechanisms underlying unmet needs for patients with lung adenocarcinoma and identify potential therapeutic targets. Mol Cancer. 2024;23(1):182.
- Sun Q, et al. Prediction of lung adenocarcinoma prognosis and diagnosis with a novel model anchored in circadian clock-related genes. Sci Rep. 2024;14(1):18202.
- Ho KH, et al. Cancer Essential Genes Stratified Lung Adenocarcinoma Patients with Distinct Survival Outcomes and Identified a Subgroup from the Terminal Respiratory Unit Type with Different Proliferative Signatures in Multiple Cohorts. Cancers (Basel). 2021;13(9):2128.
- Zhang J, et al. Unraveling the Expression Patterns of Immune Checkpoints Identifies New Subtypes and Emerging Therapeutic Indicators in Lung Adenocarcinoma. Oxid Med Cell Longev. 2022;2022:3583985.
- Zheng T, et al. The pathological significance and potential mechanism of ARHGEF6 in lung adenocarcinoma. Comput Biol Med. 2023;158:106894.
- Yu Y, et al. Predicting potential therapeutic targets and small molecule drugs for early-stage lung adenocarcinoma. Biomed Pharmacother. 2024;174:116528.
- Guo Q, et al. Heterogeneous mutation pattern in tumor tissue and circulating tumor DNA warrants parallel NGS panel testing. Mol Cancer. 2018;17(1):131.
- Wang S, et al. Development and validation of a mitotic catastrophe-related genes prognostic model for breast cancer. PeerJ. 2024;12:e18075.
- Mao Z, et al. Mitotic catastrophe heterogeneity: implications for prognosis and immunotherapy in hepatocellular carcinoma. Front Immunol. 2024;15:1409448.
- Zhang QY, et al. Multiple Regulatory Mechanisms of Post-Translational Modifications and Therapeutic Potential of Mitotic Catastrophe. Int J Mol Sci. 2026;27(8):3370..
- Minemoto Y, et al. Loss of p53 induces M-phase retardation following G2 DNA damage checkpoint abrogation. Arch Biochem Biophys. 2003;412(1):13-9.
- Liu Y, et al. Developing a prognosis and chemotherapy evaluating model for colon adenocarcinoma based on mitotic catastrophe-related genes. Sci Rep. 2024;14(1):1655.
- Ritchie ME, et al. limma powers differential expression analyses for RNA-sequencing and microarray studies. Nucleic Acids Res. 2015;43(7):e47.
- Szklarczyk D, et al. The STRING database in 2023: protein-protein association networks and functional enrichment analyses for any sequenced genome of interest. Nucleic Acids Res. 2023;51(D1):D638-d46.
- Lei J, et al. Clinicopathological characteristics of pheochromocytoma/paraganglioma and screening of prognostic markers. J Surg Oncol. 2023;128(4):510-8.
- Thorsson V, et al. The Immune Landscape of Cancer. Immunity. 2018;48(4):812-30.e14.
- Guo Y, et al. Novel immune checkpoint-related gene model to predict prognosis and treatment responsiveness in low-grade gliomas. Heliyon. 2023;9(9):e20178.
- Sun X, et al. A transcriptomic-based model associated with PARP inhibitor sensitivity and immunogenic signatures in ovarian cancer. Discover Oncology. 2026;843.
- Wang L, et al. Identification of an ac4C modification related gene signature for predicting prognosis in laryngeal squamous cell carcinoma patients based on single-cell analysis and machine learning. 2026.
- Lin W, et al. Screening of Molecular Markers of Cisplatin Resistance in Lung Adenocarcinoma and Functional Verification Based on TCGA Database. Cancer Research on Prevention and Treatment. 2024;49(6):569-74.
- Gao W, et al. Promising therapeutic efficacy and safety of a novel integrin α6-targeting peptide-drug conjugate in lung adenocarcinoma. Molecular Cancer 2025;24(1):190.
- Vitale I, et al. Mitotic catastrophe: a mechanism for avoiding genomic instability. Nat Rev Mol Cell Biol. 2011;12(6):385-92.
- Liu M, et al. CDK1-mediated phosphorylation of LDHA fuels mitosis through LDHB-dependent lactate oxidation. EMBO Reports 2025;26(20):4923-4949.
- Zhang W, et al. Inhibition of LDHA suppresses cell proliferation and increases mitochondrial apoptosis via the JNK signaling pathway in cervical cancer cells. Oncology reports 2022;47(4).
- Mangé A, et al. FKBP4 connects mTORC2 and PI3K to activate the PDK1/Akt-dependent cell proliferation signaling in breast cancer. Theranostics. 2019;9(23):7003-7015.
- Meng W, et al. FKBP4 Accelerates Malignant Progression of Non-Small-Cell Lung Cancer by Activating the Akt/mTOR Signaling Pathway. Analytical cellular pathology (Amsterdam) 2020;2020:6021602.
- Xiu-Ying H, et al. PDGFBB facilitates tumorigenesis and malignancy of lung adenocarcinoma associated with PI3K-AKT/MAPK signaling. Sci Rep. 2024;14(1):4191.
- Sharma D, Singh M, Rani R. Role of LDH in tumor glycolysis: Regulation of LDHA by small molecules for cancer therapeutics. Semin Cancer Biol. 2022;87:184-95.
- Zhang P, et al. An Epithelial-Mesenchymal Transition-Based Prognostic Model for Survival Prediction in Lung Adenocarcinoma: COL5A2 and ZEB2. Current gene therapy 2026.
- Xu X, et al. Proteomic landscape of lung adenocarcinoma precancerous lesions reveals mitochondrial dsRNA-associated immune and stress responses. American journal of cancer research 2025;15(9):3888-3903.
- Li P, et al. Peripheral blood mononuclear cell DNA methylation biomarkers for prognostic stratification in Chinese lung adenocarcinoma: a genome-wide epigenetic profiling study. Clinical Epigenetics 2025;17(1):177.
- Chaudhary S, et al. Dissecting the MUC5AC/ANXA2 signaling axis: implications for brain metastasis in lung adenocarcinoma. Exp Mol Med. 2024;56(6):1450-60.
- Kondrup M, Nygaard AD, Madsen JS, Bechmann T. S100B as a biomarker for brain metastases in patients with non-small cell lung cancer. Biomed Rep. 2020;12(4):204-8.
- Jones L, Naidoo M, Machado LR, Anthony K. The Duchenne muscular dystrophy gene and cancer. Cell Oncol (Dordr). 2021;44(1):19-32.
- Peng G, Yan J, Shi P, Li H. LINC01140 Hinders the Development of Breast Cancer Through Targeting miR-200b-3p to Downregulate DMD. Cell Transplant. 2023;32:9636897231211202.
- Alnassar N, et al. Downregulation of Dystrophin Expression Occurs across Diverse Tumors, Correlates with the Age of Onset, Staging and Reduced Survival of Patients. Cancers (Basel). 2023;15(5):1378.
- Luce LN, Abbate M, Cotignola J, Giliberto F. Non-myogenic tumors display altered expression of dystrophin (DMD) and a high frequency of genetic alterations. Oncotarget. 2017;8(1):145-55.
- Hu Z, et al. IL6-STAT3-C/EBPβ-IL6 positive feedback loop in tumor-associated macrophages promotes the EMT and metastasis of lung adenocarcinoma. J Exp Clin Cancer Res. 2024;43(1):63.
- Ugel S, Canè S, De Sanctis F, Bronte V. Monocytes in the Tumor Microenvironment. Annu Rev Pathol. 2021;16:93-122.
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
This article has been published
Video Coming Soon