Moderate-to-severe pain, inadequate perioperative communication, insufficient postoperative education, and poor PCA awareness were independently associated with low postoperative PCA satisfaction. Targeted interventions addressing these factors may improve postoperative pain management and patient satisfaction.
Araştırma makalesi
Analysis and Improvement of Factors Affecting Satisfaction of Patients with Postoperative Patient-Controlled Analgesia
Bu makalede
Özet
Özet
Patient-controlled analgesia (PCA) is widely used for postoperative pain management, yet patient satisfaction remains influenced by multiple clinical and educational factors. Identifying modifiable determinants may help optimize postoperative analgesic care. To evaluate postoperative pain management and satisfaction with postoperative PCA, identify factors associated with patient satisfaction, and propose improvement strategies. A total of 887 patients who underwent surgery and received postoperative PCA between January 2023 and April 2024 were retrospectively enrolled. Satisfaction was assessed using a 5-point Likert scale, and patients were classified into high-satisfaction (very satisfied/satisfied) and low-satisfaction (neutral/dissatisfied/very dissatisfied) groups. Clinical characteristics were compared, and independent predictors of low satisfaction were identified using multivariable logistic regression. Internal validation was performed using 5,000 nonparametric Bootstrap resamples. Among 887 patients, 852 (96.05%) reported high satisfaction, and 35 (3.95%) low satisfaction. Moderate-to-severe pain, insufficient preoperative communication, inadequate postoperative follow-up education, poor PCA awareness, and lower satisfaction with PCA button use were more common in the low-satisfaction group (all p <0.05). Multivariable analysis identified moderate-to-severe pain (Odds ratio (OR) = 2.704, 95% confidence interval (CI): 1.158–6.319), insufficient preoperative communication (OR = 2.078, 95% CI: 1.002–4.310), poor PCA awareness (OR = 3.062, 95% CI: 1.164–8.052), and inadequate postoperative education (OR = 3.300, 95% CI: 1.263–8.621) as independent predictors of low satisfaction. Satisfaction with PCA button use was significant only in univariate analysis. Bootstrap validation demonstrated generally consistent effect directions, although confidence intervals for several variables remained wide. Pain intensity, preoperative communication, postoperative education, and PCA awareness are key determinants of postoperative PCA satisfaction. Improving perioperative patient education, communication, and pain control may enhance patient experience and optimize postoperative pain management.
Giriş
Pain is among the most frequent postoperative complications. Inadequate postoperative pain management may exacerbate patients’ anxiety and psychological distress, increase the incidence of secondary complications, prolong hospitalization and recovery, and ultimately compromise overall quality of life and health status1,2. Patient-controlled analgesia (PCA) is a pain management modality in which clinicians, according to factors such as the type of surgical trauma and the patient’s medical history, preset analgesic regimens that permit individualized, self-administered dosing3,4. The portable design of PCA pumps reduces restrictions related to body position and physical environment5, enabling patients to administer analgesics as needed in response to their pain intensity. This approach helps to avoid delays and fluctuations associated with conventional analgesic procedures, facilitating the achievement of adequate analgesia with the lowest effective drug concentration. Consequently, PCA has become one of the most widely used and preferred methods for postoperative analgesia6,7.
Previous studies have identified several factors associated with patient satisfaction with postoperative PCA. Pain intensity has consistently been reported as a strong predictor of satisfaction8,9. Patient education and preoperative communication have also been shown to improve patients’ understanding of PCA and enhance their perceived control over postoperative pain management10. Device usability, including the ease of PCA button operation and alarm management, has also been recognized as an additional factor influencing the overall patient experience. In terms of outcome measurement, although several validated instruments for assessing satisfaction with pain management exist, many prior studies have used ad hoc or unvalidated questionnaires, limiting comparability across studies. Despite these insights, most prior studies have examined these factors in isolation rather than simultaneously evaluating their relative contributions within a single cohort. In addition, large‑scale surveys specifically focusing on PCA satisfaction in Chinese surgical populations are scarce11. To address these gaps, the present study was designed to simultaneously evaluate a comprehensive set of modifiable perioperative factors—including pain intensity, preoperative communication, PCA awareness, and postoperative education—in a large single‑center cohort of 887 patients, with Bootstrap internal validation to assess model stability.
The present study aims to evaluate the current status of postoperative pain management and patient satisfaction with PCA in our hospital, to identify factors influencing these outcomes, and to propose targeted improvement strategies to establish a comprehensive institutional pain management system, standardize management procedures, and enhance the quality and safety of pain management services.
In this retrospective cohort study, we hypothesized that patient satisfaction with postoperative PCA is independently associated with modifiable perioperative factors—including pain intensity, adequacy of preoperative communication, quality of postoperative follow‑up education, and patients’ level of awareness about PCA.
This study may contribute to the existing literature by simultaneously evaluating a set of clinically actionable factors in a large single-center cohort (n = 887) and proposing practical improvement strategies based on the identified associations. In addition, we employed Bootstrap internal validation to assess the stability of the multivariable model, which may provide additional confidence in the findings. By clarifying these associations, the current work may inform the development of standardized protocols to enhance patient‑centered pain management and overall satisfaction in routine practice.
Protokol
This study was approved by the Peking University People's Hospital Ethics Committee (Approval number: 2024PHB111-001). All procedures were performed in accordance with the ethical standards of the institutional research committee and the 1964 Declaration of Helsinki and its later amendments. Informed consent was obtained from all individual participants included in the study.
Study population
This study included 887 patients who underwent surgical procedures and received postoperative patient-controlled analgesia (PCA) at our hospital between January 2023 and April 2024. Eligible patients were aged 18 years or older, had complete clinical data, no documented allergy to any component of the analgesic regimen, and provided informed consent. Patients were excluded if they were pregnant or lactating, had American Society of Anesthesiologists (ASA) physical status class IV, presented with severe organic disease or significant immunometabolism disorder, had communication barriers or diagnosed psychiatric or cognitive disorders, or exhibited poor treatment adherence or inability to adequately cooperate with study procedures.
Assessment of postoperative PCA satisfaction
Patient satisfaction with postoperative PCA was assessed using a questionnaire developed by the department. The instrument encompassed multiple domains, including patients’ awareness and expectations regarding PCA; preoperative preparation and communication; pain intensity; treatment experience; analgesia management; adverse effects and discomfort; access to information and support; overall satisfaction; and suggestions for improvement. The questionnaire was developed through departmental quality-improvement discussions based on routine postoperative PCA nursing practice, patient education workflows, and common patient-reported concerns. Before formal data collection, the questionnaire content was reviewed by anesthesiology nurses and clinicians to ensure that the items covered clinically relevant aspects of PCA care. Because this was a single-center real-world quality-improvement survey, a full psychometric validation of the self-designed questionnaire was not completed before implementation; therefore, the measurement properties of the instrument should be interpreted as a study limitation. The English‑language version of the questionnaire is provided as Supplementary File 1.
A five-point Likert scale was employed, with response options of “very satisfied,” “satisfied,” “neutral,” “dissatisfied,” and “very dissatisfied.” Patients who reported being very satisfied or satisfied were classified into the high-satisfaction group, whereas those who selected neutral, dissatisfied, or very dissatisfied were classified into the low-satisfaction group.
Collection of clinical data
Members of the research team explained the study objectives and principles of confidentiality to all participants and provided standardized instructions for completing the questionnaire. The self-administered questionnaire collected information on sex, age, educational level, employment status, average monthly household income, clinical department, ASA physical status classification, pain intensity, preoperative communication with medical staff, level of awareness of PCA (including cost and potential adverse effects), postoperative follow-up and education, and satisfaction with PCA device use. Questionnaires were distributed and collected in person on the second postoperative day, approximately 24–48 h after PCA initiation and before PCA discontinuation, ensuring that all patients were assessed at a clinically equivalent time point to minimize variability in patient recall and experience. All responses were reviewed promptly by the research team to ensure completeness and accuracy.
Observation indicators
The primary observational indicators included comparisons of clinical and demographic characteristics between the high- and low-satisfaction groups, and the identification and analysis of risk factors associated with postoperative PCA satisfaction.
Statistical analysis
All statistical analyses were conducted using statistical software, with a two‑sided significance level of α = 0.05. Categorical variables were summarized as frequencies and percentages [n (%)] and compared using the χ2 test. Continuous variables were expressed as mean ± standard deviation (x̄ ± s) and analyzed using the independent‑samples t‑test. Multivariable logistic regression analysis was performed to identify independent risk factors associated with postoperative PCA satisfaction. To evaluate the internal stability of the multivariable logistic regression model, nonparametric Bootstrap validation was performed using the original dataset. Resampling with replacement was conducted at the original sample size and repeated 5,000 times. The median odds ratio (OR) and the 95% bootstrap percentile confidence interval were calculated for each variable.
Sonuçlar
Comparison of clinical data
Among the 887 patients who received postoperative PCA, 852 (96.05%) were classified as high satisfaction, whereas 35 (3.95%) were classified as low satisfaction. The patient enrollment and grouping process is summarized in Figure 1.
There were no statistically significant differences between the two groups with respect to sex, age, educational level, employment status, average monthly household income, departmental distribution, or ASA physical status classification (p > 0.05).
By contrast, the low-satisfaction group exhibited a higher proportion of patients with moderate to severe pain, insufficient preoperative communication with medical staff, limited awareness of PCA (including its cost and potential adverse effects), inadequate postoperative follow-up and education, and lower satisfaction with PCA device use compared with the high-satisfaction group (p < 0.05). Detailed comparisons are presented in Table 1, and the key variables that differed significantly between the two groups are visualized in Figure 2.
Multivariate analysis of factors influencing postoperative PCA satisfaction
Five categories of variables that were statistically significant in the univariate analysis were entered as independent variables, with low satisfaction with postoperative PCA as the dependent variable (no = 0, yes = 1). Multivariable logistic regression analysis was performed using the Enter method. The variable coding is presented in Table 2.
The results showed that moderate-to-severe pain (OR = 2.704, 95% CI: 1.158–6.319), insufficient preoperative visit communication (OR = 2.078, 95% CI: 1.002–4.310), poor awareness of PCA therapy (OR = 3.062, 95% CI: 1.164–8.052), and insufficient postoperative follow-up education (OR = 3.300, 95% CI: 1.263–8.621) were independently associated with low satisfaction with postoperative PCA (p < 0.05). Moderate awareness of PCA therapy and moderate satisfaction with PCA button use did not reach statistical significance in the multivariable model (p > 0.05), whereas low satisfaction with PCA button use did. Detailed results are summarized in Table 3, and the significant independent risk factors are visualized in the forest plot shown in Figure 3.
Bootstrap internal validation showed that the directions of the main variables' effects were generally consistent with the original model. The Bootstrap 95% CI for moderate‑to‑severe pain did not cross 1, confirming its relatively robust association with low satisfaction. However, the Bootstrap 95% CIs for insufficient preoperative communication, poor PCA awareness, and inadequate postoperative education were wide and crossed 1, indicating that the precision of these estimates remains limited by the small number of low‑satisfaction events. The bootstrap internal validation results are presented in Table 4.
Data Availability:
Due to ethical restrictions related to patient privacy and confidentiality, the full raw clinical dataset is not publicly available but may be accessed upon reasonable request to the corresponding author, subject to institutional ethics approval (Peking University People‘s Hospital Ethics Committee, approval No. 2024PHB111-001).
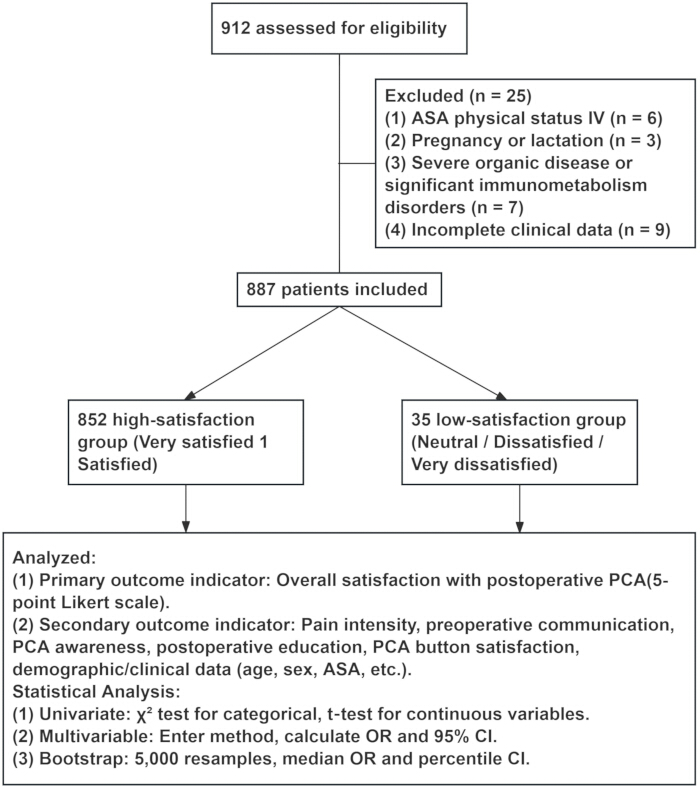
Figure 1: Study flow diagram and analytical workflow. A total of 887 patients were included and categorized into high-satisfaction (n = 852) and low-satisfaction (n = 35) groups based on a 5-point Likert scale (primary outcome). No loss to follow-up occurred, as all questionnaires were completed during hospitalization. Please click here to view a larger version of this figure.
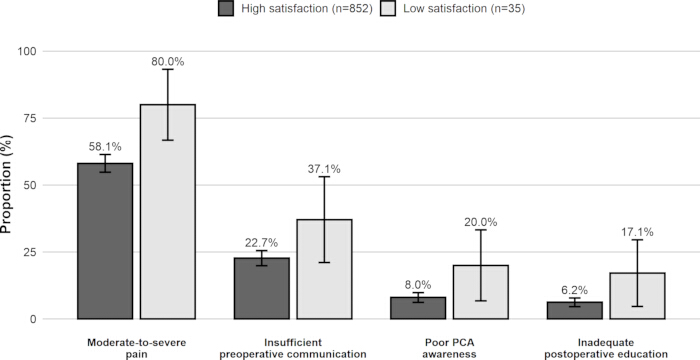
Figure 2: Comparison of key risk factors between high- and low-satisfaction groups. The bar chart displays the proportions of patients with four risk factors in the high-satisfaction (n = 852) and low-satisfaction (n = 35) groups: moderate-to-severe pain (58.1% vs. 80.0%), insufficient preoperative communication (22.7% vs. 37.1%), poor PCA awareness (8.0% vs. 20.0%), and inadequate postoperative education (6.2% vs. 17.1%). All four factors showed significantly higher proportions in the low-satisfaction group (p < 0.05 for each, χ2 test). Error bars represent 95% confidence intervals. Please click here to view a larger version of this figure.
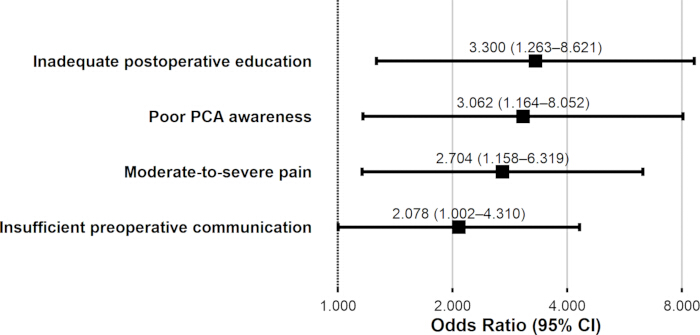
Figure 3: Forest plot of multivariable logistic regression analysis for factors associated with low satisfaction with postoperative PCA. The plot displays adjusted odds ratios (ORs) with 95% confidence intervals (CIs) for the four independent risk factors identified in the multivariable logistic regression model: moderate-to-severe pain (OR = 2.704, 95% CI: 1.158–6.319), insufficient preoperative communication (OR = 2.078, 95% CI: 1.002–4.310), poor PCA awareness (OR = 3.062, 95% CI: 1.164–8.052), and inadequate postoperative education (OR = 3.300, 95% CI: 1.263–8.621). Data points are represented by black squares, and horizontal lines indicate the corresponding 95% CIs. The vertical dashed line at OR = 1 indicates the null effect; variables with 95% CIs entirely to the right of this line were statistically significant (p < 0.05 for each). The X-axis is displayed on a log10 scale. Please click here to view a larger version of this figure.
Table 1: Comparison of clinical data [(x̄ ± s), n (%)]. Data are presented as mean ± standard deviation (x̄ ± s) for continuous variables and as n (%) for categorical variables. p-values were calculated using the independent‑samples t‑test for continuous variables and the χ2 test for categorical variables. Abbreviations: ASA = American Society of Anesthesiologists; PCA = patient‑controlled analgesia. Please click here to download this file.
Table 2: Coding of variables. The dependent variable was low satisfaction (coded as 0 = no, 1 = yes). Independent variables were coded as binary or ordinal as shown. Abbreviations: PCA = patient‑controlled analgesia. Please click here to download this file.
Table 3: Multivariable logistic regression analysis of factors associated with low satisfaction with postoperative PCA. Adjusted odds ratios (ORs) with 95% confidence intervals (CIs) are presented. Variables were entered using the Enter method. P-values were calculated using the Wald χ2 test. Abbreviations: PCA = patient‑controlled analgesia. Please click here to download this file.
| Variable | Original model OR | Bootstrap median OR | Bootstrap 95%CI |
| Moderate-to-severe pain vs mild | 2.704 | 2.823 | 1.289-8.953 |
| Insufficient preoperative communication vs adequate | 2.078 | 2.148 | 0.911-4.693 |
| Moderate PCA awareness vs good | 1.612 | 1.642 | 0.711-3.730 |
| Poor PCA awareness vs good | 3.062 | 3.173 | 0.926-8.448 |
| Insufficient postoperative education vs adequate | 3.3 | 3.379 | 0.783-8.861 |
| Moderate PCA button satisfaction vs high | 2.005 | 2.016 | 0.799-4.404 |
| Low PCA button satisfaction vs high | 2.728 | 2.719 | <0.001-9.292 |
Table 4: Bootstrap internal validation results for factors associated with low satisfaction with postoperative PCA. Bootstrap resampling was performed with 5,000 iterations using the original dataset. The median odds ratios (ORs) and bootstrap percentile 95% confidence intervals (CIs) are presented for each variable, compared with the ORs from the original multivariable logistic regression model. Abbreviations: PCA = patient‑controlled analgesia; CI = confidence interval.
Supplementary Figure 1: Institutional PCA education and follow-up pathway. Schematic overview of the institutional perioperative pathway for patient-controlled analgesia (PCA), including preoperative PCA education and informed consent, intraoperative optimization of the analgesic regimen and PCA pump parameters, and postoperative bedside guidance, pain assessment, patient satisfaction evaluation, and quality-improvement feedback. Please click here to download this file.
Supplementary File 1: Postoperative Patient-Controlled Analgesia (PCA) Satisfaction Questionnaire. Questionnaire used to collect patient demographic and clinical information and assess postoperative PCA-related factors, including pain intensity, preoperative communication, PCA awareness, postoperative follow-up and education, satisfaction with PCA button use, overall satisfaction with postoperative PCA, and suggestions for improvement. Overall satisfaction was assessed using a five-point Likert scale. Please click here to download this file.
Tartışma
Current status of postoperative PCA satisfaction
Standardized perioperative pain management is a critical component of contemporary clinical practice. Effective postoperative analgesia can substantially improve the quality of pain control, reduce pain intensity and the incidence of complications, facilitate early mobilization and functional recovery, shorten the length of hospital stay, lower medical costs, and enhance overall patient satisfaction, thereby contributing to a more harmonious physician–patient relationship12,13. In contrast, inadequate pain management may exacerbate negative emotional states such as anxiety and depression, delay postoperative recovery, and exert detrimental effects on both physical and psychological health.
PCA is characterized by a rapid onset of analgesia, stable plasma drug concentrations, and the ability to minimize “blind spots” in analgesic coverage14. Furthermore, it allows for individualized titration of analgesic dosing according to patients’ subjective pain experiences15, making it an essential modality in postoperative pain management. Nonetheless, despite these clear advantages, multiple challenges persist in routine clinical application.
In the present study, among 887 patients who received postoperative PCA, 852 (96.05%) were classified as highly satisfied, whereas 35 (3.95%) reported lower satisfaction. Multivariable analysis identified moderate‑to‑severe pain, insufficient preoperative communication, poor PCA awareness, and inadequate postoperative education as independent predictors in the original model. However, Bootstrap internal validation indicated that only moderate‑to‑severe pain had a 95% CI that did not cross 1, whereas the intervals for the other three factors were wide and crossed 1, suggesting that their associations should be interpreted with greater caution. Satisfaction with PCA device button use differed between groups, suggesting that device operation experience may still influence patients' subjective perception; however, after simultaneous adjustment for pain intensity, communication and education, and PCA awareness, its independent effect did not reach statistical significance. Based on these findings and the clinical experience, we have proposed a series of targeted optimization strategies to improve the quality of PCA management and further enhance patient satisfaction. These strategies represent planned quality‑improvement initiatives; their effectiveness requires prospective evaluation in future studies. Bootstrap internal validation confirmed a relatively robust association for moderate‑to‑severe pain (95% CI did not cross 1), whereas the CIs for the three communication‑ and education‑related factors were wide and crossed 1, underscoring the need for cautious interpretation of these latter findings due to the limited number of low‑satisfaction events.
From a theoretical perspective, these findings may be understood through the lens of patient engagement and shared decision-making frameworks. Adequate preoperative communication and postoperative education can improve patients' understanding of PCA, clarify expectations regarding analgesic effects and adverse reactions, and enhance their perceived control over postoperative pain management. Similarly, from the perspective of the Health Belief Model, patients who better understand the benefits, risks, and proper use of PCA may be more likely to actively participate in analgesic self-management and report higher satisfaction. Therefore, PCA satisfaction may reflect not only analgesic efficacy but also patients' participation, perceived safety, and confidence in the care process.
Analysis of factors affecting postoperative PCA satisfaction and improvement strategies
Inadequate preoperative consultation
Preoperative consultation constitutes a critical component of the anesthesiologist’s preoperative assessment. During this process, the clinician systematically collects relevant patient information, formulates an appropriate anesthesia plan, and provides detailed counseling to patients and their families regarding anesthesia options, the importance of postoperative analgesia, the purpose and operational procedures of PCA, anticipated costs, common adverse effects (such as nausea, vomiting, and pruritus), and key safety considerations. This process facilitates a comprehensive understanding of anesthesia-related risks and the role of PCA prior to obtaining informed consent.
If disproportionate emphasis is placed on merely obtaining a signed consent form while the preoperative visit is inadequately conducted, patients may fail to fully appreciate the potential risks and benefits of anesthesia and PCA, which may in turn reduce satisfaction and compromise analgesic outcomes16. To ensure truly informed consent, surgical safety, and optimal pain control, healthcare providers should verify that patients have an adequate understanding of the surgical procedure, anesthetic technique, and PCA use before signing consent documents17.
In response to these considerations, the hospital has implemented the following improvement measures: (1) Establishment of an online perioperative pain management clinic, with QR codes posted in the preoperative assessment center, providing full-day services from Monday to Friday; (2) Strengthening communication between the departments of anesthesiology and surgery by contacting the head nurses and charge nurses of surgical wards at the first follow-up visit, establishing instant-messaging liaison groups for pain nurses, and conducting monthly quality surveys and feedback meetings; (3) Establishing pilot departmental education teams in selected wards to provide preoperative education, including verbal counseling, live demonstrations of PCA device operation, and QR codes linking to educational videos that explain analgesic efficacy, potential adverse effects, and treatment-related costs.
Increased proportion of patients with moderate to severe pain
Nerve block anesthesia achieves analgesia by injecting local anesthetics to interrupt nerve conduction18. However, variations in operator experience, needle insertion angle, depth, and applied force may influence the effectiveness of analgesia. In addition, differences in the physical properties of puncture needles—such as tip configuration and shaft stiffness—can affect both the success rate and safety profile of nerve blocks. Repeated puncture attempts, inappropriate technique, or hematoma formation may lead to puncture-site leakage19, and design limitations of newer needle models compared with previous brands may further increase the risk of tissue injury and leakage.
Suboptimal analgesic efficacy directly exacerbates postoperative pain, delays functional recovery, and diminishes quality of life. Moreover, puncture-site leakage increases the risk of local infection and inflammation, thereby intensifying patient discomfort and potentially elevating medical costs. In order to address these issues, the hospital has implemented the following measures: (1) Adjustment of clinical techniques to accommodate newer, softer outer cannula designs while maintaining procedural consistency; (2) Optimization of fixation methods to reduce the incidence of leakage following nerve block catheter placement.
Inappropriate PCA pump parameter settings
PCA pump settings are determined by clinical experience, patient-specific needs, and device characteristics; thus, inter-institutional variability is common. To ensure both safety and efficacy, individualized parameter adjustments should be implemented based on standardized baseline settings.
In clinical practice, we have observed that suboptimal compatibility of internal PCA parameters—including alarm configurations (e.g., occlusion or high-pressure alerts) and inadequate pressure valve settings—may contribute to decreased patient satisfaction, as evidenced by clinical experience and device evaluations. These observations were not derived from the statistical analysis of the present study, as PCA parameter settings were not included as variables in the multivariable model. Nevertheless, they represent practical issues that warrant attention in quality improvement efforts. PCA alarms are intended to indicate abnormalities such as air entrapment, line occlusion, or drug depletion. Alarm tones should be clearly distinguishable yet adjustable in volume to minimize patient disturbance20. High-pressure alarm thresholds must be set with consideration of pump type, infusion rate, and the patient’s clinical status to mitigate potential safety risks. Inappropriate pressure valve settings may lead to unstable drug delivery or failure to meet specific clinical requirements.
Accordingly, existing pressure valves should be comprehensively evaluated with respect to load-bearing capacity, stability, and reliability, and optimal pressure ranges should be determined based on clinical needs21. Parameters such as bolus dose and maximum allowable dose should likewise be individualized based on the patient’s pain intensity and the analgesic agent's pharmacological properties. In response to these findings, the hospital has adopted the following measures: (1) Organization of ward-based PCA pump training sessions and establishment of a duty-based consultation mechanism to provide timely responses to clinical inquiries; (2) Collaboration with device manufacturers to upgrade internal PCA pump configurations, including optimization of alarm systems and the addition of check valves to enhance safety and reduce the risk of backflow.
Inadequate postoperative follow-up and patient education
Several factors—including interruptions in pain management training during the COVID-19 pandemic, rapid hospital expansion with the recruitment of a large number of newly employed nurses, and limited familiarity with newly introduced PCA devices—contributed to suboptimal postoperative follow-up and education, thereby markedly affecting patient satisfaction.
Disruptions in training may have left nurses insufficiently up to date on current analgesic protocols, while newly recruited staff often require additional time to adapt to clinical workflows. Effective postoperative education is essential to ensure correct PCA use22. Moreover, variations in pump models and functional configurations necessitate systematic and ongoing nurse training. A lack of proficiency may lead to incorrect operation, delays in analgesic administration, and reduced patient satisfaction.
Standardized postoperative pain care has been shown to substantially improve analgesic outcomes and patient experience23. In response to these challenges, the hospital implemented a series of strategies to strengthen postoperative follow-up and patient education, as summarized in Supplementary Figure 1. These included: (1) Provision of centralized theoretical training for pain liaison nurses, covering pain definitions and assessment, pharmacological and non-pharmacological pain management, cancer pain care, and the interpretation of relevant clinical guidelines; (2) Administration of hospital-wide theoretical examinations following completion of the training; (3) Distribution of standardized pain assessment tools to all inpatient wards; (4) Placement of QR codes on PCA pumps linking to instructional videos on pain assessment methods, to facilitate both nurse training and patient use.
It is important to note that the improvement strategies described above are proposed based on the associations identified in this observational study and on routine clinical practice at the institution. They should therefore not be interpreted as validated interventions that have been proven to increase satisfaction. Future prospective studies with before‑and‑after designs, as well as randomized controlled trials, are needed to evaluate whether these strategies effectively improve patient outcomes and satisfaction.
In conclusion, pain intensity, adequacy of preoperative communication, quality of postoperative follow-up and education, and level of awareness of PCA are important factors associated with postoperative PCA satisfaction. Although PCA button-use experience was not an independent factor in the multivariable model, it still reflects patients' subjective perception of the convenience and controllability of analgesic care. Through strengthening patient education, enhancing training for medical staff, and optimizing PCA pump configurations, the hospital can further improve postoperative PCA management. Future work will involve enlarging the study sample and further incorporating patient-reported feedback to refine inpatient pain management strategies, thereby enhancing overall patient satisfaction and the quality of healthcare services.
This study has several limitations. First, postoperative PCA satisfaction was assessed using a self-designed departmental questionnaire, and full reliability and validity testing were not completed before data collection. Future studies should adopt or combine internationally recognized pain-management satisfaction scales and conduct formal psychometric validation. Second, although clinically relevant perioperative variables such as pain intensity, preoperative communication, PCA awareness, postoperative follow-up education, and PCA button-use satisfaction were included, other potential confounders were not fully adjusted for in the analysis. These include surgical procedure type (e.g., abdominal, orthopedic, or thoracic surgery), anesthesia modality (e.g., general anesthesia, neuraxial blockade, or peripheral nerve block), specific analgesic regimen (e.g., opioid type and dosage), PCA drug composition (e.g., morphine, hydromorphone, or fentanyl-based formulations), PCA parameter settings (e.g., bolus dose, lockout interval, and background infusion rate), and adverse events such as postoperative nausea and vomiting, pruritus, and sedation. The absence of these variables may introduce residual confounding, and their potential influence on satisfaction should be systematically evaluated in future studies with larger sample sizes and more comprehensive data collection. Third, the number of patients reporting low satisfaction was limited (n = 35, 3.95%), which precluded a meaningful split‑sample or external validation. This low event count is a particular concern for the stability of the multivariable logistic regression model, as the event‑per‑variable ratio was relatively low; with 35 events and 7 variables entered into the model, the ratio of approximately 5:1 is below the generally recommended threshold of 10 events per variable for reliable logistic regression. To mitigate this concern, internal bootstrap validation with 5,000 resamples was performed to assess model stability. The bootstrap results showed generally consistent directions of effect for the main variables. Nevertheless, this internal validation approach cannot fully eliminate the risk of overfitting or serve as a substitute for external validation in an independent cohort. The relatively wide Bootstrap confidence intervals for several predictors (e.g., insufficient preoperative communication, poor PCA awareness, and inadequate postoperative education) further reflect this uncertainty and underscore that these findings should be interpreted as preliminary and hypothesis‑generating rather than definitive. Future studies with larger sample sizes and a greater number of low‑satisfaction events are needed to confirm these associations and to enable more robust multivariable modeling with adequate statistical power. Fourth, this was a single‑center retrospective study, and the findings should therefore be validated in larger, independent multicenter cohorts with more low‑satisfaction events to confirm the generalizability of the results to broader populations. In addition, the overall satisfaction rate in the cohort was extremely high (96.05%), which, while reflecting favorable clinical outcomes at our institution, inherently limited the discriminative ability of the multivariable model and reduced statistical power to detect additional predictors. This high satisfaction rate may also reflect institution‑specific factors—such as standardized PCA protocols, routine staff training, and structured patient education practices—that may not be representative of other centers with different PCA management approaches or patient populations. Consequently, the present findings should be interpreted with caution when extrapolating to institutions with substantially different baseline satisfaction rates or PCA protocols, and external validation in more diverse cohorts is warranted.
Açıklamalar
The authors declare that they have no financial conflicts of interest. No AI tools were used in the preparation of the manuscript or figures.
Author Contributions:
Wei Liu: Developed and planned the study, performed experiments, and interpreted results. Edited and refined the manuscript with a focus on critical intellectual contributions; Chao Liu, Weixin Zhang: Participated in collecting, assessing, and interpreting the data. Made significant contributions to date interpretation and manuscript preparation; Bailin Jiang, Miao He: Provided substantial intellectual input during the drafting and revision of the manuscript
Teşekkürler
This study was funded by Peking University People’s Hospital Research and Development Fund (Scientific Research) – Nursing Research Project (Approval No.: RDN2022-20)
Malzemeler
| Ad | Şirket | Katalog numarası | Yorumlar |
|---|---|---|---|
| Postoperative PCA Satisfaction Questionnaire | Peking University People’s Hospital | N/A | Department-developed questionnaire used to assess postoperative PCA satisfaction and related factors |
| Python 3.12 | Python Software Foundation | https://docs.python.org/3.12/ | Bootstrap analysis |
| SPSS version 23.0 | IBM Corporation | https://www.ibm.com/products/spss-statistics | statistical analyses |
Kaynaklar
- Gan TJ. Poorly controlled postoperative pain: prevalence, consequences, and prevention. J Pain Res. 2017;10:2287-98.
- Bozdağ Başkaya HG, Kalemci S, Zeybek A. Postoperative pain management challenge. Ann Thorac Surg. 2023;116(3):652-3.
- Grass JA. Patient-controlled analgesia. Anesth Analg. 2005;101(5 Suppl):S44-61.
- Macintyre PE. Safety and efficacy of patient-controlled analgesia. Br J Anaesth. 2001;87(1):36-46.
- Motamed C. Clinical update on patient-controlled analgesia for acute postoperative pain. Pharmacy (Basel). 2022;10(1): PMID: 35202071
- Jin X, et al. Clinical application of different doses of hydromorphone slow-release analgesia in lumbar fusion in elderly patients. Pain Ther. 2024;13(5):1219-33.
- Wu CL, Raja SN. Treatment of acute postoperative pain. Lancet. 2011;377(9784):2215-25.
- El-Tallawy SN, et al. Identifying predictors of early postoperative pain and patient satisfaction following day surgery: insights from an observational study. Cureus. 2025;17(6):e86118.
- Baek W, Jang Y, Park CG, Moon M. Factors influencing satisfaction with patient-controlled analgesia among postoperative patients using a generalized ordinal logistic regression model. Asian Nurs Res (Korean Soc Nurs Sci). 2020;14(2):73-81.
- Lam KK, Chan MTV, Chen PP, Kee WDN. Structured preoperative patient education for patient-controlled analgesia. J Clin Anesth. 2001;13(6):465-9.
- Chen W, et al. Patient satisfaction with postoperative analgesia after hepatobiliary and pancreatic surgery: a retrospective analysis. Front Surg. 2026;13: p.1887173.
- Zhang YE, Xu X, Gong R. Postoperative pain management outcomes at a Chinese hospital: a cross-sectional survey. J Perianesth Nurs. 2023;38(3):434-9.
- Joseph JM, et al. Gaps in standardized postoperative pain management quality measures: a systematic review. Surgery. 2022;171(2):453-8.
- Xuan X, Cui H, Cao Y, Hu Y. Current status and application of patient-controlled analgesia: a literature review. Int J Clin Exp Med. 2019;12(3):2633-41.
- Xu J, et al. The postoperative analgesic effect of intercostal nerve block and intravenous patient-controlled analgesia on patients undergoing lung cancer surgery. Am J Transl Res. 2021;13(8):9790-5.
- Tait AR, Teig MK, Voepel-Lewis T. Informed consent for anesthesia: a review of practice and strategies for optimizing the consent process. Can J Anaesth. 2014;61(9):832-42.
- Uysal O, Karaman S, Karaman T. Effect of educational tools on the use of patient-controlled analgesia devices. Turk J Anaesthesiol Reanim. 2023;51(3):243-8.
- Marhofer P, Greher M, Kapral S. Ultrasound guidance in regional anaesthesia. Br J Anaesth. 2005;94(1):7-17.
- Jeng CL, Torrillo TM, Rosenblatt MA. Complications of peripheral nerve blocks. Br J Anaesth. 2010;105(Suppl 1):i97-107.
- International Electrotechnical Commission. Medical electrical equipment - Part 2-24: particular requirements for the basic safety and essential performance of infusion pumps and controllers. IEC; Geneva; 2012.
- Institute for Safe Medication Practices. ISMP guidelines for optimizing safe implementation and use of smart infusion pumps. ISMP; Horsham, PA; 2020.
- Barwig K, et al. Using video to describe the patient-controlled analgesia pump programming process: a qualitative study. J Nurs Care Qual. 2024;39(1):31-6.
- Hainsworth KR, et al. Investigating the effects of cuing medication availability on patient-controlled analgesia pump usage in pediatric patients: results of a randomized controlled trial. Clin J Pain. 2021;37(1):1-10.