This article presents a comprehensive protocol for an experimental mouse model of autoimmune muscle-specific kinase (MuSK) myasthenia gravis, aimed at investigating the pathophysiology and potential therapeutic strategies for the disease.
Method Article
Active Immunization for Inducing Autoimmune Muscle-Specific Kinase (MuSK) Myasthenia Gravis in Mice
In This Article
Summary
Abstract
Myasthenia gravis (MG) is an autoimmune disorder affecting the neuromuscular junction. While most MG patients produce autoantibodies against the acetylcholine receptor (AChR), a subset of patients exhibits autoantibodies targeting the muscle-specific kinase (MuSK). MuSK MG is characterized by severe muscle weakness, treatment-resistant clinical manifestations, and myasthenic crises, often necessitating mechanical ventilation. Consequently, patients frequently require prolonged use of immunosuppressants, which are associated with long-term adverse effects. Given the severity and rarity of MuSK-MG, developing an experimental animal model is crucial for advancing new treatment modalities and a deeper understanding of the underlying pathophysiological mechanisms. Experimental autoimmune myasthenia gravis (EAMG) serves as an animal model for MuSK-MG, effectively but partly mimicking the clinical and immunological features of human MG. The induction of autoimmune animal models can be achieved through active or passive immunization. In the herein presented experimental protocol, active immunization was employed by subcutaneously administering the purified extracellular domain of human MuSK emulsified in complete Freund's adjuvant with heat-killed Mycobacterium tuberculosis. Immunization was performed at four sites, followed by a booster injection of MuSK on the 28th day. This adjuvant with M. tuberculosis enables activation of the immune system through TLR4 and enhanced phagocytosis of the administered antigen. This article comprehensively details the development and characterization of MuSK-EAMG from inception to conclusion.
Introduction
Myasthenia gravis (MG) is an autoimmune disease that develops through T-cell-dependent, antibody-mediated mechanisms. It is primarily caused by antibodies against nicotinic acetylcholine receptors (AChR) on the postsynaptic membrane of the neuromuscular junction (NMJ) in 80%-85% of patients, and by antibodies against muscle-specific kinase (MuSK) in approximately 5% of patients as well as other NMJ proteins. MG has become a prototype for autoimmune disorders and a model for understanding postsynaptic function1. Animal models of autoimmune disorders can be divided into two main categories: (1) Spontaneous models, in which animals naturally develop an autoimmune disease, and (2) Induced models, where the autoimmune disease is artificially mimicked and replicated. Studies on myasthenia gravis (MG) have demonstrated that both active and passive immunization can induce the disease, contributing significantly to the understanding of antibody-mediated conditions2.
Passive transfer is a highly effective method for evaluating the acute effects of autoantibody-mediated diseases and has been widely used to study patient-derived antibodies in MG. This approach has been beneficial in broadening understanding of the immunological factors underlying the disease. For example, passive transfer studies have shown the pathogenic impact of anti-MuSK IgG4 on the reduction of AChR clusters3. However, there are some limitations to the passive transfer model, such as the functional differences between human and rodent IgG and immune systems and the insufficiency of the passive transfer model to mimic the initial activation mechanisms of the anti-MuSK autoimmunity occurring in lymphoid tissues.
On the other hand, a potential limitation of the immunization studies is immunogenetic variability among different mouse strains4. For example, while C57BL/6 (B6) mice are susceptible to active immunization with AChR, AKR/J mice are resistant. Therefore, when creating an EAMG animal model, it is crucial to correctly select the animal species, the immunization method, and protocol content to accurately reflect the disease5.
Additionally, using the target antigen as a whole protein often results in high antibody titers. However, not all antibodies may cross-react with the mouse antigen or produce disease-causing epitopes. Therefore, active immunization models do not always accurately reflect human pathology. Nevertheless, when they successfully create an appropriate clinical and physiological phenotype, these models provide a long-term platform for testing experimental therapies.
Clinical studies indicate divergent disease mechanisms and therapeutic requirements for MuSK-MG, highlighting the need for further identification of the specific pathogenic features of this MG subtype4,5,6. Previous active immunization-based MuSK EAMG studies showed predominant involvement of Th2 type immunity and anti-mouse IgG1 in MuSK autoimmunity and identified a number of potential treatment modalities (e.g., teriflunomide, mesenchymal stem cell, FCRLB shRNA) for human MuSK MG7,8,9. This demonstrated the significance of the MuSK EAMG model in testing new therapeutic targets and investigating MuSK MG pathophysiology.
In this article, procedures for inducing the animal model, monitoring disease progression, and validation of EAMG induction have been detailed. The clinical evaluation involved monitoring weight, posture, grip strength, and clinical scores by an observer. Mice were euthanized 28 days after the second immunization, and various tissues, including blood, hind limb muscle, spleen, and axillary and inguinal lymph nodes, were collected to confirm disease establishment. Anti-MuSK antibodies were quantified in sera using the ELISA method. Additionally, immunofluorescent staining was performed on muscle tissues to visualize deposits at the neuromuscular junction. To demonstrate and compare the clinical and immune responses in mouse groups with different MuSK EAMG susceptibility, mice treated with KCNS3 shRNA showed proinflammatory action (unpublished), and FCRLB shRNA showed anti-inflammatory action9, as determined in previous studies.
Protocol
The protocol was approved by the Istanbul University Local Ethics Committee for Animal Experiments (HADYEK) with the decision number 2020/29. In our previous studies7,8,9, the EAMG model was induced in 8-10-week-old BALB/c or B6 mice via active immunization with the MuSK protein. This article presents exemplary data obtained from different experiments using MuSK-immunized BALB/C mice (4-8 mice per group). The reagents and the equipment used are listed in the Table of Materials.
1. Production and preparation of human MuSK for immunization
- Clone the human MuSK extracellular domain amino acids 24-495 (NCBI Reference Sequence: NP_005583.1) into the pPIC9 vector.
- Secrete expression in the yeast Pichia pastoris (strain GS115) system.
- Induce expression by the addition of methanol (2.5% v/v) into the growth medium.
- Add A C-terminal 6xHIS tag for purification purposes.
- Express the protein as a secreted glycosylated protein and purify it under native conditions. Dialyze the culture medium against 50 mM phosphate buffer pH 8.0, 300 mM NaCl.
- Continue with nickel-ion affinity chromatography using Ni2+/nitrilotriacetate agarose (Ni-NTA). Store the purified protein after the addition of 10% glycerol at -80 °C, where it is stable for at least two years10.
NOTE: The levels of expression, estimated after Ni-NTA purification, are approximately 0.4 mg/L culture. No other protein impurities were detected in the samples analyzed by SDS-PAGE. - Before immunization, verify the purity of the isolated extracellular domain of the MuSK protein by gel electrophoresis (Supplementary Figure 1).
- Prepare the MuSK for each mouse at a concentration of 45 µg/100 µL PBS.
- Homogenize (emulsify) the MuSK in a 1:1 ratio with PBS (100 µL) and Complete Freund's Adjuvant (CFA-100 µL) containing Mycobacterium tuberculosis H37Ra (10 mg/10 mL) (total volume of the emulsion is 200 µL per mouse).
2. Anesthesia and immunization procedure
- Before immunization, dilute the propofol in PBS (1:5 ratio).
- Administer intraperitoneally at 50 mg/kg per mouse.
NOTE: Isoflurane can also be used for anesthesia via inhalation (following institutionally approved protocols). The initial concentration is typically set at 3%-5% with an oxygen flow rate of 1-2 L/min, while the maintenance concentration is usually 1%-3% with an oxygen flow rate of 0.5-1 L/min. - First Immunization: Inject a total of 45 µg/200 µL prepared MuSK in CFA subcutaneously into the shoulders and inner hind paws (approximately 11.25 µg/50 µL for each part).
- Second Immunization: Inject a total of 45 µg/200 µL prepared MuSK in CFA subcutaneously into the shoulders and hips (approximately 11.25 µg/50 µL for each part).
NOTE: Administer the injections twice at a 28-day interval to establish the model. Intramuscular administration is associated with muscle pain, which may interfere with clinical weakness assessment. Since EAMG is a muscle disease, utilization of intramuscular injection may induce pain-related non-myasthenic weakness and thus act as a confounder. A control group immunized with only CFA (without MuSK) is recommended.
3. Clinical scoring
- Exercise the mice by gently dragging them 40 times across the top grid of a cage as they attempt to grip the grid to induce fatigue, as symptoms of myasthenia gravis in mice become more pronounced after exercise and fatigue.
- After exercising, carefully observe the mice for changes in activity, weight, and muscle strength. Assign appropriate scores based on these observations to guide the evaluation criteria.
NOTE: Score 0: Mice remain active and continue to explore their environment; Score 1: A hunched posture is observed after exercise, but mice return to normal activity and sociability. Fur grooming is generally maintained. Score 2: A hunched posture is visible even before exercise and becomes more pronounced after exercise. A decrease in self-grooming and activity is noted. Score 3: A dramatic hunched posture is observed before and after exercise. There is a significant decrease in movement, sociability, and muscle strength, accompanied by a weight loss of 1-2 grams every 2-3 days. Dehydration occurs, making it difficult for mice to reach water and food. Dehydration is identified by the skin not returning quickly after being pinched and changes in feces. Mice in pain are characterized by squinting and a hunched posture. Mice showing signs of severe pain and weight loss exceeding 20% are sacrificed. Score 4: The mouse is found dead in the cage. The deceased mouse should be removed immediately, and the cage should be changed5. - Check the mice daily as symptoms rapidly progressed approximately 10 days after the second immunization. Perform clinical scoring and measurements weekly for the first 28 days and then twice a week.
- Perform weight measurement.
NOTE: Weight measurement provides a crucial parameter for tracking disease progression. Due to the high metabolic rates of mice, body weight can vary significantly. It is important to use the same scale for all measurements and to conduct these measurements at the same time of day for consistency. - Perform muscle strength measurement. Use a horizontal dynamometer with a grid wire to measure muscle strength.
- Exercise the mice for clinical scoring by gently dragging them over the cage 40 times to induce fatigue.
- Immediately place each mouse on the grid of the dynamometer and gently pull by the tail, ensuring that all paws are firmly gripping the grid. Consider only measurements where the mice grasp the grid with all four paws.
NOTE: Try to apply an equal amount of force during each measurement, and it is recommended that the same researcher conducts all measurements to maintain reliability and reduce variability. Since fatigability is the hallmark of MG weakness, a series of grip strength tests should be performed without measuring grip strength. Afterward, seven measurements were performed for each mouse, and the maximum and minimum values were discarded. The average of the remaining five measurements is calculated to ensure reliable results.
4. Tissue sample preparation
NOTE: Sacrifice the mice 28 days after the second immunization following institutionally approved protocols. Collecting blood, muscle, spleen, and lymph nodes from the sacrificed mice will be beneficial for further investigations.
- Cardiac blood collection
NOTE: To collect cardiac blood, anesthetize the mice using a proper anesthetic (e.g., propofol) approved by the ethical committee. Cardiac puncture requires anesthesia and is a terminal procedure, meaning animals must be euthanized immediately afterward.- After deeply anesthetizing the rat, place it on its back, open the abdomen, and locate the heart, approximately 1 cm above the lowest rib and slightly to the right.
- Using a 25-35 G needle, draw blood carefully from the left ventricle at a 45-degree angle without moving the syringe to avoid complications11.
- Transfer the blood samples to dry tubes for serum separation and/or to EDTA tubes for RNA isolation- if planned.
- Separate the serum by centrifugation and keep the serum samples at -20 °C until it is used.
- Muscle sample preservation and preparation
- Collect anterior tibialis muscle11,12,13. Rinse with ice-cold PBS.
- Place samples in cryotubes, immediately plunge into liquid nitrogen-cooled isopentane at -20 °C, and store in a -80 °C freezer.
NOTE: Samples should be snap-frozen for more accurate results in experiments. - Place the tissues vertically on a sectioning mount; a cork can be used. Embed the samples for immunofluorescence staining in OCT (Optimal Cutting Temperature compound).
- Allow the tissue to float on liquid nitrogen-cooled isopentane. Store in a -80 °C freezer until sectioning with a cryostat.
5. Evaluation of neuromuscular junctions via immunofluorescence labeling
- Cryostat sectioning and fixation
- Section the frozen tissues embedded in OCT at -24 °C to a thickness of 7 µm using a cryostat.
- Fix the sections in acetone cooled to -20 °C. Wash with PBS for 5 min.
- Wash again PBS containing 0.4% Triton X (PBS-T) for 10 min.
NOTE: A permeabilization step can be performed to correct the conformation of molecules affected by fixation, ensuring more accurate binding. Permeabilization involved treatment with PBS containing 1% FBS for 10 min and PBS-T for another 10 min. - Block the sections with PBS-T containing 10% FBS for 30 min to prevent nonspecific binding.
- Immunofluorescence staining
NOTE: For staining, the following antibodies can be used: C3, IgG, Acetylcholine receptor marker α-bungarotoxin.- Dilute the selected antibodies in PBS-T containing 1% FBS.
- Incubate in the dark at room temperature for 2.5 h.
- Wash the sections with PBS-T containing 1% FBS.
- Counterstain with DAPI.
- Store the sections until examination under a fluorescence microscope in a dark and humid environment at 4 °C.
- Perform imaging and analysis.
NOTE: Bungarotoxin (BTX)-positive neuromuscular junctions in each section should be counted using a fluorescence microscope. Capture images at 20x magnification. For analysis, BTX and C3 or IgG-positive neuromuscular junctions were counted manually under the microscope. The percentage of double-positive junctions relative to the total BTX-labeled junctions in serial sections should be used for analysis.
6. Western blot
- Protein isolation and quantification
- Use muscle samples that are snap-frozen.
- Prepare lysis buffer with protease and phosphatase inhibitors.
- Add 0.5 mm zirconium oxide beads equal to the sample weight and 2x the volume of the lysis buffer.
- Homogenize samples using a homogenizer.
- Centrifuge lysate at 12,000 x g for 15 min at 4 °C.
- Collect the supernatant containing the protein lysate.
- Use a BCA assay kit or Bradford reagent to quantify protein concentration.
- Prepare protein samples to the desired concentration with lysis buffer. 25 μg protein per well is efficient for showing AChR.
- SDS-PAGE gel electrophoresis
- Mix protein samples with 4x Laemmli buffer.
- Heat the samples at 95 °C for 5 min to denaturate.
- Load equal amounts of protein and a protein ladder into wells of an SDS-PAGE gel.
- Run the gel at 200 V for 30 min (time may vary between different power supplies).
- Protein transfer
- For semi-dry transfer with nitrocellulose membrane, wet every component with a cold transfer buffer.
- Set up the transfer sandwich: sponge, filter paper, gel, membrane, filter paper, sponge.
NOTE: Ensure no bubbles are present between layers. The transfer program should be selected according to the manufacturer's instructions (see Table of Materials).
- Blocking and antibody incubation
- Block the membrane in 5% non-fat dry milk or BSA in TBST for 1 h at room temperature with gentle rocking.
- Incubate membrane with primary antibody (anti-AChR) diluted in 2.5% blocking buffer overnight at 4 °C with gentle rocking.
- Wash the membrane 3 times for 10 min each in TBST.
- Incubate membrane with HRP-conjugated secondary antibody (IgG HRP) diluted in 2.5% blocking buffer for 1 h at room temperature.
- Wash the membrane 3 times for 10 min each in TBST.
- Detection and imaging
- Apply ECL substrate to the membrane according to the manufacturer's instructions.
- Capture the chemiluminescent signal using an imaging system.
- Analyze bands using imaging software.
NOTE: Always keep proteins and reagents on ice to prevent degradation. Ensure equal loading by running a housekeeping protein (e.g., beta-actin, alpha-tubulin, or GAPDH) as a control. Optimize antibody concentrations and incubation times for best results. Showing that AChR protein is less expressed in MuSK-immunized mice is crucial.
7. Homemade Anti-MuSK IgG ELISA
- Prepare MuSK antigen at a concentration of 0.5 µg per well in 100 µL of carbonate bicarbonate buffer (Plate Coating).
- Dispense 100 µL of the antigen solution into each well of an immunoassay plate.
- Incubate the plate overnight at 4 °C.
- Wash the plate with PBS containing 0.5% Tween 20 (washing solution).
- Incubate the plate with PBS containing 5% FBS (blocking solution) for 90 min at 4 °C to block nonspecific binding sites (Blocking).
- Since optimization studies showed high levels of MuSK-IgG, dilute the serum samples 1/50,000 in blocking solution.
- Without washing after blocking, add the diluted serum samples to the wells.
- Incubate the plate at 37 °C for 90 min.
- Wash the plate three times with the washing solution.
- Dilute HRP-conjugated anti-mouse IgG secondary antibody (ab97023) 1/5000 in blocking solution.
- Add 100 µL of the diluted secondary antibody to each well.
- Incubate the plate at 37 °C for 90 min.
- Wash the plate three times with the washing solution.
- Add 100 µL of TMB substrate to each well and observe the color change.
- Stop the reaction at an appropriate time using 2 M H2SO4.
- Measure the optical density at 450 nm using a spectrophotometer.
- Perform all samples in duplicates and on the same plate for consistency.
NOTE: Optical density values should be used for analysis as no standard sample dilutions were available. There should be no color change in the negative control wells (blank). A rapid color change is expected, so the stop solution should be kept nearby to immediately stop the reaction in the wells.
Results
In evaluating and validating the MuSK Experimental Autoimmune Myasthenia Gravis (EAMG) model, several key parameters and experimental results are critical to demonstrate the successful induction and characterization of the disease model. Below are the representative results that confirm the establishment of the MuSK EAMG model.
Clinical scoring
Mice are monitored and scored for clinical symptoms of myasthenia gravis using a standardized clinical scoring system. This scoring includes evaluating muscle strength, posture, and general physical condition. An increase in clinical scores over time, as compared to baseline and control mice, confirms the progression and severity of the disease in the experimental group. The clinical score data should show a clear and progressive increase, highlighting the model's effectiveness in mimicking human MuSK myasthenia gravis (Figure 1).
Grip strength and body weight measurements
Functional assessment of the mice includes measuring grip strength and body weight. These parameters are critical for evaluating the clinical manifestation of MuSK EAMG. Results should demonstrate a significant reduction in grip strength and body weight in the experimental group compared to the controls. These reductions reflect the muscle weakness and overall physical decline associated with the disease (Figure 2).
Serum Anti-MuSK antibodies
One of the primary indicators of the successful induction of the MuSK EAMG model is the presence and increase of anti-MuSK antibodies in the serum. The levels of specific antibody quantified using enzyme-linked immunosorbent assay (ELISA). Results should show a significant increase in anti-MuSK antibodies compared to baseline levels and control groups, confirming the immune system's response to the immunization protocol. As illustrated in Figure 3, mice immunized with Complete Freund's Adjuvant (CFA) exhibit negligible levels of anti-MuSK antibodies. In contrast, those immunized with MuSK display the highest antibody concentrations. Two treatment options were evaluated in this context. Treatment 1 results in significantly lower anti-MuSK antibody levels compared to the MuSK-immunized group, indicating its superior efficacy. Conversely, Treatment 2 shows higher antibody concentrations than Treatment 1, demonstrating its relatively lesser effectiveness. Therefore, the data suggest that Treatment 1 is more efficacious in reducing anti-MuSK antibody levels than Treatment 2 (Figure 3).
Immunofluorescent staining for C3 and IgG deposits
Immunofluorescent staining of muscle sections is employed to detect the presence of C3 and IgG deposits at the neuromuscular junction. Positive staining indicates the deposition of complement component 3 (C3) and immunoglobulin G (IgG), which are hallmarks of the autoimmune attack in MuSK EAMG. Representative images should display prominent fluorescence signals at the neuromuscular junctions, corroborating the pathological immune response in the muscle tissue. As illustrated in Figure 3, the presence of C3 or IgG accumulation in muscle sections is confirmed through double-positive staining with BTX and either C3 and/or IgG. This double-positive staining indicates colocalization and provides strong evidence of immune complex deposition at the neuromuscular junctions, validating the pathological changes associated with the MuSK EAMG model (Figure 4).
Western blot analysis of AChR protein in muscle samples
Western blot analysis is performed on muscle samples to evaluate the expression levels of the acetylcholine receptor (AChR) protein. In the MuSK EAMG model, there is an expected decrease in AChR protein levels due to the autoimmune attack. Representative results from the Western blot should show a marked reduction in AChR bands' intensity in the immunized mice, indicating successful model induction (Figure 5 and Supplementary Figure 2).
The successful establishment and evaluation of the MuSK EAMG model are demonstrated by (1) A significant increase in serum anti-MuSK antibody levels, (2) Presence of C3 and IgG deposits in muscle sections as shown by immunofluorescent staining, (3) Decreased grip strength and body weight measurements, (4) Reduced AChR protein levels in muscle samples confirmed by Western blot analysis, (5) Elevated clinical scores indicate disease progression. These representative results collectively validate the MuSK EAMG model as a reliable and effective tool for studying MuSK myasthenia gravis and exploring potential therapeutic interventions.
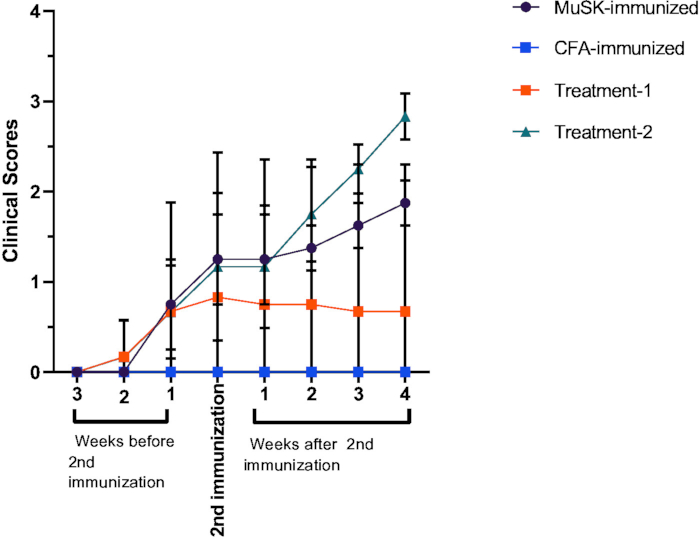
Figure 1: Clinical scores. Representative clinical scores of CFA-immunized, MuSK-immunized, and two different treatment-receiving groups (FCRLB-silencing shRNA (treatment 1) and KCNS3-silencing shRNA (treatment 2)) of MuSK-immunized mice. FCRLB and KCNS3 shRNAs were administered i.p. only once at a concentration of 100.000 infectious units 3 h after the second immunization. Note that FCRLB-shRNA treated group has lower average clinical scores than KCNS3-shRNA treated group, suggesting that FCRLB acts in favor of MuSK-EAMG induction, whereas KCNS3 has a preventive action in the MuSK-EAMG model (unpublished data). (***) indicates p < 0.001, (**) indicates p < 0.01 by repeated measures ANOVA. Error bars represent standard deviation (SD). Please click here to view a larger version of this figure.
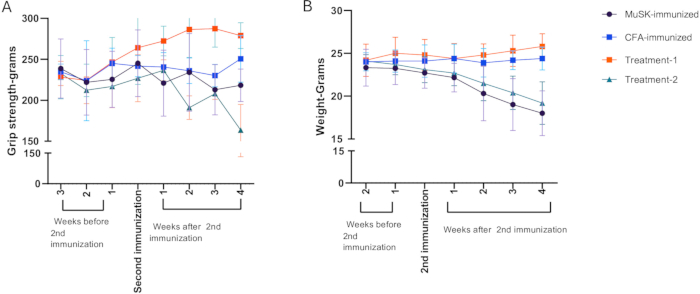
Figure 2: Grip strength (A) and body weight (B) measurements of representative groups. Note that the FCRLB silencing shRNA (treatment 1) treated group has higher average grip strength and weight values than the KCNS3 silencing shRNA treated group (treatment 2), suggesting that FCRLB acts in favor of MuSK-EAMG induction, whereas KCNS3 has a preventive action in the MuSK-EAMG model. (***) indicates p < 0.001, (**) indicates p < 0.01 by repeated measures ANOVA. Error bars represent standard deviation (SD). Please click here to view a larger version of this figure.
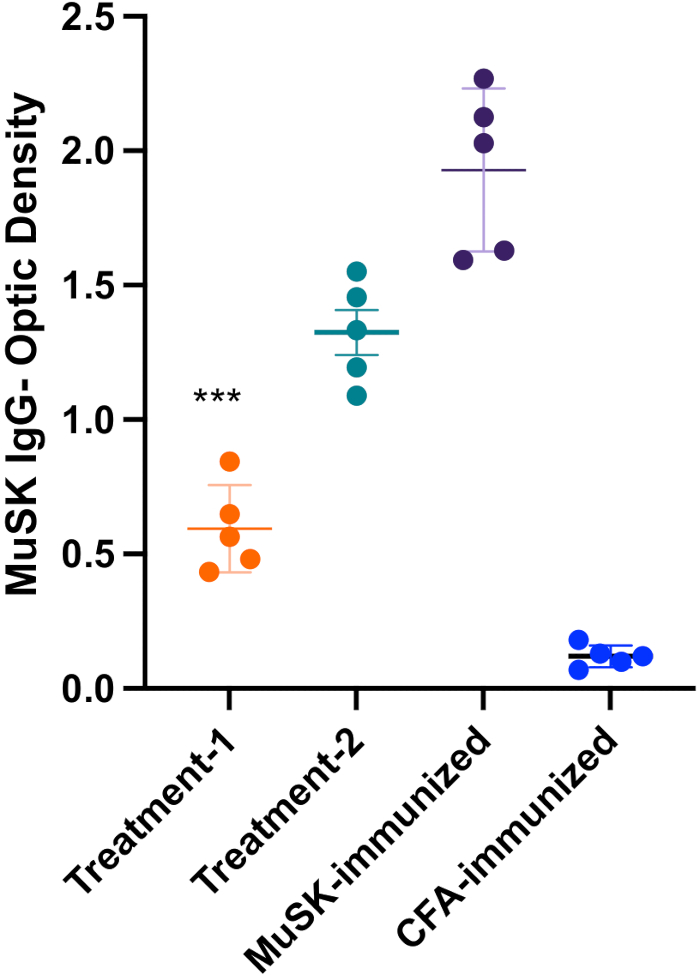
Figure 3: Representative results of serum anti-MuSK antibody levels in MuSK- (treatment-1, treatment-2, MuSK-immunized) and CFA-immunized mice. FCRLB-silencing shRNA (treatment 1) administration reduces anti-MuSK IgG levels compared to KCNS3-silencing shRNA (treatment 2) and non-treated MuSK-immunized mice. *** indicates p < 0.001 by ANOVA. Please click here to view a larger version of this figure.
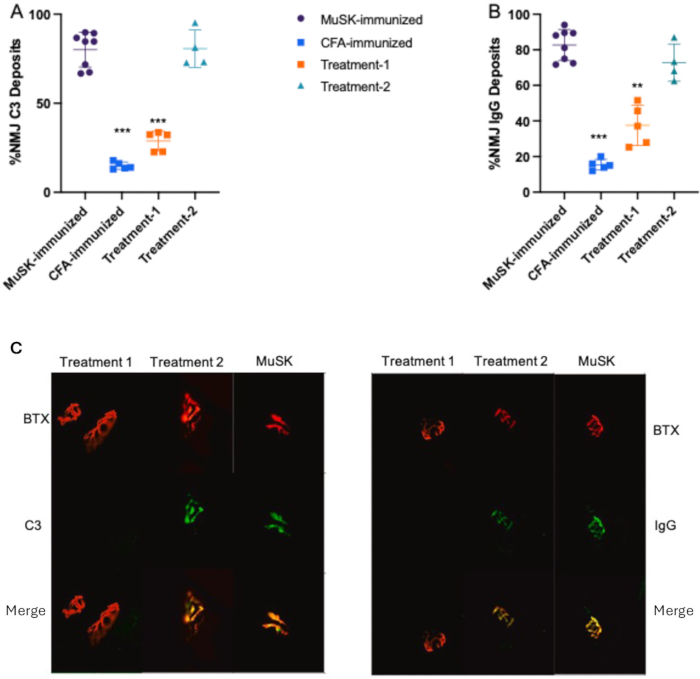
Figure 4: Immunofluorescent staining. Immunofluorescent stainings of muscle sections (A) C3 and (B) IgG deposits shown by immunofluorescent staining of muscle sections. (C) Representative images of IgG and C3 staining. Treatment 1 indicates FCRLB-silencing shRNA, which ameliorates MuSK-EAMG, and treatment 2 indicates KCNS3-silencing shRNA, which aggravates MuSK-EAMG (unpublished data). (***) indicates p< 0.001, (**) indicates p < 0.01 by ANOVA. BTX, bungarotoxin. Magnification: 20x. Please click here to view a larger version of this figure.
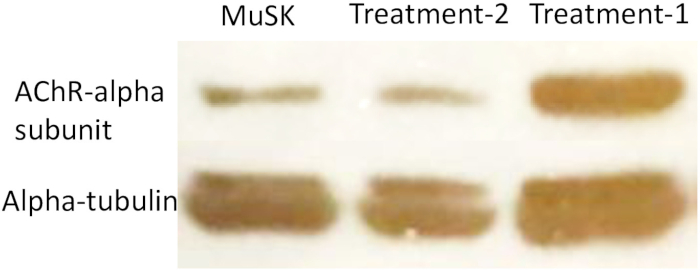
Figure 5: Representative image of AChR alpha subunit protein western blot results. Treatment 1 indicates FCRLB shRNA, which ameliorates MuSK-EAMG and prevents AChR loss, treatment 2 indicates KCNS3 shRNA, which aggravates MuSK-EAMG and reduces AChR expression. Please click here to view a larger version of this figure.
Supplementary Figure 1: SDS-PAGE analysis of purified human MuSK extracellular domain (MuSK-ECD). Following Ni-NTA elution, a sample of MuSK-ECD (15µg) was analyzed by SDS-PAGE. The molecular weight of MuSK-ECD is approximately 53 kDa. The higher apparent molecular weight seen on the gel is due to the glycosylation of the protein. Please click here to download this File.
Supplementary Figure 2: Western blot. Image of the entire Western blotting membrane with muscle samples of KCNS3 shRNA-, FCRLB shRNA-, non-treated mice for demonstration of AChR alpha subunit (around 53 kDa, upper row bands). Alpha-tubulin bands (lower row bands, around 50 kDa) were used as reference. Brain tissue was used as a negative control to show the specificity of the commercial antibody against the anti-muscle AChR alpha subunit. Please click here to download this File.
Discussion
Murine MuSK-EAMG mimics human MuSK-MG both in its clinical and immunopathogenic aspects in terms of muscle weakness, weight loss due to bulbar muscle weakness, circulating anti-MuSK antibodies, and reduced muscle AChR. As for milestones and anticipated timeline for this MuSK-EAMG model, clinical signs of muscle weakness should appear within the first week after the second immunization. Approximately 5% of mice may develop signs of disease after the first immunization. A >70% EAMG (at least grade 1) prevalence is expected after two immunizations. If the incidence of disease is lower, a third immunization may be administered7,14,15. MuSK-immunized mice receiving the MuSK protein in CFA in both immunizations yield slightly higher antibody and clinical responses than mice receiving MuSK in CFA and IFA in two succeeding immunizations, respectively14. Although this difference is minimal, CFA was used in both immunizations to achieve optimal results and higher EAMG prevalence. For the second immunization, injection sites were changed to the hips to introduce the antigen to the widest possible variety of superficial lymph nodes in two immunizations (axillary nodes-shoulder immunization, popliteal nodes-foot immunization, inguinal nodes-hip immunization). Secondly, since the foot pads get swollen after the first immunization, a different injection site, such as the hips, is required.
MuSK immunization may induce severe disease in mice, and mortality may ensue in a matter of 1-2 days; thus, mice should be observed daily. A 2-3 month commitment is required to complete an experiment and a month to perform various immunological parameters. Prevalence of MuSK-EAMG may show variations between 70%-90% even in most capable hands, depending on the type of autoantigen and genetic features of individual mice. Studies have shown that MuSK-EAMG is induced effectively in B6 and BALB/c mice; thus, the immunogenetic background of these mice is suitable for this model. Mouse strains carrying the H-2b (B6), H-2k, and H-2d (BALB/c) MHC haplotypes are susceptible to the development of MuSK-EAMG. Nevertheless, whether MuSK-EAMG can be induced in mouse strains with different MHC haplotypes should be further investigated.
It is well known that the same protein produced by different host cells may display different post-translational modifications and amino acid contents. These differences may result in variations in the pharmacokinetics, biological activity, and immunogenicity of the produced protein15. In all MuSK-EAMG studies, the extracellular domain of the MuSK protein produced in yeast has been utilized. Although a high prevalence of EAMG has been achieved with this product, it remains to be elucidated whether the MuSK antigen expressed by mammalian cells or specific peptides of the MuSK protein could induce a more robust MuSK-EAMG.
A significant distinction between MuSK-MG and MuSK-EAMG induced by immunization is the deposition of complement at the neuromuscular junction (NMJ) in mice with MuSK-EAMG9, whereas complement deposition in muscle tissue is not typically observed in MuSK-MG16. As a possible explanation, in the MuSK-EAMG model, IgG isotypes other than non-complement fixing IgG1 (mouse analog of human IgG4 and the dominant IgG in MuSK-EAMG in mice) may also be involved. As a matter of fact, previous studies have shown the involvement of mouse IgG2 and IgG3 in MuSK-EAMG14.
MuSK IgG isotypes induced by MuSK immunization could provide useful information for a better understanding of MuSK-EAMG. Previous reports have shown that mouse IgG1 is the predominant IgG isotype in both muscle specimens and circulation. Different from the passive transfer model of MuSK-EAMG, which is mainly induced by human anti-MuSK IgG4, the active immunization model of MuSK-EAMG is mediated predominantly by mouse IgG117. Unlike mouse IgG1, human IgG4 is capable of Fab-arm exchange, resulting in IgG4 antibodies composed of two different binding sites and, hence, a monovalent binding feature. Monovalent anti-MuSK IgG4 is more potent than the parental bivalent form18. The immunization-based MuSK-EAMG indicates that the bivalent anti-MuSK-IgG is also capable of inducing highly prevalent and severe EAMG.
MuSK MG patients harbor antibodies specific for different MuSK epitopes, with those specific for the Ig1 domain being more closely related to disease severity19. As a limitation, investigated antibodies to the entire extracellular domain of the MuSK protein and the immunodominant peptide of MuSK protein are not known in this model. Thus, it would be interesting to know if the MuSK-EAMG model recapitulates this aspect of the human disease.
So far, the active immunization-induced MuSK-EAMG model has been used in preclinical animal model studies of FCRLB silencing shRNA and teriflunomide8,9. Naturally, this model can be used to assess the efficacy of a plethora of treatment modalities in MuSK-MG. An attractive potential candidate in this context could be CAR-T cell therapy, which has been shown to be effective in AChR-MG patients20.
In brief, MuSK-EAMG induced by active immunization in mice provides a useful setting for dissecting the cellular and molecular mechanisms of MuSK-MG pathogenesis and designing specific therapies such as shRNA targeting specific genes, anti-inflammatory stem cells and immunomodulating drugs currently in use15,17,18.
Disclosures
There are no disclosures to declare.
Acknowledgements
We would like to acknowledge the support and contributions of Istanbul University Health Sciences Institute and the Aziz Sancar Institute of Experimental Medicine in the completion of this research.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 125I-α-bungarotoxin | Invitrogen | BTX T1175 | |
| 2-Methylbutane | Sigma-Aldrich | M32631 | |
| 40 μm Cell Strainer | NEST | 258369 | |
| 96 well Maxisorp plate | Sigma-Aldrich | M9410 | |
| Adjuvant Incomplete | Becton Dickinson & Co. | 263910 | |
| Anti-AChR alfa1 | Alomone | ANC-001 | |
| Anti-mouse IgG HRP | Abcam | ab97023 | |
| Bullet Blender Storm | Next Advance | Tissue homogenizer | |
| C3 | Novus | NB200-540G | |
| Carbonate-Bicarbonate Buffer | Merck | C3041 | |
| Cryostat | Leica | CM1860 | |
| Dynamometer Imada DST-50N | Muromachi | MK380Si | |
| Fluorescence microscope | Leica | DM4M | |
| Glass syringe with luer lock | ISOLAB | 094.92.005 | |
| IgG | Abcam | ab96871 | |
| Microplate Photometer, Multiskan FC | Thermo Scientific | 51119000 | |
| Mouse Surgical Kit | Kent Scientific Corparation | INSMOUSEKIT | |
| Mycobacterium tuberculosis H37Ra | Becton Dickinson & Co. | 231141 | |
| OCT Compound | Agar Scientific | AGR1180 | |
| Syringes, 1 mL | Becton Dickinson & Co. | 309625 | |
| Syringes, 2 mL | B. Braun | 7389 | |
| Universal animal restrainer | Merck | Z756911-1EA | |
| WesternBright Sirius-Western blotting detection kit | Advansta | K-12043-D10 | ECL |
References
- Keesey, J. A. A history of treatments for myasthenia gravis. Semin Neurol. 24, 5-16 (2004).
- Giannoccaro, M. P., Wright, S. K., Vincent, A. In vivo mechanisms of antibody-mediated neurological disorders: Animal models and potential implications. Front Neurol. 10, 1394(2020).
- Verschuuren, J. J. G. M., Plomp, J. J. Passive transfer models of myasthenia gravis with muscle-specific kinase antibodies. Ann N Y Acad Sci. 1413 (1), 111-118 (2018).
- Berman, P. W., Patrick, J. Linkage between the frequency of muscular weakness and loci that regulate immune responsiveness in murine experimental myasthenia gravis. J Exp Med. 152 (3), 507-520 (1980).
- Kusner, L. L., et al. Guidelines for pre-clinical assessment of the acetylcholine receptor-specific passive transfer myasthenia gravis model-recommendations for methods and experimental designs. Exp Neurol. 270, 3-10 (2015).
- Koneczny, I., et al. IgG4 autoantibodies in organ-specific autoimmunopathies: Reviewing class switching, antibody-producing cells, and specific immunotherapies. Front Immunol. 13, 834342(2022).
- Ulusoy, C., et al. Dental follicle mesenchymal stem cell administration ameliorates muscle weakness in MuSK-immunized mice. J Neuroinflammation. 12, 231(2015).
- Yilmaz, V., et al. Effects of teriflunomide on B cell subsets in MuSK-induced experimental autoimmune myasthenia gravis and multiple sclerosis. Immunol Invest. 50 (6), 671-684 (2021).
- Koral, G., et al. Silencing of Fcrlb by shRNA ameliorates MuSK-induced EAMG in mice. J Neuroimmunol. 383, 578195(2023).
- Trakas, N., Zisimopoulou, P., Tzartos, S. J. Development of a highly sensitive diagnostic assay for muscle-specific tyrosine kinase (MuSK) autoantibodies in myasthenia gravis. J Neuroimmunol. 240-241, 79-86 (2011).
- JoVE, Science Education Database. Blood withdrawal I. JoVE Sci Educ. , (2023).
- Peretti, A. L., et al. Action of vanillin (Vanilla planifolia) on the morphology of tibialis anterior and soleus muscles after nerve injury. Einstein (Sao Paulo). 15 (2), 186-191 (2017).
- Van Der Meulen, J. H., Kuipers, H., Stassen, F. R., Keizer, H. A., Van Der Vusse, G. J. High energy phosphates and related compounds, glycogen levels and histology in the rat tibialis anterior muscle after forced lengthening and isometric exercise. Pflugers Arch. 420 (3-4), 354-358 (1992).
- Kucukerden, M., et al. MuSK-induced experimental autoimmune myasthenia gravis does not require IgG1 antibody to MuSK. J Neuroimmunol. 295-296, 84-92 (2016).
- Ulusoy, C., et al. Preferential production of IgG1, IL-4 and IL-10 in MuSK-immunized mice. Clin Immunol. 151 (2), 155-163 (2014).
- Mori, S., et al. Antibodies against muscle-specific kinase impair both presynaptic and postsynaptic functions in a murine model of myasthenia gravis. Am J Pathol. 180 (2), 798-810 (2012).
- Wu, B., Goluszko, E., Huda, R., Tuzun, E., Christadoss, P. Experimental autoimmune myasthenia gravis in the mouse. Curr Protoc Immunol. Chapter 15, Unit 15.23. , (2011).
- Klooster, R., et al. Muscle-specific kinase myasthenia gravis IgG4 autoantibodies cause severe neuromuscular junction dysfunction in mice. Brain. 135 (Pt 4), 1081-1101 (2012).
- Vergoossen, D. L. E., et al. Functional monovalency amplifies the pathogenicity of anti-MuSK IgG4 in myasthenia gravis. Proc Natl Acad Sci U S A. 118 (13), e2020635118(2021).
- Oh, S., et al. Precision targeting of autoantigen-specific B cells in muscle-specific tyrosine kinase myasthenia gravis with chimeric autoantibody receptor T cells. Nat Biotechnol. 41 (9), 1229-1238 (2023).
Reprints and Permissions
This article has been published
Video Coming Soon