This study evaluates a nurse-led gastrointestinal tolerability–adapted osteoporosis care pathway after hip fracture. The pathway uses risk stratification, regimen selection, structured follow-up, and trigger-based optimization to improve treatment continuity, adherence, and outcome capture over 24 months.
Research Article
Nurse-Led Gastrointestinal Tolerability–Adapted Osteoporosis Care After Hip Fracture: 24-Month Implementation Outcomes
In This Article
Summary
Abstract
Older adults remain at high risk for subsequent fragility fractures after hip fracture; however, post-discharge anti-osteoporosis therapy is frequently delayed, interrupted, or discontinued. This single-center, non-randomized longitudinal implementation study evaluated a nurse-led gastrointestinal (GI) tolerability–adapted osteoporosis care pathway for older adults following surgical treatment of hip fracture. A total of 147 participants were enrolled, including 73 in the nurse-led pathway group and 74 in the usual care group. The intervention incorporated discharge-time GI tolerability risk stratification, safety verification, tolerability-adapted regimen selection, standardized patient education, structured follow-up at 1 week and 1, 3, 6, 12, 18, and 24 months, and predefined criteria for treatment reassessment. Outcomes included implementation fidelity, timely treatment initiation, medication adherence measured by the proportion of days covered (PDC), treatment persistence, changes in bone mineral density (BMD), GI adverse events, and first confirmed subsequent fragility fracture. Compared with usual care, the nurse-led pathway achieved higher rates of GI risk stratification, education checklist completion, safety laboratory review, timely therapy initiation, follow-up completion, and dual-energy X-ray absorptiometry (DXA) assessment. Mean PDC and the proportion of participants achieving a PDC ≥0.80 were consistently higher in the intervention group throughout the 24-month follow-up. Lumbar spine and total hip BMD demonstrated greater improvements in the pathway group, whereas femoral neck BMD changes were smaller. Time-to-event analyses for subsequent fragility fractures favored the intervention group but should be interpreted with caution, given the limited number of events and the non-randomized study design. These findings demonstrate that a nurse-led GI tolerability–adapted osteoporosis care pathway is feasible and may improve treatment continuity following hip fracture. Larger multicenter randomized studies are warranted to confirm its effects on BMD and refracture outcomes.
Introduction
Hip fractures in older adults represent a major public health challenge because they are associated with functional decline, disability, institutionalization, and increased mortality1. Following an initial hip fracture, the risk of a subsequent fragility fracture is particularly high in the early post-fracture period, making secondary fracture prevention an essential component of long-term recovery2. Current clinical guidelines recommend incorporating anti-osteoporosis pharmacotherapy into post-fracture management; however, treatment initiation and long-term continuation remain inconsistent after hospital discharge3. This implementation gap limits the transition from acute surgical care to sustained fracture-prevention management.
The effectiveness of anti-osteoporosis therapy depends on maintaining adequate medication exposure over time. Improvements in bone mineral density (BMD) and reductions in fracture risk generally require sustained adherence and persistence rather than treatment initiation alone4. Poor adherence is common in osteoporosis management and is associated with diminished therapeutic effectiveness5. Medication coverage below commonly accepted adherence thresholds has been linked to an increased risk of subsequent fractures in real-world studies6. Consequently, adherence serves not only as a key process-of-care indicator but also as an intermediate determinant of skeletal outcomes7. Maintaining long-term adherence is particularly challenging after hip fracture because recovery is frequently complicated by frailty, polypharmacy, caregiver dependence, limited mobility, and fragmented post-discharge follow-up8.
Gastrointestinal (GI) intolerance represents an important barrier to sustained anti-osteoporosis therapy. Oral bisphosphonates require specific administration conditions and may be poorly tolerated by older adults with gastroesophageal reflux symptoms, dysphagia, postural limitations, constipation, or a history of upper GI disease9. GI symptoms may result in missed doses, unsupervised treatment interruptions, or permanent discontinuation10. These problems may remain undetected when follow-up is inconsistent or when medication refill information is dispersed across hospital and community pharmacy systems. A structured care pathway that identifies GI risk before discharge and links signals of intolerance to timely reassessment of treatment may help reduce avoidable interruptions in therapy.
Nurse-led fracture liaison services and post-fracture care models have been shown to improve osteoporosis assessment, patient education, treatment initiation, and care coordination following fragility fractures11. Nurses are well-positioned to deliver structured education, monitor symptoms, communicate with caregivers, track medication refills, and coordinate physician or pharmacist reassessments when treatment-related barriers arise12. However, although many post-fracture care models emphasize diagnosis and treatment initiation, relatively few incorporate GI tolerability as a structured component of regimen selection and longitudinal follow-up13. Integrating GI risk stratification with ongoing adherence monitoring may be particularly valuable for older adults recovering from hip fractures, who require prolonged anti-osteoporosis therapy but may have difficulty tolerating complex oral treatment regimens.
Accordingly, this study evaluated a nurse-led, GI tolerability–adapted anti-osteoporosis care pathway for older adults following surgical treatment of hip fracture. The pathway incorporated discharge-time GI risk assessment, safety verification, tolerability-adapted treatment selection, standardized patient education, structured longitudinal follow-up, and predefined criteria for treatment optimization. The study assessed implementation fidelity, medication adherence and persistence, changes in bone mineral density, GI adverse events, and the occurrence of a first subsequent fragility fracture over 24 months. Because treatment allocation was based on implementation of the care pathway rather than randomization, analyses of subsequent fracture outcomes were considered exploratory and hypothesis-generating rather than confirmatory.
Protocol
The study was approved by the Ethics Committee of Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University (Approval ID: 2026(115)). Written informed consent was obtained from all participants or their legally authorized representatives before enrollment. All procedures were conducted in accordance with the Declaration of Helsinki and institutional guidelines for clinical research involving human participants.
Study design and setting
This single-center, non-randomized, parallel-group controlled implementation study evaluated a nurse-led gastrointestinal (GI) tolerability–adapted anti-osteoporosis care pathway for older adults following surgical treatment of hip fracture. The study was conducted at Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University, between January 2021 and December 2024. Participants were followed for 24 months after hospital discharge. The study was reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines14. Participant screening, group allocation, follow-up schedule, and analysis-set construction are summarized in Figure 1. The prespecified outcome definitions and 24-month assessment schedule are summarized in Supplementary Table 1.
Participants were allocated based on the implementation of the nurse-led pathway rather than by randomization. Patients admitted before pathway implementation (January 2021–December 2022) received usual care, whereas those admitted after implementation (January 2023–December 2024) were managed using the nurse-led pathway. To minimize temporal bias, identical eligibility criteria, follow-up schedules, outcome definitions, DXA assessment windows, adherence calculations, and refracture adjudication procedures were applied to both groups. The calendar period was included in the adjusted and sensitivity analyses.
Participants
Consecutive inpatients aged ≥65 years admitted with a low-energy femoral neck or intertrochanteric hip fracture were screened for eligibility. Low-energy fractures were defined as fractures resulting from a fall from standing height or lower.
Participants were eligible if they were ≥65 years of age, underwent surgical treatment for a low-energy femoral neck or intertrochanteric fracture, survived to hospital discharge, were considered eligible for anti-osteoporosis therapy after assessment of renal function, corrected calcium, and vitamin D status, had complete baseline clinical and medication data, were able to participate in follow-up directly or through a caregiver, and provided written informed consent.
Participants were excluded if they sustained high-energy trauma, had pathological fractures secondary to malignancy or metabolic bone disease other than osteoporosis, had an expected survival of <6 months, had severe renal impairment (estimated glomerular filtration rate <30 mL/min/1.73 m2), uncorrected hypocalcemia, active upper GI bleeding, severe esophageal stricture, unstable gastrointestinal disease requiring urgent treatment, prior anti-osteoporosis therapy for >3 months during the preceding year, lacked reliable follow-up or caregiver support, or declined participation.
Baseline assessment
Baseline assessments were completed during the index hospitalization, preferably within 48 h before discharge. Demographic and clinical variables included age, sex, body mass index, fracture type, surgical procedure, time from admission to surgery, length of hospital stay, smoking status, alcohol consumption, previous fragility fracture, comorbidities, medication history, caregiver availability, and baseline GI risk factors. Comorbidity burden was assessed using the Charlson Comorbidity Index, and frailty was evaluated using the Clinical Frailty Scale.
Baseline laboratory investigations included serum calcium, albumin, corrected calcium, phosphate, creatinine, estimated glomerular filtration rate, alkaline phosphatase, 25-hydroxyvitamin D, and parathyroid hormone, where available. Medication review focused on nonsteroidal anti-inflammatory drugs, antiplatelet agents, anticoagulants, proton pump inhibitors, glucocorticoids, sedatives, and previous anti-osteoporosis medications.
Bone mineral density (BMD) was assessed using dual-energy X-ray absorptiometry (DXA) before discharge whenever feasible. If pre-discharge DXA could not be performed, scanning was completed within 4–6 weeks after discharge and considered the baseline assessment. Measurements were obtained at the lumbar spine, femoral neck, and total hip, with the contralateral non-fractured hip preferentially selected for hip measurements.
Usual care
Participants assigned to the usual-care group received routine perioperative management, standard discharge counseling, physician-directed anti-osteoporosis therapy, and routine outpatient follow-up in accordance with institutional practice. Structured GI risk stratification, nurse-led treatment selection, proactive refill monitoring, and predefined treatment-modification algorithms were not incorporated into usual care.
Nurse-led GI tolerability–adapted pathway
The nurse-led pathway was initiated before discharge and continued throughout the 24-month follow-up period. A specialist osteoporosis nurse coordinated care among orthopedic surgeons, geriatricians or endocrinologists, pharmacists, rehabilitation staff, DXA and laboratory services, and community healthcare providers. The workflow for GI risk assessment, treatment selection, follow-up, and regimen modification is illustrated in Figure 2.
Before discharge, GI tolerability was categorized as low, moderate, or high risk according to predefined clinical criteria (Supplementary Table 2). Risk classification incorporated gastrointestinal history, swallowing ability, ability to remain upright after medication administration, concomitant medications, and current GI symptoms.
Treatment selection was individualized according to GI risk, renal function, corrected calcium concentration, 25-hydroxyvitamin D status, fracture risk, patient preference, and anticipated follow-up compliance. Patients at low GI risk were preferentially prescribed oral bisphosphonates with standardized administration instructions. Patients at moderate risk received oral therapy only when administration requirements could be reliably followed; otherwise, non-oral antiresorptive therapy was recommended. Patients classified as high GI risk preferentially received intravenous zoledronic acid or subcutaneous denosumab after confirmation of treatment safety and physician approval. Calcium and vitamin D supplementation were recommended unless contraindicated.
Before discharge, the specialist nurse completed a standardized education checklist covering medication administration, dosing schedule, calcium and vitamin D supplementation, recognition of warning symptoms, refill procedures, follow-up appointments, and contact information. Patients receiving oral bisphosphonates received additional education on fasting administration with water, maintaining an upright posture for at least 30 min after dosing, separating from food and calcium supplements, and promptly reporting GI symptoms.
Trigger-based regimen optimization
Treatment optimization followed the decision algorithm shown in Figure 2. Gastrointestinal triggers included new or worsening reflux, nausea, vomiting, epigastric pain, abdominal pain, dysphagia, constipation, suspected GI bleeding, or any GI symptom interfering with medication adherence. Adherence triggers included missed prescription refills; treatment interruptions exceeding 30 days for oral therapy; delayed injections or infusions exceeding 30 days; early PDC <0.80; patient-reported discontinuation; or caregiver-reported treatment difficulties.
Mild symptoms prompted reinforcement of medication administration techniques, pharmacist review of concomitant medications, dietary and constipation management, and repeat assessment within 7–14 days. Persistent symptoms or recurrent non-adherence prompted multidisciplinary reassessment involving the treating physician, pharmacist, and specialist nurse. Management included temporary treatment interruption, gastroprotective therapy when appropriate, transition from oral to injectable therapy, simplification of the treatment regimen, or referral for community nursing support. Severe symptoms, suspected GI bleeding, progressive dysphagia, dehydration, or hospitalization required urgent physician assessment and discontinuation or modification of therapy.
Outcomes and follow-up
The primary outcome was medication continuity, assessed using the proportion of days covered (PDC), adherence target attainment, and treatment persistence. Secondary outcomes included changes in bone mineral density (BMD) at prespecified skeletal sites and the time to first confirmed subsequent fragility fracture. Safety outcomes included gastrointestinal (GI) adverse events, other treatment-related adverse events, regimen switching, temporary treatment interruption, permanent treatment discontinuation, adverse event-related hospitalization, and death. Outcome definitions and the 24-month assessment schedule are provided in Supplementary Table 1.
Follow-up assessments were performed at 1 week and at 1, 3, 6, 12, 18, and 24 months after discharge in both study groups. At each follow-up, medication exposure, refill status, adherence barriers, GI symptoms, other adverse events, falls, suspected refractures, hospitalizations, deaths, and treatment modifications were recorded. DXA examinations were repeated at 12 and 24 months whenever feasible.
Medication adherence and persistence
Medication adherence was assessed using the proportion of days covered (PDC), which estimates medication availability over a defined observation period15. The observation period began on the date of discharge following the index hip-fracture admission and ended at 24 months, death, withdrawal, or the last confirmed follow-up, whichever occurred first. Time-specific PDC values were calculated at 1, 3, 6, 12, 18, and 24 months. PDC was calculated as the number of covered medication days divided by the total eligible follow-up days, capped at 1.00. A PDC ≥0.80 was considered to indicate adequate adherence, consistent with commonly accepted thresholds in osteoporosis research16. PDC was interpreted as a measure of medication availability rather than confirmed medication ingestion.
Medication dispensing and refill data were obtained from hospital outpatient pharmacy records, discharge prescriptions, electronic medical records, external prescription documentation, community pharmacy receipts, medication packages presented or photographed during follow-up, and structured nursing records. External pharmacy use without documentary verification was documented but excluded from the primary PDC analysis and included only in the expanded-source sensitivity analysis. For oral therapies, covered days were calculated based on the dispensed quantity and the prescribed dosing interval. Each confirmed denosumab injection contributed 180 covered days, whereas each confirmed zoledronic acid infusion contributed 365 covered days. Overlapping medication supplies were carried forward without double-counting.
Treatment persistence was defined as continuous anti-osteoporosis therapy without a clinically meaningful treatment gap. Non-persistence was defined as an interruption exceeding 60 days for oral therapy or more than 90 days beyond the scheduled administration date for injectable or infusion therapies. The date, duration, cause, and corrective action associated with each interruption were recorded. Permanent discontinuation was defined as the absence of anti-osteoporosis medication coverage for the remainder of the follow-up period after treatment interruption.
BMD assessment
Bone mineral density was measured at the lumbar spine, femoral neck, and total hip using dual-energy X-ray absorptiometry (DXA). Absolute BMD change was expressed in g/cm2, and relative BMD change was calculated as:
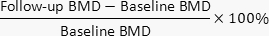
Site-specific BMD changes were classified using the least significant change approach for serial DXA interpretation17. An increase in BMD was defined as a relative gain >3.0% from baseline, whereas a decrease was defined as a relative loss >3.0%. Changes between −3.0% and +3.0% were classified as stable BMD. Participants without valid baseline and follow-up DXA measurements at the same anatomical site were excluded from site-specific BMD analyses but remained eligible for adherence and refracture analyses.
Refracture ascertainment
A subsequent fragility fracture was defined as a new low-energy fracture occurring after discharge from the index hip-fracture admission. At each follow-up visit, participants were screened for suspected refractures by recording new falls, focal pain, emergency department visits, hospitalizations, imaging examinations, or fracture diagnoses made at other institutions. Refractures were confirmed using imaging reports, hospital records, discharge summaries, or external medical documentation. Events reported only during interviews, without radiographic or medical-record confirmation, were classified as suspected refractures and excluded from the primary analysis.
The event date was defined as the injury date when available, or, if unavailable, as the date of the first medical encounter. Only the first confirmed refracture was included in the primary time-to-event analysis. Fracture location, confirmation source, and the interval between symptom onset and confirmation were recorded. All refracture events were independently reviewed by two clinicians, and disagreements were resolved by a senior orthopedic specialist.
GI adverse-event grading
Gastrointestinal adverse events were graded using a predefined four-level clinical severity scale. Grade 1 events consisted of mild symptoms that did not require treatment interruption or additional medication. Grade 2 events comprised moderate symptoms requiring additional medical management, pharmacist or physician review, intensified follow-up, or treatment interruption of ≤14 days. Grade 3 events included symptoms resulting in discontinuation of the current regimen, treatment interruption exceeding 14 days, outpatient or emergency evaluation, or a change in the route of administration. Grade 4 events represented serious GI complications, including suspected or confirmed GI bleeding, gastrointestinal perforation, severe dehydration, or hospitalization. The relationship between each event and anti-osteoporosis therapy was classified by the treating physician as unrelated, possibly related, probably related, or definitely related.
Implementation fidelity and KPI thresholds
Implementation fidelity was evaluated using predefined indicators, including completion of GI risk stratification, discharge education checklist completion, baseline safety laboratory review, treatment initiation within 1 month and within 90 days, calcium and vitamin D supplementation when indicated, completion of scheduled follow-up, DXA completion, documentation of GI adverse-event assessments, completion of trigger-based interventions, and completeness of refracture adjudication. Prespecified key performance indicator (KPI) thresholds and corrective-action criteria are summarized in Figure 3 and Supplementary Table 3.
The predefined KPI targets were as follows: GI risk stratification completion ≥90% by discharge or within 1 week; discharge education checklist completion ≥85%; baseline safety laboratory review ≥85% before treatment selection; treatment initiation ≥70% within 1 month and ≥85% within 90 days; follow-up completion ≥80% through 6 months and ≥75% at 24 months; DXA completion ≥70% at 24 months; documented GI adverse-event assessment ≥85%; and confirmed refracture adjudication ≥95%. Failure to achieve predefined KPI targets triggered additional patient contact, caregiver engagement, staff retraining, pharmacist collaboration, community nursing support, or reassessment of the treatment regimen.
Sample size
The sample size calculation was based on the primary adherence outcome. Pilot data from the study center and published osteoporosis adherence studies suggested a mean 24-month PDC of 0.55 in the usual-care group and 0.68 in the pathway group, corresponding to an anticipated between-group difference of 0.13. Assuming a pooled standard deviation of 0.25, a two-sided α of 0.05, and 80% statistical power, a minimum of 59 participants per group was required. Allowing for a 20% attrition rate over the 24-month follow-up period, the target enrollment was approximately 74 participants per group. The final study cohort comprised 147 participants, including 73 in the pathway group and 74 in the usual-care group. The study was not powered to detect differences in refracture outcomes; therefore, refracture analyses were considered secondary and exploratory.
Statistical analysis
Statistical analyses were performed using R version 4.3.2 and SPSS version 27.0. All statistical tests were two-sided, and a P < 0.05 was considered statistically significant. Continuous variables are presented as the mean ± standard deviation or median (interquartile range), as appropriate, whereas categorical variables are presented as frequencies and percentages. Between-group comparisons were performed using Student's t-test or the Mann–Whitney U test for continuous variables and the chi-square or Fisher's exact test for categorical variables. Baseline comparability was assessed using P values and standardized mean differences.
The primary analysis followed the intention-to-treat principle, with all participants analyzed according to their original group allocation. A per-protocol analysis was also performed after excluding participants with major protocol deviations, withdrawal of consent, or no post-discharge adherence data available.
PDC was analyzed both as a continuous outcome and as a binary variable, using the predefined adherence threshold of PDC ≥ 0.80. Continuous PDC values were evaluated using linear regression, whereas binary adherence outcomes were analyzed using log-binomial regression or modified Poisson regression with robust standard errors. Multivariable models were adjusted for age, sex, fracture type, surgical procedure, Charlson Comorbidity Index, previous fragility fracture, baseline GI risk category, estimated glomerular filtration rate, baseline 25-hydroxyvitamin D concentration, baseline BMD, and calendar period.
Longitudinal BMD changes were analyzed using linear mixed-effects models with fixed effects for treatment group, time, and the group-by-time interaction, together with participant-specific random intercepts. Separate analyses were performed for the lumbar spine, total hip, and femoral neck. Time to first confirmed refracture was evaluated using Kaplan–Meier survival curves, the log-rank test, and Cox proportional hazards regression. The proportional hazards assumption was assessed using Schoenfeld residuals. Because the number of refracture events was limited, hazard ratio estimates were interpreted as exploratory. Death before refracture was evaluated using Fine–Gray competing-risk regression18.
Missing data were summarized by study group, variable, follow-up time point, and reason for missingness. Multiple imputation by chained equations was used for missing covariates and repeated non-event outcomes when the missing-at-random assumption was considered plausible19. Because follow-up completion varied across study groups, prespecified sensitivity analyses for missing-not-at-random were performed. For adherence analyses, a conservative worst-case scenario classified participants lost to follow-up in the pathway group as non-adherent and those lost to follow-up in the usual-care group as adherent at 24 months. For BMD analyses, missing pathway-group DXA values were imputed to the 10th percentile of observed changes, whereas missing usual-care values were imputed to the 90th percentile. For refracture analyses, a conservative event-assignment scenario assumed that participants lost to follow-up in the pathway group experienced a refracture at the midpoint between their last contact and 24 months, whereas participants lost to follow-up in the usual-care group were censored at their last confirmed follow-up. A tipping-point analysis was performed by varying the assumed outcomes among participants lost to follow-up until the principal between-group conclusions were no longer statistically or clinically meaningful.
Prespecified subgroup analyses evaluated the effects of age, sex, GI risk category, renal function, baseline BMD category, and previous fragility fracture. Interaction terms were assessed within the regression models, and all subgroup analyses were considered exploratory.
Results
Cohort enrollment, allocation, and follow-up capture
A total of 198 older adults with surgically treated hip fractures were screened for eligibility. Fifty-one participants were excluded because they did not meet the inclusion criteria (n = 29), declined participation or did not provide informed consent (n = 12), had severe comorbidities or an expected survival of less than 6 months (n = 6), or were unable to complete follow-up because no caregiver or valid contact information was available (n = 4). The final study cohort comprised 147 participants, including 73 in the nurse-led gastrointestinal (GI) tolerability–adapted pathway group and 74 in the usual-care group. Participant screening, group allocation, follow-up, and analysis-set construction are illustrated in Figure 1. Participants in the usual-care group were enrolled before implementation of the nurse-led pathway, whereas those in the pathway group were enrolled after implementation.
Baseline dual-energy X-ray absorptiometry (DXA) was completed within the predefined assessment window in 103 of 147 participants (70.1%), with comparable completion rates between the pathway and usual-care groups (71.2% vs. 68.9%; Table 1). Follow-up completion rates were significantly higher in the pathway group at 3 months (93.2% vs. 82.4%; RR, 1.13; P = 0.046), 6 months (89.0% vs. 77.0%; RR, 1.16; P = 0.049), 12 months (84.9% vs. 67.6%; RR, 1.26; P = 0.013), and 24 months (79.5% vs. 59.5%; RR, 1.34; P = 0.009). Similarly, DXA completion rates were significantly higher in the pathway group at 12 months (82.2% vs. 55.4%; RR, 1.48; P < 0.001) and 24 months (75.3% vs. 51.4%; RR, 1.47; P = 0.003; Table 2).
Baseline characteristics and GI tolerability risk profile
Baseline demographic characteristics, fracture-related variables, perioperative factors, comorbidities, laboratory findings, and gastrointestinal (GI) tolerability risk profiles were comparable between the two groups (Table 1). There were no significant differences in age (79.0 ± 7.6 vs. 79.7 ± 8.0 years; P = 0.56), female sex (68.5% vs. 73.0%; P = 0.55), body mass index (22.4 ± 3.8 vs. 22.8 ± 4.0 kg/m2; P = 0.51), fracture type (P = 0.64), surgical procedure (P = 0.58), time from admission to surgery (P = 0.71), or length of hospital stay (P = 0.63) between the nurse-led pathway and usual-care groups. Baseline treatment-safety parameters were also similar, including serum 25-hydroxyvitamin D [25(OH)D] concentrations (18.9 ± 7.1 vs. 18.3 ± 6.7 ng/mL; P = 0.63), corrected calcium levels (2.24 ± 0.12 vs. 2.23 ± 0.11 mmol/L; P = 0.58), and estimated glomerular filtration rate (eGFR) (65.7 ± 18.1 vs. 63.9 ± 18.9 mL/min/1.73 m2; P = 0.56).
Baseline GI tolerability risk factors were likewise well balanced between the two groups. The prevalence of previous gastroesophageal reflux disease (20.5% vs. 23.0%; P = 0.71), a history of gastritis or peptic ulcer disease (17.8% vs. 20.3%; P = 0.69), previous upper GI bleeding (5.5% vs. 6.8%; P = 0.75), dysphagia or swallowing difficulty (8.2% vs. 10.8%; P = 0.59), inability to remain upright for at least 30 min (13.7% vs. 12.2%; P = 0.79), nonsteroidal anti-inflammatory drug use (21.9% vs. 24.3%; P = 0.73), anticoagulant or antiplatelet therapy (37.0% vs. 41.9%; P = 0.54), and proton pump inhibitor use (43.8% vs. 47.3%; P = 0.67) did not differ significantly between groups. Similarly, the distribution of predefined GI tolerability risk categories was comparable between the pathway and usual-care groups (P = 0.93) (Table 1).
Implementation fidelity and care-process performance
Implementation of care-process indicators was consistently higher in the nurse-led pathway group than in the usual-care group (Table 2). Completion of enrollment with documented follow-up planning was significantly higher in the pathway group (91.8% vs. 32.4%; RR, 2.83; P < 0.001), as were completion of the discharge education checklist (89.0% vs. 39.2%; RR, 2.27; P < 0.001), documentation of GI risk stratification (95.9% vs. 17.6%; RR, 5.45; P < 0.001), and completion of baseline safety laboratory review before treatment initiation (86.3% vs. 55.4%; RR, 1.56; P < 0.001).
Timely initiation of anti-osteoporosis therapy was also more frequent in the pathway group, both within 1 month (74.0% vs. 41.9%; RR, 1.76; P < 0.001) and within 90 days (87.7% vs. 63.5%; RR, 1.38; P = 0.001). Initiation of vitamin D supplementation (83.6% vs. 64.9%; RR, 1.29; P = 0.010) and calcium supplementation (79.5% vs. 60.8%; RR, 1.31; P = 0.014) was likewise more common in the pathway group. Trigger-based regimen optimization was implemented more frequently in participants managed through the nurse-led pathway than in those receiving usual care (23.3% vs. 8.1%; RR, 2.87; P = 0.012). In addition, documentation of GI adverse-event assessments during follow-up was significantly more frequent in the pathway group (90.4% vs. 56.8%; RR, 1.59; P < 0.001; Table 2).
Treatment patterns, GI adverse events, and switching dynamics
Initial anti-osteoporosis treatment selection within 90 days differed significantly between the two groups (P = 0.003). Oral bisphosphonates were prescribed less frequently in the nurse-led pathway group than in the usual-care group (24.7% vs. 41.9%), whereas non-oral antiresorptive therapies were used more frequently (50.7% vs. 28.4%). The median time to treatment initiation was significantly shorter in the pathway group than in the usual-care group (21.8 [10.6–43.7] vs. 36.9 [16.1–63.2] days; P = 0.021).
Overall exposure to anti-osteoporosis therapy remained higher in the pathway group at both 12 months (82.2% vs. 66.2%; P = 0.028) and 24 months (68.5% vs. 50.0%; P = 0.024). GI symptoms were reported by 28.8% of participants in the pathway group and 41.9% of those receiving usual care (P = 0.094), whereas moderate-to-severe GI symptoms occurred in 11.0% and 20.3% of participants, respectively (P = 0.120). Regimen switching during the 24-month follow-up was more common in the pathway group (26.0% vs. 13.5%; P = 0.049). Permanent treatment discontinuation by 24 months occurred less frequently in the pathway group (26.0% vs. 40.5%; P = 0.063), as did GI-related discontinuation (5.5% vs. 13.5%; P = 0.110), although these differences did not reach statistical significance (Table 3).
Longitudinal adherence and persistence
Longitudinal medication adherence and treatment persistence are summarized in Table 4 and illustrated in Figure 4. Figure 4A shows mean proportion of days covered (PDC) values at 1, 3, 6, 12, 18, and 24 months, whereas Figure 4B shows Kaplan–Meier curves for time to treatment discontinuation.
Mean PDC remained consistently higher in the pathway group throughout follow-up, with the between-group difference increasing from 0.11 at 1 month (0.83 ± 0.14 vs. 0.72 ± 0.18; P < 0.001) to 0.19 at 24 months (0.74 ± 0.21 vs. 0.55 ± 0.25; P < 0.001).
Using the predefined adherence threshold of PDC ≥0.80, adherence target attainment was significantly higher in the pathway group at every assessment: 1 month (71.2% vs. 44.6%; RR, 1.60; P = 0.002), 3 months (68.5% vs. 39.2%; RR, 1.75; P < 0.001), 6 months (63.0% vs. 33.8%; RR, 1.86; P < 0.001), 12 months (69.9% vs. 44.6%; RR, 1.57; P = 0.002), 18 months (64.4% vs. 39.2%; RR, 1.64; P = 0.001), and 24 months (60.3% vs. 36.5%; RR, 1.65; P = 0.004).
Treatment persistence was also superior in the pathway group. Continued medication coverage was significantly higher at 12 months (74.0% vs. 55.4%; RR, 1.34; P = 0.014), 18 months (65.8% vs. 44.6%; RR, 1.47; P = 0.009), and 24 months (60.3% vs. 37.8%; RR, 1.60; P = 0.004). Median time to treatment discontinuation was longer in the pathway group (17.8 [11.4–24.0] vs. 12.1 [6.8–19.6] months; P = 0.003), and the proportion of participants who discontinued treatment by 24 months was lower (39.7% vs. 62.2%; RR, 0.64; P = 0.006).
Bone mineral density changes
Changes in bone mineral density (BMD) are summarized in Figure 5A, which illustrates the distribution of 24-month BMD changes (ΔBMD) at the lumbar spine, total hip, and femoral neck. Paired DXA measurements suitable for longitudinal analysis were available for 49 participants in the pathway group and 37 participants in the usual-care group at 12 months, and for 45 and 34 participants, respectively, at 24 months. Baseline BMD values did not differ significantly between the two groups at any skeletal site (Table 5).
At 12 months, participants in the pathway group demonstrated significantly greater increases in lumbar spine BMD (+0.024 ± 0.036 vs. +0.011 ± 0.039 g/cm2; between-group difference, 0.013 g/cm2; P = 0.031) and total hip BMD (+0.014 ± 0.028 vs. +0.005 ± 0.031 g/cm2; between-group difference, 0.009 g/cm2; P = 0.048). Improvements in femoral neck BMD were numerically greater in the pathway group but did not differ significantly between groups (+0.008 ± 0.024 vs. +0.002 ± 0.026 g/cm2; between-group difference, 0.006 g/cm2; P = 0.110).
At 24 months, significantly greater gains in lumbar spine BMD (+0.038 ± 0.044 vs. +0.015 ± 0.048 g/cm2; between-group difference, 0.023 g/cm2; P = 0.006) and total hip BMD (+0.022 ± 0.034 vs. +0.008 ± 0.037 g/cm2; between-group difference, 0.014 g/cm2; P = 0.018) remained evident in the pathway group. Although femoral neck BMD also increased to a greater extent in the pathway group, the between-group difference did not reach statistical significance (+0.013 ± 0.029 vs. +0.004 ± 0.031 g/cm2; between-group difference, 0.009 g/cm2; P = 0.079).
Refracture outcomes
Refracture-free survival is shown in Figure 5B, which presents Kaplan–Meier estimates of the time to first confirmed subsequent fragility fracture. During the 24-month follow-up period, 7 of 73 participants (9.6%) in the pathway group and 14 of 74 participants (18.9%) in the usual-care group experienced at least one confirmed refracture. Although the crude incidence was lower in the pathway group, the difference was not statistically significant (RR, 0.51; P = 0.110). A total of eight refracture events occurred in the pathway group compared with sixteen in the usual-care group (incidence rate ratio [IRR], 0.50; P = 0.090), corresponding to incidence rates of 6.4 and 13.2 events per 100 person-years, respectively (rate difference, −6.8 per 100 person-years; P = 0.070; Table 6).
Time-to-event analyses also favored the pathway group but were interpreted as exploratory because of the limited number of events. Kaplan–Meier estimates of refracture-free survival were 95.7% and 89.6% at 12 months and 90.1% and 80.4% at 24 months for the pathway and usual-care groups, respectively. The unadjusted Cox proportional hazards model yielded a hazard ratio of 0.54 (95% CI, 0.22–0.98; P = 0.042), and the log-rank test demonstrated a significant between-group difference (P = 0.038).
All confirmed refractures were verified using imaging or medical records. The interval between symptom reporting and event confirmation was significantly shorter in the pathway group than in the usual-care group (6.8 ± 3.1 vs. 9.4 ± 4.7 days; mean difference, −2.6 days; P = 0.014).
Subgroup and sensitivity analyses
Prespecified subgroup analyses demonstrated no statistically significant interactions according to age, sex, GI risk category, renal function category, or previous fragility fracture for 24-month medication adherence, lumbar spine BMD change, or first subsequent refracture (Table 7). Nevertheless, the direction of the treatment effect remained generally consistent across all subgroups.
Sensitivity analyses were performed to account for differences in follow-up completion and DXA availability between the study groups. Per-protocol analyses, expanded-source refill verification, multiple imputation, and adjustment for calendar period all produced effect estimates that were directionally consistent with the primary analysis.
Under a conservative missing-not-at-random scenario, in which participants lost to follow-up in the pathway group were classified as non-adherent and those lost to follow-up in the usual-care group as adherent, the 24-month adherence difference was attenuated but remained numerically favorable to the pathway group (52.1% vs. 43.2%; RR, 1.21; P = 0.280). Under the conservative BMD missing-data scenario, the between-group difference in lumbar spine BMD at 24 months decreased to 0.011 g/cm2 (95% CI, −0.002 to 0.025; P = 0.092). Similarly, under the conservative refracture event-assignment scenario, the hazard ratio moved toward the null (HR, 0.78; 95% CI, 0.39–1.56; P = 0.480).
Tipping-point analysis indicated that the primary adherence finding would lose statistical significance if at least eight additional participants lost to follow-up in the usual-care group were assumed to be adherent and at least six additional participants lost to follow-up in the pathway group were assumed to be non-adherent. Collectively, these sensitivity analyses supported the robustness of the adherence findings and indicated that estimates of BMD and refracture outcomes were more sensitive to assumptions about missing outcome data.
DATA AVAILABILITY:
The raw data supporting the findings of this study have been deposited in the figshare repository and are publicly available at https://doi.org/10.6084/m9.figshare.32906351.v1
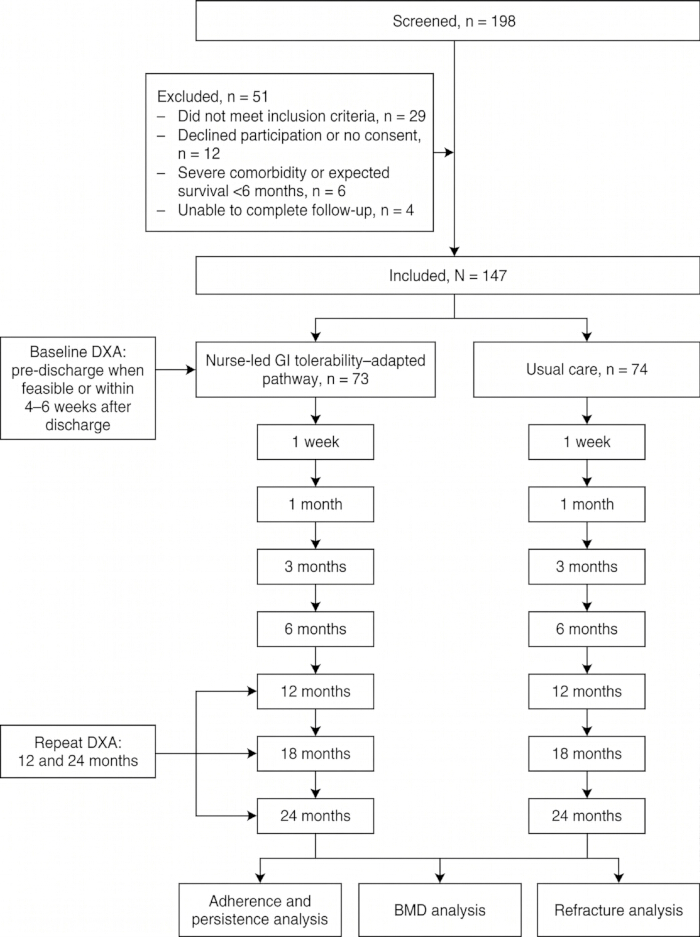
Figure 1: Participant flow and analysis sets. Participant screening, exclusions, group allocation, scheduled follow-up, DXA assessment windows, and analysis sets for adherence, BMD, and refracture outcomes. Please click here to view a larger version of this figure.
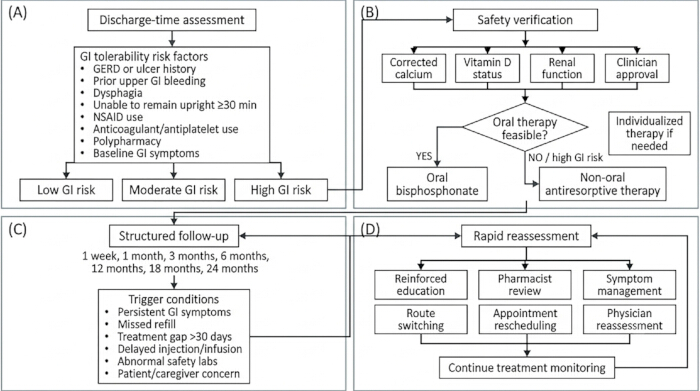
Figure 2: GI tolerability–adapted regimen workflow. (A) GI risk stratification. (B) Safety verification and initial regimen selection. (C) Follow-up triggers for GI symptoms and non-adherence. (D) Closed-loop regimen optimization. Please click here to view a larger version of this figure.
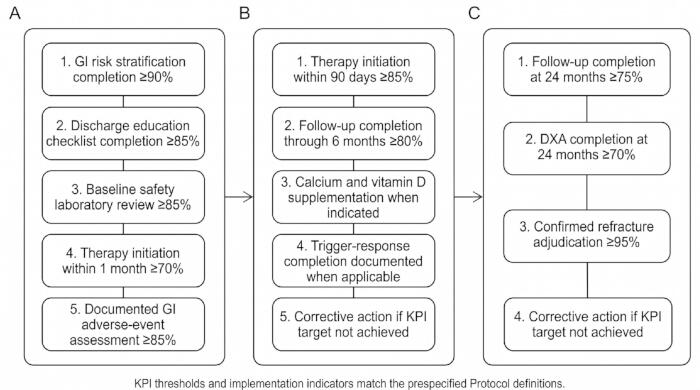
Figure 3: Implementation fidelity and KPI thresholds. (A) Early implementation indicators from discharge to 1 month. (B) Mid-term implementation indicators from 1 to 6 months. (C) Long-term implementation indicators from 12 to 24 months. The quantitative KPI thresholds and implementation indicators were matched to the prespecified Protocol definitions. Corrective actions were triggered when predefined targets were not achieved. Please click here to view a larger version of this figure.
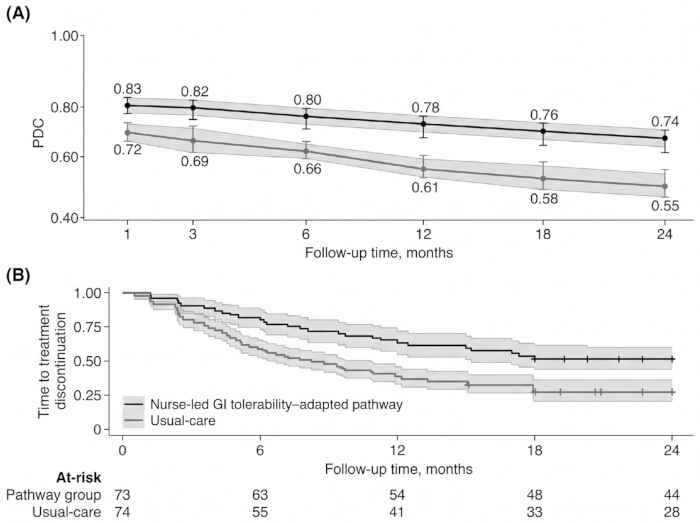
Figure 4: Medication adherence and persistence. (A) Mean PDC at 1, 3, 6, 12, 18, and 24 months. (B) Kaplan–Meier curves for time to treatment discontinuation. Abbreviations: PDC = proportion of days covered. Please click here to view a larger version of this figure.
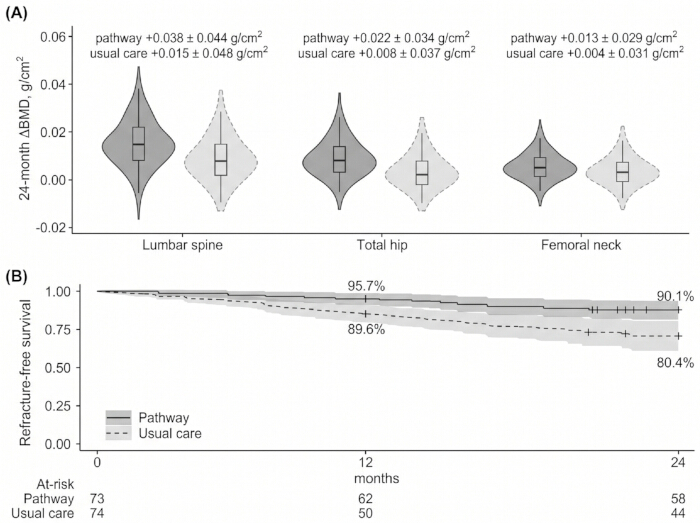
Figure 5: BMD change and refracture-free survival. (A) Twenty-four-month change from baseline in BMD at the lumbar spine, total hip, and femoral neck. (B) Kaplan–Meier curves for time to first confirmed refracture. Abbreviations: BMD = bone mineral density. Please click here to view a larger version of this figure.
| Characteristic | Overall, n = 147 | Nurse-led pathway, n = 73 | Usual care, n = 74 | P value | |
| Demographics | |||||
| Age, years | 79.3 ± 7.8 | 79.0 ± 7.6 | 79.7 ± 8.0 | 0.56 | |
| Female sex, n (%) | 104 (70.7) | 50 (68.5) | 54 (73.0) | 0.55 | |
| BMI, kg/m² | 22.6 ± 3.9 | 22.4 ± 3.8 | 22.8 ± 4.0 | 0.51 | |
| Caregiver available, n (%) | 121 (82.3) | 61 (83.6) | 60 (81.1) | 0.69 | |
| Fracture and perioperative features | |||||
| Fracture type, n (%) | 0.64 | ||||
| Femoral neck fracture | 76 (51.7) | 39 (53.4) | 37 (50.0) | ||
| Intertrochanteric fracture | 71 (48.3) | 34 (46.6) | 37 (50.0) | ||
| Surgery type, n (%) | 0.58 | ||||
| Internal fixation | 79 (53.7) | 38 (52.1) | 41 (55.4) | ||
| Arthroplasty | 68 (46.3) | 35 (47.9) | 33 (44.6) | ||
| Time to surgery, hours | 36.8 (24.4–52.6) | 35.9 (24.0–51.8) | 37.6 (24.8–53.4) | 0.71 | |
| Length of stay, days | 11.2 ± 4.6 | 11.0 ± 4.4 | 11.4 ± 4.8 | 0.63 | |
| Pre-fracture independent ambulation, n (%) | 112 (76.2) | 54 (74.0) | 58 (78.4) | 0.53 | |
| Comorbidities and bone-health status | |||||
| Charlson comorbidity index | 4.1 ± 1.7 | 4.0 ± 1.7 | 4.2 ± 1.8 | 0.44 | |
| Diabetes mellitus, n (%) | 39 (26.5) | 18 (24.7) | 21 (28.4) | 0.61 | |
| Hypertension, n (%) | 96 (65.3) | 46 (63.0) | 50 (67.6) | 0.56 | |
| Chronic kidney disease, eGFR <60, n (%) | 44 (29.9) | 20 (27.4) | 24 (32.4) | 0.5 | |
| Prior fragility fracture, n (%) | 36 (24.5) | 17 (23.3) | 19 (25.7) | 0.73 | |
| Prior anti-osteoporotic therapy, n (%) | 18 (12.2) | 9 (12.3) | 9 (12.2) | 0.99 | |
| 25(OH)D, ng/mL | 18.6 ± 6.9 | 18.9 ± 7.1 | 18.3 ± 6.7 | 0.63 | |
| Corrected calcium, mmol/L | 2.24 ± 0.11 | 2.24 ± 0.12 | 2.23 ± 0.11 | 0.58 | |
| eGFR, mL/min/1.73 m² | 64.8 ± 18.5 | 65.7 ± 18.1 | 63.9 ± 18.9 | 0.56 | |
| Baseline DXA completed within window, n (%) | 103 (70.1) | 52 (71.2) | 51 (68.9) | 0.76 | |
| GI tolerability risk profile | |||||
| Prior GERD, n (%) | 32 (21.8) | 15 (20.5) | 17 (23.0) | 0.71 | |
| History of gastritis/peptic ulcer, n (%) | 28 (19.0) | 13 (17.8) | 15 (20.3) | 0.69 | |
| Prior upper GI bleeding, n (%) | 9 (6.1) | 4 (5.5) | 5 (6.8) | 0.75 | |
| Dysphagia or swallowing difficulty, n (%) | 14 (9.5) | 6 (8.2) | 8 (10.8) | 0.59 | |
| Unable to remain upright ≥30 min, n (%) | 19 (12.9) | 10 (13.7) | 9 (12.2) | 0.79 | |
| Chronic constipation, n (%) | 41 (27.9) | 19 (26.0) | 22 (29.7) | 0.62 | |
| Concomitant NSAID use, n (%) | 34 (23.1) | 16 (21.9) | 18 (24.3) | 0.73 | |
| Concomitant anticoagulant/antiplatelet use, n (%) | 58 (39.5) | 27 (37.0) | 31 (41.9) | 0.54 | |
| Proton pump inhibitor use, n (%) | 67 (45.6) | 32 (43.8) | 35 (47.3) | 0.67 | |
| GI risk category, n (%) | 0.93 | ||||
| Low risk | 63 (42.9) | 31 (42.5) | 32 (43.2) | ||
| 58 (39.5) | 29 (39.7) | 29 (39.2) | |||
| High risk | 26 (17.7) | 13 (17.8) | 13 (17.6) | ||
Table 1: Baseline characteristics and GI tolerability risk profile. Demographic, fracture-related, perioperative, comorbidity, laboratory, DXA, and GI-risk variables in the overall cohort and by group. Please click here to download this Table.
| Indicator | Nurse-led pathway, n = 73 | Usual care, n = 74 | Effect estimate | P value | |
| Early implementation ≤1 week | |||||
| Enrollment completed and follow-up plan documented | 67/73 (91.8%) | 24/74 (32.4%) | RR 2.83 | <0.001 | |
| Education checklist completed | 65/73 (89.0%) | 29/74 (39.2%) | RR 2.27 | <0.001 | |
| GI tolerability risk stratification recorded | 70/73 (95.9%) | 13/74 (17.6%) | RR 5.45 | <0.001 | |
| Baseline safety labs reviewed before therapy decision | 63/73 (86.3%) | 41/74 (55.4%) | RR 1.56 | <0.001 | |
| Therapy initiation and optimization | |||||
| Anti-osteoporotic therapy initiated by 1 month | 54/73 (74.0%) | 31/74 (41.9%) | RR 1.76 | <0.001 | |
| Anti-osteoporotic therapy initiated by 90 days | 64/73 (87.7%) | 47/74 (63.5%) | RR 1.38 | 0.001 | |
| Vitamin D supplementation initiated by discharge or ≤1 month | 61/73 (83.6%) | 48/74 (64.9%) | RR 1.29 | 0.01 | |
| Calcium supplementation initiated by discharge or ≤1 month | 58/73 (79.5%) | 45/74 (60.8%) | RR 1.31 | 0.014 | |
| Trigger-based regimen optimization performed | 17/73 (23.3%) | 6/74 (8.1%) | RR 2.87 | 0.012 | |
| Documented GI adverse-event assessment during follow-up | 66/73 (90.4%) | 42/74 (56.8%) | RR 1.59 | <0.001 | |
| Follow-up completeness | |||||
| Follow-up completed at 1 month | 69/73 (94.5%) | 63/74 (85.1%) | RR 1.11 | 0.069 | |
| Follow-up completed at 3 months | 68/73 (93.2%) | 61/74 (82.4%) | RR 1.13 | 0.046 | |
| Follow-up completed at 6 months | 65/73 (89.0%) | 57/74 (77.0%) | RR 1.16 | 0.049 | |
| Follow-up completed at 12 months | 62/73 (84.9%) | 50/74 (67.6%) | RR 1.26 | 0.013 | |
| Follow-up completed at 24 months | 58/73 (79.5%) | 44/74 (59.5%) | RR 1.34 | 0.009 | |
| Outcome capture | |||||
| DXA completed at 12 months | 60/73 (82.2%) | 41/74 (55.4%) | RR 1.48 | <0.001 | |
| DXA completed at 24 months | 55/73 (75.3%) | 38/74 (51.4%) | RR 1.47 | 0.003 | |
| Adherence target achieved at 12 months | 51/73 (69.9%) | 33/74 (44.6%) | RR 1.57 | 0.002 | |
| Adherence target achieved at 24 months | 44/73 (60.3%) | 27/74 (36.5%) | RR 1.65 | 0.004 | |
Table 2: Implementation fidelity, follow-up completeness, and outcome capture. Completion of pathway processes, therapy initiation, supplementation, trigger-based optimization, follow-up, DXA capture, and adherence target attainment. Please click here to download this Table.
| Variable | Overall, n = 147 | Nurse-led pathway, n = 73 | Usual care, n = 74 | P value | |
| Initial anti-osteoporotic regimen within 90 days, n (%) | 0.003 | ||||
| Oral bisphosphonate | 49 (33.3) | 18 (24.7) | 31 (41.9) | ||
| Non-oral antiresorptive therapy | 58 (39.5) | 37 (50.7) | 21 (28.4) | ||
| Anabolic therapy | 6 (4.1) | 4 (5.5) | 2 (2.7) | ||
| No anti-osteoporotic drug initiated by 90 days | 34 (23.1) | 14 (19.2) | 20 (27.0) | ||
| Time to therapy initiation, days | 28.6 (13.2–55.4) | 21.8 (10.6–43.7) | 36.9 (16.1–63.2) | 0.021 | |
| Medication exposure during follow-up | |||||
| Any anti-osteoporotic drug exposure at 12 months | 109 (74.1) | 60 (82.2) | 49 (66.2) | 0.028 | |
| Any anti-osteoporotic drug exposure at 24 months | 87 (59.2) | 50 (68.5) | 37 (50.0) | 0.024 | |
| Vitamin D supplementation at 12 months | 118 (80.3) | 63 (86.3) | 55 (74.3) | 0.067 | |
| Calcium supplementation at 12 months | 103 (70.1) | 55 (75.3) | 48 (64.9) | 0.17 | |
| GI adverse events during follow-up | |||||
| Any GI symptom reported | 52 (35.4) | 21 (28.8) | 31 (41.9) | 0.094 | |
| Moderate-to-severe GI symptoms | 23 (15.6) | 8 (11.0) | 15 (20.3) | 0.12 | |
| GI symptom requiring additional medication | 27 (18.4) | 10 (13.7) | 17 (23.0) | 0.14 | |
| Switching and discontinuation dynamics | |||||
| Any regimen switch within 24 months | 29 (19.7) | 19 (26.0) | 10 (13.5) | 0.049 | |
| Switch triggered by GI intolerance | 18 (12.2) | 12 (16.4) | 6 (8.1) | 0.12 | |
| Switch triggered by non-adherence risk | 11 (7.5) | 8 (11.0) | 3 (4.1) | 0.12 | |
| Temporary interruption >30 days | 24 (16.3) | 9 (12.3) | 15 (20.3) | 0.19 | |
| Permanent discontinuation by 24 months | 49 (33.3) | 19 (26.0) | 30 (40.5) | 0.063 | |
| GI-related discontinuation by 24 months | 14 (9.5) | 4 (5.5) | 10 (13.5) | 0.11 | |
Table 3: Treatment patterns, GI adverse events, and switching or discontinuation. Initial regimen selection, timing of therapy initiation, medication exposure, GI symptoms, regimen switching, treatment interruption, and discontinuation during follow-up. Please click here to download this Table.
| Outcome | Timepoint | Nurse-led Pathway | Usual Care | Effect Estimate | P Value |
| n = 73 | n = 74 | ||||
| PDC | 1 month | 0.83 ± 0.14 | 0.72 ± 0.18 | Mean diff 0.11 | <0.001 |
| PDC | 3 months | 0.82 ± 0.15 | 0.69 ± 0.19 | Mean diff 0.13 | <0.001 |
| PDC | 6 months | 0.80 ± 0.17 | 0.66 ± 0.21 | Mean diff 0.14 | <0.001 |
| PDC | 12 months | 0.78 ± 0.19 | 0.61 ± 0.23 | Mean diff 0.17 | <0.001 |
| PDC | 18 months | 0.76 ± 0.20 | 0.58 ± 0.24 | Mean diff 0.18 | <0.001 |
| PDC | 24 months | 0.74 ± 0.21 | 0.55 ± 0.25 | Mean diff 0.19 | <0.001 |
| Adherence Target Achieved (n%) | 1 month | 52/73 (71.2) | 33/74 (44.6) | RR 1.60 | 0.002 |
| Adherence Target Achieved (n%) | 3 months | 50/73 (68.5) | 29/74 (39.2) | RR 1.75 | <0.001 |
| Adherence Target Achieved (n%) | 6 months | 46/73 (63.0) | 25/74 (33.8) | RR 1.86 | <0.001 |
| Adherence Target Achieved (n%) | 12 months | 51/73 (69.9) | 33/74 (44.6) | RR 1.57 | 0.002 |
| Adherence Target Achieved (n%) | 18 months | 47/73 (64.4) | 29/74 (39.2) | RR 1.64 | 0.001 |
| Adherence Target Achieved (n%) | 24 months | 44/73 (60.3) | 27/74 (36.5) | RR 1.65 | 0.004 |
| Persistence (n%) | 6 months | 63/73 (86.3) | 55/74 (74.3) | RR 1.16 | 0.069 |
| Persistence (n%) | 12 months | 54/73 (74.0) | 41/74 (55.4) | RR 1.34 | 0.014 |
| Persistence (n%) | 18 months | 48/73 (65.8) | 33/74 (44.6) | RR 1.47 | 0.009 |
| Persistence (n%) | 24 months | 44/73 (60.3) | 28/74 (37.8) | RR 1.60 | 0.004 |
| Time to Discontinuation (months) | Overall | 17.8 (11.4–24.0) | 12.1 (6.8–19.6) | Median diff 5.7 | 0.003 |
| Discontinuation by 24 Months (n%) | Overall | 29/73 (39.7) | 46/74 (62.2) | RR 0.64 | 0.006 |
Table 4: Longitudinal medication adherence and persistence. Mean PDC, PDC ≥0.80 attainment, continued treatment coverage, time to discontinuation, and 24-month discontinuation. Please click here to download this Table.
| Anatomical Site | Timepoint | Nurse-led pathway | Usual care | Between-group difference in change | P value |
| Lumbar spine L1–L4, g/cm² | Baseline | 0.814 ± 0.112 | 0.807 ± 0.118 | — | 0.69 |
| Lumbar spine L1–L4, g/cm² | 12 months | 0.838 ± 0.115 | 0.818 ± 0.121 | — | 0.33 |
| Lumbar spine L1–L4, g/cm² | Change from baseline | +0.024 ± 0.036 | +0.011 ± 0.039 | 0.013 | 0.031 |
| Lumbar spine L1–L4, g/cm² | 24 months | 0.852 ± 0.119 | 0.822 ± 0.126 | — | 0.19 |
| Lumbar spine L1–L4, g/cm² | Change from baseline | +0.038 ± 0.044 | +0.015 ± 0.048 | 0.023 | 0.006 |
| Total hip, g/cm² | Baseline | 0.694 ± 0.103 | 0.687 ± 0.108 | — | 0.71 |
| Total hip, g/cm² | 12 months | 0.708 ± 0.106 | 0.692 ± 0.112 | — | 0.41 |
| Total hip, g/cm² | Change from baseline | +0.014 ± 0.028 | +0.005 ± 0.031 | 0.009 | 0.048 |
| Total hip, g/cm² | 24 months | 0.716 ± 0.109 | 0.695 ± 0.116 | — | 0.29 |
| Total hip, g/cm² | Change from baseline | +0.022 ± 0.034 | +0.008 ± 0.037 | 0.014 | 0.018 |
| Femoral neck, g/cm² | Baseline | 0.562 ± 0.091 | 0.557 ± 0.094 | — | 0.78 |
| Femoral neck, g/cm² | 12 months | 0.570 ± 0.093 | 0.559 ± 0.097 | — | 0.48 |
| Femoral neck, g/cm² | Change from baseline | +0.008 ± 0.024 | +0.002 ± 0.026 | 0.006 | 0.11 |
| Femoral neck, g/cm² | 24 months | 0.575 ± 0.095 | 0.561 ± 0.099 | — | 0.45 |
| Femoral neck, g/cm² | Change from baseline | +0.013 ± 0.029 | +0.004 ± 0.031 | 0.009 | 0.079 |
Table 5: BMD changes at prespecified skeletal sites. Baseline, 12-month, and 24-month BMD values at the lumbar spine, total hip, and femoral neck, with absolute changes from baseline and between-group differences. Please click here to download this Table.
| Outcome | Nurse-led pathway, n = 73 | Usual care, n = 74 | Effect estimate | P value |
| Refracture incidence | ||||
| Patients with ≥1 refracture, n (%) | 7 (9.6) | 14 (18.9) | RR 0.51 | 0.11 |
| Total refracture events, n | 8 | 16 | IRR 0.50 | 0.09 |
| Follow-up time, person-years | 124.7 | 121.3 | — | — |
| Incidence rate, per 100 person-years | 6.4 | 13.2 | Rate diff −6.8 | 0.07 |
| Time-to-event analysis: first refracture | ||||
| Kaplan–Meier refracture-free survival at 12 months, % | 95.7 | 89.6 | — | — |
| Kaplan–Meier refracture-free survival at 24 months, % | 90.1 | 80.4 | — | — |
| Median time to first refracture, months | Not reached | Not reached | — | — |
| Unadjusted Cox model HR, pathway vs usual care | — | — | 0.54 (0.22–0.98) | 0.042 |
| Log-rank test | — | — | — | 0.038 |
| First refracture site | ||||
| Confirmed first refractures, n | 7 | 14 | — | — |
| Contralateral hip | 1 (14.3) | 3 (21.4) | — | — |
| Vertebral | 3 (42.9) | 5 (35.7) | — | — |
| Distal radius/forearm | 2 (28.6) | 3 (21.4) | — | — |
| Proximal humerus | 1 (14.3) | 2 (14.3) | — | — |
| Pelvis/other fragility sites | 0 (0.0) | 1 (7.1) | — | — |
| Event ascertainment quality | ||||
| Refractures confirmed by imaging/records, n/N (%) | 7/7 (100.0) | 14/14 (100.0) | — | — |
| Time from symptom report to confirmation, days | 6.8 ± 3.1 | 9.4 ± 4.7 | Mean diff −2.6 | 0.014 |
Table 6: Refracture outcomes and time-to-event analysis. Refracture incidence, event counts, incidence rates, Kaplan–Meier estimates, Cox model results, first refracture sites, and event-confirmation quality. Please click here to download this Table.
| Analysis | Pathway (n) | Usual Care (n) | 24-Month Adherence Estimate | P Interaction / P Value (Adherence) | 24-Month Lumbar-Spine ΔBMD Estimate | P Interaction / P Value (BMD) | First-Refracture Estimate | P Interaction / P Value (Refracture) |
| Prespecified subgroup analyses | ||||||||
| Overall adjusted model | 73 | 74 | RR 1.52 (1.10–2.10) | — | MD 0.021 (0.006–0.035) | — | Adjusted HR 0.56 (0.24–1.06) | — |
| Age ≥ 80 years | 41 | 43 | RR 1.41 (0.92–2.16) | 0.62 | MD 0.020 (0.003–0.037) | 0.71 | HR 0.59 (0.22–1.23) | 0.83 |
| Age < 80 years | 32 | 31 | RR 1.67 (1.04–2.69) | MD 0.023 (0.005–0.041) | HR 0.52 (0.17–1.18) | |||
| Female | 50 | 54 | RR 1.48 (1.02–2.14) | 0.74 | MD 0.022 (0.005–0.038) | 0.53 | HR 0.55 (0.21–1.11) | 0.79 |
| Male | 23 | 20 | RR 1.63 (0.88–3.03) | MD 0.018 (−0.002–0.039) | HR 0.62 (0.18–1.58) | |||
| High GI risk | 13 | 13 | RR 1.76 (0.92–3.38) | 0.21 | MD 0.024 (0.001–0.048) | 0.48 | HR 0.49 (0.12–1.30) | 0.37 |
| Low–moderate GI risk | 60 | 61 | RR 1.46 (1.04–2.04) | MD 0.020 (0.005–0.035) | HR 0.60 (0.25–1.20) | |||
| eGFR <60 mL/min/1.73 m² | 20 | 24 | RR 1.36 (0.80–2.33) | 0.88 | MD 0.016 (−0.004–0.036) | 0.64 | HR 0.63 (0.20–1.51) | 0.92 |
| eGFR ≥60 mL/min/1.73 m² | 53 | 50 | RR 1.58 (1.09–2.29) | MD 0.023 (0.006–0.039) | HR 0.54 (0.22–1.08) | |||
| Prior fragility fracture: yes | 17 | 19 | RR 1.50 (0.81–2.78) | 0.95 | MD 0.023 (0.000–0.047) | 0.57 | HR 0.53 (0.16–1.36) | 0.81 |
| Prior fragility fracture: no | 56 | 55 | RR 1.53 (1.05–2.22) | MD 0.020 (0.005–0.035) | HR 0.57 (0.24–1.15) | |||
| Sensitivity analyses | ||||||||
| Per-protocol analysis | 66 | 65 | RR 1.59 (1.15–2.21) | 0.006 | MD 0.022 (0.006–0.038) | 0.009 | HR 0.50 (0.20–1.03) | 0.059 |
| Expanded-source refill verification | 73 | 74 | RR 1.48 (1.10–1.99) | 0.01 | Not applicable | — | Not applicable | — |
| Multiple imputation | 73 | 74 | RR 1.50 (1.10–2.03) | 0.009 | MD 0.020 (0.004–0.036) | 0.015 | HR 0.61 (0.27–1.22) | 0.145 |
| Calendar-period adjusted model | 73 | 74 | RR 1.43 (1.04–1.96) | 0.028 | MD 0.019 (0.003–0.035) | 0.022 | HR 0.66 (0.29–1.34) | 0.225 |
| Conservative MNAR adherence scenario | 73 | 74 | RR 1.21 (0.86–1.69) | 0.28 | Not applicable | — | Not applicable | — |
| Conservative MNAR BMD scenario | 52 | 51 | Not applicable | — | MD 0.011 (−0.002–0.025) | 0.092 | Not applicable | — |
| Conservative refracture event-assignment scenario | 73 | 74 | Not applicable | — | Not applicable | — | HR 0.78 (0.39–1.56) | 0.48 |
| Tipping-point analysis | 73 | 74 | Null if ≥8 missing usual-care participants were assumed adherent and ≥6 missing pathway-group participants were assumed non-adherent | — | More sensitive than adherence endpoint | — | More sensitive because of low event count | — |
Table 7: Subgroup and sensitivity analyses. Prespecified subgroup estimates and sensitivity analyses for 24-month adherence, 24-month lumbar-spine BMD change, and first-refracture risk. Please click here to download this Table.
Supplementary Table 1: Outcome definitions and measurement schedule. Definitions and follow-up timing for adherence, persistence, BMD, refracture, safety, death, follow-up completion, and missingness-related outcomes.Please click here to download this file.
Supplementary Table 2: GI risk stratification and regimen decision rules. Operational GI-risk criteria, safety verification steps, initial regimen selection, trigger response, and switching rules.Please click here to download this file.
Supplementary Table 3: Fidelity checklist and KPI thresholds. Fidelity domains, KPI definitions, denominators, target thresholds, time anchors, and corrective actions.Please click here to download this file.
Discussion
This single-center, non-randomized implementation study evaluated a nurse-led gastrointestinal (GI) tolerability–adapted anti-osteoporotic care pathway for older adults following surgical treatment of hip fracture. The most consistent findings were observed in care-process execution and dispensing-based adherence. Compared with usual care, the pathway group had more complete GI risk stratification, discharge education, safety laboratory review, therapy initiation, follow-up capture, and proportion of days covered (PDC)-based adherence over 24 months. These results are consistent with the role of structured post-fracture care models in improving secondary fracture-prevention processes20. BMD changes and refracture-related time-to-event estimates were directionally favorable, but they require cautious interpretation because DXA completion differed between groups, the sample size was modest, and refracture events were limited.
The pathway mainly addressed care gaps that occur after discharge, when osteoporosis treatment must be initiated, monitored, and continued outside the acute surgical episode. Older hip-fracture patients often have multimorbidity, polypharmacy, GI vulnerability, limited mobility, and dependence on caregivers, all of which can delay treatment or lead to discontinuation21. By converting these barriers into predefined checkpoints, GI risk classification, oral-administration feasibility, safety verification, refill monitoring, and follow-up completion, the pathway improved the traceability of post-fracture osteoporosis care. The largest between-group differences occurred in these process indicators, suggesting that the intervention worked primarily by improving continuity and coordination rather than by introducing a single therapeutic component.
The adherence results were aligned with this mechanism. Mean PDC and PDC ≥0.80 attainment were higher in the pathway group throughout follow-up, probably reflecting earlier therapy initiation, more active refill surveillance, caregiver contact, and predefined responses to missed refills or intolerance. However, PDC measures medication availability rather than confirmed ingestion22. The adherence findings, therefore, indicate improved medication coverage and continuity of care, not a direct confirmation that all doses were taken. The use of pharmacy records, external prescription evidence, medication package confirmation, caregiver verification, and sensitivity analyses reduced, but did not eliminate, the possibility of unmeasured medication-taking gaps.
The tolerability-adapted regimen strategy changed treatment delivery in a clinically plausible way. Oral bisphosphonate use was lower and non-oral antiresorptive therapy was higher in the pathway group, reflecting the predefined decision rules for participants with GI risk factors or poor oral-administration feasibility. More regimen switching occurred in the pathway group, but within this protocol, switching was a planned corrective response to GI intolerance, missed refills, treatment gaps, or delayed attendance at injections or infusions. GI symptoms and GI-related discontinuation were numerically lower in the pathway group, but these comparisons were not statistically significant. The data therefore support better detection and management of GI-related treatment barriers, but they do not establish a clear reduction in GI adverse events.
BMD findings were supportive but not confirmatory. The pathway group had greater lumbar-spine and total-hip BMD gains at 12 and 24 months, while femoral-neck differences were smaller and not statistically significant. This pattern is consistent with the adherence findings because sustained anti-osteoporotic therapy is generally required before measurable BMD differences are expected23. However, paired BMD analyses included only participants with valid serial DXA, and DXA completion was higher in the pathway group. The conservative missingness scenario attenuated the lumbar-spine BMD difference, indicating that BMD estimates remained sensitive to assumptions about participants without follow-up DXA.
Refracture findings require the most conservative interpretation. The crude proportion with at least one refracture was lower in the pathway group, but the crude comparison did not reach statistical significance. Cox and log-rank analyses suggested a lower hazard of first refracture, although only 21 participants experienced it. This limited event count reduces precision and increases the risk of model instability. Refracture risk is also affected by fall risk, rehabilitation, frailty, comorbidity, baseline bone status, and competing mortality24. Because allocation was determined by pathway implementation status rather than randomization, selection bias and temporal confounding cannot be excluded. The study was conducted at a single center, and higher follow-up and DXA completion in the pathway group may have affected outcome ascertainment. Overall, the pathway was feasible and was associated with more complete care processes and better dispensing-based adherence, whereas BMD and refracture estimates should be considered exploratory. Larger multicenter studies using randomized or stepped-wedge designs, stronger adherence verification, more complete DXA capture, and prespecified competing-risk analyses are needed to confirm effectiveness and refine tolerability-adapted decision rules25.
Disclosures
The authors declare no competing financial interests and no conflicts of interest related to this work.
Acknowledgements
The authors thank the nursing staff, orthopedic team, and follow-up personnel at the study center for their support in patient screening, pathway implementation, and longitudinal follow-up. The authors also thank all patients and their families for participating in this study. This work was supported by the Health and Wellness Bureau of Longquanyi District, Chengdu (Grant No. WJKY2025020).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 25-hydroxyvitamin D assay | Beckman Coulter | Access 25(OH) Vitamin D Total Kit, B24838 | Baseline vitamin D assessment and safety verification before antiresorptive therapy. |
| Case report forms | Study site | Local document set | Standardized collection of eligibility, baseline characteristics, fracture details, medication history, follow-up status, adverse events, and outcomes. |
| Chemistry analyzer | Roche Diagnostics | cobas 8000 modular analyzer series, cobas c 702 module | Measurement of serum calcium, albumin, phosphate, creatinine, alkaline phosphatase, and other routine chemistry indicators. |
| Discharge education checklist | Study site | Local document set | Standardized recording of medication education, administration instructions, warning symptoms, refill plan, and follow-up schedule. |
| DXA analysis software | GE HealthCare | enCORE software platform | Region-of-interest definition, BMD calculation, and serial DXA comparison. |
| DXA bone densitometer | GE HealthCare | Lunar iDXA | Bone mineral density measurement at lumbar spine, femoral neck, and total hip at baseline, 12 months, and 24 months. |
| External refill documentation | External hospitals / community pharmacies | Not applicable | Verification of external prescriptions, community pharmacy receipts, medication packages, or caregiver-provided refill records. |
| GI tolerability risk checklist | Study site | Local document set | Documentation of GI symptoms, GI disease history, swallowing ability, upright-position feasibility, GI-risk medications, constipation, and polypharmacy. |
| Hospital electronic medical record system | Study hospital | Local institutional EMR/HIS | Extraction of admission data, surgery data, laboratory results, discharge prescriptions, outpatient records, and hospitalization events. |
| Hospital pharmacy dispensing system | Study hospital | Local institutional pharmacy information system | Extraction of discharge prescriptions, outpatient refill dates, dispensed quantity, and medication supply information for PDC calculation. |
| Immunoassay analyzer | Beckman Coulter | Access 2 Immunoassay System | Measurement platform for serum 25-hydroxyvitamin D. |
| Medication adherence worksheet | Study site | Local spreadsheet template | Calculation of PDC, refill gaps, interruption duration, persistence status, and expanded-source sensitivity analysis. |
| Secure data capture platform | REDCap Consortium / study hospital | REDCap or local institutional EDC | Data entry, audit trail, role-based access, query resolution, and analysis dataset export. |
| Statistical software | IBM | IBM SPSS Statistics 27.0 | Descriptive statistics, baseline comparisons, and quality-control analyses where used. |
| Statistical software | R Foundation for Statistical Computing | R, version recorded in analysis log | Regression analysis, mixed-effects models, Kaplan–Meier curves, Cox models, competing-risk models, multiple imputation, and sensitivity analyses. |
| Structured follow-up script | Study site | Local document set | Telephone or clinic follow-up at 1 week, 1 month, 3 months, 6 months, 12 months, 18 months, and 24 months. |
| Trigger-response log | Study site | Local document set | Documentation of GI intolerance, missed refill, treatment gap, regimen reassessment, switching decision, and corrective action. |
References
- Haentjens P, et al. Meta-analysis: excess mortality after hip fracture among older women and men. Ann Intern Med. 2010;152:380-390.
- Banefelt J, et al. Risk of imminent fracture following a previous fracture in a Swedish database study. Osteoporos Int. 2019;30:601-609.
- Conley RB, et al. Secondary fracture prevention: consensus clinical recommendations from a multistakeholder coalition. J Bone Miner Res. 2020;35:36-52.
- Caro JJ, Ishak KJ, Huybrechts KF, Raggio G, Naujoks C. The impact of compliance with osteoporosis therapy on fracture rates in actual practice. Osteoporos Int. 2004;15:1003-1008.
- Siris ES, et al. Impact of osteoporosis treatment adherence on fracture rates in North America and Europe. Am J Med. 2009;122:S3-S13.
- Siris ES, et al. Adherence to bisphosphonate therapy and fracture rates in osteoporotic women: relationship to vertebral and nonvertebral fractures from 2 US claims databases. Mayo Clin Proc. 2006;81:1013-1022.
- Keshishian A, et al. Examining the effect of medication adherence on risk of subsequent fracture among women with a fragility fracture in the U.S. Medicare population. J Manag Care Spec Pharm. 2017;23:1178-1190.
- Reyes BJ, et al. Postacute management of older adults suffering an osteoporotic hip fracture: a consensus statement from the International Geriatric Fracture Society. Geriatr Orthop Surg Rehabil. 2020;11:2151459320935100.
- Siris ES, et al. Association between gastrointestinal events and compliance with osteoporosis therapy. Bone Rep. 2015;4:5-10.
- Kennel KA, Drake MT. Adverse effects of bisphosphonates: implications for osteoporosis management. Mayo Clin Proc. 2009;84:632-638.
- Marsh D, et al. Coordinator-based systems for secondary prevention in fragility fracture patients. Osteoporos Int. 2011;22:2051-2065.
- Le HV, et al. Fracture liaison service: a multidisciplinary approach to osteoporosis management. Osteoporos Int. 2024;35:1719-1727.
- Hiligsmann M, et al. Determinants, consequences and potential solutions to poor adherence to anti-osteoporosis treatment: results of an expert group meeting organized by the European Society for Clinical and Economic Aspects of Osteoporosis, Osteoarthritis and Musculoskeletal Diseases and the International Osteoporosis Foundation. Osteoporos Int. 2019;30:2155-2165.
- von Elm E, et al. The Strengthening the Reporting of Observational Studies in Epidemiology statement: guidelines for reporting observational studies. Lancet. 2007;370:1453-1457.
- Prieto-Merino D, et al. Estimating proportion of days covered using real-world online medicine suppliers' datasets. J Pharm Policy Pract. 2021;14:113.
- Cadarette SM, Burden AM. Measuring and improving adherence to osteoporosis pharmacotherapy. Curr Opin Rheumatol. 2010;22:397-403.
- Kendler DL, et al. Repeating measurement of bone mineral density when monitoring with dual-energy X-ray absorptiometry: 2019 ISCD official position. J Clin Densitom. 2019;22:489-500.
- Fine JP, Gray RJ. A proportional hazards model for the subdistribution of a competing risk. J Am Stat Assoc. 1999;94:496-509.
- van Buuren S, Groothuis-Oudshoorn K. mice: multivariate imputation by chained equations in R. J Stat Softw. 2011;45:1-67.
- Ganda K, et al. Models of care for the secondary prevention of osteoporotic fractures: a systematic review and meta-analysis. Osteoporos Int. 2013;24:393-406.
- Lems WF, et al. EULAR/EFORT recommendations for management of patients older than 50 years with a fragility fracture and prevention of subsequent fractures. Ann Rheum Dis. 2017;76:802-810.
- Lam WY, Fresco P. Medication adherence measures: an overview. Biomed Res Int. 2015;2015:217047.
- Lyles KW, et al. Zoledronic acid and clinical fractures and mortality after hip fracture. N Engl J Med. 2007;357:1799-1809.
- Bliuc D, et al. Mortality risk associated with low-trauma osteoporotic fracture and subsequent fracture in men and women. JAMA. 2009;301:513-521.
- Hemming K, et al. The stepped wedge cluster randomised trial: rationale, design, analysis, and reporting. BMJ. 2015;350:h391.