This paper presents protocols for the bedside assessment of autonomic dysfunction in patients with Parkinson’s disease (PD) and multiple system atrophy (MSA). These protocols are categorized into three levels based on their simplicity and equipment requirements and are described using a step-by-step approach. Additionally, this paper provides clinical interpretation and troubleshooting.
Method Article
Protocols for Bedside Assessment of Autonomic Dysfunction in Parkinson's Disease and Multiple System Atrophy
In This Article
Summary
Abstract
Assessment of autonomic dysfunction is crucial for clinical management of PD and MSA. Autonomic dysfunction can provide important clues for its diagnosis and clinical management. Furthermore, it often progresses over time and significantly affects patients’ quality of life. Therefore, it is essential to develop bedside clinical assessment protocols for autonomic dysfunction. This paper provides a step-by-step description to demonstrate the evaluation method. In both outpatient and bedside settings, autonomic function should be systematically evaluated: beginning with a medical interview, followed by a physical examination and, when necessary, using simple instrumental tests. Assessment should emphasize circulatory, sudomotor, urinary, and bowel dysfunction. This paper will explain each of the following items. Circulatory assessment: medical interview, evaluation of cold-discolored extremities, capillary refill, 10-second cold water stress load test, active standing test, the coefficient of variation of R-R intervals, and overnight oximetry provides further detailed evaluation in MSA. Sudomotor symptoms: medical interview, assessment of sweating at rest and under stress using palpation, visual inspection, and the spoon test, and finger wrinkling after immersion in warm water. Urinary assessment: urination frequency, sensation of incomplete bladder emptying, voiding diaries, and the measurement of post-void residual (PVR) urine volume. Bowel assessment: medical interview, abdominal percussion, and rectal ultrasonography. Bedside assessment is influenced by the examiner's experience, medication, and the testing environment. Considering the limitations of bedside assessments, more comprehensive diagnostic evaluations should be conducted when necessary. We also describe the characteristics of autonomic dysfunction in PD and MSA. Appropriate management of each type of autonomic dysfunction is also essential.
Introduction
The purpose of this protocol is to provide a comprehensive, step-by-step approach for evaluating autonomic function at the bedside, focusing on the circulatory, sudomotor, urinary, and bowel systems. Autonomic dysfunction is a key feature of PD and MSA, which provides crucial diagnostic and prognostic information. In patients with PD and MSA, autonomic dysfunction affects daily life and progresses over time. Impaired communication can make it difficult for patients to report symptoms. Therefore, mastering noninvasive bedside assessment protocols for autonomic dysfunction is necessary. However, bedside assessments are often performed inconsistently in clinical practice. Several studies have reported new bedside methods for assessing and interpreting autonomic dysfunction in patients with PD and MSA. However, it is difficult for clinicians to grasp all of these at once and to judge their priorities. This manuscript therefore reviews and summarizes existing reports.
The primary benefits of bedside protocols in the clinical management of patients with PD and MSA are accessibility and sustainability. Various methods exist for the detailed assessment of autonomic function; however, they often face limitations in terms of institutional accessibility, invasiveness, and time requirements. For example, the head-up tilt test, which is valuable for assessing blood pressure (BP) variability, requires the use of a tilt table1. For sudomotor function, the thermoregulatory sweat test requires a special chamber, while the quantitative sudomotor axon reflex test requires a multi-compartmental sweat capsule2. Although these methods provide highly reliable results, their limited availability renders long-term monitoring impractical. Furthermore, although urodynamic testing is useful for evaluating lower urinary tract dysfunction, it is invasive because it requires catheterization and requires high clinical expertise for equipment operation and calibration3. Given these constraints, routinely performing these tests for the clinical management of patients with PD or MSA remains challenging. Therefore, the development of practical bedside assessment protocols is essential.
Although various methods for the bedside assessment of autonomic dysfunction have been reported individually in the literature, even existing comprehensive literature and textbooks often merely list these methods exhaustively. Consequently, they lack a systematic framework that guides clinicians in prioritizing tests, leaving many detailed procedures unclear4,5,6. Furthermore, existing research protocols generally assume that patients can fully complete the examinations. Therefore, they lack comprehensive guidelines for addressing clinical challenges, such as cases where tests cannot be completed7,8, equipment is unavailable, or troubleshooting is required. This protocol addresses this gap by integrating circulatory, sudomotor, urinary, and bowel assessments into a step-by-step protocol and tiered workflow (Figure 1), comprising core bedside screening (Core), optional bedside instrumental assessment (Optional), and advanced or referral-level testing (Advanced) examinations specifically applicable to patients with PD and MSA. It further provides disease-specific interpretations, contraindications, common sources of errors, troubleshooting, and alternative approaches when the procedure cannot be completed. The protocol is based on previously established methods and current diagnostic criteria; as such, its contribution is not the introduction of a new diagnostic test, but the development of a practical and reproducible framework for bedside autonomic assessment.
‘Core’ screening refers to essential screening tasks that can be performed in any setting. Such techniques require no specialized equipment other than the tools available in all medical institutions, such as sphygmomanometers, which are cost-effective and technically accessible. The 'Optional' assessment involves the use of specialized tools; while not strictly mandatory, these tests are highly recommended for the diagnosis and practice of patients with PD and MSA, and can be conducted with minimal training. Conversely, 'Advanced' testing encompasses tests which are beneficial for the management of MSA and PD, but not strictly essential. Such tests should require specialized equipment and a significant training period to achieve proficiency. Although autonomic dysfunction is associated with various neurodegenerative diseases, onset time, clinical characteristics, and diagnostic criteria vary across individual diseases.
In this paper, the protocols and interpretations focus on autonomic dysfunction associated with PD or MSA; therefore, the clinical features and interpretations do not apply to all neurodegenerative diseases. In this manuscript, the section titled “Bedside Assessment Protocol” provides the protocols and methods for interpretation. The section titled "Representative Results" outlines important considerations and how to apply the findings in clinical practice in PD and MSA.
Protocol
This manuscript serves exclusively as an educational demonstration and does not constitute human subject clinical research. Participation by the staff at the Department of Neurology, Gifu University Graduate School of Medicine, was entirely voluntary. Each participant provided written informed consent to participate. The list of materials used for this protocol has been provided in the Table of Materials.
1. Preparation before examination
- Identify the patients’ chief complaints and diurnal variations in autonomic dysfunction.
- Confirm the factors that may affect autonomic function, including medications and comorbidities such as diabetes mellitus, peripheral vascular disease, dehydration, cardiac disease, prostatic conditions, pelvic floor disorders, dermatological conditions, peripheral neuropathy.
- Explain the purpose and methods of the examinations.
- Confirm the patient’s current medications and the timing of their last meal and drink.
- Prepare the necessary personnel and devices.
- Decide whether to discontinue the interfering medication.
- Confirm patients’ medication.
- Evaluate the risks of withdrawal: Recognize that the sudden cessation of agents may trigger serious adverse events (Table 1)9,10.
- Make an individualized clinical decision for medication discontinuation.
NOTE: When medication discontinuation is not possible, adjust the interpretation of the assessment findings accordingly (Table 1)9,10.
2. Bedside Assessment Protocol
- Circulatory assessment
- Medical interview (Core)
NOTE: Medical interview should focus on peripheral circulation and orthostatic hypotension (OH).- Peripheral circulation.
- Inquire about episodes of coldness and changes in the skin color of the hands and feet.
- If present, identify the temperature and the situations that trigger these changes.
- Confirm whether symptoms improve with warming.
- Orthostatic hypotension (OH)
- Inquire about the symptoms that occur in the standing position and resolve them in the supine position11, especially syncope, dizziness, vision and head discomfort, fatigue, and decreased concentration.
- Confirm the duration between standing and symptoms onset, as well as potential triggering situations (e.g., after meals, bathing, and defecation).
- Peripheral circulation.
- Cold-discolored extremities
NOTE: Cold-discolored extremities refer to coldness and color changes in the hands and feet caused by peripheral circulation insufficiency12,13.- Inspection of the extremities (Core)4,14
- Confirm whether the skin shows a purplish tone or pallor.
- Palpate hands and feet and assess skin coolness.
- Evaluate the differences between the left and right sides as well as between the hands and feet.
NOTE: A digital thermometer, along with thermography, provides a more objective assessment (Advanced).
- Capillary refill (Core)4,12
- Apply pressure with your thumb to the back of your own hand or foot (as a healthy control) until the skin surface blanches.
- Release the pressure.
- Measure the time it takes for the skin color to return to its original state (capillary refill time).
- Apply the same amount of pressure to the patient’s hand or foot dorsum.
- Release the pressure.
- Measure the patient’s capillary refill time.
- Compare the patient's capillary refill time with your own.
NOTE: A longer capillary refill time in the patient than in the health control may indicate an abnormality.
- 10 s cold water stress test (Optional)15
- Check for the following contraindications: Raynaud's phenomenon, severe uncontrolled hypertension, cardiovascular disease, peripheral vascular disease, and history of frostbite on the hands.
- Measure skin temperature after a 15 min rest in a room set at 25 °C and 50% humidity.
- Immerse the patient’s finger in 4 °C water for 10 s.
- Remove finger from the water.
- Measure the skin temperature every min for 15 min by a digital thermometer.
- Inspection of the extremities (Core)4,14
- Active standing test (Core)4,5
- Conduct the examination in the morning in a quiet room with controlled temperature (20–25 °C) and humidity (40–60%).
- Choose a BP monitor. An automated BP monitor is preferable; however, a manual BP monitor may also be used.
- Choose the cuff covering about 80% of the upper arm16.
- Attach BP and heart rate (HR) monitors to the patient.
- Keep the patient in the supine position for 10 min.
- Measure BP and HR.
- Ask the patient to stand quickly from the supine position (within 3 s).
- Support the patient’s arm to ensure the cuff is positioned at the level of the right atrium (sternal angle).
- Measure the BP and HR immediately after standing, and then every minute for 10 min.
- Stop the test immediately if the patient develops fatigue, pallor, hyperventilation, or a decrease in BP of ≥60 mmHg.
- Classify the OH as initial, classical, or delayed. Initial OH is defined as a decrease of >40 mmHg in systolic blood pressure (SBP) and/or >20 mmHg in diastolic blood pressure (DBP) within 15 s of standing. Classical OH is defined as a sustained decrease in SBP > 20 mmHg and/or DBP > 10 mmHg within 3 min of standing. Delayed OH is defined as OH later than 3 min after standing.
- When SBP decreases by >20 mmHg, calculate the ΔHR/ΔSBP ratio. ΔHR/ΔSBP < 0.5 suggests neurogenic OH17. However, this criterion cannot be applied to patients taking beta-blockers or those with pacemakers.
- Perform a tilt-table test if OH is suspected, even when the orthostatic test results are negative.
- Perform an ambulatory blood pressure monitoring (ABPM) to assess the impact of diurnal variation and specific events on BP if necessary16.
- Other assessments (CVR-R and overnight oximetry) (Optional, Advanced)
NOTE: After adequate medical interview and orthostatic testing, the coefficient of R-R intervals (CVR-R), ABPM, and overnight oximetry can provide a more detailed evaluation of circulatory autonomic dysfunction. However, these examinations have institutional, locational, and temporal limitations as they require specialized equipment and prolonged monitoring, including overnight recordings.- CVR-R (Optional)
NOTE: CVR-R reflects the pulse rate variability at rest. It is primarily influenced by the parasympathetic nervous system; however, the sympathetic nervous system also partially contributes5,18.- Keep the patient at rest in the supine position for 15 min in a room maintained at 25 °C.
- Record an electrocardiogram for 100 beats at rest and during controlled breathing at six deep breaths per minute (5 s inhalation and 5 s exhalation).
- Obtain mean R-R intervals (mRR) and the R-R standard deviation (RR-SD) by an electrocardiogram. Calculate CVR-R as RR-SD/mRR x 100(%)18.
- Compare the results with reference values. Average CVR-R values are as follows: 10–29 years, 6%; 30–59 years, 3.4%; and >60 years, 2.8%. A Ten CVR-R < 2% at rest is considered abnormal at all ages. CVR-R is higher during deep breathing than at rest, providing greater sensitivity for detecting autonomic dysfunction18.
- Do not interpret the CVR-R results in patients with a history of ischemic heart disease, concurrent arrhythmias, or those taking medications that influence HR (e.g., beta blockers or other antiarrhythmic drugs)5,18,19.
- Overnight oximetry (Advanced)20
NOTE: Overnight oximetry assesses HR variability in response to hypoxia during sleep.- Place a pulse oximeter on the patient’s finger and secure the recording device to the wrist using the provided strap.
- Record overnight variations in oxygen saturation (SpO2) and pulse rate.
- Confirm the oxygen desaturation index (ODI) and the pulse event index (PEI).
NOTE: The ODI is defined as the number of >4% decreases in SpO2 from the average per hour. The PEI is the number of >6 bpm PR decreases in PR from the average per hour. - Calculate PEI/ODI ratio. A value <1 suggests autonomic dysfunction in patients with MSA20.
- CVR-R (Optional)
- Medical interview (Core)
- Sudomotor assessment6
- Medical interview (Core)
- Inquire about the symptoms of sweating abnormalities, including increased or decreased sweating, their distribution, and precipitating situations.
- Classify the symptoms as hypohidrosis, anhidrosis, and hyperhidrosis.
- Identify the area of sweating, whether on the palms and soles or the entire body.
- When evaluating hypohidrosis, confirm whether sweating under conditions that normally provoke sweating (e.g., during summer heat, after exercise, or after bathing) has decreased relative to the patient’s baseline.
- Confirm whether hypohidrosis is generalized or segmental/partial, including the unilateral, lower-body, localized, and distal forms.
- When evaluating hyperhidrosis, identify the precipitating conditions, including temperature, physical activity, emotional stress, and food intake.
- Determine whether hyperhidrosis is generalized or partial.
- Inspection and palpation of the skin5,6 (Core)
- Allow the patient to rest for 10–15 min in a climate-controlled room maintained at 25 °C and below 40% relative humidity.
- Touch and observe the regions of hypohidrosis, which may feel dry and appear smooth because of reduced moisture.
NOTE: These test results may be influenced by age, room temperature, humidity, hydration status, medications, mental status, skin condition, and the examiner's interpretation.
- Spoon test (Core)21,22
- Hold a dry spoon between the thumb and index finger.
- Gently stroke the back of the spoon along the skin surface, following the skin folds.
- Stroke each of the following areas once on both the left and right sides: the forehead, neck, chest, forearm, hand dorsum, proximal leg, and foot dorsum.
- Check whether the spoon stops moving on the skin.
- If the spoon stops moving, record the result as positive.
- In areas where the spoon adheres to moist skin, quickly dry the area before proceeding to stroke the next site.
NOTE: Although the spoon test has low inter-examiner variability, it remains a qualitative assessment21.
- Induction of sweating by mental arithmetic (Core)
- Tell the patient to keep subtracting 7 from 100.
- Examine whether sweating is induced on the palms and soles during mental arithmetic.
- Terminate the exam after assessing sweating on all limbs.
- Evaluate the differences in sweating across various skin regions, including asymmetry and regional distribution. In the anhidrotic areas, leopard-like patches of preserved sweating, referred to as patchy sweating, are observed. In areas of hyperhidrosis, increased skin moisture and “beaded sweat” are observed.
- Finger wrinkling test (Optional)24,25
NOTE: This test evaluates autonomic nerve function surrounding the sweat glands.- Immerse the patient’s hand in 40 °C water for 30 min.
- Assess the degree of finger wrinkling on all 10 fingers.
- Grade the result on the fingertips according to the following scale25: Grade 0- no evidence of skin wrinkling; Grade 1- skin not completely smooth; Grade 2- two or fewer lines of wrinkling; Grade 3- three or more wrinkle lines; Grade 4- wrinkling completely distorting the pulp of the finger. Compare the grades between the left and right hands (Figure 2).
NOTE: This test is susceptible to factors such as skin conditions and should therefore be considered as a supplementary examination only.
- Medical interview (Core)
- Urinary function assessment
- Medical interview (Core)
- Urine storage
- Confirm urinary frequency during the daytime and nighttime.
- Confirm whether the frequency is bothersome.
NOTE: In daily urination, more than 8 times a day is a criterion for lowering the quality of life (QOL)26,27. At night, urination (more than two voids per night) negatively affects the QOL28. - Confirm urinary urgency, which is a sudden and unbearable urge.
- Confirm urinary incontinence, characterized by a strong urge to urinate and involuntary urine leakage.
- Urination disorders
- Confirm delays in the initiation of urination and urine flow, the need for abdominal straining, and prolonged voiding time.
- Evaluate factors affecting both storage and voiding function, including medication, sleep, anxiety, cognitive impairment, neurological symptoms, and lumbar disc herniation (LDH).
- Urine storage
- Micturition diary29 (Core)
- Tell the patients to record the time of urination, hydration, and urinary incontinence.
- Instruct the patient to measure and record their fluid intake and urine output accurately, if possible.
- Instruct the patients to record subjective symptoms such as urinary urgency.
- Tell the patients to record the wake-up time and bedtime, and the time of taking medicine.
- Instruct the patient to continue recording for at least three days.
- Measurement of PVR (Core, Optional)
NOTE: Assessment of the PVR volume is important for distinguishing and managing storage and voiding disorders. Perform the assessment immediately after voiding.- Abdominal examination to assess PVR volume (Core)
- Place the patient in the supine position with knees flexed.
- Observe suprapubic distension, which may become visible when the bladder volume exceeds 500 mL.
- Perform abdominal palpation and percussion; abnormal findings may be detected when the volume exceeds 150-200 mL30. Perform the examination gently to minimize bladder irritation.
- Automated bladder scanner (Optional)31,32
- Conduct the scan immediately following urination (within 10 min).
- Place the patient in the supine position.
- Apply gel to the contact surface of the probe.
- Locate the pubic symphysis manually.
- Place the probe on the central line superior to the pubic symphysis.
- Press the "Start/Determine" button.
- Move the probe cranially until the displayed maximum bladder volume coincides with the peak of the graph.
- Press the "Start/Determine" button at that position.
- Do not move the probe during scanning.
- Repeat the test at least twice to ensure an accurate evaluation.
NOTE: Bladder scanner measurements may be inaccurate in patients with ascites, prior pelvic surgery, indwelling urinary catheters, or obesity31.
- The other methods to measure PVR volume (Advanced)31,32
- Measure the longitudinal, transverse, and anteroposterior diameters of the bladder using ultrasonography, or measure the PVR volume by catheterization to calculate bladder volume in cases where bladder scanning is inappropriate.
- Consult the urology department if PVR volume cannot be obtained or if the results are inconsistent.
- Abdominal examination to assess PVR volume (Core)
- Other assessments (Core)
NOTE: Organic disorders may also cause urinary dysfunction.- Perform inspection and palpation of the abdomen and genitalia to assess conditions such as LDH, pelvic organ prolapse, and uterine leiomyoma.
- Perform a digital rectal examination to detect prostatic hypertrophy.
- Conduct cognitive and neurological examinations to identify the underlying conditions that cause functional urinary incontinence.
- Medical interview (Core)
- Bowel function assessment
- Medical interview (Core)34,35
- Confirm whether the patient is aware of constipation.
- Inquire about the onset of constipation.
- Confirm the number of bowel movements per week. Slow-transit constipation is defined as fewer than three bowel movements per week.
- Inquire about stool consistency and form.
- Confirm whether bowel movements are accompanied by abdominal pain and loose stools unrelated to laxative use to help differentiate constipation from irritable bowel syndrome with constipation.
- Confirm whether the bowel movements are accompanied by outlet obstruction, excessive straining, incomplete evacuation, and manual maneuvers.
- Assess for pharmacological causes of constipation and a history of abdominal surgery.
- Classify the severity of subjective constipation symptoms according to the constipation item of the Movement Disorder Society-sponsored revision of the Unified Parkinson's Disease Rating Scale (MDS-UPDRS).
NOTE: Rating scale as per MDS-UPDRS is: 0- no constipation, 1- constipation is present and requires extra effort to defecate, but it does not interfere with daily life or cause discomfort, 2- constipation causes some problems with daily life or feelings of discomfort, 3- constipation causes significant problems with daily life or considerable discomfort, although the patient is not completely unable to function, 4- physical assistance from another person (e.g., enema or manual disimpaction) is generally required for defecation36.
- Defecation diary (Core)
NOTE: A defecation diary is useful for assessing bowel dysfunction, considering the limited outpatient consultation time and day-to-day variability in bowel symptoms.- Instruct the patient to record the time of defecation, stool volume, stool consistency, and symptoms during defecation.
- Categorize stool consistency objectively based on the Bristol Stool Form scale37.
- Physical examination of the abdomen (Core)
NOTE: Physical examinations should include an abdominal examination, inspection of the perineum, and digital rectal examination.- Place the patient in the supine position with the knees flexed to relax the abdominal muscles.
- Perform auscultation to listen to bowel sounds that indicate intestinal peristalsis.
- Perform percussion of the abdomen to check for tympany, which suggests the presence of intestinal gas.
- Perform abdominal palpation to detect abdominal distension, tenderness, and masses. Examine the entire abdomen systematically, assessing areas of pain or symptoms last.
- Perform an inspection of the perineum. Check for perianal lesions such as hemorrhoids, anal fissures, and rectal prolapse.
- Observe perineal descent and anal gaping during straining, imaging evacuation.
- The digital rectal examination.
- Place the patient in the lateral recumbent position with the knees flexed.
- Tell the patient to exhale slowly.
- Insert a lubricated index finger gently into the anal canal.
- Check for the contraction of sphincter tone and fecal mass in the rectum.
- Assess anal sphincter relaxation during simulated defecation.
- Rectal ultrasonography (Advanced)
NOTE: Transabdominal rectal ultrasonography can noninvasively assess rectal fecal retention and is useful for the diagnosis of constipation and the evaluation of treatment38.- Perform rectal ultrasonography when the bladder is full.
- Set the ultrasound frequency to 5 MHz and depth to 6–15 cm.
- Put the probe (convex type) on the lower abdomen in the supine position transversely.
- Sweep caudally to identify the level of maximum bladder area.
- Check the appearance of the rectum: “Crescent sign”, “Full moon sign”, or no obvious hyperechoic area 39.
NOTE: The “Crescent sign” indicates a small amount of retained fecal material along the rectal wall. The “Full-moon sign” indicates a fecal material occupying the entire rectal lumen. In the absence of rectal feces, the rectum can be visualized behind the bladder without an associated hyperechoic shadow. This method serves as a supportive assessment for fecal impaction but is insufficient to diagnose the underlying etiology of constipation. In cases of obesity, bladder volume less than 100 mL, and the presence of gastrointestinal gas, assessment accuracy may sometimes be compromised.
- Medical interview (Core)34,35
Results
This section summarizes the interpretation of bedside assessment findings in PD and MSA. Interpretation of findings is organized according to the supportive clinical features, exploratory research findings, and validated diagnostic criteria.
Circulatory assessment
Cold-discolored extremities: validated diagnostic criteria
Examination of autopsy cases revealed the prevalence of cold-discolored extremities; MSA was 20.3%, PD was 5.7%, progressive supranuclear palsy (PSP)- Richardson syndrome was 2.9%, and PSP-Parkinsonism was 0%; therefore, MSA has an especially high prevalence40. Therefore, the criteria for MSA positioned this symptom as a supportive clinical feature17.
Cold-discolored extremities: exploratory research findings
In an observational study involving 184 patients with MSA whose medical records for less than 3 years from onset were available, patients with MSA with cold-discolored extremities tended to have higher scores on the Unified MSA Rating Scale and Non-Motor Symptom Scale, which reflect the severity of motor and nonmotor symptoms, and shorter survival time41. Cold-discolored extremities can be prognostic factors. Assessment of skin temperature alone helps in the diagnosis. The comparison among 25 healthy, 50 PD, and 50 MSA patients reported that the skin temperature of patients with PD and MSA was significantly lower than that of healthy controls42. However, the skin temperature in patients with PD was the same as that of those with MSA. A skin temperature below 28 °C was detected only in 6% of patients with MSA. This very small ratio could not differentiate between PD and MSA.
10 second cold water stress test: exploratory research findings
10 second cold water stress test was performed with no adverse events or dropout, while the trial utilizing an ice pack in 857 patients, including PD, MSA, and healthy, had a dropout rate of approximately 13–14%43. A retrospective study of the 10-second cold water stress test included 27 of PD and 7 of MSA who were diagnosed at least 5 years after disease onset15. In conclusion, patients with MSA recovered skin temperature faster than patients with PD. 9.6 °C at thermography 11 min post-cooling could differentiate MSA from PD with a sensitivity of 80.3% and specificity of 85.7%.
Active standing test: validated diagnostic criteria
Because PD has a higher comorbidity of delayed OH than COH, extending the active standing test by 10 min after standing can improve the sensitivity for OH5. Focusing on the MSA criteria regarding OH, the BP decrease criterion was changed from >30/15 mmHg in the Gilman classification to >20/10 mmHg in the movement disorder society proposed, as the change improved the sensitivity of MSA diagnosis from 28–48%17.
Active standing test: exploratory research findings
In a study, 255 patients (67 of MSA, 188 of PD) were tested with continuous non-invasive BP monitoring and an active standing test. The study demonstrated the high comorbidity rate of OH among patients with MSA and PD; MSA was classical OH (COH), and PD was initial OH7. MSA patients tend to have higher SBP and DBP in the supine position, and HR and lower ΔHR and ΔSBP than PD patients. ΔHR/ΔSBP at 10 min post-standing was suggested to distinguish MSA-OH from PD-OH7.
In another study, 1,809 patients with PD were divided into akinetic-rigid (AR), mixed (M), and tremor-dominant subtypes. The AR subtype has been reported to have more BP decrease than the M subtype in the active standing test8.
CVR-R, ambulatory BP monitoring, overnight oximetry: exploratory research findings
A study of 73 patients with PD was conducted to investigate the CVR-R. The results showed that, in patients within two years of disease onset, there was a significant positive correlation between the heart-to-mediastinum (H/M) ratio on 123I-meta-iodobenzylguanidine myocardial scintigraphy and CVR-R, with lower H/M ratios being associated with lower CVR-R. Furthermore, the study reported that a lower CVR-R was significantly associated with a higher prevalence of orthostatic hypotension44. The PEI/ODI of overnight oximetry is an increase in HR in response to a SpO2 decrease. In a retrospective study on 26 of MSA, patients who died suddenly had a lower PEI/ODI ratio during their lifetime. A long-term follow-up study showed that every patient had a decrease in the PEI/ODI, which was reported as a possible prognostic factor20. The utility of PEI/ODI of overnight oximetry for evaluating autonomic functions other than MSA has not yet been investigated.
Sudomotor assessment: exploratory research findings
One prospective study involving 205 patients with autonomic dysfunction, including PD and MSA, evaluated the sensitivity and specificity of palpation, visual inspection, and the spoon test compared with the thermoregulatory sweat test22. The results indicated that the sensitivity was low for visual inspection (less than 5%) and palpation (less than 17%, even at the neck, where it was the highest). For the spoon test, while sensitivity remained low in the upper and lower extremities (4–15%), with values of approximately 50% in the forehead and trunk, reaching 85% in the neck region. Both visual inspection and palpation demonstrated 100% specificity. For the spoon test, specificity was slightly lower in the neck (56%) but remained high in other body regions.
In a study of 18 patients with PD (Hoehn and Yahr 1–3) exhibiting hemiparkinsonism, the total number of finger wrinkles following immersion in 40℃ water was compared. The results showed 15.3 ± 8.5 wrinkles in healthy controls, while the affected-side fingers had 13.1 ± 6.8 wrinkles, and the unaffected-side fingers had 6.1 ± 6.8 wrinkles, suggesting that autonomic dysfunction was more pronounced on the unaffected-side24. Regarding the wrinkle grading protocol, a comparison between 15 patients with autonomic dysfunction (including 3 patients with PD) and healthy subjects revealed a median grade sum (for digits 2–5 of the right hand) of 15 (11.25–16) in the healthy group, compared to 12 (8–14) in the patient group26.
Urinary function disorder: validated diagnostic criteria
A prospective cohort study of 121 patients with MSA reported that 18% of patients complained of lower urinary tract symptoms as the only initial symptom45. Furthermore, patients with MSA reported urinary incontinence at an average of 2.8 years before the emergence of any motor symptoms45. A retrospective study of 33 patients with PD and 32 patients with MSA-P reported that an increase in PVR volume measured by bladder scanning was accompanied by MSA progression, the features of which are differentiation points of PD: sensitivity, 34%; specificity, 95%46.
Bowel function disorder: validated diagnostic criteria
A prospective study of 465 patients with PD (Hoehn and Yahr II or lower) investigated the correlation between medical interview results regarding constipation and cognitive dysfunction. Each complaint was defined using the MDS-UPDRS constipation item, for which a score of 0 indicated no complaints, 1 indicated minor/moderate complaints, and 2–4 indicated major complaints. Over an average follow-up period of 5.1 years, the researchers found that greater constipation severity was a significant prognostic factor for worse cognitive decline47.
Bowel function disorder: supportive clinical features
Rectal ultrasonography may serve as supportive insight for competitive treatment. In a prospective study of 163 patients who visited the emergency department for constipation, the sensitivity and specificity of rectal ultrasonography compared to abdominal X-ray were reported as 0.84 and 0.94, respectively48. Rectal ultrasonography shows potential as a non-invasive method for evaluating rectal fecal impaction easily. However, no studies regarding PD or MSA have been reported, and further research is required.
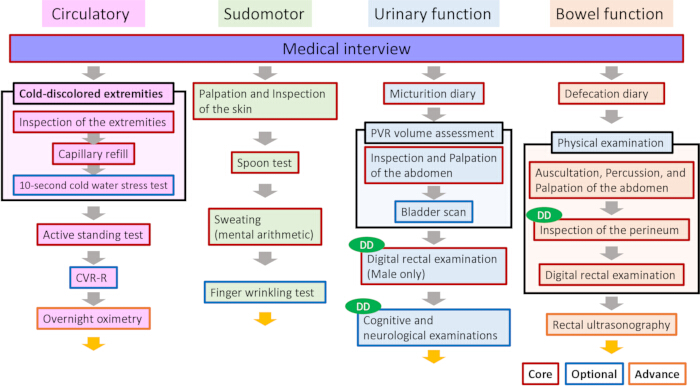
Figure 1: Workflow for bedside assessment of autonomic dysfunction. This figure illustrates the overall workflow for bedside assessment of autonomic dysfunction in patients with Parkinson's disease and MSA. Core bedside screening is enclosed in red boxes, optional bedside instrumental assessment in blue, and advanced or referral-level testing in orange. Orange arrows indicate that when bedside assessment is insufficient, further investigations or specialist consultation are recommended. ‘Core’ means core bedside screening. ‘Optional’ means an optional bedside instrumental assessment. ‘Advanced’ means advanced or referral-level testing. Abbreviations used: DD = differential diagnosis. Please click here to view a larger version of this figure.
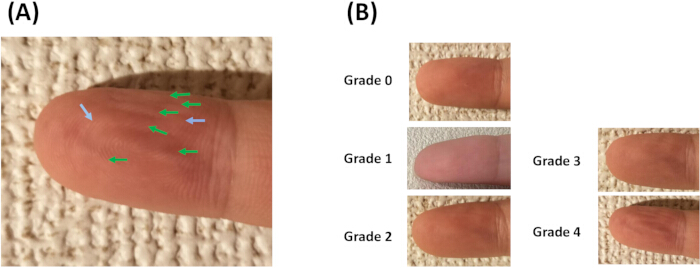
Figure 2. Finger wrinkling grading for assessment of sudomotor function. (A) Magnified view of the finger wrinkles. Green arrows indicate individual wrinkle lines. Light blue arrows indicate areas where wrinkles have merged (fused). (B) The grading criteria (Grades 0–4) based on wrinkle severity. Please click here to view a larger version of this figure.
Table 1: Medications that may affect bedside assessment of autonomic dysfunction9,10. This table summarizes the drug classes, mechanisms of action, potentially affected autonomic domains (circulation, sweating, and urination), effects on autonomic symptoms or test interpretation, approximate times corresponding to the five elimination half-lives, and clinical considerations for temporary withholding. A plus sign (+) indicates that a medication may affect symptoms, measurements, or interpretation in that domain; a minus sign (−) indicates that no substantial direct effect is expected at usual doses. Although not universally agreed, this is sometimes used as a medication washout period for autonomic testing. Abbreviations: ACE = angiotensin-converting enzyme; ARB = angiotensin II receptor blocker; AV = atrioventricular; BP = blood pressure; BPH = benign prostatic hyperplasia; COMT = catechol-O-methyltransferase; D2/D3 = dopamine receptors; DOPA = 3,4-dihydroxyphenylalanine; ER = extended-release; HR = heart rate; IR = immediate release; MAO-B = monoamine oxidase B; NMDA = N-methyl-D-aspartate; OAB = overactive bladder; OH = orthostatic hypotension; PVR = post-void residual; RAAS = renin–angiotensin–aldosterone system. Please click here to download this Table.
Discussion
These protocols provide an approach for bedside assessment of autonomic dysfunction. In assessing any domain, it is essential to have a comprehensive medical history and conduct patient interviews, followed by assessment using appropriate clinical procedures. The primary advantage of these bedside assessment protocols is their high accessibility, which facilitates continuous monitoring. This allows for early detection of autonomic dysfunction, thereby providing opportunities for timely clinical intervention. Furthermore, these protocols remain applicable even when patients transition from outpatient care to home-based care.
When implementing this protocol, it is necessary to be aware of the available troubleshooting methods. Although it is preferable to assess autonomic dysfunction under consistent conditions, including temperature, this is sometimes difficult to achieve in clinical practice. If it is difficult to maintain consistent conditions, the temperature and humidity should be noted, and the results should be interpreted by considering these modifying factors. Measuring BP at one-minute intervals is insufficient to capture the rapid hemodynamic changes that occur within 15 s of standing. Therefore, the diagnosis of initial OH requires continuous beat-to-beat BP monitoring. This can be achieved by using either the Finapres method (finger arterial photoplethysmography) or invasive arterial pressure monitoring49. If patients cannot maintain a standing posture independently, a passive transition to a seated position may serve as an alternative. However, this approach requires caution, as it has not been sufficiently validated in patients with PD or MSA50. If the patient cannot consistently maintain a micturition or defecation diary due to cognitive dysfunction, have the caregiver record it or proceed to the next test step29.
The protocols described herein were based on previously established methods and interpretations. However, because this information is scattered across numerous publications, it is difficult for clinicians to comprehensively grasp it. Furthermore, some studies have failed to provide sufficient information regarding the specific conditions required for testing. In the present study, we provide a comprehensive, step-by-step guide for bedside assessment protocols and clinical interpretation of autonomic dysfunction in patients with PD and MSA. We believe that this systematic framework is highly valuable in clinical practice.
This bedside assessment has several limitations. Firstly, as the disease progresses, complications such as cognitive impairment may develop, or physical conditions, such as the inability to stand may arise, making continuous assessment using a consistent method difficult30,50. Additionally, changes in unavoidable medications could influence the results, precluding direct comparisons with previous data9,10. In clinical settings such as outpatient clinics, where time constraints prevent adequate rest periods or where it is difficult to maintain a uniform ambient temperature and humidity, the reliability of the results may be compromised4,5,24. In cases where patient complaints are inconsistent with clinical findings or when bedside assessment is unreliable owing to underlying comorbidities, specialized autonomic testing or consultation with a subspecialist is warranted. The described protocols require an understanding of the prerequisite knowledge, clinical notes, and potential troubleshooting strategies.
These protocols have the potential for application in studies of autonomic function in patients with PD and MSA. Their feasibility for early-stage implementation across facilities, combined with minimal patient burden, facilitates continuous assessment. This makes them valuable tools for investigating autonomic dysfunctions related to disease progression and prognosis. However, for research purposes, it is crucial to standardize conditions, such as rest periods, ambient temperature, humidity, and medication, both across different patients and at different time points for the same patient.
Disclosures
The authors have no disclosures regarding this manuscript.
Acknowledgements
We would like to thank Editage for English language editing. We thank the staff of the Department of Neurology at Gifu University Graduate School of Medicine for their cooperation in the video recording.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Elemano2 | TERUMO | 228AHBZX00029 | |
| FCP-9800 | Fukuda Denshi | 303ADBZX00038000 | |
| GEL-SCAN-CA | FUJIFILM | 66-0038-95 | |
| Lilium α-200 | Ozuka | 227ADBZX00146000 | |
| PULSOX-300i | KONICA MINOLTA | 225AABZX00066000 | |
| Thermal Imager Mini2 V2 | HIKMICR | EA3141976 | |
| Vscan Air | GE healthcare Japan | VA002001517 |
References
- Fereshtehnejad SM, Lökk J. Orthostatic hypotension in patients with Parkinson's disease and atypical parkinsonism. Parkinsons Dis. 2014;2014:475854.
- Illigens BM, Gibbons CH. Sweat testing to evaluate autonomic function. Clin Auton Res. 2009;19:79-87.
- Raz O, Tse V, Chan L. Urodynamic testing: physiological background, setting-up, calibration and artefacts. BJU Int. 2014;114:22-8.
- Campese N, Leys F, Wenning GK, Fanciulli A. Bedside assessment of autonomic dysfunction in multiple system atrophy. J Parkinsons Dis. 2022;12:2277-81.
- Japan Society of Neurovegetative Research. Diagnostic test of autonomic nervous function, 5th ed. Bunkodo; Tokyo; 2015.
- Hirayama K, editor. Neurological symptomatology with color illustrations. Rev. 2nd ed. Bunkodo; Tokyo; 2005.
- Zeng J, et al. The differences of orthostatic hypotension in patients with Parkinson's disease and multiple system atrophy. Front Neurol. 2023 14:1070943.
- Oikonomou P, Koschel J, Altmann CF, Jost WH. Differences in prevalence of orthostatic hypotension between Parkinson's Disease motor subtypes. Neurol Neurochir Pol. 2025;59:188-90.
- Lipp A, et al. Ventilatory and cardiovascular responses to hypercapnia and hypoxia in multiple-system atrophy. Arch Neurol. 2010;67:211-6.
- Huang CC, Lai YR, Lien CY, Cheng BC, Kung CT, Chiang YF, et al. Effectiveness of different methods for baroreflex sensitivity assessment in determining the severity of cardiovascular autonomic neuropathy in patients with Parkinson's disease. Front Neurosci. 2022;16:833344.
- Kaufmann H, et al. The orthostatic hypotension questionnaire (OHQ): validation of a novel symptom assessment scale. Clin Auton Res. 2012;22:79-90.
- Klein C, Brown R, Wenning G, Quinn N. The cold hands sign in multiple system atrophy. Mov Disord. 1997;12:514-8.
- Shindo K, Tsuchiya M, Ichinose Y, Koh K, Hata T, Yamashiro N, et al. Pre- and postganglionic vasomotor dysfunction causes distal limb coldness in multiple system atrophy. J Neurol Sci. 2017;380:191-195.
- Reich SG. The cold hands sign in MSA. Multiple system atrophy. Neurology. 2003;60:719.
- Takahashi M, Hagiwara W, Itaya S, Abe K, Maeda T, Inaba A, et al. Ten-second cold water stress test differentiates Parkinson's disease from multiple system atrophy: a cross-sectional pilot study. Biomedicines. 2025;13:1585.
- Staessen JA, Fagard R, Thijs L, Amery A. A consensus view on the technique of ambulatory blood pressure monitoring. The fourth international consensus conference on 24-hour ambulatory blood pressure monitoring. Hypertension. 1995;26:912-8.
- Wenning GK, et al. The movement disorder society criteria for the diagnosis of multiple system atrophy. Mov Disord. 2022;37:1131-48.
- Miyamoto M, et al. The correlation between CVR-R and carotid atherosclerosis in type 2 diabetes mellitus patients with diabetic neuropathy. J Physiol Anthropol. 2010;29:149-52.
- Lalanza JF, et al. Methods for heart rate variability biofeedback (HRVB): a systematic review and guidelines. Appl Psychophysiol Biofeedback. 2023;48:275-97.
- Ohshima Y, et al. Variation of respiratory and pulse events in multiple system atrophy. Parkinsonism Relat Disord. 2023;115:105817.
- Tsementzis SA, Hitchcock ER. The spoon test: a simple bedside test for assessing sudomotor autonomic failure. J Neurol Neurosurg Psychiatry. 1985;48:378-80.
- Khurana RK, Russell C. The spoon test: a valid and reliable bedside test to assess sudomotor function. Clin Auton Res. 2017;27:91-5.
- Shindo K, et al. Sympathetic sudomotor and vasoconstrictive neural function in patients with Parkinson's disease. Parkinsonism Relat Disord. 2008;14:548-52.
- Djaldetti R, Melamed E, Gadoth N. Abnormal skin wrinkling in the less affected side in hemiparkinsonism-a possible test for sympathetic dysfunction in Parkinson's disease. Biomed Pharmacother. 2001;55:475-8.
- Van Barneveld S, van der Palen J, van Putten MJ. Evaluation of the finger wrinkling test: a pilot study. Clin Auton Res. 2010;20:249-53.
- Coyne KS, et al. The impact of urinary urgency and frequency on health-related quality of life in overactive bladder: results from a national community survey. Value Health. 2004;7:455-63.
- Lukacz ES, et al. Urinary frequency in community-dwelling women: what is normal? Am J Obstet Gynecol. 2009;200:552.
- Tikkinen KA, et al. Auvinen A. Nocturia frequency, bother, and quality of life: how often is too often? A population-based study in Finland. Eur Urol. 2010;57:488-96.
- Panicker JN, et al. European Academy of Neurology (EAN)/European Federation of Autonomic Societies (EFAS)/International Neuro-Urology Society (INUS) Guidelines for practising neurologists on the assessment and treatment of neurogenic urinary and sexual symptoms (NEUROGED Guidelines). Eur J Neurol. 2025;32:e70119.
- Selius BA, Subedi R. Urinary retention in adults: diagnosis and initial management. Am Fam Physician. 2008;77:643-50.
- Prentice DM, et al. Discrepancies in measuring bladder volumes with bedside ultrasound and bladder scanning in the intensive care unit: A pilot study. J Intensive Care Soc. 2018;19(2):122-6.
- Agency for Clinical Innovation. Using a bladder scanner for adult patients: Clinician toolkit [Internet]. Chatswood: ACI; 2025 May [cited 2026 Jul 20]. Available from: https://aci.health.nsw.gov.au/__data/assets/pdf_file/0019/191062/ACI-Bladder-scanner-clinician-toolkit.pdf
- Lilium Otsuka Co., Ltd. Lilium α-200 [Internet]. Tokushima: Lilium Otsuka Co., Ltd.; [n.d.] [cited 2026 Jul 20]. Available from: https://www.lilium-otsuka.co.jp/product/alpha-200/
- Drossman DA. Functional gastrointestinal disorders: what's new for Rome IV?. Lancet Gastroenterol Hepatol. 2016;1:6-8.
- Bharucha AE, Lacy BE. Mechanisms, Evaluation, and Management of Chronic Constipation. Gastroenterology. 2020;158:1232-49.
- Goetz CG, et al. Movement Disorder Society-sponsored revision of the Unified Parkinson's Disease Rating Scale (MDS-UPDRS): scale presentation and clinimetric testing results. Mov Disord. 2008;23:2129-70.
- Lewis SJ, Heaton KW. Stool form scale as a useful guide to intestinal transit time. Scand J Gastroenterol. 1997;32:920-4.
- Matsumoto M, et al. Expert consensus document: diagnosis for chronic constipation with faecal retention in the rectum using ultrasonography. Diagnostics (Basel). 2022;12:300.
- Tanaka S, et al. Fecal distribution changes using colorectal ultrasonography in older people with physical and cognitive impairment living in long-term care facilities: a longitudinal observational study. Healthcare (Basel). 2018;6:55.
- Miki Y, et al. Identification of multiple system atrophy mimicking Parkinson's disease or progressive supranuclear palsy. Brain. 2021;144:1138-51.
- Cao B, et al. The cold hand sign in multiple system atrophy: frequency-associated factors and its impact on survival. Front Aging Neurosci. 2021;13:767211.
- Asahina M, et al. Skin temperature of the hand in multiple system atrophy and Parkinson's disease. Parkinsonism Relat Disord. 2013;19:560-2.
- Augustis S, Saferis V, Jost WH. Autonomic disturbances including impaired hand thermoregulation in multiple system atrophy and Parkinson's disease. J Neural Transm (Vienna). 2017;124:965-72.
- Shibata M, et al. Cardiac parasympathetic dysfunction concurrent with cardiac sympathetic denervation in Parkinson's disease. J Neurol Sci. 2009;276:79-83.
- Sakakibara R, et al. Bladder dysfunction as the initial presentation of multiple system atrophy: a prospective cohort study. Clin Auton Res. 2019;29:627-31.
- Fanciulli A, et al. Urinary retention discriminates multiple system atrophy from Parkinson's disease. Mov Disord. 2019;34:1926-8.
- Camacho M, et al. Early constipation predicts faster dementia onset in Parkinson's disease. NPJ Parkinsons Dis. 2021;7:45.
- Dupriez F, et al. Point-of-care ultrasound diagnostic accuracy for fecal impaction in the emergency department: a prospective study. Intern Emerg Med. 2025. Advance online publication.
- Bartels K, Esper SA, Thiele RH. Blood pressure monitoring for the anesthesiologist: a practical review. Anesth Analg. 2016;122:1866-79.
- Oyake K, et al. Comparison of the sit-up test and head-up tilt test for assessing blood pressure and hemodynamic responses in healthy young individuals. Blood Press Monit. 2022;27:79-86.
Reprints and Permissions
This article has been published
Video Coming Soon