This study elaborately describes a modeling method for cervical spondylosis in rats and an acupotomy intervention strategy, providing a visualized operational protocol for relevant research.
Method Article
Acupotomy for Cervical Spondylosis in Rats: A Visualized Protocol for Model Establishment and Intervention
* These authors contributed equally
In This Article
Summary
Abstract
Cervical spondylosis (CS) is a chronic degenerative disease. Degenerative changes in the intervertebral discs of the cervical spine, along with subsequent pathological alterations, affect surrounding tissues and structures, leading to clinical manifestations such as neck pain, stiffness, limited mobility, and occasionally numbness and radiating symptoms in the upper limbs. Among these, nerve root compression is the most common. Therefore, this study established a rat model of CS induced by cervical nerve root compression. Acupotomy therapy has shown potential in clinical CS treatment by releasing local soft tissue adhesions and alleviating nerve compression. However, there is currently a lack of visualized procedural protocols in animal experiments. This study provides a detailed description of a reliable method for establishing a rat model of CS and the corresponding acupotomy intervention protocol. In this procedure, we elaborate on the model induction process, the steps of acupotomy manipulation, therapeutic localization, rat restraint techniques, and critical precautions. Additionally, this study used electromyography (EMG) to confirm the successful establishment of the CS model and evaluated the intervention through mechanical withdrawal thresholds, gait analysis, and nerve root histopathology. This research not only provides a reference for the establishment of the CS rat model and acupotomy intervention but also offers a systematic and feasible experimental framework for future studies investigating the mechanisms of action.
Introduction
Cervical spondylosis (CS) is a common degenerative spinal disease. Its core pathological process originates from the degeneration of intervertebral discs, which further triggers a series of secondary pathological changes, including intervertebral space stenosis, osteophyte formation, and ligament hypertrophy1,2. These pathological alterations result in a variety of clinical symptoms, such as soreness and pain in the neck and shoulders, and radiating numbness in the upper extremities. In severe cases, neurological impairments may occur, including motor dysfunction and even tetraplegia2,3. Notably, the incidence of cervical spondylosis has gradually increased in recent years, with a progressively younger onset age, imposing a substantial socioeconomic burden4. Degeneration of the cervical intervertebral discs and osteophytic proliferation may involve the adjacent bony and soft-tissue structures, resulting in stenosis of the cervical spinal canal or intervertebral foramina and consequent compression of nearby structures, including cervical nerve roots, the spinal cord, and the vertebral arteries1,2,3,4. Among these, compression of the cervical nerve roots is the most frequent, accounting for approximately 60%–70% of all cases of CS5,6,7. Although multiple therapeutic approaches are available in clinical practice, including physical therapy, pharmacological intervention, and surgery, non-surgical treatments have become the preferred option for most patients due to the high cost, substantial trauma, and uncertain postoperative outcomes of surgical procedures4. In contemporary medical practice, nonsteroidal anti-inflammatory drugs and neurotrophic agents are commonly employed. Although these medications can relieve pain and delay disease progression to a certain extent, they are accompanied by adverse reactions such as digestive system injury and renal damage8,9.
Acupotomy therapy is a characteristic therapeutic modality developed on the basis of traditional Chinese acupuncture theories combined with modern minimally invasive surgical techniques. It exerts effects by dissecting and releasing soft tissue adhesions, regulating local inflammatory factors, and improving regional microcirculation10,11,12. In recent years, the clinical efficacy of acupotomy for cervical spondylosis has been widely recognized, showing promising potential in alleviating nerve compression, relieving pain, and improving cervical motor function13,14. Nevertheless, when applied in animal experiments, acupotomy interventions face challenges such as imprecise localization and difficulty in controlling the depth of manipulation. Meanwhile, to translate these clinical observations into robust evidence-based conclusions, the establishment of stable and reproducible animal models is an essential prerequisite. The intravertebral nylon suture method induces direct mechanical compression by inserting nylon sutures into the intervertebral foramen, thereby precisely mimicking the pathophysiological process of clinical nerve root compression15. This modeling approach also offers advantages, such as a short modeling cycle and controllable compression segments15. However, its surgical procedure largely relies on personal experience, and detailed, visualized operational descriptions are currently lacking.
This study presents a complete, detailed, and visualized experimental protocol covering the establishment of a rat model of cervical spondylosis and the entire procedure of acupotomy intervention. Since anesthetic agents may affect the measurement of mechanical withdrawal threshold and consequently interfere with experimental results16,17,18,19, a dedicated rat restraint device was adopted in this study. This article provides a detailed description of the rat model induction process, the stepwise acupotomy manipulation, the precise localization of treatment sites, the methods for rat restraint and fixation, and other key experimental precautions. Multiple evaluation dimensions were adopted, including mechanical withdrawal threshold measurement, electrophysiological recordings, gait analysis, and nerve root histopathological observation. This study aims to provide a visualized protocol for model induction and acupotomy intervention in a rat model of cervical spondylosis, thereby furnishing methodological support for mechanistic investigations and the evaluation of the efficacy of acupotomy therapy in the treatment of CS.
Protocol
All experimental procedures were reviewed, approved, and stringently monitored by the Laboratory Animal Ethics Committee of Beijing MDKN Biotech Company (Approval ID: MDKN-2025-096). All protocols were conducted in strict accordance with the Guide for the Care and Use of Laboratory Animals issued by the National Institutes of Health (NIH). The reagents and equipment employed in this study are listed in the Table of Materials.
1. Experimental animals and groups
- Select adult male Sprague–Dawley (SD) rats weighing 230.0 g ± 20 g for inclusion in the experiment.
- House the animals in a dedicated laboratory animal facility.
- Maintain the ambient temperature at 24 °C ± 2 °C and relative humidity at 50%–60%, under a 12 h light/dark cycle. Provide ad libitum access to standard chow and water throughout the study.
- After a 7-day acclimatization period, randomly assign 24 rats into four groups (n = 6 per group): the normal control (Control) group, the sham-operated (Sham) group, the CS model (Model) group, and the acupotomy group. The timeline of the experimental design is illustrated in Figure 1.
2. Establishment of the CS model
NOTE: Withhold food and water from all rats for 12 h prior to modeling. Weigh and record body weight. Sterilize all surgical instruments by high-pressure steam autoclaving (Figure 2A).
- Prepare nylon thread 1 day before surgery by cutting it into segments with a diameter of 0.5 mm and a length of approximately 1 cm. Immerse the filaments in 75% ethanol for 4 h, dry them under sterile conditions, and then soak them in 0.1% poly-L-lysine solution for 8 h to enhance tissue adhesiveness.
- Place the rat in an induction chamber. Induce anesthesia with 4% isoflurane, then maintain anesthesia at 1.5%–2.0% isoflurane via a face mask. Secure the animal in the prone position (following institutionally approved protocols).
- Shave the dorsal cervical region to fully expose the surgical field. Disinfect the surgical area three times with povidone iodine from inside to outside, and repeat the disinfection procedure with 75% ethanol.
- Palpate and mark the highest spinous process (T2) on the rat's dorsum. Make a midline dorsal skin incision of approximately 3 cm, extending cranially from the peak of the T2 spinous process. Bluntly dissect the subcutaneous tissue and posterior cervical musculature (Figure 2B).
- Fully expose the left vertebral arch from C5 to T1, and thoroughly scrape off the overlying muscular and connective tissues (Figure 2C).
- Gently dissect the ligamentum flavum and connective tissues at the C6–C7 and C7–T1 intervertebral spaces using microforceps. Open the left vertebral arch of C7 with mosquito forceps to expose the spinal cord.
- Retract the spinal cord gently toward the right side using an ophthalmic nerve dissector. Position the sterilized nylon thread beneath the C6–C7 and C7–T1 nerve roots along the longitudinal axis of the spinal cord with microsurgical forceps; avoid excessive compression to prevent vertebral venous injury.
NOTE: Expose the spinal cord at the identical anatomical site in the sham group without inserting the nylon thread. - Close and suture the incision layer by layer upon completion of the procedure.
- Transfer rats to a thermostatically controlled heating pad maintained at 37 °C, and monitor vital signs until full consciousness recovery.
- Administer an intramuscular injection of 50,000 units of penicillin sodium solution into the hind limb for postoperative anti-infection prophylaxis. Return animals to their home cages for postoperative recovery.
3. Restraint procedure
- Secure the rat in a black restraint mesh sleeve.
- Fasten two nylon cable ties onto a plastic frame. Fasten the upper cable tie at the axillary region and the lower cable tie around the pelvic region (Figure 3B).
NOTE: Use a plastic plate measuring 200 mm × 300 mm × 5 mm, perforated with 20 mm × 4 mm slots spaced at 10 mm intervals along the long edges and 3 mm intervals along the short edges, and equipped with five supporting feet located at the center and four corners (Figure 3A). - After model induction, repeat the above restraint procedure for each rat in all groups for three consecutive days to ensure adequate habituation. Maintain each restraint session for a minimum of 5 min per day.
4. Acupotomy treatment
- Initiate acupotomy intervention on the 4th day following model establishment.
- Prepare disposable sterile acupotomy needles (diameter: 0.40 mm; length: 40 mm).
- Remove the fur over the cervical region to fully expose the operative field.
- Palpate the soft tissues on both sides of the cervical spinous processes to identify indurated nodules or cord‑like structures. Determine one spinous process point at C6 or C7, and then locate two additional points approximately 0.5 cm lateral to each side of this spinous process.
- Designate these three sites as the acupotomy insertion points and mark them (Figure 3C).
- Disinfect the marked insertion sites with medical povidone iodine followed by 75% medicinal ethanol.
- Orient the cutting edge of the acupotomy parallel to the posterior midline and maintain the needle shaft perpendicular to the posterior cervical coronal plane during insertion.
- Apply gentle compression over the insertion site with the left thumb, while holding the acupotomy steadily between the right thumb and index finger. Penetrate rapidly through the subcutaneous tissue in a perpendicular direction, then advance the needle slowly until reaching the bony surface.
- Perform localized longitudinal cutting three times and transverse soft tissue release twice within the lesioned area, while restricting the operative range within 1 mm. Withdraw the needle upon completion of the manipulation (Figure 3D).
- Apply firm pressure to the insertion site for 3 min to achieve hemostasis. Administer the acupotomy intervention once every 5 days, for a total of three sessions.
NOTE: Except for the acupotomy group, the other three groups do not receive any therapeutic intervention. However, the animals in these groups are immobilized in the same manner and for the same duration as those in the acupotomy group.
5. Mechanical withdrawal threshold (MWT) test
NOTE: Conduct the measurement on the day before model establishment surgery, the 3rd day, and the 14th day after surgery, using a plantar mechanical pain stimulator for rats and mice.
- Place each rat into a transparent testing chamber positioned on a metal mesh floor in a quiet environment maintained at 24 °C ± 2 °C.
- Allow the rat to acclimate inside the chamber for at least 5 min, or until exploratory and grooming behaviors have largely subsided.
- Position the tip of the von Frey filament perpendicularly to the plantar surface of the left forepaw, between the third and fourth metacarpals. Apply the stimulus from below through the metal mesh until a brisk paw withdrawal, licking, or shaking response is elicited.
- Record the displayed value at the moment of withdrawal as the mechanical pain threshold.
- After testing each rat, thoroughly wipe the metal mesh floor and inner walls of the chamber with 75% medical alcohol, then dry with clean gauze to eliminate residual odors that may influence subsequent behavioral tests. Introduce the next rat only after the apparatus has completely dried.
NOTE: Test all rats sequentially in a rotating order for three rounds. Maintain an interval of at least 10 min between two successive MWT measurements in the same rat. Use the mean of the three measurements as the final MWT value for each rat.
6. Electromyography (EMG) recording
NOTE: Perform resting-state EMG on Day 3 after model establishment using a biological signal acquisition and analysis system.
- Anesthetize the rat by isoflurane inhalation (induction concentration 3%–4%, maintenance concentration 1.5%–2.0%). Secure the animal in the prone position on the experimental platform and fully expose the left forelimb.
- Connect the lead wires of the recording electrodes to the designated acquisition channels. Launch the acquisition software, select the EMG signal mode, and set the sampling frequency to 20 kHz with a band-pass filter range of 15 Hz–5 kHz.
- Disinfect the muscles of the left forelimb (flexor carpi radialis, flexor carpi ulnaris, biceps brachii, and triceps brachii) using degreased cotton balls soaked in 75% medical ethanol.
- Insert the needle recording electrode perpendicularly into the muscle belly, oriented orthogonally to the direction of the muscle fibers. Insert a second needle electrode 3–5 mm away as the reference electrode, and insert the ground electrode into the base of the tail.
- Observe insertional activity immediately after needle insertion. Once insertional potentials have disappeared and the muscle is fully relaxed, record the resting EMG signal for 1 min for each rat.
NOTE: Maintain a quiet environment throughout recording and minimize external electromagnetic interference. Common interferences include power-frequency interference from alternating current and high-frequency noise from other laboratory equipment, which manifests as regular sine waves superimposed on electromyograms. These interferences can be reduced through grounding, filter settings, and environmental management. - Withdraw all needle electrodes carefully and return the rat to its home cage, allowing it to recover spontaneously from anesthesia.
- After completing EMG recording for each rat, clean the needle electrodes with 75% medical ethanol using degreased cotton balls and dry them thoroughly with sterile gauze to prevent cross-contamination.
7. Gait analysis in rats
NOTE: Perform gait analysis on the first day after completion of acupotomy intervention (postoperative Day 15 after model surgery). The gait analysis system consists of a treadmill equipped with a transparent belt, a high-speed digital camera positioned beneath the belt, and a computer workstation.
- Place the rat on the treadmill track and allow it to acclimate freely for 3 min.
- Activate the treadmill belt and gradually increase the speed from 5.0 cm/s until the rat exhibits a stable gait without exploratory behavior.
- Acquire a 10 s ventral (bottom-view) walking video of the rat using the high-speed camera.
- After completion of testing for each rat, thoroughly wipe the treadmill belt and testing chamber with 75% ethanol to eliminate residual odors that may affect subsequent behavioral assessments. Allow the belt to dry completely before introducing the next rat.
- Import the recorded videos into the analysis software. Use the software to identify the paw placement of each limb and extract a series of gait parameters.
- Upon completion of automated analysis, export the gait parameter data for subsequent statistical analysis.
- Include the following gait parameters in the present study: average printed area of the left front paw (the average of the size of the foot print over the entire stance), maximum stance area of the left front paw (the maximum size of the foot print over the entire stance), and stance pressure of the left front paw (reflecting the relative intensity of paw pressure during the stance phase as recorded by the gait analysis system).
NOTE: Acquire three valid gait sequences for each rat and use the mean of the three measurements for analysis.
8. HE staining of the nerve root tissues
NOTE: After the behavioral tests on postoperative Day 15 after model surgery, collect nerve root tissue samples for HE staining.
- Anesthetize rats by intraperitoneal injection of 2% sodium pentobarbital (0.3 mL/100 g), and perform transcardial perfusion with paraformaldehyde.
- Dissect the C6–T1 spinal nerve roots and immerse the tissue in 4% paraformaldehyde at 4 °C for post-fixation for 48 h.
CAUTION: Handle paraformaldehyde as an irritant in a well-ventilated environment or chemical fume hood. - Rinse the fixed nerve root tissue under running tap water for 1 h to remove residual fixative.
- Subject the tissue to graded ethanol dehydration, clear sequentially in xylene (I) and xylene (II), embed in paraffin, and section at a thickness of 3–5 µm. Bake the sections at 65 °C.
- Dewax the sections sequentially in xylene (I) and xylene (II), 8 min each. Rehydrate the sections through a graded ethanol series (100% for 15 min, 95% for 5 min, 80% for 5 min, 70% for 3 min), then immerse in distilled water for 2 min.
- Stain the sections with hematoxylin solution for 5 s, then rinse in running water for 2 min to remove excess stain.
- Differentiate the sections in distilled water for 30 s. Immerse the sections in 70% ethanol for 10 s, followed by 80% ethanol for 10 s.
- Stain the sections with eosin solution for 4 min, then rinse under running water to remove superficial stain. Dehydrate the sections through graded ethanol (70% for 10 s, 80% for 10 s, 95% for 10 s, 100% for 160 s), clear in xylene for 4 min.
- Mount the slides with neutral resin.
- Examine the pathological and morphological alterations of the spinal nerve root tissue under a light microscope at 400× magnification, and acquire microscopic images from representative target fields.
9. Statistical analysis
- Perform statistical analyses using SPSS software. Express continuous variables that conform to a normal distribution as mean ± standard deviation.
- Under the assumptions of normality and homogeneity of variance, analyze mechanical withdrawal thresholds using repeated-measures analysis of variance, and analyze gait parameters using one-way ANOVA. Conduct post hoc pairwise comparisons between groups using the Least Significant Difference (LSD) test.
- Apply nonparametric tests if the assumptions of normal distribution or homogeneity of variance are not satisfied.
- Consider differences to be statistically significant at p < 0.05.
Results
Mechanical withdrawal threshold (MWT) assessments demonstrated comparable baseline values across all groups prior to model induction. On the 3rd day after modeling and sham operation, no significant difference was observed between the sham group and the control group (p > 0.05). In contrast, both the model and acupotomy groups exhibited a marked reduction in MWT relative to the sham group (p < 0.01, Figure 4). Upon completion of treatment, the acupotomy group showed a significant elevation in MWT compared with the model group (p < 0.05, Figure 4).
Electromyography (EMG) recordings revealed that on the 3rd day after modeling and sham operation, abnormal spontaneous activities such as fibrillation potentials and positive sharp waves were detectable at rest in needle EMG of both the model and acupotomy groups. In contrast, no abnormal spontaneous discharges were observed in the resting needle EMG traces of the control or sham groups (Figure 5). If no abnormal spontaneous potentials are present in the affected side, it suggests that the model may not have successfully damaged the target nerve root, and the surgical procedure needs to be rechecked.
Gait analysis revealed that, following completion of treatment, the average print area, maximum stance area, and stance pressure in the sham group did not differ significantly from those in the control group (p > 0.05). In contrast, all gait parameters were markedly reduced in the model group compared with the sham group (p < 0.001). Relative to the model group, the acupotomy group exhibited significant elevations in each of these gait indices (p < 0.05, Figure 6). The average print area is the average of the size of the footprint over the entire stance. The maximum stance area is the maximum size of the footprint over the entire stance. The standing pressure reflects the relative intensity of paw pressure during the stance phase as recorded by the gait analysis system.
HE staining of cervical nerve root tissue demonstrated that, in the control and sham groups, the morphology of the nerve root tissue appeared essentially normal. Nerve fibers and neuronal cell bodies were arranged in a relatively orderly and compact fashion, with well-defined structural boundaries and no evident interstitial edema. In contrast to the sham group, the model group exhibited pronounced pathological alterations indicative of nerve root injury, characterized by disorganized, loose arrangements of nerve fibers and cell bodies, rupture and deformation of a subset of neuronal cells, partial fiber fragmentation, and marked interstitial edema. Relative to the model group, acupotomy treatment markedly ameliorated these pathological lesions, as evidenced by a more regular alignment of nerve fibers and cell bodies, attenuation of interstitial edema, and partial restoration of the structural integrity of the neural tissue (Figure 7).
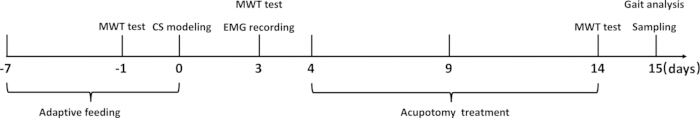
Figure 1: Time axis diagram of experimental design. After a 7-day adaptive feeding period, CS models were established in both the model group and the acupotomy group of rats. The sham group was exposed to the same spinal cord region as the model group, but without the placement of the fish line. Acupotomy intervention began on the 4th day after successful modeling in the acupotomy group. Mechanical pain thresholds of the rats were measured on the day before modeling, on postoperative day 3, and at the end of intervention on postoperative day 14. Electromyography assessment was performed on postoperative day 3 to evaluate nerve root compression. Gait analysis was performed on postoperative day 15 after the intervention to evaluate the motor coordination function of rats. The detection samples were collected after the behavioral tests on postoperative day 15. Please click here to view a larger version of this figure.
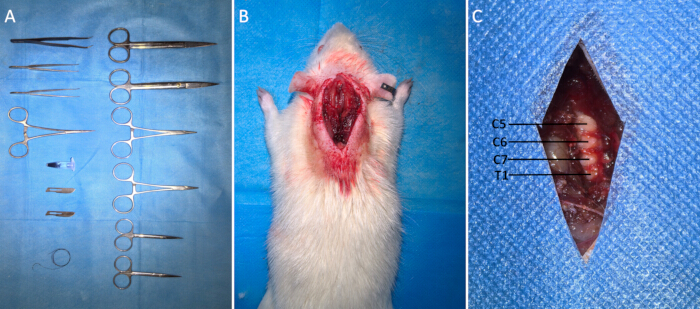
Figure 2: Establishment of the CS rat model. (A) Surgical instruments used for model induction. (B) Dorsal cervical incision and tissue dissection. (C) Left C5–T1 cervical vertebral laminae. Please click here to view a larger version of this figure.
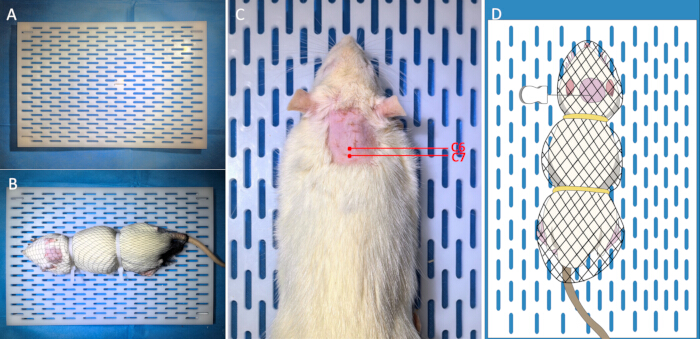
Figure 3: Procedure of acupotomy intervention. (A) Plastic board used for rat restraint. (B) Schematic illustration of rat restraint. (C) Anatomical surface landmarks corresponding to the C6 and C7 spinous processes in rats. (D) Schematic representation of acupotomy treatment in rats. Please click here to view a larger version of this figure.
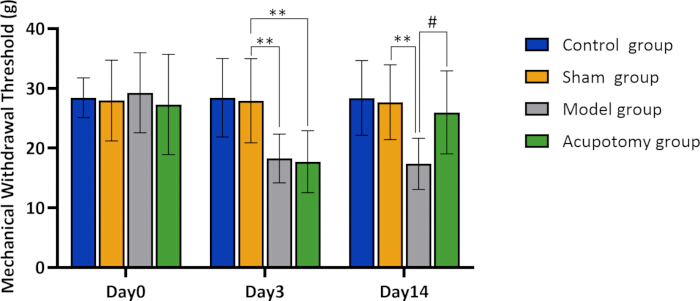
Figure 4: Comparison of mechanical withdrawal threshold among the four experimental rat groups (n = 6 per group). **p < 0.01 versus the sham operation group; #p < 0.05 versus the model group. Please click here to view a larger version of this figure.
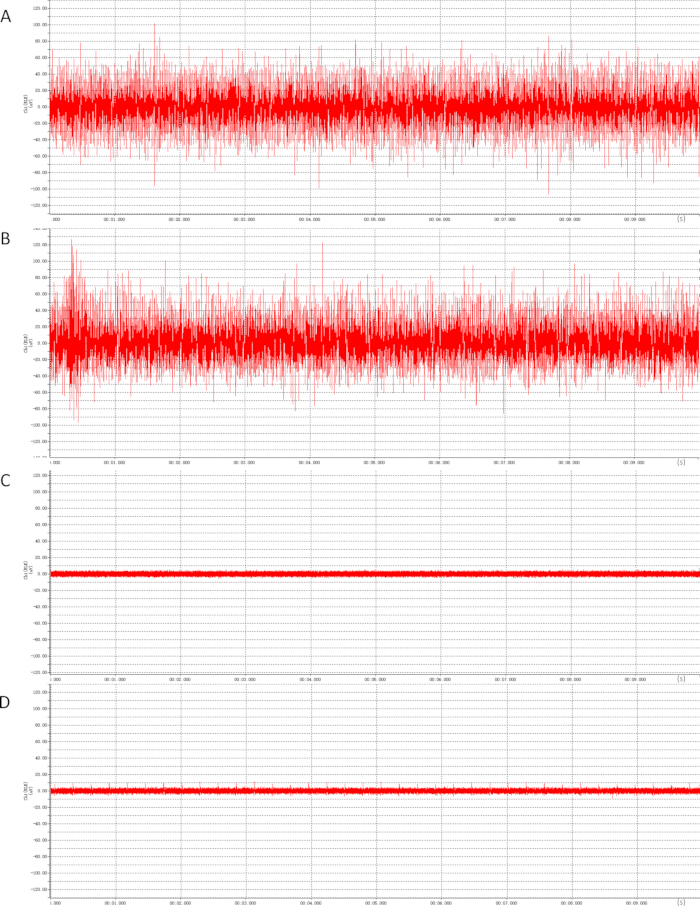
Figure 5: Resting-state forelimb electromyograms in the four experimental groups following model induction. (A) Electromyogram of the forelimb in the model group. (B) Electromyogram of the forelimb in the acupotomy group. (C) Electromyogram of the forelimb in the control group. (D) Electromyogram of the forelimb in the sham group. Please click here to view a larger version of this figure.
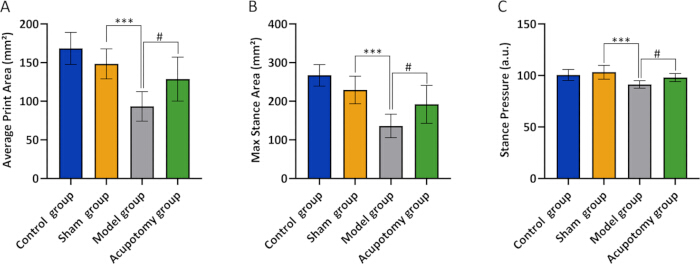
Figure 6: Comparison of gait parameters among the four experimental rat groups (n = 6 per group). (A) Comparison of average print area. (B) Comparison of maximum stance area. (C) Comparison of stance pressure. ***p < 0.001 versus the sham operation group; #p < 0.05 versus the model group. Please click here to view a larger version of this figure.
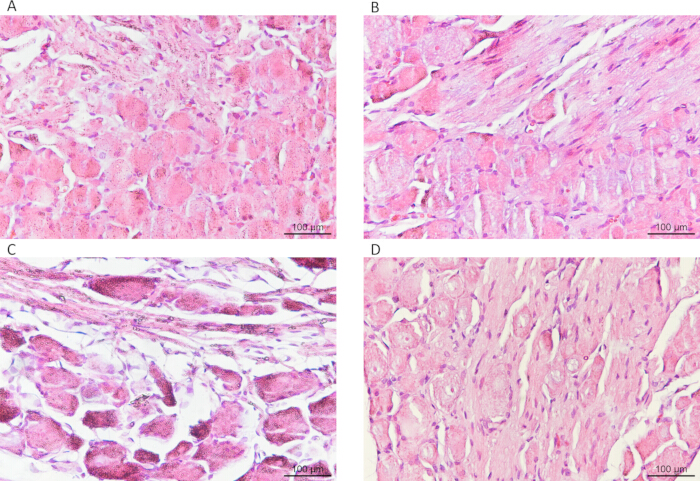
Figure 7: HE staining of nerve root tissue from the four experimental rat groups at 400× magnification. (A) HE staining of the control group. (B) HE staining of the sham group. (C) HE staining of the model group. (D) HE staining of the acupotomy group. Scale bar = 100 µm. Please click here to view a larger version of this figure.
Discussion
The selection of an appropriate animal model is a prerequisite for elucidating the pathogenesis of cervical spondylosis (CS) and for rigorously evaluating therapeutic interventions. Currently, the intravertebral nylon suture method is widely adopted due to its advantages of relative simplicity, short modeling cycle, and high reproducibility and reliability15,20. In this approach, a compressive material is implanted into the rat spinal canal to exert continuous compression on the cervical spinal nerve roots, thereby recapitulating the pathological condition of nerve root impingement caused by intervertebral disc herniation or osteophytic hyperplasia in clinical settings. Among the secondary injuries associated with cervical spondylosis, nerve root compression is the most common and constitutes a principal cause of pronounced clinical manifestations, typically presenting as neck pain, stiffness, and radiating symptoms in the upper limbs5,7,21. Accordingly, this study adopted the intravertebral nylon suture method to establish a rat model of CS and provided a visualized operational protocol for model establishment and acupotomy intervention in rats with CS.
Following compression of the nerve root, local ischemia, inflammatory responses, and mechanical irritation may induce both peripheral and central sensitization, ultimately leading to hyperalgesia22,23,24,25,26. The present findings demonstrated a marked reduction in the mechanical pain threshold of the ipsilateral forepaw in rats after model induction, indicating that the procedure successfully evoked mechanical hyperalgesia. In rats receiving acupotomy intervention, the mechanical withdrawal threshold was significantly restored, suggesting that acupotomy release effectively attenuates the state of pain sensitization. Pain not only affects sensory thresholds but also alters the spontaneous movement patterns of animals. Gait analysis systems, by capturing spatiotemporal parameters of paw prints during locomotion, provide an objective quantification of pain-induced compensatory gait alterations, thereby overcoming the pronounced subjectivity inherent in traditional behavioral scoring methods27. In this study, rats in the model group exhibited reduced average print area, maximum stance area, and stance pressure of the ipsilateral forepaw, reflecting load-avoidance behavior and protective gait changes secondary to pain. In contrast, rats subjected to acupotomy intervention showed a normalization tendency in these gait parameters, indicating that acupotomy treatment, while alleviating pain, also improves locomotor coordination. Histomorphological observations further revealed intergroup differences in the arrangement and morphology of nerve fibers and neuronal cell bodies within the nerve root, as well as in the degree of interstitial edema. These findings suggest that acupotomy therapy may attenuate pathological alterations of the nerve root.
Compression of the nerve root not only induces disturbances in sensory conduction but may also result in denervation or aberrant hyperexcitability of the innervated musculature. Electromyography (EMG) at rest, by recording spontaneous electrical activity (such as fibrillation potentials and positive sharp waves) in a fully relaxed muscle, provides a sensitive indicator of abnormal sarcolemmal excitability secondary to neurogenic injury and constitutes a pivotal electrophysiological modality for evaluating radiculopathies in both clinical and experimental settings28,29,30. Under physiological conditions, a completely relaxed muscle exhibits electrical silence, with an absence of spontaneous discharges. In this study, pronounced spontaneous discharges were detected in the resting muscles of the ipsilateral forelimb in rats following model induction. Such abnormal resting EMG activity is a characteristic manifestation of neurogenic damage and suggests that the cervical nerve roots of these rats may be subjected to sustained compression31. The abnormal EMG findings in the model and acupotomy groups after modeling further confirmed the successful establishment of the CS rat model from an electrophysiological perspective.
To avoid confounding behavioral assessments with the cumulative effects of repeated anesthesia, acupotomy intervention in this study was performed using a restraint apparatus in awake animals32. Previous reports have demonstrated that adequate habituation training and repeated exposure can markedly attenuate restraint-induced stress responses33,34,35,36. This suggests that the habituation training before intervention in this protocol can effectively minimize the interference of acute restraint stress on experimental indicators.
This study is not without limitations. First, the intravertebral nylon suture method primarily reproduces acute or subacute mechanical compression, whereas human CS typically follows a chronic degenerative course. Second, although the present restraint protocol was designed to minimize stress, future investigations should assess stress-related biomarkers, such as serum cortisol, to more comprehensively evaluate the impact of the restraint apparatus.
In conclusion, this study provides a detailed operational procedure for establishing a rat model of CS and subsequently treating it with acupotomy. The results indicate that acupotomy release significantly elevates mechanical pain thresholds, ameliorates pain-avoidant gait patterns, and attenuates pathological alterations of the nerve root. This work thus provides a systematic and practical experimental framework for elucidating the mechanisms underlying acupotomy therapy for the treatment of CS.
Disclosures
All authors have declared no potential conflicts of interest.
Acknowledgements
This study was supported by the National Key Research and Development Program of China (Grant No. 2023YFC3502703) and the Key Project of the Hubei Provincial Natural Science Foundation Innovation and Development Joint Fund (Grant No. 2024AFD271).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.5 mL syringe | Hebei Yunsheng Biotechnology Co., Ltd | SN-04442 | |
| 1 mL syringe | Shanghai Zhiyu Medical Equipment Co., LTD | ZSQ-1 | |
| 4-0 Suture with Needle, Single-armed (4×12) | GLASS | JZZSX193 | |
| 75% alcohol | Shandong Anjie Gaoke Disinfection Technology Co. LTD | 75-500ml | |
| Acupotomy Needle | Beijing Huaxia Blue Chip Biotechnology Co., Ltd. | HY0440 | |
| Adherent slide | CITOTEST | 188105 | |
| Biological Signal Acquisition and Analysis System | Techman | BL-420N | |
| Biological Signal Acquisition and Analysis System (Software) | Techman | BL-420N Version 3.0.0.237 | |
| Cover glass | Citotest Labware Manufacturing Co.,Ltd | 10212432C | |
| Dehydrator | DIAPATH | Donatello | |
| Electronic balance | Mettler-Toledo | ME203E/02 | |
| Electrothermal blast drying oven | Labotery | GEL-70 | |
| Embedding machine | Wuhan Junjie Electronics Co., Ltd | JB-P5 | |
| Environmental Friendly Dewaxing Transparent Liquid | Servicebio | G1128-1L | |
| ESD-Safe Black Stainless Steel Tweezers (Curved Tip) | solomen | ESD-15 | |
| Ethanol | SCRC | 100092683 | |
| Fat-free cotton ball | Caoxian Hualu Sanitary Material Co. LTD | TZMQ-500 | |
| Hematoxylin-eosin (HE) HD constant dye kit | Servicebio | G1076 | |
| Hemostatic Forceps | solomen | B0557 | |
| IBM SPSS Statistics | IBM Corporation | Version 22.0 | |
| Imaging system | Nikon | NIKON DS-U3 | |
| Iodophor | Shandong Anjie Gaoke Disinfection Technology Co. LTD | DF-500 | |
| Isoflurane | RWD life science | R510-22-10 | |
| Latex gloves | Beijing Ruijing Latex Products Co. LTD | RJJC-S | |
| Mechanical Paw Poking Test Device | Kew basis | KW-CT-1 | |
| Medical forceps | AIZANCHENG | AZN00008 | |
| Mosquito hemostatic forceps | Servicebio | QX1310D | |
| Neutral gum | SCRC | 10004160 | |
| Normal saline solution | SHIMEN | SLYS-500ml | |
| Ophthalmic scissors | solomen | B0754 | |
| Paraffin liquid | Macklin | 8012-95-1 | |
| Paraformaldehyde Fixative (Neutral) | Servicebio | G1101 | |
| Pathology slicer | Shanghai Leica Instrument Co., Ltd | RM2016 | |
| Penicillin G Sodium for Injection | Jilin Huamu Animal Health Product Co., Ltd. | Veterinary Drug Approval No.070011248 | |
| Poly-L-lysine solution | Shanghai Yuanye Biotechnology Co., Ltd. | R23126-50ml | |
| Rodent Clipper | solomen | B1564 | |
| Rodent Gait Imaging and Analysis System | Clever | TreadScan; BCamCapture | |
| Rodent Gait Imaging and Analysis System (Software) | Clever | TreadScan Version 4.00; BCamCapture Version 3.00 | |
| SD rats | Beijing Sibefei Biotechnology Co., Ltd | A102 | |
| Small Animal Anesthesia Machine | YuYAN | ABM | |
| Steam sterilizer (autoclave) | Yamato | SQ810C | |
| Surgical Blade | solomen | B1177 | |
| Surgical mask | winner | WJKZ-1 | |
| Surgical needle holder | solomen | B0772 | |
| Surgical scissors | GLASS | JZZSX-ZC544R | |
| Tissue spreader | Zhejiang Kehua Instrument Co., Ltd | KD-P | |
| Ultrapure Water Polishing System | Aiken water El | AK-RO-C2 | |
| Universal tissue fixative (neutral) | Servicebio | G1101-15ML | |
| Upright optical microscope | Nikon | NIKON ECLIPSE E100 | |
| Xylene | SCRC | 10023418 |
References
- Theodore N. Degenerative cervical spondylosis. N Engl J Med. 2020;383(2):159-68.
- Yeshna, Singh M, Monika, Kumar A, Garg V, Jhawat V. Pathophysiology and emerging therapeutic strategies for cervical spondylosis: the role of pro-inflammatory mediators, kinase inhibitors, and organogel-based drug delivery systems. Int Immunopharmacol. 2025;151:114350.
- Nouri A, Tetreault L, Singh A, Karadimas SK, Fehlings MG. Degenerative cervical myelopathy: epidemiology, genetics, and pathogenesis. Spine (Phila Pa 1976). 2015;40(12):E675-93.
- Lakhapate SS, Devade OA, Redasani VK. A brief review on cervical spondylosis. J Drug Deliv Ther. 2025;15(7):144-149.
- Chen B, et al. Acupotomy versus acupuncture for cervical spondylotic radiculopathy: protocol of a systematic review and meta-analysis. BMJ Open. 2019;9(8):e029052.
- Yang F, Li WX, Liu Z, Liu L. Balance chiropractic therapy for cervical spondylotic radiculopathy: study protocol for a randomized controlled trial. Trials. 2016;17(1):513.
- Woods BI, Hilibrand AS. Cervical radiculopathy: epidemiology, etiology, diagnosis, and treatment. J Spinal Disord Tech. 2015;28(5):E251-259.
- Kartha S, Weisshaar CL, Philips BH, Winkelstein BA. Pre-treatment with meloxicam prevents the spinal inflammation and oxidative stress in DRG neurons that accompany painful cervical radiculopathy. Neuroscience. 2018;388:393-404.
- Harirforoosh S, Asghar W, Jamali F. Adverse effects of nonsteroidal anti-inflammatory drugs: an update of gastrointestinal, cardiovascular and renal complications. J Pharm Pharm Sci. 2013;16(5):821-847.
- Jiang G, Wan B, Huang W, Chen L, Duan B, Wang Y. Influence of acupotomy loosing on IL-6, IL-10 and TNF-α in synovial fluid of rheumatoid arthritis patients with elbow joint stiffness. World J Acupunct Moxibustion. 2018;28(2):91-96.
- Sun J, et al. Acupotomy therapy for knee osteoarthritis pain: systematic review and meta-analysis. Evid Based Complement Alternat Med. 2020;2020:2168283.
- Hu J, Tong H, Zhang J, Jiang L. Acupotomy for musculoskeletal pain: exploring therapeutic potential and future directions. J Pain Res. 2025;18:3027-3036.
- Kwon CY, Yoon SH, Lee B. Clinical effectiveness and safety of acupotomy: an overview of systematic reviews. Complement Ther Clin Pract. 2019;36:142-152.
- Lijian Z, Zhen Z, Yuan Y, Nachuan Z. Ultrasound-guided acupotomy for cervical spondylosis: a systematic review and meta-analysis based on GRADE quality assessment. Front Pain Res (Lausanne). 2025;6:1654265.
- Shi T, et al. Acupuncture relieves cervical spondylosis radiculopathy by regulating spinal microglia activation through MAPK signaling pathway in rats. J Pain Res. 2023;16:3945-3960.
- Mogil JS. Animal models of pain: progress and challenges. Nat Rev Neurosci. 2009;10(4):283-294.
- Yamauchi M, Sekiyama H, Shimada SG, Collins JG. Halothane suppression of spinal sensory neuronal responses to noxious peripheral stimuli is mediated, in part, by both GABA(A) and glycine receptor systems. Anesthesiology. 2002;97(2):412-417.
- Li Q, Mathena RP, Eregha ON, Mintz CD. Effects of early exposure of isoflurane on chronic pain via the mammalian target of rapamycin signal pathway. Int J Mol Sci. 2019;20(20):5102.
- Boegel K, Gyulai FE, Moore KK, Gold MS. Deleterious impact of a γ-aminobutyric acid type A receptor-preferring general anesthetic when used in the presence of persistent inflammation. Anesthesiology. 2011;115(4):782-790.
- Liguo Z, Bin T, Xu W, He Y. Research progression and evaluation of an animal model of cervical radiculopathy. Chin J Tissue Eng Res. 2018;22(35):5700-5705.
- Caridi JM, Pumberger M, Hughes AP. Cervical radiculopathy: a review. HSS J. 2011;7(3):265-272.
- Liu DL, et al. Chronic cervical radiculopathic pain is associated with increased excitability and hyperpolarization-activated current (Ih) in large-diameter dorsal root ganglion neurons. Mol Pain. 2017;13:1744806917707127.
- Rothman SM, Winkelstein BA. Chemical and mechanical nerve root insults induce differential behavioral sensitivity and glial activation that are enhanced in combination. Brain Res. 2007;1181:31-43.
- Rothman SM, Huang Z, Lee KE, Weisshaar CL, Winkelstein BA. Cytokine mRNA expression in painful radiculopathy. J Pain. 2009;10(1):90-99.
- Hubbard RD, Winkelstein BA. Transient cervical nerve root compression in the rat induces bilateral forepaw allodynia and spinal glial activation: mechanical factors in painful neck injuries. Spine (Phila Pa 1976). 2005;30(17):1924-1932.
- Costigan M, Scholz J, Woolf CJ. Neuropathic pain: a maladaptive response of the nervous system to damage. Annu Rev Neurosci. 2009;32:1-32.
- Vrinten DH, Hamers FFT. "CatWalk" automated quantitative gait analysis as a novel method to assess mechanical allodynia in the rat: a comparison with von Frey testing. Pain. 2003;102(1-2):203-209.
- Gonçalves LI, Oliveira Junior PH, Baima JPS. Cervical radiculopathy for neurologists: the role of electrodiagnosis. Arq Neuropsiquiatr. 2025;83(10):s00451812893.
- Tong HC. Incremental ability of needle electromyography to detect radiculopathy in patients with radiating low back pain using different diagnostic criteria. Arch Phys Med Rehabil. 2012;93(6):990-992.
- Lee SJ, Han TR, Hyun JK, Jeon JY, Myong NH. Electromyographic findings in nucleus pulposus-induced radiculopathy in the rat. Spine (Phila Pa 1976). 2006;31(18):2053-2058.
- Fisher MA. Electrophysiology of radiculopathies. Clin Neurophysiol. 2002;113(3):317-35.
- Miller AL, Golledge HDR, Leach MC. The influence of isoflurane anaesthesia on the rat grimace scale. PLoS One. 2016;11(11):e0166652.
- Medeiros MA, Canteras NS, Suchecki D, Mello LEAM. c-fos expression induced by electroacupuncture at the Zusanli point in rats submitted to repeated immobilization. Braz J Med Biol Res. 2003;36(12):1673-1684.
- Grissom N, Kerr W, Bhatnagar S. Struggling behavior during restraint is regulated by stress experience. Behav Brain Res. 2008;191(2):219-226.
- Grissom N, Bhatnagar S. Habituation to repeated stress: get used to it. Neurobiol Learn Mem. 2009;92(2):215-224.
- Gray M, Bingham B, Viau V. A comparison of two repeated restraint stress paradigms on hypothalamic-pituitary-adrenal axis habituation, gonadal status and central neuropeptide expression in adult male rats. J Neuroendocrinol. 2010;22:92-101.