This protocol describes the procedure for mouse heart extraction and cannulation, as well as the preparation and configuration of the Langendorff retrograde perfusion system. The experimental setup is coupled with a high-resolution optical system designed to evaluate the mechanical responses of the atria and ventricles while preserving their natural dynamics.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Optical System for Assessment of Atrial and Ventricular Mechanics in Langendorff-perfused Mouse Hearts
* These authors contributed equally
In This Article
Summary
Abstract
The mouse heart serves as a widely used model in cardiovascular research, facilitated by advances in engineering technologies. However, assessment of atrial and ventricular contractility remains challenging due to the small size of the mouse heart. This study introduces a novel methodology for evaluating contractility and heart rate in an intact, isolated heart. Using a Langendorff-perfused mouse heart in combination with a high-resolution optical system enables evaluation of atrial and ventricular contractility. The experimental setup addresses challenges associated with small heart size and rapid contraction rates while acquiring high-resolution signals. Synchronization between stimulus frequency and heart contraction frequency in the range of 420 to 660 beats per minute (bpm) was consistent with results from the auxotonic method. Additionally, measurements of ventricular shortening and atrial dynamic signals allow for the determination of atrioventricular contraction. This method is suitable for assessing contractility and heart rate in an intact, isolated heart without pharmacological or systemic influences. These results demonstrate that the optical system enables measurement of ventricular and atrial shortening responses.
Introduction
There is much to discover in cardiac physiology; key processes, such as cardiac pace-making and excitation-contraction coupling, are central tenets that are continually researched1. Although the effects of biological noise on cardiac contractility2 and pace-making activity remain poorly understood1, new optical imaging methods have allowed the presentation of new paradigms3,4.
Two experimental methodologies using the Langendorff system have made invaluable contributions to measuring cardiac function. First, the isovolumic contraction method, where a signal is obtained from a small balloon inserted into the left ventricle5,6,7. Second, the auxotonic recording method, where a signal is obtained by suturing one end of a thread to the apex of the heart and the other end to a mechanical recording device to measure auxotonic contractions along the axis of the heart2,8. Nevertheless, evaluating atrial and ventricular contractility in the mouse heart is challenging due to its diminutive size. Furthermore, preparation requires a certain degree of gentleness, since the heart is susceptible to injury9,10,11,12,13.
The optical system for assessing the mechanical dynamics of mouse hearts has several novel features and advantages. First, this method is suitable for assessing contractility and heart rate in an intact, isolated heart in the absence of pharmacological or systemic influences. The protocol could also be effectively employed in experiments assessing ischemia-reperfusion injury when looking into pharmacological, cell-regeneration, or oxygen-therapy-based treatments.
In this paper, we present a protocol for recording biophysical parameters of mouse heart contractile function using a high-resolution optical system. This method helps assess contractility and heart rate in an intact, isolated heart. Furthermore, it permits evaluation of atrial and ventricular contractility. The Langendorff mouse heart preparation presents a refinement that includes a slight modification to minimize loss of perfusate temperature and motion artifacts without inhibiting muscle contractions.
Access restricted. Please log in or start a trial to view this content.
Protocol
All animal procedures were conducted in accordance with Federal Regulations for Animal Experimentation and Care and were approved by the Animal Care Committee of CINVESTAV (CINVESTAV Zacatenco, D.F., Mexico). In this study, C57BL/6J male mice are used, weighing 28–34 g, and aged 8–14 weeks. All materials and equipment used in the protocol are listed in the Table of Materials. Supplementary Files 1–11 provide supporting diagrams, software guides, analysis programs, pacing data, and application files for the protocol.
1. Stock preparation
- Prepare two stock solutions in advance and store them in a refrigerator at 4 °C: (1) Stock I, 1 L (in deionized water; in g/L: 76.13 NaCl, 4.02 KCl, 1 MgCl2(6H2O), 0.4 NaH2PO4) and (2) Stock II, 0.1 L (in deionized water; in g/L: 73.5 CaCl2(2H2O)).
NOTE: The solutions may be used for up to 30 days after preparation. Store them at 4 °C.
2. Langendorff system connection and cleanup
- Connect the reservoir (1), reservoir thermal bath (2), perfusion pump (3), serpentine (4), serpentine recirculator (5), monitoring system (6), and drainage system (8), as shown in Figure 1A.
NOTE: The connection between the monitoring system and the drainage system is shown in greater detail in Supplementary File 1. - Fill the Langendorff system with 1 L of deionized water at 50 °C, then start the perfusion and drainage pumps (Supplementary File 1, drainage system). After approximately 20–30 min, remove the liquid from the system, then proceed to the next step.
NOTE: Verify that there are no leaks or pressure drops in the system. If this occurs, do not proceed with the experiment. - Fill the system with 1 L of 1% acetic acid (dissolved in deionized water), then turn off the perfusion and drainage pumps and wait for 60 min, then turn on the pumps to remove the liquid.
- Repeat step 2.2 twice.
- Fill the system with 70% ethanol (dissolved in deionized water) to prevent adhesion of solution components.
NOTE: The Langendorff perfusion system must be cleaned every ten experiments or monthly. The pre-experiment cleaning protocol is explained in section 4. While the post-experiment cleaning protocol is detailed in section 8.
3. Preparation of Tyrode solution during the experiment
- Prepare 1 L of solution in mM: 130.25 NaCl, 5.4 KCl, 0.53 MgCl2(6H2O), 0.33 NaH2PO4, 1.8 CaCl2(2H2O), 10 D-glucose, 10 HEPES, adjusted for pH 7.35 ± 0.05 by NaOH.
- Mix 100 mL Stock I with 700 mL of deionized water under constant stirring, then raise the temperature of the solution to 37 °C; maintain solution oxygenation by connecting the O2 tank to the air stone as shown in Figure 1A (1).
- Add 3.6 mL of Stock II and 96.4 mL of deionized water to obtain 1.8 mM CaCl2(2H2O), then add NaOH to adjust the pH to 7.35 ± 0.05.
- Complete with deionized water to obtain 1 L of Tyrode solution.
NOTE: It is recommended to store 100 mL of the solution in the refrigerator at 4 °C; this volume will be required later in step 6.
4. Langendorff system preparation
NOTE: If the Langendorff system is not filled with ethanol on the day of the experiment, it is not recommended to proceed with the procedure; instead, repeat section 2.
- Turn on the perfusion and drainage pumps. Set the perfusion pump flow rate to 3 mL/min and the drainage pump to 10 mL/min. Drain the system.
- Fill the system with 1 L of deionized water at 37 °C, then drain the water.
- Fill the system with the Tyrode’s solution prepared in step 3 and maintain the solution at physiological temperature and constant oxygenation.
- Turn on the reservoir thermal baths and the serpentine recirculator. Set the reservoir temperature (Figure 1A (2)) to 38 °C to maintain the solution under physiological conditions. Set the temperature of the serpentine (Figure 1A (5)) at 40 °C. This compensates for the loss of temperature in the Langendorff system solution.
NOTE: If the temperature of the Tyrode solution at the system outlet is not physiological (37 ± 0.5 °C), adjust the serpentine recirculator temperature. It is not recommended to proceed to step 6 until the temperature has stabilized at the appropriate value. - Turn on the pressure monitor (Supplementary File 1, monitoring system) and calibrate in the range of 0–200 mmHg. The monitoring and pacing application is available to help calibrate the system (Supplementary File 3 and Supplementary File 11).
NOTE: It is essential to verify that there is no pressure loss and no bubbles in the system. If the system contains bubbles, temporarily block the lower outlet of the serpentine and open the upper valve; this will cause the column to fill, allowing the bubbles to be released into the outside. It is not recommended to proceed with the experiment until this condition has been verified.
5. Optical system14
- Assemble the CMOS camera (Figure 1A, 10), adjustable camera lens (LC), and illumination system.
NOTE: The illumination system consists of two LEDs (Figure 1A, 9), two plano-convex illumination lenses (LI), an illumination control (Figure 1A, 11), an acquisition card (Supplementary File 1, monitoring system), and 3D-designed support pieces (Supplementary File 1). - Place a reference object with a volume of approximately 1,000 mm3 at 100–200 mm from the camera’s lens (center of Figure 1A).
NOTE: The object must be positioned at the heart position in the Langendorff system. This position can be observed in Figure 1B, specifically in the center of the image where the light beams impinge. - Start the camera acquisition software, then set the camera with a subsampling of 4x (4 pixels = 1 subpixel). Set a region of interest (ROI) of 200 x 200 subpixels (Supplementary File 2).
NOTE: With this configuration, a temporal resolution of 750 frames per second (fps) is possible. - Turn on the illumination system (Supplementary File 1), adjust the light beams to focus on the reference object, and achieve homogeneous illumination (Figure 1B).
- Adjust the light intensity on the reference object to avoid overexposing of the image.
NOTE: The image must look like Figure 2A (or Figure 1C, Controller PC). Reflections on the surface of the object (heart) must be reduced as much as possible without losing the definition of its contour. This can be done by adjusting the Illumination control power or by reducing the exposure time in the camera settings. - Focus the camera lens to obtain a clear image of the reference object (Figure 1C, controller PC). Ensure that the reference object occupies 80% of the field of view (Figure 2A) to obtain a conversion scale of approximately 61 µm per subpixel.
NOTE: The optical system automatically activates the Illumination system when the camera is set to acquisition mode (Figure 1A and Supplementary File 2). It is recommended to keep the camera in standby mode so that the Illumination system remains off, activating only during experimental data collection periods to avoid overheating.
6. Surgical and cannulation procedures
- Heparinization and anesthesia
- Prepare an anesthetic mixture containing tiletamine-zolazepam (40 mg/kg mouse body weight) and xylazine (10 mg/kg mouse body weight), then dilute to 200 µL with saline solution.
- Inject the anesthetic mixture intraperitoneally using a 27 G needle. Allow the mouse to enter deep anesthesia.
NOTE: Verify the absence of a reflex in response to a stimulus in the limbs or tail (usually, 10 min is enough). - Inject 200 UI of unfractionated heparin intraperitoneally using a 27 G needle gauge and wait approximately 5 min to continue with the experiment.
- Extraction and cannulation
- Place the mouse in a supine position, remove the fur and skin from the thoracic area with surgical scissors.
- Make an abdominal incision below the diaphragm, making sure to maintain its integrity.
- Continue with a transverse incision in the diaphragm and quickly perform a bilateral ascending thoracotomy through the ribs, then remove the rib wall.
NOTE: Taking care not to damage the heart. If the heart is compromised or damaged during the procedure, it is recommended that the experiment not proceed. - Smoothly hold the superior structures of the heart using fine tweezers, the aortic arch, and adjacent vessels. Smoothly lift to make a cut underneath and upwards, and remove the heart and lungs together.
- Quickly transfer the heart into a petri dish containing 50 mL of Tyrode solution at 4 °C for an initial wash.
NOTE: From the moment the diaphragm is incised, the animal will begin to experience respiratory distress; from this point forward, there is a 60 s window to perform steps 6.2.3–6.2.6. Exceeding this time limit may induce ischemic damage. - Remove lungs and excess adipose tissue to expose the aortic arch using a stereoscopic microscope and fine scissors.
NOTE: When cleaning the tissue, ensure the aortic arch is not damaged. If the aorta is cut below the brachiocephalic artery, cannulation will be difficult, potentially leading to pressure leaks. - Transfer the heart into the custom-made cannulation base containing 50 mL of Tyrode buffer at 4 °C and insert the aortic extremity into the cannula custom-made from a 20 G needle (Supplementary File 1).
NOTE: Be careful not to damage the aortic valve. If the valve is compromised, the heart swells, and the coronary circulation will not properly flush. - Tie two cannulation knots using 4/0 silk suture: the first in the indentation distal to the tip of the cannula and the second before the brachiocephalic trunk (Supplementary File 1).
- Slowly apply Tyrode solution using a 1 mL syringe filled with buffer at room temperature. Verify that the coronary tissue clears to confirm good cannulation.
- Remove adipose tissue to allow access to the ventricles and atria.
NOTE: Avoid exceeding 5 min of cannulation to preserve heart viability. - Transfer the heart into a Langendorff system and allow it to stabilize for 30 min.
NOTE: The heart is placed in the center of the system (Figure 1A,B), suspended vertically. When hanging the heart, take extreme care to prevent air bubbles from forming. If this occurs, the pressure will increase above 140 mmHg, the heart will begin to swell, and it will no longer be viable.
NOTE: The Langendorff montage is complete when the heart exhibits a mechanically stable response, a natural oscillation frequency of approximately 360 beats per minute (BPM), and a perfusion pressure between 60 and 110 mmHg.
7. Pacing protocol and video recording
- Heart viability
- Verify that the coronary pressure is in the range 60–110 mmHg with a 3 mL/min perfusion pump. If the coronary perfusion pressure drops below 60 mmHg, slightly increase the perfusion pump flow rate (low pressure will cause the heart to become pale and flaccid). Conversely, if the pressure exceeds 110 mmHg, slightly decrease the pump flow rate (excessive pressure will induce tissue edema and a progressive increase in pressure until cardiac arrest occurs).}
NOTE: Maintaining the perfusion pressure outside the aforementioned optimal range for an extended period will irreversibly compromise heart viability. - Place the heart in a frontal position so that a full-frontal view is obtained in the camera. Adjust the position so that both atria are visible in the camera (Figure 2A).
- Gently place the platinum electrodes superficially on the top of the right atrium at the pacemaker node. Use the camera feed as a guide to bring the electrodes into the field of view. Position the electrode so that it does not obstruct the right atrium. While monitoring the camera live view, slowly advance the electrode until it contacts the atrial tissue, taking care not to exert excessive compression (which would flatten the right atrium in the image).
NOTE: If performed correctly, the camera view will resemble Figure 2A. - Launch the monitoring and pacing application (Supplementary File 11) and turn on the acquisition card (Figure 1A (6)). Set stimulus parameter values: amplitude at 2 V, frequency at 420, 540, and 720 pulses per minute (PPM) with a 7 ms duty-cycle square pulse (inset of Figure 2A).
- Apply the viability stimulations starting with the lowest frequency, using a stimulation duration of 20 s followed by a 20 s recovery period (resting time) between events.
NOTE: Assess heart viability via camera monitoring. If the organ is physiologically functional, a synchronization between the applied stimulus and the cardiac response will be observed, accompanied by proper coordination between the heart chambers. Conversely, a lack of viability will be manifested by a loss of the chamber’s coordination or by the exclusive presence of isolated atrial contractions. - Close the chamber door because the experiment is sensitive to the room light and thermal fluctuations (Figure 1C).
NOTE: The chamber door must remain closed during experimental time. Monitor the heart viability with the camera and perfusion pressure.
- Verify that the coronary pressure is in the range 60–110 mmHg with a 3 mL/min perfusion pump. If the coronary perfusion pressure drops below 60 mmHg, slightly increase the perfusion pump flow rate (low pressure will cause the heart to become pale and flaccid). Conversely, if the pressure exceeds 110 mmHg, slightly decrease the pump flow rate (excessive pressure will induce tissue edema and a progressive increase in pressure until cardiac arrest occurs).}
- Data recording
- Apply the pacing protocol, which consists of square pulse trains of 30 s duration, followed by 30 s without a signal. Set stimulus parameter values in each pacing train: amplitude at 2 V, 7 ms duty cycle, and frequency in the range of 360 to 720 PPM.
NOTE: Pacing protocol begins at 360 PPM and increases by 60 PPM at each time point (inset of Figure 2A). - Continuously record videos of the dynamics of the heart’s frontal view in .avi format using camera acquisition software (Supplementary File 2). Make a 20 s video recording of each pacing train. Record the 20 s segment beginning 5 s after pacing. A representative raw recording is provided in Supplementary Movie 1.
NOTE: A computer simultaneously records the pacing train applied (.xls, Supplementary File 9) to each recorded video (.avi), generated by the monitoring and pacing application and the camera acquisition software, respectively (Supplementary File 2 and Supplementary File 3). - Verify heart viability by comparing the first video, recorded before starting the stimulation protocol, with the second video, recorded after applying the protocol (Figure 2B).
- Apply the pacing protocol, which consists of square pulse trains of 30 s duration, followed by 30 s without a signal. Set stimulus parameter values in each pacing train: amplitude at 2 V, 7 ms duty cycle, and frequency in the range of 360 to 720 PPM.
8. Langendorff perfusion system post-experimental clean-up
- Remove stimulus and ECG platinum electrodes. Remove the heart from the system and drain all residual Tyrode solutions.
- Turn off the optical system and close the O2 valve.
- Rinse the system with 1 L of deionized water at 37 °C, and drain the system.
- Repeat steps 2.4 and 2.5.
- Turn off all systems and equipment.
9. Video processing
- Begin by importing each video into computational software and applying a video normalization function15.
- Select a region of interest (ROI) that includes the heart area. Perform image segmentation to remove background noise, electrodes, and the cannula (Supplementary File 4).
NOTE: To correctly select the image area to be removed, please refer to Supplementary File 10. - Conduct a global mechanical dynamics analysis (Supplementary File 5). Supporting variability and signal examples are shown in Supplementary Figure S1, Supplementary Figure S2, and Supplementary Figure S3.
- Apply morphological operators to each video frame to detect the heart perimeter, then apply a fill frame algorithm to generate a mask15.
- Count the pixels within the segmented area in each frame, then normalize this count by the total number of pixels in the image to produce a dynamic signal (inset in Figure 2B and Supplementary Figure S3).
- Apply a 5th-order bidirectional Butterworth filter between 3 and 100 Hz to the obtained signal to suppress high-frequency noise and perfusion dripping artifacts15.
- Normalize the signals across all videos using the recorded maximum and minimum values.
- Determine the heart rate by calculating the interval between two maximum-amplitude values (IAA (s)) for each dynamical and stimulus signal.
- Obtain the frequency in BPM with the next formula:
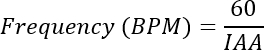
- Generate Poincaré maps from IAA data to illustrate variability over short and long-term periods16,17,18 (Supplementary Figure S1 and Supplementary Figure S2).
NOTE: For more detailed information, please refer to Supplementary File 10.
- Conduct a segmental analysis of the ventricular mechanical dynamics (Supplementary File 6).
- Apply image binarization. Use morphological operators to delimit the ventricular area, adjusting it to an elliptical geometry without compromising the ROI15.
- Fit a minimum ellipse to the ventricular area in each frame. Extract the coordinates of a set of distal points in a frame. Use a set of 10–20 points in each extreme along the Y axis (Figure 3A). A representative ellipse-estimation output is provided in Supplementary Movie 2.
- Calculate the ventricular shortening as the mean distance between extreme points along the Y axis in each video19.
- Apply a 5th-order bidirectional Butterworth filter between 3 and 100 Hz to the obtained signal to suppress high-frequency noise and perfusion dripping artifacts15.
- Normalize the ventricular shortening signal relative to all videos obtained for each pacing, and calculate heart rate and delay as in steps 9.3.5–9.3.6.
NOTE: Parameters, such as ventricular cycle duration (DVE), relaxation duration (DVW), interventricular interval (IVV), and ventricular amplitude (VA), are obtained (Figure 3A).
NOTE: For more detailed information, please refer to Supplementary File 10.
- Conduct a segmental analysis of the atria’s mechanical dynamics (Supplementary File 7).
- Use two ROIs to delimit the atria (Figure 3C).
- Analyze each atrium individually.
- Use morphological operators to delineate atria while adjusting them without compromising the ROI15. Use a contrast-increase algorithm to delineate each atrium20,21.
- Apply image binarization and quantify the number of pixels that differ from zero per frame to obtain an atrial dynamic signal.
- Apply a 5th-order bidirectional Butterworth filter between 3 and 100 Hz to the obtained signals to suppress high-frequency noise and perfusion dripping artifacts15.
- Calculate the average of two atrial signals (Figure 3D).
- Normalize the atrial shortening signal relative to all videos obtained for each pacing and calculate heart rate and delay as in steps 9.3.5–9.3.6.
NOTE: Parameters, such as atrial cycle duration (DAE), atrial-atrial interval (IAT), and atrial amplitude (AA), are obtained (Figure 3D). For more detailed information, refer to Supplementary File 10.
- Conduct an electro-mechanical analysis13,22 (Supplementary File 8).
- Compare the pacing data with the atrial and ventricular signals (Figure 3D).
- Calculate the propagation time in the heart conduction system, obtaining the delay between the atrium and ventricular events (AVD), taking the applied stimulus as a reference.
Access restricted. Please log in or start a trial to view this content.
Results
The cardiac mechanical function experiments are performed using the Langendorff apparatus, as shown in Figure 1A (Top). The monitoring and optical systems enable video recording when illumination control is triggered, as shown in Figure 1A (Bottom). Figure 1C illustrates the external view of the thermostatically controlled cabinet, designed to maintain the heart isolated from ambient thermal fluctua...
Access restricted. Please log in or start a trial to view this content.
Discussion
The mouse heart is very sensitive to temperature variations2,9,10,11,22. In this experiment, the perfused heart was vertically positioned. We included a slight modification to minimize loss of perfusate temperature and motion artifacts in the Langendorff perfusion method. A recirculation pump was added to the serpentine to minimize loss of perfusate temperatur...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors have no conflicts of interest to declare.
Acknowledgements
This work was supported by the Secretariat of Science, Humanities, Technology and Innovation (SECIHTI) grant funded No. LN-2025-C-23.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 1 mL syringe | BD Plastipak | 302485 | Surgical procedure |
| 20 G needle | NIPRO | AH-2032 | Aortic cannula |
| 25 mm adjustable lens with 8x-100x magnification | Generic | N/A | Optical system camera lens; cited generically as adjustable camera lens |
| 27 G needle | BD PrecisionGlide | 302358 | Surgical procedure |
| 3D-designed support pieces | CINVESTAV | N/A | Custom 3D-designed support pieces |
| 4-0 silk suture | AMERICAN SUTURE | TGSN0901 | Aortic cannula |
| 40-A power supply | STEREN | PRL-25 | LED power supply |
| Air stone | N/A | N/A | Tyrode's solution oxygenation |
| CaCl2 (2H2O) | Sigma-Aldrich | C3306 | Tyrode's solution |
| D-Glucose | J.T. Baker | 1916-01 | Tyrode's solution |
| Drainage pump | CINVESTAV | N/A | Custom drainage pump; cited generically as drainage pump |
| F = 25.4 mm, plano-convex lens | THORLABS | LA1951-A | Optical system illumination lens; cited generically as plano-convex illumination lens |
| Glacial acetic acid | Sigma-Aldrich | 695092 | Langendorff system cleaning |
| Heparin | PiSA | 060M91 | Anticoagulant |
| HEPES | Sigma-Aldrich | H3375 | Tyrode's solution |
| High-power LEDs | Luminius | CBT-90-G-L11-C12 | LED light source |
| Illumination system | CINVESTAV | N/A | Custom illumination system; cited generically as illumination system |
| KCl | CTR SCIENTIFIC | CTR02196 | Tyrode's solution |
| LabVIEW software version 2018 | NATIONAL INSTRUMENTS | N/A | Software used to run the monitoring and pacing application; cited generically as monitoring and pacing application |
| MATLAB software | The MathWorks | N/A | Computational software for video normalization, segmentation, and analysis programs; cited generically as computational software |
| Medical-grade oxygen | GRUPO INFRA | N/A | Tyrode's solution oxygenation |
| MgCl2 (6H2O) | CTR SCIENTIFIC | CTR02104 | Tyrode's solution |
| Mini-Pump variable flow | CONTROL COMPANY | 3385 | Perfusion pump |
| Mouse Surgical Kit | Kent Scientific | INSMOUSEKIT | Surgical procedure |
| NaCl | Sigma-Aldrich | S5886 | Tyrode's solution |
| NaH2PO4 | DEQ | DEQF290400250 | Tyrode's solution |
| NaOH | CTR SCIENTIFIC | CTR03108 | pH adjustment |
| NI USB-6009 | NATIONAL INSTRUMENTS | 779026-01 | Acquisition card |
| Platinum electrodes, diam. 0.25 mm | Sigma-Aldrich | 349402 | Electrical stimulation electrodes |
| Power supply (12 V, 30 A) | Karnick | PTA-12V30A | Recirculator power supply |
| Pressure monitor | CINVESTAV | N/A | Custom pressure monitor; cited generically as pressure monitor |
| Pressure transducer | LA BOUVET | B17295 | Langendorff system pressure monitor |
| Pure ethyl alcohol | Sigma-Aldrich | 493511 | Ethanol for system cleaning |
| Recirculating thermal bath (LXC) | PolyScience | L113A0412 | Reservoir recirculator |
| Saline solution | PiSA | 111848 | 0.9% sodium chloride (NaCl) solution |
| Serpentine thermal bath | CINVESTAV | N/A | Custom serpentine recirculator/thermal bath |
| Stereomicroscope | N/A | N/A | Surgical procedure |
| Stereomicroscope illumination | N/A | N/A | Surgical procedure |
| uEye Cockpit software | IDS Imaging Development System GmBH | N/A | Camera acquisition software; cited generically as camera acquisition software |
| UI-3360CP-NIR-GL Rev.2 | IDS | AB00624 | High-speed CMOS camera; cited generically as CMOS camera |
| Xylazine | PiSA | 4001211 | Anesthetic |
| Zoletil 100 | Virbac | 83048907 | Tiletamine-zolazepam anesthetic; cited generically as anesthetic mixture |
References
- Guarina L et al. Biological noise is a key determinant of the reproducibility and adaptability of cardiac pacemaking and EC coupling. J Gen Physiol. 2022;154(9):e202012613.
- Peña-Romo A et al. Noise enhanced the electrical stimulation-contractile response coupling in isolated mouse heart. Int J Cardiol. 2016;221:155-60.
- Bychkov R et al. Synchronized cardiac impulses emerge from heterogeneous local calcium signals within and among cells of pacemaker tissue. JACC Clin Electrophysiol. 2020;6(8):907-31.
- Clancy CE, Santana LF. Evolving discovery of the origin of the heartbeat: a new perspective on sinus rhythm. JACC Clin Electrophysiol. 2020;6(8):932-4.
- Asamudo EU, Ng YH, Bers DM. Langendorff isolated heart perfusion model for functional studies in mice. In: Chandrasekera DNK, Katare R, editors. Cardiomyocytes: Methods and Protocols. Springer Nature; New York; 2025. p. 111-24.
- Louradour J et al. Simultaneous assessment of mechanical and electrical function in Langendorff-perfused ex vivo mouse hearts. Front Cardiovasc Med. 2023;10:1293032.
- Noly PE et al. Assessment of ex vivo murine biventricular function in a Langendorff model. J Vis Exp. 2022;(190):e64384.
- Beckett PR. The isolated perfused heart preparation: two suggested improvements. J Pharm Pharmacol. 1970;22(11):818-22.
- Ihara K et al. Electrophysiological assessment of murine atria with high-resolution optical mapping. J Vis Exp. 2018;(132):e56478.
- King DR, Hardin KM, Hoeker GS, Poelzing S. Reevaluating methods reporting practices to improve reproducibility: an analysis of methodological rigor for the Langendorff whole heart technique. Am J Physiol Heart Circ Physiol. 2022;323(3):H363-77.
- Lang D, Sulkin M, Lou Q, Efimov IR. Optical mapping of action potentials and calcium transients in the mouse heart. J Vis Exp. 2011;(55):e3275.
- Liao R, Podesser BK, Lim CC. The continuing evolution of the Langendorff and ejecting murine heart: new advances in cardiac phenotyping. Am J Physiol Heart Circ Physiol. 2012;303(2):H156-67.
- Sung YL, Tsai YS, Chang CL, Hu YF. Protocol for high-resolution optical mapping of ex vivo rat heart for electrophysiological studies. STAR Protoc. 2025;6(2):103734.
- Lee P et al. Low-cost optical mapping systems for panoramic imaging of complex arrhythmias and drug-action in translational heart models. Sci Rep. 2017;7:43217.
- Laughner JI et al. Processing and analysis of cardiac optical mapping data obtained with potentiometric dyes. Am J Physiol Heart Circ Physiol. 2012;303(7):H753-65.
- Hao X et al. TGF-β1-mediated fibrosis and ion channel remodeling are key mechanisms in producing the sinus node dysfunction associated with SCN5A deficiency and aging. Circ Arrhythm Electrophysiol. 2011;4(3):398-406.
- Pizzo E et al. Heart rate variability reveals altered autonomic regulation in response to myocardial infarction in experimental animals. Front Cardiovasc Med. 2022;9:843144.
- Tayel MB, AlSaba EI. Poincaré plot for heart rate variability. Int J Biomed Biol Eng. 2015;9(9).
- Bazan C, Barba DT, Blomgren P, Paolini P. Image processing techniques for assessing contractility in isolated adult cardiac myocytes. Int J Biomed Imaging. 2009;2009:352954.
- Christoph J, Luther S. Marker-free tracking for motion artifact compensation and deformation measurements in optical mapping videos of contracting hearts. Front Physiol. 2018;9:1483.
- Lebert J, Ravi N, Kensah G, Christoph J. Real-time optical mapping of contracting cardiac tissues with GPU-accelerated numerical motion tracking. Front Cardiovasc Med. 2022;9:787627.
- Larsen TS et al. The isolated working mouse heart: methodological considerations. Pflugers Arch. 1999;437:979-85.
- Vornanen M. Basic functional properties of the cardiac muscle of the common shrew (Sorex araneus) and some other small mammals. J Exp Biol. 1989;145:339-51.
- VanderBrink BA et al. Assessment of atrioventricular nodal physiology in the mouse. J Interv Card Electrophysiol. 1999;3(3):207-12.
- Shansky RM, Murphy AZ. Considering sex as a biological variable will require a global shift in science culture. Nat Neurosci. 2021;24(4):457-64.
- Shansky RM. Are hormones a “female problem” for animal research? Science. 2019;364(6443):825-6.
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
This article has been published
Video Coming Soon