This review synthesizes clinical and translational evidence on recent advances in the pathological classification and treatment of intracranial chordoma, including surgical approaches, radiotherapy, and targeted therapies.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Review Article
New Progress in Pathological Classification and Treatment of Intracranial Chordoma
In This Article
Summary
Abstract
Chordoma is a rare malignant bone tumor with an annual incidence of approximately 0.08 per 100,000 individuals according to the Surveillance, Epidemiology, and End Results (SEER) database, and intracranial chordoma accounts for approximately one-third of all chordoma cases. Its rarity has limited understanding of the disease, particularly of uncommon pathological subtypes, and no universal consensus has been established regarding pathological classification and optimal treatment strategies. Intracranial chordoma is also characterized by difficulty in achieving gross total resection, resistance to conventional radiotherapy and chemotherapy, and a high recurrence rate, which complicate clinical management. This narrative review synthesizes clinical studies and translational research addressing the pathological classification and treatment of intracranial chordoma, with emphasis on surgical approaches, radiotherapy, and targeted therapies. More detailed characterization of pathological subtypes, together with developments in neuroendoscopic surgery, proton beam therapy, carbon ion radiotherapy, and molecularly targeted treatment, has expanded the available approaches to disease classification and management. Evaluation of these developments provides an updated overview of current strategies and remaining challenges in the diagnosis and treatment of intracranial chordoma.
Introduction
Chordoma is a rare, locally aggressive malignant bone tumor arising from remnants of notochordal tissue. According to the Surveillance, Epidemiology, and End Results (SEER) database, the annual incidence is approximately 0.08 per 100,000 individuals, accounting for 1%–4% of primary malignant bone tumors1,2. Chordomas predominantly occur in the axial skeleton, including the clivus, spine, and sacrococcygeal region. Intracranial chordomas account for approximately 27%–42% of all chordomas and are generally slow-growing tumors with infrequent metastasis1,3,4,5,6,7. However, resistance to conventional radiotherapy and chemotherapy, together with the difficulty of achieving complete surgical resection, contributes to a recurrence rate of approximately 30%–51%8,9,10,11,12,13,14,15.
Chordomas are pathologically classified into three subtypes: conventional or classic chordoma, poorly differentiated chordoma, and dedifferentiated chordoma. Conventional chordoma is associated with a relatively favorable prognosis and is primarily managed by complete surgical resection when feasible. In contrast, poorly differentiated and dedifferentiated chordomas exhibit more aggressive behavior and poorer clinical outcomes and may require multimodal treatment, including surgery, radiotherapy, and targeted therapy. Pathological classification, therefore, has an important role in treatment selection and clinical management. This review examines recent advances in the pathological characterization and treatment of intracranial chordoma, with emphasis on the relationship between pathological subtype and therapeutic strategy.
Access restricted. Please log in or start a trial to view this content.
Review and Perspective
1. Classification
- Conventional/classic chordoma
Conventional chordoma is the most common pathological subtype16,17. Microscopically, the tumor is primarily composed of epithelioid cells embedded in a myxoid stroma and arranged in lobules separated by fibrous septa11. These epithelioid cells characteristically contain vacuolated cytoplasm and are referred to as physaliphorous or vacuolated cells, a characteristic first described by the German pathologist Rudolf Virchow in 185718. Certain chordomas exhibit both vacuolated cytomorphology and a hyaline cartilaginous matrix and are histologically similar to chondrosarcoma; these tumors are referred to as chondroid chordomas6,19. Chondroid chordoma was previously classified as an independent pathological subtype but is included within conventional chordoma in the latest World Health Organization (WHO) classification of bone and soft tissue tumors. Although earlier studies suggested a more favorable prognosis for chondroid chordoma than for conventional chordoma, more recent studies indicate minimal prognostic differences between the two20,21,22,23. Well-differentiated conventional chordoma may histologically resemble benign notochordal cell tumor (BNCT), which has a more favorable prognosis and generally does not require surgical intervention, making careful differentiation important. Conventional chordoma has the most favorable prognosis among the three chordoma subtypes, with a median overall survival of 4–7 years and a 10-year survival rate of approximately 40%–60%12. - Poorly differentiated chordoma
Poorly differentiated chordoma is a very rare subtype. In the 1980s and 1990s, Sibley, Coffin, and colleagues reported malignant skull-base tumors in children that lacked the characteristic vacuolated cells of chordoma but demonstrated immunohistochemical features consistent with chordoma, including positivity for cytokeratin, vimentin, and S-100 protein24,25. Consequently, classification as a distinct pathological subtype remained controversial for an extended period, and heterogeneous terms such as cellular chordoma and atypical chordoma were used in the literature24,25,26,27,28,29. Poorly differentiated chordoma was formally recognized as a distinct subtype in the 2020 WHO Classification of Tumours of Soft Tissue and Bone. Microscopically, tumor cells exhibit rhabdoid and signet-ring features, lack the characteristic vacuolated cells of conventional chordoma, and rarely show a mucinous matrix30,31,32. This subtype is associated with a substantially poorer prognosis than conventional chordoma. In a study by Hoch et al., 5 of 6 patients with poorly differentiated chordoma died, corresponding to an 83% mortality rate; 2 patients developed lung metastases, and the only surviving patient developed cervical lymph node metastasis33. Mean overall survival has been reported to range from approximately 9–53 months32,34,35. - Dedifferentiated chordoma
Dedifferentiated chordoma is another rare pathological subtype and predominantly affects adults. Histopathologically, these tumors are characterized by biphasic morphology, with classic vacuolated chordoma cells coexisting with a high-grade sarcomatous component composed of spindle or pleomorphic cells. The two components maintain distinct borders while showing transitional zones that illustrate progression from chordomatous to sarcomatous differentiation36. Immunohistochemically, the conventional component resembles conventional chordoma, whereas the sarcomatous component shows loss of Brachyury expression and is negative for cytokeratin37. Heffelfinger et al. termed this sarcomatous transformation “dedifferentiation,” and subsequent studies commonly adopted the term “dedifferentiated chordoma”6,38,39,40. Terms such as sarcomatoid chordoma and anaplastic chordoma have also been used. Because “anaplastic chordoma” has referred to poorly differentiated chordoma in some studies, continued use of these overlapping terms is not recommended41. Dedifferentiated chordoma demonstrates the most aggressive clinical behavior and the poorest prognosis among chordoma subtypes, with median overall survival after diagnosis generally less than 24 months38,42.
2. Immunohistochemistry and molecular biology
The Brachyury gene belongs to the T-box (TBX) gene family, and its encoded protein is important for notochord development43,44,45. Brachyury expression is highly restricted to the embryonic notochord and chordoma, providing high sensitivity and specificity as a diagnostic marker22,43,45,46. Brachyury is therefore an important immunohistochemical marker for distinguishing chordoma from other tumors. Its expression also provides molecular evidence supporting the notochordal origin of chordoma. Some studies have suggested that Brachyury-negative chordomas are associated with a poorer prognosis than Brachyury-positive tumors46. However, this association has been reported in only a limited number of studies and requires further validation.
SWI/SNF-related, matrix-associated, actin-dependent regulator of chromatin, subfamily B, member 1 (SMARCB1) is a core component of the switch/sucrose-non-fermentable (SWI/SNF) chromatin-remodeling complex. Loss of this tumor-suppressor gene is strongly associated with the development of atypical teratoid and rhabdoid tumors34,47. SMARCB1 is generally retained in chordoma subtypes other than poorly differentiated chordoma and can therefore assist in distinguishing poorly differentiated chordoma from other subtypes34,48. Chordomas also characteristically express cytokeratin, and most express epithelial membrane antigen (EMA) and S100 protein21,46,49,50. These immunohistochemical markers help distinguish chordoma from other tumors. The pathological subtypes and immunohistochemical characteristics of chordoma are summarized in Table 1.
| Type | High-Risk Population | Pathological Characteristics | Immunohistochemistry/Molecular Biology | Prognosis |
| Conventional chordoma | Adults | Vacuolated cells are present | Positive for Brachyury, cytokeratin, S100 protein, and SMARCB1 | Most favorable among the three subtypes |
| Poorly differentiated chordoma | Children and adolescents | Absence of characteristic vacuolated cells | Loss of SMARCB1 | Intermediate |
| Dedifferentiated chordoma | Adults | Contains both vacuolated chordoma cells and a high-grade sarcomatous component | Conventional component resembles conventional chordoma; the dedifferentiated component shows loss of Brachyury and is negative for cytokeratin | Poor |
Table 1: Pathological subtypes and immunohistochemical characteristics of chordoma. Summary of the pathological subtypes of chordoma and their principal immunohistochemical characteristics. SMARCB1, SWI/SNF-related, matrix-associated, actin-dependent regulator of chromatin, subfamily B, member 1.
3. Therapy
- Surgical Therapy
Surgical resection remains the primary treatment modality for intracranial chordoma. Intracranial chordomas frequently arise in the clivus, where critical neural and vascular structures make complete tumor resection technically challenging. The extent of resection is an important prognostic factor51. Accordingly, maximal safe resection remains a principal objective of surgical management.
Surgical approaches can be broadly categorized as anterior, lateral, and posterior52,53,54. Data from Beijing Tiantan Hospital indicate that approximately 60% of intracranial chordomas arise in the upper two-thirds of the clivus55. Many intracranial chordomas can therefore be accessed through a ventral transnasal transsphenoidal route, permitting tumor resection while preserving surrounding anatomical structures. Transsphenoidal surgery can be performed using endoscopic-assisted or microscopic-assisted techniques. A systematic review by Komotar et al. analyzed outcomes in 766 patients with intracranial chordoma and reported a higher gross total resection (GTR) rate with endoscopic endonasal surgery (EES) than with traditional open surgery (61.0% vs. 48.1%)56. The reported incidences of nerve injury, cerebrospinal fluid (CSF) leakage, and meningitis after EES were 1.3%, 5.0%, and 0.9%, respectively, compared with 24.2%, 10.7%, and 5.9% after open surgery56. Mortality and recurrence rates were also lower in the EES cohorts than in the open-surgery cohorts (4.7% vs. 21.6% and 16.8% vs. 40%, respectively)56. No statistically significant differences were reported for pneumonia, sepsis, diabetes insipidus, wound infection, or hydrocephalus56. Free fat grafts may assist in repairing dural defects, reducing CSF leakage, and providing a physical barrier along dural defects55.
The limitations of EES are primarily related to tumor location, extent of infiltration, and tumor size. Although chordomas are more frequently located in the upper and middle clivus, approximately one-third occur in the lower clivus9,55. The lower clivus lies at the distal end of the transsphenoidal approach, which can make complete resection more difficult. Residual tumor and recurrence rates after surgery have been reported to be higher for lower clival chordomas than for tumors of the upper and middle clivus8. In such cases, a far-lateral approach may be considered. Tumor infiltration also affects approach selection. When a tumor extends bilaterally beyond the clivus, the operating space and visual field available through an endoscopic approach may be limited. Alternative approaches have therefore been described. Orbitofrontal craniotomy has been recommended for tumors extending lateral to the optic nerve, whereas far-lateral or posterior transpetrous approaches may be considered for tumors extending lateral to the carotid artery57. Tumor size is another important factor. Chordomas with a diameter greater than 4 cm or a volume exceeding 80 cm3 may be difficult to resect completely using EES alone and may require combined surgical approaches58.
EES is therefore an important surgical option for chordomas of the upper and middle clivus. For tumors located in the lower clivus, tumors of excessive size, or tumors with extensive bilateral invasion, the surgical approach should be individualized according to anatomical and biological characteristics. Evidence comparing surgical approaches remains limited by the rarity of chordoma and the absence of large randomized controlled trials. Aside from several meta-analyses, the largest single-center series has been reported from Beijing Tiantan Hospital. Differences among studies in definitions of resection extent and residual tumor further limit direct comparison of outcomes. Larger multicenter studies using standardized outcome definitions are therefore needed to clarify the relative advantages and limitations of different surgical approaches. - Radiotherapy
Conventional radiotherapy has limited efficacy in intracranial chordoma. Proton beam therapy (PBT) and carbon ion radiotherapy (CIRT) have been associated with reduced recurrence and improved survival outcomes23,32. These particle-based approaches produce a concentrated energy deposition near the end of the radiation path, known as the Bragg peak, allowing a therapeutic dose to be delivered to the tumor while reducing radiation exposure to adjacent normal tissues59,60,61. PBT and CIRT have been evaluated in spinal, sacral, and intracranial chordoma populations62,63,64,65,66,67. A systematic review and meta-analysis by Rodrigues et al. reported 5-year overall survival (OS) rates of 83% for PBT and 89% for CIRT and 5-year progression-free survival (PFS) rates of 84% and 81%, respectively67. PBT and CIRT require specialized facilities and large particle accelerators, which limit their availability. Standardized radiotherapy protocols, including modality selection and dose prescription, have also not been established. Earlier studies frequently evaluated extracranial chordoma populations, whereas evidence specifically addressing intracranial chordoma remains comparatively limited67,68,69. These factors continue to limit the broader application and direct comparison of particle radiotherapy approaches. - Pharmacotherapy
- Targeted Therapies
Targeted therapies evaluated in chordoma include inhibitors of platelet-derived growth factor receptor (PDGFR), epidermal growth factor receptor (EGFR), and vascular endothelial growth factor receptor (VEGFR).
Imatinib mesylate is a tyrosine kinase inhibitor (TKI) targeting PDGFR and has been widely studied in chordoma70,71. Reported partial response (PR) rates range from 0%–5%, stable disease (SD) rates from 69%–74%, and progressive disease (PD) rates from 26%–28%; median PFS is approximately 9 months, and OS ranges from approximately 30–35 months72,73,74. Imatinib has also been evaluated in combination with mammalian target of rapamycin (mTOR) inhibitors such as everolimus or sirolimus and with cyclophosphamide75,76,77. Dasatinib, another PDGFR inhibitor, has also been evaluated in chordoma. In a phase 2 trial involving 32 patients, median PFS was 6.3 months, with 2-year and 5-year OS rates of 43% and 18%, respectively78.
EGFR inhibitors evaluated in chordoma include erlotinib, lapatinib, and cetuximab. Clinical evidence for erlotinib remains limited. In a study of five patients receiving erlotinib monotherapy and evaluated according to Response Evaluation Criteria in Solid Tumors (RECIST), one patient achieved PR and four achieved SD74. Erlotinib has also been evaluated in combination with cetuximab, linsitinib, and other agents79,80,81,82,83,84. A phase II trial by Stacchiotti et al. evaluated lapatinib monotherapy and reported PR, SD, and PD rates of 40%, 50%, and 10%, respectively, with median PFS of 8 months and median OS of 25 months85. Cetuximab, gefitinib, and other EGFR inhibitors have also been reported in chordoma, although available evidence remains limited and further investigation is required86,87.
Sorafenib is a TKI targeting VEGFR and PDGFR88,89. In a phase 2 trial involving 27 patients, the PR rate was 4%, the 6-month PFS rate was 85.35%, the 6-month OS rate was 100%, the 9-month PFS rate was approximately 73%, and the 12-month OS rate was approximately 86.5%89. Another clinical study reported PR, SD, and PD rates of 9%, 82%, and 9%, respectively74. Sunitinib and pazopanib are additional multitargeted TKIs with similar pharmacological mechanisms90,91,92. Reported SD and PD rates for sunitinib were 44% and 56%, respectively, whereas SD and PD rates for pazopanib were both 50%; PFS of up to 15 months was reported in some patients93,94.
Collectively, available studies indicate potential disease-control activity of therapies targeting PDGFR, EGFR, and VEGFR. However, the evidence base remains limited by small sample sizes, case reports, and retrospective analyses. The largest phase 2 trial included 56 patients, demonstrating the scarcity of large systematic clinical studies. Most studies also evaluated advanced chordoma without stratification by pathological subtype. Consequently, the therapeutic activity of these agents across different pathological subtypes remains insufficiently defined. Selected non-case-report studies are summarized in Table 2. Targeted therapies evaluated in chordoma include inhibitors of platelet-derived growth factor receptor (PDGFR), epidermal growth factor receptor (EGFR), and vascular endothelial growth factor receptor (VEGFR) (Figure 1). - Cytotoxic drugs
Camptothecin-based agents and alkylating agents have also been evaluated in chordoma. A phase II trial of oral 9-nitrocamptothecin in patients with advanced or metastatic chordoma reported a median PFS of 9.9 weeks, with 3-month and 6-month PFS rates of 47% and 33%, respectively95. In a small retrospective series, Dhall et al. described three patients treated with postoperative cyclophosphamide and etoposide; all remained recurrence-free during long-term follow-up, with a median follow-up of 9 years and a range of 6–13 years96. Another report described complete remission in a pediatric patient treated with vincristine, cyclophosphamide, and etoposide; magnetic resonance imaging showed tumor shrinkage at 3 months and no detectable tumor at 12- and 30-month follow-up97. Anthracyclines and cisplatin have also been reported to produce partial responses in some patients. However, these reports have largely involved poorly differentiated or dedifferentiated chordoma, and the available evidence remains limited. - Other drugs
Palbociclib is a cyclin-dependent kinase (CDK) inhibitor. CDKs are serine/threonine kinases involved in cell-cycle regulation and transcription. Homozygous deletion of CDKN2A and CDKN2B has been reported in a subset of chordomas and is associated with altered CDK activity and tumor proliferation98. Palbociclib has been evaluated in chordoma cell lines and patient-derived xenografts, and a phase 2 clinical trial has also been initiated99,100,101,102.
Immunotherapeutic approaches under investigation include immune checkpoint inhibitors, T-cell therapies, monoclonal antibodies, and vaccine therapies targeting Brachyury. Most studies remain at an early stage, and evidence of clinical benefit is currently limited103,104,105,106. The underlying regulatory mechanisms also require further clarification. These approaches, therefore, remain investigational therapeutic strategies for chordoma.
- Targeted Therapies
| Target | Drug | Study Type | Sample Size | PR (%) | SD (%) | PD (%) | PFS | OS |
| PDGFR | Imatinib | Phase 2 | 56 | 2 | 70 | 28 | 9.2 months | 35 months |
| Imatinib | Retrospective case series | 46 | 0 | 74 | 26 | 9.9 months | 30 months | |
| Imatinib | Retrospective study | 62 | 5 | 69 | 26 | NR | NR | |
| Dasatinib | Phase 2 | 32 | NR | NR | NR | 6.3 months | NR | |
| EGFR | Erlotinib | Retrospective study | 5 | 20 | 80 | NR | 4 months | NR |
| Lapatinib | Phase 2 | 18 | 40 | 50 | 10 | 8 months | 25 months | |
| VEGFR | Sorafenib | Phase 2 | 27 | 4 | NR* | NR* | 6-month PFS: 85.35%; 9-month PFS: 73.0% | 6-month OS: 100%; 12-month OS: 86.5% |
| Sorafenib | Retrospective study | 11 | 9 | 82 | 9 | NR | NR | |
| Sunitinib | Phase 2 | 9 | NR | 44 | 56 | NR | NR | |
| Pazopanib | Case series | 4 | NR | 50 | 50 | 8.5 months | NR | |
| Abbreviation, PR, Partial Response; SD, Stable Disease; PD, Progressive Disease; PFS, Progression-Free Survival; OS, Overall Survival | ||||||||
| Foot note, in the study by Bompas et al.89, the median PFS and OS were not described. These data were the PFS rates at 6/9 and 12 months | ||||||||
Table 2: Selected targeted therapy studies in chordoma. Summary of selected studies evaluating targeted therapies in chordoma, including treatment response and survival outcomes. PR, partial response; SD, stable disease; PD, progressive disease; PFS, progression-free survival; OS, overall survival.
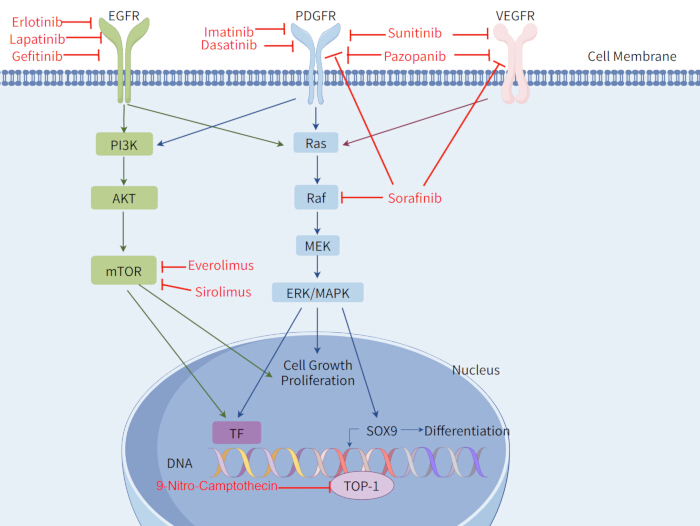
Figure 1: Chordoma-related therapeutic targets and signal transduction pathways. Overview of chordoma-related therapeutic targets and associated signal transduction pathways. EGFR, epidermal growth factor receptor; PDGFR, platelet-derived growth factor receptor; VEGFR, vascular endothelial growth factor receptor; PI3K, phosphoinositide 3-kinase; AKT, protein kinase B; mTOR, mammalian target of rapamycin; Ras, rat sarcoma; Raf, rapidly accelerated fibrosarcoma; MEK, mitogen-activated protein kinase kinase; ERK, extracellular signal-regulated kinase; MAPK, mitogen-activated protein kinase; TF, transcription factor; SOX9, SRY-box transcription factor 9; TOP-1, topoisomerase I. Created using FigDraw. Please click here to view a larger version of this figure.
Access restricted. Please log in or start a trial to view this content.
Conclusions
Advances in pathological classification and treatment have improved the understanding and management of chordoma. The 2020 WHO classification refined chordoma taxonomy by recognizing poorly differentiated chordoma as a distinct entity. Surgical resection remains the main treatment for intracranial chordoma. Endoscopic endonasal surgery has shown favorable outcomes for tumors involving the upper and middle clivus, including higher gross total resection rates and lower recurrence in observational studies. However, the avai...
Access restricted. Please log in or start a trial to view this content.
Disclosures
No conflicts of interest are disclosed.
Acknowledgements
No specific grant was received from funding agencies in the public, commercial, or not-for-profit sectors.
Access restricted. Please log in or start a trial to view this content.
References
- McMaster ML et al. Chordoma: incidence and survival patterns in the United States, 1973–1995. Cancer Causes Control. 2001;12(1):1-11. doi:10.1023/A:1008947301735.
- Healey JH, Lane JM. Chordoma: a critical review of diagnosis and treatment. Orthop Clin North Am. 1989;20(3):417-426.
- Eriksson B, Gunterberg B, Kindblom LG. Chordoma: a clinicopathologic and prognostic study of a Swedish national series. Acta Orthop Scand. 1981;52(1):49-58. doi:10.3109/17453678108991758.
- Higinbotham NL, Phillips RF, Farr HW, Hustu HO. Chordoma: thirty-five-year study at Memorial Hospital. Cancer. 1967;20(11):1841-1850. doi:10.1002/1097-0142(196711)20:11<1841::AID-CNCR2820201107>3.0.CO;2-2.
- Chambers KJ et al. Incidence and survival patterns of cranial chordoma in the United States. Laryngoscope. 2014;124(5):1097-1102. doi:10.1002/lary.24420.
- Heffelfinger MJ, Dahlin DC, MacCarty CS, Beabout JW. Chordomas and cartilaginous tumors at the skull base. Cancer. 1973;32(2):410-420. doi:10.1002/1097-0142(197308)32:2<410::AID-CNCR2820320219>3.0.CO;2-S.
- Soo MY. Chordoma: review of clinicoradiological features and factors affecting survival. Australas Radiol. 2001;45(4):427-434. doi:10.1046/j.1440-1673.2001.00950.x.
- Jahangiri A et al. Factors predicting recurrence after resection of clival chordoma using variable surgical approaches and radiation modalities. Neurosurgery. 2015;76(2):179–186. doi:10.1227/NEU.0000000000000611.
- Sen C et al. Clival chordomas: clinical management, results, and complications in 71 patients. J Neurosurg. 2010;113(5):1059-1071. doi:10.3171/2009.9.JNS08596.
- Di Maio S, Temkin N, Ramanathan D, Sekhar LN. Current comprehensive management of cranial base chordomas: 10-year meta-analysis of observational studies. J Neurosurg. 2011;115(6):1094-1105. doi:10.3171/2011.7.JNS11355.
- Wasserman JK, Gravel D, Purgina B. Chordoma of the head and neck: a review. Head Neck Pathol. 2018;12(2):261–268. doi:10.1007/s12105-017-0860-8.
- Yamaguchi T, Imada H, Iida S, Szuhai K. Notochordal tumors. Surg Pathol Clin. 2017;10(3):637-656. doi:10.1016/j.path.2017.04.008.
- Colia V, Stacchiotti S. Medical treatment of advanced chordomas. Eur J Cancer. 2017;83:220-228. doi:10.1016/j.ejca.2017.06.038.
- Radaelli S et al. Sacral chordoma: long-term outcome of a large series of patients surgically treated at two reference centers. Spine. 2016;41(12):1049-1057. doi:10.1097/BRS.0000000000001604.
- Fischbein NJ, Kaplan MJ, Holliday RA, Dillon WP. Recurrence of clival chordoma along the surgical pathway. AJNR Am J Neuroradiol. 2000;21(3):578-583.
- Lee IJ, Lee RJ, Fahim DK. Prognostic factors and survival outcome in patients with chordoma in the United States: a population-based analysis. World Neurosurg. 2017;104:346-355. doi:10.1016/j.wneu.2017.04.118.
- Tauziède-Espariat A et al. Prognostic and therapeutic markers in chordomas: a study of 287 tumors. J Neuropathol Exp Neurol. 2016;75(2):111-120. doi:10.1093/jnen/nlv010.
- Sahyouni R, Goshtasbi K, Mahmoodi A, Chen JW. A historical recount of chordoma. J Neurosurg Spine. 2018;28(4):422-428. doi:10.3171/2017.7.SPINE17668.
- Rosenberg AE, Brown GA, Bhan AK, Lee JM. Chondroid chordoma—a variant of chordoma: a morphologic and immunohistochemical study. Am J Clin Pathol. 1994;101(1):36-41. doi:10.1093/ajcp/101.1.36.
- Forsyth PA et al. Intracranial chordomas: a clinicopathological and prognostic study of 51 cases. J Neurosurg. 1993;78(5):741-747. doi:10.3171/jns.1993.78.5.0741.
- Mitchell A et al. Chordoma and chondroid neoplasms of the spheno-occiput: an immunohistochemical study of 41 cases with prognostic and nosologic implications. Cancer. 1993;72(10):2943-2949. doi:10.1002/1097-0142(19931115)72:10<2943::AID-CNCR2820721014>3.0.CO;2-6.
- Vujovic S et al. Brachyury, a crucial regulator of notochordal development, is a novel biomarker for chordomas. J Pathol. 2006;209(2):157-165. doi:10.1002/path.1969.
- Jian BJ et al. Adjuvant radiation therapy and chondroid chordoma subtype are associated with a lower tumor recurrence rate of cranial chordoma. J Neurooncol. 2010;98(1):101-108. doi:10.1007/s11060-009-0068-1.
- Sibley RK, Day DL, Dehner LP, Trueworthy RC. Metastasizing chordoma in early childhood: a pathological and immunohistochemical study with review of the literature. Pediatr Pathol. 1987;7(3):287-301. doi:10.1080/15513818709177131.
- Coffin CM, Swanson PE, Wick MR, Dehner LP. Chordoma in childhood and adolescence: a clinicopathologic analysis of 12 cases. Arch Pathol Lab Med. 1993;117(9):927-933.
- Becker LE, Yates AJ, Hoffman HJ, Norman MG. Intracranial chordoma in infancy: case report. J Neurosurg. 1975;42(3):349-352. doi:10.3171/jns.1975.42.3.0349.
- Wold LE, Laws ER. Cranial chordomas in children and young adults. J Neurosurg. 1983;59(6):1043-1047. doi:10.3171/jns.1983.59.6.1043.
- Borba LA, Al-Mefty O, Mrak RE, Suen J. Cranial chordomas in children and adolescents. J Neurosurg. 1996;84(4):584-591. doi:10.3171/jns.1996.84.4.0584.
- Sassin JF, Chutorian AM. Intracranial chordoma in children. Arch Neurol. 1967;17(1):89-93. doi:10.1001/archneur.1967.00470250093010.
- Tirabosco R, O'Donnell P, Flanagan AM. Notochordal tumors. Surg Pathol Clin. 2021;14(4):619-643. doi:10.1016/j.path.2021.06.006.
- Karpathiou G et al. Chordomas: a review with emphasis on their pathophysiology, pathology, molecular biology, and genetics. Pathol Res Pract. 2020;216(9):153089. doi:10.1016/j.prp.2020.153089.
- Yeter HG, Kosemehmetoglu K, Soylemezoglu F. Poorly differentiated chordoma: review of 53 cases. APMIS. 2019;127(9):607–615. doi:10.1111/apm.12978.
- Hoch BL, Nielsen GP, Liebsch NJ, Rosenberg AE. Base of skull chordomas in children and adolescents: a clinicopathologic study of 73 cases. Am J Surg Pathol. 2006;30(7):811-818. doi:10.1097/01.pas.0000209828.39477.ab.
- Hasselblatt M et al. Poorly differentiated chordoma with SMARCB1/INI1 loss: a distinct molecular entity with dismal prognosis. Acta Neuropathol. 2016;132(1):149-151. doi:10.1007/s00401-016-1574-9.
- Shih AR et al. Clinicopathologic characteristics of poorly differentiated chordoma. Mod Pathol. 2018;31(8):1237-1245. doi:10.1038/s41379-018-0002-1.
- Morimitsu Y, Aoki T, Yokoyama K, Hashimoto H. Sarcomatoid chordoma: chordoma with a massive malignant spindle-cell component. Skeletal Radiol. 2000;29(12):721-725. doi:10.1007/s002560000264.
- Hung YP et al. Dedifferentiated chordoma: clinicopathologic and molecular characteristics with integrative analysis. Am J Surg Pathol. 2020;44(9):1213-1223. doi:10.1097/PAS.0000000000001501.
- Meis JM et al. “Dedifferentiated” chordoma: a clinicopathologic and immunohistochemical study of three cases. Am J Surg Pathol. 1987;11(7):516-525. doi:10.1097/00000478-198707000-00003.
- Smith J, Reuter V, Demas B. Case report 576. Anaplastic sacrococcygeal chordoma (dedifferentiated chordoma). Skeletal Radiol. 1989;18(7):561-564. doi:10.1007/BF00351762.
- Ng WK, Tang V. Crush preparation findings of “sarcomatoid” chordoma of the sacrum: report of a case with histologic, immunohistochemical, and ultrastructural correlation. Diagn Cytopathol. 2001;25(6):406-410. doi:10.1002/dc.10024.
- Chavez JA, Nasir Ud Din, Memon A, Perry A. Anaplastic chordoma with loss of INI1 and brachyury expression in a 2-year-old girl. Clin Neuropathol. 2014;33(6):418-420. doi:10.5414/NP300724.
- Fernandez-Miranda JC et al. Clival chordomas: a pathological, surgical, and radiotherapeutic review. Head Neck. 2014;36(6):892-906. doi:10.1002/hed.23415.
- Miettinen M et al. Nuclear Brachyury expression is consistent in chordoma, common in germ cell tumors and small cell carcinomas, and rare in other carcinomas and sarcomas: an immunohistochemical study of 5229 cases. Am J Surg Pathol. 2015;39(10):1305-1312. doi:10.1097/PAS.0000000000000462.
- Showell C, Binder O, Conlon FL. T-box genes in early embryogenesis. Dev Dyn. 2004;229(1):201-218. doi:10.1002/dvdy.10480.
- Jambhekar NA et al. Revisiting chordoma with brachyury, a “new age” marker: analysis of a validation study on 51 cases. Arch Pathol Lab Med. 2010;134(8):1181-1187. doi:10.5858/2009-0476-OA.1.
- Oakley GJ, Fuhrer K, Seethala RR. Brachyury, SOX-9, and podoplanin, new markers in the skull base chordoma vs chondrosarcoma differential: a tissue microarray-based comparative analysis. Mod Pathol. 2008;21(12):1461-1469. doi:10.1038/modpathol.2008.144.
- Roberts CWM, Leroux MM, Fleming MD, Orkin SH. Highly penetrant, rapid tumorigenesis through conditional inversion of the tumor suppressor gene Snf5. Cancer Cell. 2002;2(5):415-425. doi:10.1016/S1535-6108(02)00185-X.
- Mobley BC et al. Loss of SMARCB1/INI1 expression in poorly differentiated chordomas. Acta Neuropathol. 2010;120(6):745-753. doi:10.1007/s00401-010-0767-x.
- Tirabosco R et al. Brachyury expression in extra-axial skeletal and soft tissue chordomas: a marker that distinguishes chordoma from mixed tumor/myoepithelioma/parachordoma in soft tissue. Am J Surg Pathol. 2008;32(4):572-580. doi:10.1097/PAS.0b013e31815b693a.
- Al-Adnani M, Cannon SR, Flanagan AM. Chordomas do not express CD10 and renal cell carcinoma antigen: an immunohistochemical study. Histopathology. 2005;47(5):535-537. doi:10.1111/j.1365-2559.2005.02131.x.
- Barber SM et al. Chordoma—current understanding and modern treatment paradigms. J Clin Med. 2021;10(5):1054. doi:10.3390/jcm10051054.
- Crumley RL, Gutin PH. Surgical access for clivus chordoma: the University of California, San Francisco, experience. Arch Otolaryngol Head Neck Surg. 1989;115(3):295-300. doi:10.1001/archotol.1989.01860270037011.
- Blevins NH, Jackler RK, Kaplan MJ, Gutin PH. Combined transpetrosal-subtemporal craniotomy for clival tumors with extension into the posterior fossa. Laryngoscope. 1995;105(9):975-982. doi:10.1288/00005537-199509000-00018.
- Bertalanffy H, Seeger W. The dorsolateral, suboccipital, transcondylar approach to the lower clivus and anterior portion of the craniocervical junction. Neurosurgery. 1991;29(6):815-821. doi:10.1097/00006123-199112000-00002.
- Wang L et al. Clinical features and surgical outcomes of patients with skull base chordoma: a retrospective analysis of 238 patients. J Neurosurg. 2017;127(6):1257-1267. doi:10.3171/2016.9.JNS16559.
- Komotar RJ et al. The endoscope-assisted ventral approach compared with open microscope-assisted surgery for clival chordomas. World Neurosurg. 2011;76(3-4):318-327. doi:10.1016/j.wneu.2011.02.026.
- Koutourousiou M et al. Endoscopic endonasal approach for resection of cranial base chordomas: outcomes and learning curve. Neurosurgery. 2012;71(3):614-625. doi:10.1227/NEU.0b013e31825ea3e0.
- Fraser JF et al. Endoscopic endonasal transclival resection of chordomas: operative technique, clinical outcome, and review of the literature. J Neurosurg. 2010;112(5):1061-1069. doi:10.3171/2009.7.JNS081504.
- Yaniv D et al. Skull base chordomas: review of current treatment paradigms. World J Otorhinolaryngol Head Neck Surg. 2020;6(2):125-131. doi:10.1016/j.wjorl.2020.01.008.
- Konieczkowski DJ, DeLaney TF, Yamada Y. Radiation strategies for spine chordoma: proton beam, carbon ions, and stereotactic body radiation therapy. Neurosurg Clin N Am. 2020;31(2):263-288. doi:10.1016/j.nec.2019.12.002.
- Wu S et al. Carbon ion radiotherapy for patients with extracranial chordoma or chondrosarcoma: initial experience from Shanghai Proton and Heavy Ion Center. J Cancer. 2019;10(15):3315-3322. doi:10.7150/jca.29667.
- Mima M et al. Particle therapy using carbon ions or protons as a definitive therapy for patients with primary sacral chordoma. Br J Radiol. 2014;87(1033):20130512. doi:10.1259/bjr.20130512.
- Uhl M et al. Carbon ion beam treatment in patients with primary and recurrent sacrococcygeal chordoma. Strahlenther Onkol. 2015;191(7):597-603. doi:10.1007/s00066-015-0825-3.
- Imai R et al. Carbon ion radiation therapy for unresectable sacral chordoma: an analysis of 188 cases. Int J Radiat Oncol Biol Phys. 2016;95(1):322-327. doi:10.1016/j.ijrobp.2016.02.012.
- Fuchs B et al. Operative management of sacral chordoma. J Bone Joint Surg Am. 2005;87(10):2211-2216. doi:10.2106/JBJS.D.02693.
- Stacchiotti S et al. Chordoma of the mobile spine and sacrum: a retrospective analysis of a series of patients surgically treated at two referral centers. Ann Surg Oncol. 2010;17(1):211-219. doi:10.1245/s10434-009-0740-x.
- Rodrigues ACLF et al. Proton beam and carbon ion radiotherapy in skull base chordoma: a systematic review, meta-analysis and meta-regression with trial sequential analysis. Neurosurg Rev. 2024;47(1):893. doi:10.1007/s10143-024-03117-1.
- Potter GM et al. Skull base chordoma and chondrosarcoma: neuroradiologist's guide to diagnosis, surgical management, and proton beam therapy. Radiographics. 2024;44(10):e240036. doi:10.1148/rg.240036.
- Gersey ZC et al. A refined treatment strategy for skull base chordoma: a protocol and management algorithm. Neurosurg Rev. 2025;48(1):729. doi:10.1007/s10143-025-03869-4.
- Tamborini E et al. Molecular and biochemical analyses of platelet-derived growth factor receptor B, PDGFRA, and KIT receptors in chordomas. Clin Cancer Res. 2006;12(23):6920-6928. doi:10.1158/1078-0432.CCR-06-1584.
- Zeinali M et al. Systematic review of novel target therapies and clinical trials in chordoma. Clin Neurol Neurosurg. 2025;259:109222. doi:10.1016/j.clineuro.2025.109222.
- Hindi N et al. Imatinib in advanced chordoma: a retrospective case series analysis. Eur J Cancer. 2015;51(17):2609-2614. doi:10.1016/j.ejca.2015.07.038.
- Stacchiotti S et al. Phase II study of imatinib in advanced chordoma. J Clin Oncol. 2012;30(9):914-920. doi:10.1200/JCO.2011.35.3656.
- Lebellec L et al. Advanced chordoma treated by first-line molecular targeted therapies: outcomes and prognostic factors. A retrospective study of the French Sarcoma Group (GSF/GETO) and the Association des Neuro-Oncologues d'Expression Française (ANOCEF). Eur J Cancer. 2017;79:119-128. doi:10.1016/j.ejca.2017.03.037.
- Stacchiotti S et al. Imatinib and everolimus in patients with progressing advanced chordoma: a phase 2 clinical study. Cancer. 2018;124(20):4056-4063. doi:10.1002/cncr.31685.
- Stacchiotti S et al. Response to imatinib plus sirolimus in advanced chordoma. Ann Oncol. 2009;20(11):1886-1894. doi:10.1093/annonc/mdp210.
- Adenis A et al. A dose-escalating phase I of imatinib mesylate with fixed dose of metronomic cyclophosphamide in targeted solid tumours. Br J Cancer. 2013;109(10):2574-2578. doi:10.1038/bjc.2013.648.
- Schuetze SM et al. Phase 2 study of dasatinib in patients with alveolar soft part sarcoma, chondrosarcoma, chordoma, epithelioid sarcoma, or solitary fibrous tumor. Cancer. 2017;123(1):90-97. doi:10.1002/cncr.30379.
- Singhal N, Kotasek D, Parnis FX. Response to erlotinib in a patient with treatment refractory chordoma. Anticancer Drugs. 2009;20(10):953-955. doi:10.1097/CAD.0b013e328330c7f0.
- Launay SG et al. Efficacy of epidermal growth factor receptor targeting in advanced chordoma: case report and literature review. BMC Cancer. 2011;11:423. doi:10.1186/1471-2407-11-423.
- Houessinon A et al. Sustained response of a clivus chordoma to erlotinib after imatinib failure. Case Rep Oncol. 2015;8(1):25-29. doi:10.1159/000371843.
- Macaulay VM et al. Phase I dose-escalation study of linsitinib (OSI-906) and erlotinib in patients with advanced solid tumors. Clin Cancer Res. 2016;22(12):2897-2907. doi:10.1158/1078-0432.CCR-15-2218.
- Migliorini D et al. First report of clinical responses to immunotherapy in 3 relapsing cases of chordoma after failure of standard therapies. Oncoimmunology. 2017;6(8):e1338235. doi:10.1080/2162402X.2017.1338235.
- Asklund T et al. Durable stabilization of three chordoma cases by bevacizumab and erlotinib. Acta Oncol. 2014;53(7):980-984. doi:10.3109/0284186X.2013.878472.
- Stacchiotti S et al. Phase II study on lapatinib in advanced EGFR-positive chordoma. Ann Oncol. 2013;24(7):1931-1936. doi:10.1093/annonc/mdt117.
- Hof H, Welzel T, Debus J. Effectiveness of cetuximab/gefitinib in the therapy of a sacral chordoma. Onkologie. 2006;29(12):572-574. doi:10.1159/000096283.
- Lindèn O, Stenberg L, Kjellén E. Regression of cervical spinal cord compression in a patient with chordoma following treatment with cetuximab and gefitinib. Acta Oncol. 2009;48(1):158-159. doi:10.1080/02841860802266672.
- Wilhelm SM et al. BAY 43-9006 exhibits broad spectrum oral antitumor activity and targets the RAF/MEK/ERK pathway and receptor tyrosine kinases involved in tumor progression and angiogenesis. Cancer Res. 2004;64(19):7099-7109. doi:10.1158/0008-5472.CAN-04-1443.
- Bompas E et al. Sorafenib in patients with locally advanced and metastatic chordomas: a phase II trial of the French Sarcoma Group (GSF/GETO). Ann Oncol. 2015;26(10):2168-2173. doi:10.1093/annonc/mdv300.
- Chow LQM, Eckhardt SG. Sunitinib: from rational design to clinical efficacy. J Clin Oncol. 2007;25(7):884–896. doi:10.1200/JCO.2006.06.3602.
- Chellappan DK et al. The role of pazopanib on tumour angiogenesis and in the management of cancers: a review. Biomed Pharmacother. 2017;96:768-781. doi:10.1016/j.biopha.2017.10.058.
- Meng T et al. Molecular targeted therapy in the treatment of chordoma: a systematic review. Front Oncol. 2019;9:30. doi:10.3389/fonc.2019.00030.
- George S et al. Multicenter phase II trial of sunitinib in the treatment of nongastrointestinal stromal tumor sarcomas. J Clin Oncol. 2009;27(19):3154-3160. doi:10.1200/JCO.2008.20.9890.
- Lipplaa A, Dijkstra S, Gelderblom H. Efficacy of pazopanib and sunitinib in advanced axial chordoma: a single reference centre case series. Clin Sarcoma Res. 2016;6:19. doi:10.1186/s13569-016-0059-x.
- Chugh R et al. Phase II study of 9-nitro-camptothecin in patients with advanced chordoma or soft tissue sarcoma. J Clin Oncol. 2005;23(15):3597-3604. doi:10.1200/JCO.2005.02.170.
- Dhall G et al. The role of chemotherapy in pediatric clival chordomas. J Neurooncol. 2011;103(3):657-662. doi:10.1007/s11060-010-0441-0.
- Al-Rahawan MM, Siebert JD, Mitchell CS, Smith SD. Durable complete response to chemotherapy in an infant with a clival chordoma. Pediatr Blood Cancer. 2012;59(2):323-325. doi:10.1002/pbc.23297.
- Martinez Moreno M et al. Shedding light on emerging therapeutic targets for chordoma. Expert Opin Ther Targets. 2023;27(8):705-713. doi:10.1080/14728222.2023.2248382.
- Von Witzleben A et al. Preclinical characterization of novel chordoma cell systems and their targeting by pharmacological inhibitors of the CDK4/6 cell-cycle pathway. Cancer Res. 2015;75(18):3823-3831. doi:10.1158/0008-5472.CAN-14-3270.
- Liu T et al. CDK4 expression in chordoma: a potential therapeutic target. J Orthop Res. 2018;36(6):1581-1589. doi:10.1002/jor.23819.
- Passeri T et al. In vivo efficacy assessment of the CDK4/6 inhibitor palbociclib and the PLK1 inhibitor volasertib in human chordoma xenografts. Front Oncol. 2022;12:960720. doi:10.3389/fonc.2022.960720.
- Sharifnia T et al. Small-molecule targeting of brachyury transcription factor addiction in chordoma. Nat Med. 2019;25(2):292-300. doi:10.1038/s41591-018-0312-3.
- Godinez C et al. Combinatorial therapies for epigenetic, immunotherapeutic, and genetic targeting of chordoma. J Neurooncol. 2025;172(2):307-315. doi:10.1007/s11060-024-04920-y.
- Heery CR et al. Phase I trial of a yeast-based therapeutic cancer vaccine (GI-6301) targeting the transcription factor Brachyury. Cancer Immunol Res. 2015;3(11):1248-1256. doi:10.1158/2326-6066.CIR-15-0119.
- Heery CR et al. Phase I study of a poxviral TRICOM-based vaccine directed against the transcription factor Brachyury. Clin Cancer Res. 2017;23(22):6833-6845. doi:10.1158/1078-0432.CCR-17-1087.
- DeMaria PJ et al. Randomized, double-blind, placebo-controlled phase II study of yeast-Brachyury vaccine (GI-6301) in combination with standard-of-care radiotherapy in locally advanced, unresectable chordoma. Oncologist. 2021;26(5):e847-e858. doi:10.1002/onco.13720.
Access restricted. Please log in or start a trial to view this content.