This bibliometric and visualized analysis maps the development of negative pressure wound therapy (NPWT) research from 1991 to 2026. It summarizes publication patterns, collaboration networks, influential sources, and thematic transitions from mechanistic studies to wound care, wound dressings, infection prevention, and clinical outcome evaluation.
Research Article
Negative Pressure Wound Therapy Research: A Bibliometric and Visualized Analysis of the Web of Science Core Collection
* These authors contributed equally
In This Article
Summary
Abstract
Negative pressure wound therapy (NPWT) is widely used in surgical and wound care, but its long-term intellectual structure and collaboration patterns remain incompletely characterized. We screened 5,957 records retrieved from the Web of Science Core Collection and conducted a bibliometric and visualized analysis of 4,063 included articles and reviews. Records were screened independently by two researchers, and disagreements were resolved by consensus. VOSviewer, CiteSpace, and complementary statistical tools were used to evaluate publication trends, collaboration networks, keyword co-occurrence, citation bursts, and country-level patterns. Publication activity increased markedly after 2004. The United States and China were the most productive countries, whereas European and U.S. institutions occupied central positions in collaboration networks. Thematic emphasis evolved from subatmospheric pressure, perfusion, and mechanistic research toward wound care, wound dressings, surgical-site infection, diabetic foot ulcers, and efficacy. These findings define the development of NPWT research and identify priorities for multicenter clinical studies, mechanistic investigation, material innovation, and international collaboration.
Introduction
Negative pressure wound therapy (NPWT) is a widely used clinical modality that promotes wound healing by applying localized subatmospheric pressure to reduce tissue edema, remove exudate, and support infection control. It has been applied to diabetic foot ulcers1,2, open abdominal wounds3,4, traumatic soft-tissue defects, and orthopedic wounds5,6. Landmark experimental and clinical reports published in 1997 established the biological basis and clinical feasibility of vacuum-assisted closure7,8. Proposed mechanisms include microdeformation-induced cell proliferation9, angiogenesis10, and improved local perfusion. Over the past three decades, the clinical scope of NPWT has expanded toward individualized treatment and device-based innovation, including NPWT with instillation11.
Despite its widespread use, uncertainty remains regarding the strength of the clinical evidence for NPWT12. A 2014 Cochrane review found insufficient evidence of clear benefits for surgical wounds healing by primary intention and noted the potential influence of commercial funding13. A subsequent Cochrane update reported uncertainty for several clinically important outcomes, although NPWT may reduce surgical-site infection in selected settings14. Adequately powered, independently funded trials are therefore needed, particularly in high-risk surgical populations. Optimal pressure settings, dressing selection, site-specific protocols, and long-term prognostic factors also remain incompletely defined. Research activity is geographically uneven. Foundational experimental and clinical studies of NPWT were conducted by U.S. research groups, and subsequent global analyses indicate that U.S. and European institutions became prominent contributors to the field’s research and collaboration networks7,8,15. Chinese research groups have contributed a growing body of clinical evidence involving diabetic foot ulcers1, burns16, and orthopedic and open-fracture wounds17. In the present dataset, however, Chinese publications were more frequently produced within single-country research networks, and participation in multinational collaborations was less extensive than that observed among several established U.S. and European groups. These findings highlight opportunities to strengthen multinational collaboration and mechanistically oriented research on NPWT.
Bibliometric analysis provides a quantitative framework for mapping publication trends, collaboration networks, influential contributors, core journals, highly cited studies, and emerging topics. Although a bibliometric analysis of NPWT has previously been reported15, a comprehensive evaluation of publication trends, collaboration networks, influential sources, and thematic evolution remains limited. This study, therefore, mapped publication trends, collaboration networks, influential sources, and thematic evolution in NPWT research.
Protocol
The complete bibliometric workflow consists of literature retrieval, eligibility assessment, duplicate and version checking, independent relevance screening, data standardization, descriptive analysis, network analysis, and visualization. The raw records, screening decisions, and reproducible analysis package are provided in Supplemental File 1, Supplemental File 2, and Supplemental File 3, respectively.
Data source and search strategy
The bibliometric analysis was conducted using the Web of Science Core Collection (WoSCC), with the Science Citation Index Expanded (SCI-EXPANDED/SCIE) selected as the data source. The publication period was restricted to 1 January 1991 through 30 June 2026; therefore, the 2026 publication cohort represents a partial year because the search window ended on 30 June 2026.
The following search strategy was applied: TS=("negative pressure wound therapy" OR "vacuum assisted closure" OR "vacuum sealing drainage") AND DOP=(1991-01-01/2026-06-30). The Topic (TS) field was used to search titles, abstracts, author keywords, and Keywords Plus, whereas the Date of Publication (DOP) field was used to restrict the publication period.
No language or document-type restrictions were applied during record retrieval. Eligibility assessment was performed after data export to preserve a complete and auditable record-selection process. The final WoSCC search was conducted on 23 July 2026, yielding 5,957 records, which were exported on 24 July 2026. The complete search strategy, database and index information, date range, search and export dates, and eligibility workflow are summarized in Figure 1 and further documented in the README Reproducible Workflow.md file provided in Supplemental File 3.
Record export and initial data verification
The retrieved records were exported from the Web of Science Core Collection with Full Record and Cited References selected as the record content and Plain Text File as the export format. Because the total dataset exceeded the maximum number of records permitted per export, the 5,957 records were downloaded in 12 consecutive batches comprising records 1–500, 501–1,000, 1,001–1,500, 1,501–2,000, 2,001–2,500, 2,501–3,000, 3,001–3,500, 3,501–4,000, 4,001–4,500, 4,501–5,000, 5,001–5,500, and 5,501–5,957.
Following export, the records were verified to ensure that the principal bibliographic fields required for subsequent analyses were present, including the accession number (UT), DOI, title, authors, affiliations, source journal, publication year (PY), publication date (PD), document type (DT), language, abstract, author keywords, Keywords Plus, total citations (TC), usage counts (U1 and U2), and cited references (CR). The original plain-text export files were preserved without modification and are provided as Supplemental File 1.
Because the WoSCC plain-text export does not retain the search-history page or a dedicated exported Date of Publication (DOP) field, the original search string and search date were documented in Figure 1, the manuscript, and the README Reproducible Workflow.md file included in Supplemental File 3. The original DOP restriction applied during database retrieval was retained and was not replaced by post-export filtering based on publication year (PY), publication date (PD), or Early Access (EA) date.
Document-type screening and retraction assessment
The 5,957 retrieved records were imported into the screening dataset for eligibility assessment. Original research articles and review articles were retained without applying any language restrictions. Eligible Web of Science document-type classifications included Article, Article; Proceedings Paper, Article; Early Access, Review, and Review; Early Access. Early Access was treated as an indexing status rather than as an independent publication type to avoid duplicate counting of the same publication.
During screening, 1,078 records with ineligible document types were excluded, followed by the removal of 59 retraction-related records. After document-type screening and retraction assessment, 4,820 Article- and Review-type records were retained for duplicate and version assessment. The excluded records and the corresponding record-specific reasons are provided in the DT_Exclusions_1078 and Retraction_Exclusions_59 worksheets of Supplemental File 2.
Duplicate and publication-version assessment
Duplicate and publication-version assessment was performed using the Web of Science accession number (UT) as the primary record identifier. When duplicate or related records had different accession numbers, they were compared using the DOI, normalized title, authors, source journal, publication year, volume, issue, page numbers, abstract, document type, and publication-version information. For each set of related records, the final or most appropriate publication version was retained, and the relationship between retained and excluded records was documented.
A total of 23 duplicate or superseded-version records were removed, including nine superseded Cochrane review versions and 14 verified duplicate, reprint, duplicate-indexing, language-version, or other related-version records. After duplicate and publication-version assessment, 4,797 unique records were retained for topical relevance screening. The accession numbers of retained and excluded records, duplicate-verification criteria, and record-specific rationales are provided in the Duplicate_Exclusions_23 worksheet of Supplemental File 2.
Independent topical relevance screening
Topical relevance screening was independently performed by two trained researchers on the 4,797 unique records. Each reviewer evaluated the title, abstract, author keywords, and Keywords Plus for every record and recorded an independent inclusion or exclusion decision together with a record-specific rationale before reconciliation.
Records were considered eligible when negative pressure wound therapy (NPWT), vacuum-assisted closure (VAC), or vacuum sealing drainage (VSD) constituted the principal intervention or comparator, the technique under evaluation, a primary clinical outcome, the subject of a mechanistic investigation, a guideline or consensus topic, or a principal component of the wound-management pathway. Records were excluded when NPWT, VAC, or VSD was mentioned only as background information, included only in a list of treatment options, reported solely as a previously failed treatment or non-use, used only as an incidental rescue measure, described only as a complication or covariate, fell outside the principal subject of the study, or appeared only as a false-positive Keywords Plus term.
The independent screening decisions were compared, with initial agreement achieved for 4,782 records and disagreement identified for 15 records. All discrepancies were resolved through discussion, and, when necessary, adjudication by a third researcher. The final decision and supporting rationale were documented for each disputed record. In the audited dataset, all 15 disputed records were ultimately excluded, and no disagreements remained unresolved.
Following topical relevance screening, 734 records were excluded and 4,063 records were retained for the bibliometric analysis. Supplemental File 2 contains the decisions of both reviewers, reviewer-specific rationales, disagreement indicators, final inclusion decisions, supporting evidence statements, and the final dataset of 4,063 records.
The final record-selection process was internally verified, confirming that the 5,957 retrieved records comprised 1,137 records excluded because of document type or retraction status, 23 duplicate or superseded records, 734 records excluded during topical relevance screening, and 4,063 records included in the final bibliometric analysis (5,957 = 1,137 + 23 + 734 + 4,063). Figure 1 presents a PRISMA-style flow diagram to illustrate the bibliographic record-selection process. Because this study is a bibliometric analysis rather than a systematic review, a full-text risk-of-bias assessment was not performed.
Final dataset construction and cited-reference integration
The final dataset of 4,063 records was finalized and frozen on 24 July 2026 and was used for all subsequent descriptive, citation, network, and visualization analyses. All included records were verified to contain unique Web of Science accession numbers (UTs).
To enable cited-reference analyses, the cited-reference (CR) fields were retrieved from the complete 5,957-record Full Record and Cited References export and integrated into the final dataset by exact matching of UT identifiers. This integration process was performed without altering dataset membership or the citation and usage-count snapshot associated with the original export.
Following integration, 4,048 included records were confirmed to contain at least one exported cited-reference (CR) field, whereas 15 records contained no cited-reference list in the Web of Science Core Collection export. The cited-reference integration script and the corresponding audit report are provided in Supplemental File 3.
Data cleaning and descriptive analysis
Author names, institutional names, journal titles, cited references, countries/regions, and keywords were standardized using unit-specific thesauri. Separate thesauri were applied to each analytical unit, and author, organization, country, keyword, journal, and cited-reference thesauri were not combined during the standardization process.
Annual publication output was grouped according to the publication year (PY) recorded in the Web of Science Core Collection. Years with no publications between 1991 and 2026 were retained in the analysis and displayed as zero to ensure a continuous time series. Document types were classified into five mutually exclusive categories, with Early Access treated as an indexing status rather than an independent publication type to avoid duplicate counting.
Total citations (TC), usage counts during the preceding 180 days (U1), and usage counts since 2013 (U2) were aggregated by publication year. Because TC, U1, and U2 are dynamic indicators in the Web of Science Core Collection, these metrics represent the database snapshot exported on 24 July 2026.
Data processing, screening-log management, descriptive statistical analyses, and generation of Figure 2A,B and Figure 3A–C were performed using Python 3.12.10 with the pandas 3.0.3, openpyxl 3.1.5, and matplotlib 3.11.0 libraries, together with Microsoft Excel.
VOSviewer network analyses
Bibliometric network analyses were performed using VOSviewer version 1.6.21. The final Web of Science Core Collection plain-text dataset was imported as bibliographic database files. Full counting was applied for all analyses, and association-strength normalization was used to construct and visualize the bibliometric networks.
Unit-specific thesauri were applied according to the analytical unit under investigation. Keyword co-occurrence analysis was performed using All keywords with a minimum occurrence threshold of 30, resulting in a network comprising 158 nodes and 6,468 edges (Figure 4A). Author collaboration analysis was conducted using the Authors unit with a minimum threshold of six documents per author, producing a network of 51 nodes and 134 edges (Figure 5A). Institutional collaboration analysis was performed using the Organizations unit with a minimum threshold of 10 documents per organization, yielding 109 nodes and 351 edges (Figure 5B). Country collaboration analysis used the Countries unit with a minimum threshold of seven documents per country, generating a supplemental network containing 50 nodes and 438 edges. Source-journal bibliographic coupling analysis was conducted using the Sources unit with a minimum threshold of 20 documents per source, resulting in 39 nodes and 741 edges (Figure 6A). Cited-reference co-citation analysis was performed using the Cited references unit with a minimum threshold of 68 citations per reference, producing a network of 91 nodes and 3,626 edges (Figure 6C).
The VOSviewer map files and corresponding network files generated for each analysis were retained to ensure reproducibility. The complete mapping parameters, threshold values, thesauri, mapping audits, and saved VOSviewer map and network files are provided in Supplemental File 3.
CiteSpace keyword burst and journal dual-map analyses
Keyword burst detection and journal dual-map analyses were performed using CiteSpace version 7.0.R0 (64-bit, Advanced) with the final frozen Web of Science Core Collection dataset. Keyword burst analysis was conducted using a time span of 1991–2026 with 1-year time slices. Terms were extracted from the title, abstract, author keywords, and Keywords Plus fields. Keyword was selected as the node type, the selection criterion was set to Top N = 50 per time slice, and no pruning was applied.
Citation burst analysis was performed using the Burstness function, and the 25 keywords with the strongest citation bursts were retained for presentation in Figure 4B. Because the literature search covered publications only through 30 June 2026, citation bursts terminating in 2026 were interpreted as extending to the endpoint of the partial search window rather than representing activity across a complete calendar year.
A journal dual-map overlay was generated from the same frozen Web of Science dataset to visualize citation pathways between citing and cited journal disciplines (Figure 7). The complete CiteSpace parameter settings and the saved Top-25 keyword burst results are provided in Supplemental File 3.
Institutional, journal, and country-level visualizations
Institutional, journal, and country-level bibliometric visualizations were generated using bibliometrix and complementary visualization software. Institutional names were harmonized using the standardized affiliation data described above. The collaboration network was then constructed based on co-authorship relationships among institutions meeting the predefined publication threshold. Nodes represent institutions, links denote collaborative relationships, and thicker links indicate higher collaboration intensity.
To examine citation relationships among the most productive journals, the 15 journals with the highest publication output were identified. Directed citation links were constructed from citing journals to cited journals after excluding journal self-citations. The resulting network comprised 15 nodes and 200 directed non-self citation edges. For visualization, only the 56 citation links with weights of at least 45 were displayed in Figure 6B. This network represents direct citation relationships among the 15 most productive journals and does not constitute a Bradford core analysis or a bibliographic-coupling map.
Country and region analyses were performed using full counting across all author affiliations, with each country contributing no more than once to an individual publication. Publications were classified as single-country publications (SCP) or multiple-country publications (MCP) according to the corresponding author's country and whether the complete set of author affiliations represented one or multiple countries. For country-level analyses only, Taiwan, Hong Kong, and Macao were aggregated under China, while the original institutional names and address information were preserved.
Country/region analyses and SCP/MCP visualizations presented in Figure 8A,B were generated using R version 4.6.1 with the bibliometrix (v5.4.1) and ggplot2 (v4.0.3) packages, together with SCImago Graphica version 1.0.55.
Reproducibility and data verification
Reproducibility and technical validation were supported through three complementary supplemental files. Supplemental File 1 contains the unmodified raw Web of Science Core Collection (WoSCC) export used as the primary data source. Supplemental File 2 documents all document-type, retraction, duplicate/publication-version, and topical-relevance screening decisions, enabling complete reproduction of the study selection process.
Supplemental File 3 provides the materials required to reproduce the data-cleaning procedures, cited-reference integration, descriptive analyses, VOSviewer network analyses, CiteSpace keyword burst analyses, institutional collaboration network, journal direct-citation network, and technical validation procedures. Reproduced outputs were compared with the archived node counts, edge counts, screening totals, cited-reference coverage, and figure-source audit files to verify analytical consistency.
All analyses were confirmed to use the same frozen dataset comprising 4,063 records and the same citation and usage-count snapshot obtained on 24 July 2026. Consolidated software versions and key analytical parameters are provided in the Table of Materials.
Results
Basic publication output and annual trend analysis
A total of 4,063 NPWT-related publications were included: 3,563 Articles (87.7%) and 500 Reviews (12.3%). These totals classify Early Access as an indexing status rather than a separate document type. Annual publication output is shown in Figure 2A, and the plotting categories used to display document types and Early Access status are shown in Figure 2B.
Publication output was minimal from 1991 to 2003 and began to rise in 2004. Growth accelerated after 2019, and output remained high during 2021–2025. This trajectory indicates sustained international interest in NPWT.
Figure 2B uses five mutually exclusive display categories to show Early Access status: Article (n = 3,340; 82.2%), Article Proceedings Paper (n = 203; 5.0%), Article Early Access (n = 20; 0.5%), Review (n = 492; 12.1%), and Review Early Access (n = 8; 0.2%). Thus, 3,340 + 203 + 20 = 3,563 Articles and 492 + 8 = 500 Reviews; the five plotting categories sum to the same 4,063 records included in the PRISMA flow diagram.
Citation and usage trend analysis
Citation and usage patterns were evaluated by publication year. U1 was defined as the 180-day recent usage count, and U2 was defined as cumulative usage since 2013. Aggregate U1 and U2 values are influenced by the number and age of publications in each annual cohort. Results are shown in Figure 3.
As shown in Figure 3A, the annual total citation count reached its highest level of 5,265 in 2017, followed by 5,117 in 2013, 4,818 in 2008, 4,810 in 2011, and 4,714 in 2014. In contrast, the cumulative citation counts for articles published from 2024 to 2026 appeared comparatively lower; however, this observation should be interpreted with caution, as it may reflect a restricted citation window rather than an intrinsic decline in scholarly influence. Regarding citation performance per publication, the highest average was recorded for papers published in 1997 (1,681 citations per paper); however, this value was based on only two highly cited foundational publications and was therefore strongly influenced by the small cohort size. Mean and median citation counts should be considered when comparing citation performance across publication-year cohorts.
Figure 3B presents the recent usage count (U1) of publications by publication year over the past 180 days. The U1 metric reflects recent platform activity associated with published articles. It should be noted that the total U1 counts are inherently affected by the number of publications per year. Across all included records, the total U1 count was 1,507. Publications from 2025 recorded the highest U1 count (372), followed by those from 2023 and 2024 (167 each), 2021 (140), and the partial 2026 cohort (121). These findings indicate relatively high recent platform activity for newer NPWT publication cohorts. However, U1 should not be interpreted as a direct measure of full-text downloads, readership, or scholarly impact.
Cumulative usage since 2013 (U2) reflects longer-term platform activity. As shown in Figure 3C, publications from 2017 recorded the highest cumulative usage count (3,284), followed by those from 2021 (2,502), 2014 (2,166), 2020 (2,080), and 2015 (1,953). The total U2 count across all included records was 31,766. Notably, publications from 2021 demonstrated considerable cumulative usage despite their relatively shorter availability period. All U1 and U2 usage data were exported from the Web of Science Core Collection on 24 July 2026, and the temporal availability of these metrics should be taken into account when interpreting recent publication cohorts. For publications issued before 2013, U2 includes only usage recorded since 2013 and therefore does not represent lifetime usage.
Keyword co-occurrence and burst analysis
Following the identification of overall publication output and trend dynamics, this study further recognized research hotspots and frontier evolution in the field through keyword co-occurrence and burst analyses, with the results presented in Figure 4.
A minimum occurrence threshold of 30 was applied to improve network readability. A total of 158 connected keywords were retained to construct the co-occurrence network, which contained 6,468 links and was divided into 6 clusters (Figure 4A). Cluster 1 (red cluster) primarily focused on the core technologies, mechanisms, and reconstructive applications of NPWT. The most prominent keywords included “negative pressure wound therapy,” “reconstruction,” “trial,” “dressings,” and “device,” representing research focusing on equipment, mechanisms and reconstructive applications. Other highly associated terms included “skin,” “VAC,” “wounds,” “wound control,” “system,” “flap,” “defects,” “fractures,” and “repair,” reflecting research related to NPWT techniques, underlying mechanisms, and wound management.
Cluster 2 (green cluster) was mainly associated with wound healing and diabetic foot ulcers. The central keyword was “wound healing,” accompanied by terms such as “diabetic foot ulcers,” “multicenter,” “ulcers,” “wound,” “care,” “debridement,” and “instillation.” This cluster primarily represented clinical investigations evaluating the therapeutic efficacy of NPWT in chronic wounds, particularly diabetic foot ulcers.
Cluster 3 (blue cluster) focused on surgical complications, outcomes, and infection prevention. The core keyword was “complications,” “surgery,” “surgical site infection,” “prevention,” and “outcomes.” This cluster reflected the application of NPWT in perioperative complication management, surgical site infection prevention, and outcome evaluation.
The remaining clusters further complemented the knowledge structure of the NPWT field. Cluster 4 (yellow) was related to open-abdomen and trauma management, with “management,” “open abdomen,” “trauma,” “closure,” and “abdominal compartment syndrome.” as representative keywords. Cluster 5 (purple) focused on infection and cardiothoracic surgical applications, centered on “infection,” “mediastinitis,” “cardiac surgery,” “risk factors,” and “poststernotomy mediastinitis.” Cluster 6 (light blue) represented complex infections and their clinical outcomes, centered on “mortality,” “necrotizing fasciitis,” “Fournier’s gangrene,” “diagnosis,” and “case report.” Collectively, these six clusters provide a comprehensive overview of the major research directions and knowledge structure within the NPWT field.
Keyword burst analysis revealed the temporal characteristics of the top 25 keywords with the strongest citation bursts from 1991 to 2026 (Figure 4B). The three keywords with the highest burst strengths were “wound control” (strength = 41.68, 1999–2011), “subatmospheric pressure” (strength = 32.63, 2001–2014), and “wound care” (strength = 28.20, 2021–2026). During the early period (1999–2014), research primarily focused on the fundamental principles of negative pressure technology, represented by “wound control,” “subatmospheric pressure,” “topical negative pressure,” “wound closure,” “fascial closure,” and “VAC therapy.”
During the intermediate period (2007–2018), research directions gradually shifted toward specific clinical applications, including soft tissue injury, poststernotomy mediastinitis, abdominal compartment syndrome, and randomized controlled trials. In recent years, research hotspots have further evolved toward “surgical site infection” (2019–2026), “risk” (2019–2026), “diabetic foot ulcer” (2020–2026), and “wound care” (2021–2026), highlighting the growing emphasis on wound management, infection prevention and control, and diabetic foot ulcer treatment. Furthermore, the emergence of “case report” (2021–2026) and “efficacy” (2024–2026) as burst keywords indicates that clinical outcome evaluation and the accumulation of clinical evidence from case-based studies have become emerging frontiers in this field.
Interdisciplinary characteristics
To further illustrate the distribution patterns of source and cited journals, a dual-map overlay analysis was performed, as shown in Figure 7. The citing journals are displayed on the left side of the map, whereas the cited journals are presented on the right side. The labels represent the major disciplinary areas covered by the journals, and the colored curves indicate the major citation pathways from citing journals to cited journals.
Several prominent citation pathways were identified in the current map. The most significant pathway originated from “Medicine, Medical, Clinical” on the left and extended toward “Health, Nursing, Medicine” on the right, indicating that NPWT studies published in clinical medical journals primarily drew upon knowledge from health, nursing, and medicine journals. In addition, citation links were observed from “Medicine, Medical, Clinical” toward “Molecular Biology, Genetics” and “Dermatology, Dentistry, Surgery,” reflecting the interdisciplinary connections between NPWT research and molecular biology, surgical science, and related clinical specialties. Overall, these citation patterns demonstrate the interdisciplinary nature of NPWT research, with citation links spanning clinical medicine, nursing and health sciences, molecular biology, dermatology, dentistry, and surgery.
Author and institutional collaboration networks
As shown in Figure 5A, analysis of the author collaboration network based on 4,063 included publications revealed a multi-centric collaborative landscape comprising five major clusters, with 51 connected authors and 134 collaborative links. The green cluster, centered around Ingemansson R with Malmsjö M and Lindstedt S as co-core authors, represented the largest collaborative team in the field, predominantly from Lund University, Sweden. The red cluster was centered on Gabriel A, Kim PJ, and Attinger CE and also included Gupta S and Stannard JP, bringing together major clinical investigators from North America and Europe. The blue cluster, centered on Orgill DP and Horch RE, was primarily associated with plastic and reconstructive surgery. The yellow cluster, led by Lavery LA, Armstrong DG, and Kirsner RS, concentrated on diabetic foot and wound management. The purple cluster was centered on Sjögren J and included Hetzer R, Petzina R, and Gustafsson L, reflecting collaboration in cardiothoracic surgery and mediastinitis management.
According to Price’s Law, the core author threshold was calculated as M = 0.749 × √Nmax, where Nmax = 60 and M was approximately 5.80. Authors with at least 6 publications were classified as core authors. A total of 212 authors met this threshold, representing 1.3% of the 16,615 authors in the dataset. Figure 5A shows collaboration among these core authors; isolated nodes and some labels may not be displayed. The most prolific authors were Ingemansson R (60 publications), Malmsjö M (54), Orgill DP (39), Horch RE (34), Lindstedt S (29), Armstrong DG and Gabriel A (21 each), and Attinger CE, Liu Y, and Yu AX (20 each). These publication counts are summarized in Table 1.
Regarding institutional collaboration, as shown in Figure 5B, the network revealed a multi-centric landscape comprising nine major clusters, with prominent hubs in Europe and the United States and a distinct cluster of Chinese institutions. The red cluster included Harvard University, Harvard Medical School, Brigham and Women’s Hospital, Heidelberg University, Duke University, and the University of Utah. The green cluster was centered on Lund University, Lund University Hospital, and Skåne University Hospital and included Griffith University, Uppsala University, the University of Queensland, Ghent University, the University of Amsterdam, and the University of Helsinki. The blue cluster consisted primarily of Chinese institutions, including Shanghai Jiao Tong University, Zhejiang University, Soochow University, Shandong University, Sun Yat-sen University, and Sichuan University. The yellow cluster included the University of Oxford, the University of Manchester, Karolinska Institutet, University College London, and the University of Warwick. The purple cluster comprised the University Hospital Zurich, Mayo Clinic, Hannover Medical School, and the medical universities of Vienna and Graz. The light-blue cluster included Wake Forest University, the University of Miami, Georgetown University, the University of Arizona, MedStar Georgetown University Hospital, and the University of Toronto. The remaining orange, brown, and pink clusters represented additional collaborative groups centered on institutions such as Chang Gung University, the University of São Paulo, the University of Pisa, the University of Maryland, Johns Hopkins University, and the Cleveland Clinic.
In the institutional network visualization, node size was proportional to institutional publication output, edges denoted collaborative relationships with line thickness reflecting collaboration intensity, and node color represented cluster affiliation. Lund University exhibited a notably large node size within the network, while MedStar Georgetown University Hospital occupied a relatively central position within its respective cluster. It should be noted that due to potential differences in institutional name standardization between the network visualization and the publication count statistics, node sizes should not be directly equated with rankings in Table 2. Cross-regional edges among different clusters indicated the presence of inter-regional collaborations in NPWT research. Overall, the author and institutional collaboration networks consistently demonstrated prominent European and U.S. research hubs with substantial participation from Asian institutions, while highlighting the pivotal roles of Swedish and American scholars in driving the field’s collaborative framework.
Core journals and highly cited papers
After identifying the core research contributors, this study further analyzed the publication platforms and milestone achievements in the NPWT field, as shown in Figure 6A. Node size corresponded to the number of publications in the NPWT field, with larger nodes indicating higher publication output; colors represented different journal clusters; and edges denoted bibliographic coupling relationships among journals based on shared references. The network comprised five major clusters. The green cluster represented the core wound care and plastic surgery cluster, with the International Wound Journal as the largest node, and also included the Journal of Wound Care, Wounds-A Compendium of Clinical Research and Practice, Plastic and Reconstructive Surgery, and Ostomy Wound Management, among other wound care and plastic surgery specialty journals. The blue cluster focused on orthopedics, trauma, and general clinical medicine, with Medicine as its largest node. The red cluster centered on general surgery and surgical infection, anchored by the Journal of Clinical Medicine. The purple cluster specializes in plastic, thoracic, and cardiothoracic surgery, with the Annals of Plastic Surgery as its core. The yellow cluster covered wound care, burns, plastic surgery, and pediatric surgery, with Advances in Skin & Wound Care as its largest node. Overall, wound care journals exhibited the greatest concentration of large nodes and closely interconnected relationships within the network.
As shown in Table 3, among the top 15 most productive journals, the International Wound Journal ranked first with 265 publications, followed by Wounds-A Compendium of Clinical Research and Practice with 192, and the Journal of Wound Care with 153. These three journals together contributed 610 publications, accounting for 15.0% of all included literature. The top five also included Plastic and Reconstructive Surgery (88) and the Annals of Plastic Surgery (82). In terms of disciplinary distribution, the top 15 journals were predominantly wound care and plastic surgery journals, with wound care journals collectively contributing 872 publications (21.5%), representing the primary publication channels for NPWT research. Regarding journal publication-country distribution, among the top 15 journals, 2 were published in the United Kingdom, while the United States accounted for 10 journals, reflecting that U.S.-based journals constituted the largest share of these publication venues. Figure 6B illustrates the direct citation relationships among these core journals.
In addition to journal-level metrics, the most influential individual publications were further examined. As shown in Table 4, the most highly cited paper was the clinical study by Argenta LC et al. (1997) published in the Annals of Plastic Surgery (TC = 1,708), which introduced vacuum-assisted closure as a new method for wound control and treatment. The second most cited work was the foundational animal study by Morykwas MJ et al. (1997), also published in the Annals of Plastic Surgery (TC = 1,654), which investigated the basic mechanisms underlying vacuum-assisted closure. The third to fifth most cited papers were published in Advances in Therapy (2017, TC = 1,641), Intensive Care Medicine (2013, TC = 1,033), and The Lancet (2005, TC = 700), covering chronic wound management, clinical practice guidelines for intra-abdominal hypertension and abdominal compartment syndrome, and NPWT after partial diabetic foot amputation, respectively. The publication years of highly cited papers ranged from 1997 to 2021, with the most recent paper addressing moist wound healing using commonly available dressings. Collectively, these findings suggested that NPWT research was anchored in a core group of wound care journals, while the most influential works span both foundational experimental and clinical studies, reviews, randomized controlled trials, and clinical guidelines that have shaped the field’s knowledge base.
As shown in Figure 6C, the co-citation network of cited references was categorized into five clusters. The red cluster, positioned mainly on the left and in the center of the network, was anchored by the 1997 study by Morykwas MJ et al., which represented one of the foundational works in the field with a notably large node size; the cluster predominantly included foundational experimental and early clinical studies, with a focus on the mechanistic basis and clinical applications of NPWT. The green cluster, situated from the center to the upper-right, encompassed research on the mechanisms and wound-repair effects of NPWT, with the 2004 study by Wackenfors A et al. as a core node, along with a series of publications by Kim PJ. The yellow cluster, located in the lower-left region, was centered on cardiothoracic applications of NPWT, with a focus on the management of sternal wound infections. The purple cluster was distributed throughout the lower part of the network and included studies on temporary abdominal closure and open-abdomen management. The blue cluster, distributed mainly on the right and lower-right, was built around the body of work by Stannard JP et al., focusing on traumatic surgical scenarios, including open fractures and surgical site infections. Overall, the network exhibited a temporal evolution from fundamental mechanistic principles toward specialized clinical applications in wound repair, trauma, cardiothoracic surgery, and open-abdomen management.
Country/region output and collaboration landscape
Country and regional outputs are shown in Figure 8. Figure 8A uses countries identified from all contributing authors' affiliations, allowing a single publication to be attributed to multiple countries. The United States ranked first, followed by China, Germany, the United Kingdom, Italy and Japan. Figure 8B uses the corresponding author’s country and classifies records as Single-Country Publications (SCP) or Multi-Country Publications (MCP). The United States led both SCP and MCP output. China ranked second in total output but had a substantially lower MCP share, indicating a comparatively low proportion of internationally coauthored publications. European and selected Asian countries produced fewer publications but were also represented among the leading countries with corresponding authors.
Because Figure 8A uses all-author affiliations and Figure 8B uses the corresponding author’s country, country totals differ between panels. SCP denotes publications whose authors were affiliated with one country; MCP denotes publications involving authors from more than one country.
Data availability
The raw Web of Science Core Collection export (Supplemental File 1), record-level screening log (Supplemental File 2), and reproducible workflow, code, and analysis-output package (Supplemental File 3) are provided with the paper. Supplemental File 3 contains the software environment, analysis parameters, scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Public redistribution and reuse of proprietary Web of Science records remain subject to Clarivate’s applicable licensing terms.
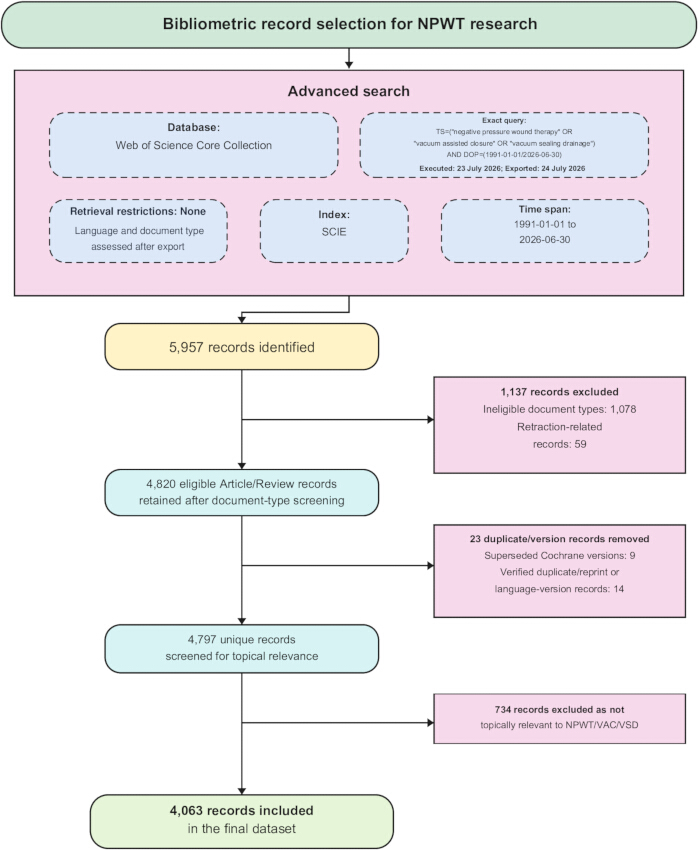
Figure 1. PRISMA-style flow diagram for the NPWT bibliometric analysis. PRISMA was used solely to display the record-selection process; this study was not conducted as a systematic review. The diagram summarizes record identification, document-type screening, topic-relevance screening, and final inclusion. The WoSCC search was conducted on 23 July 2026, and the records were exported on 24 July 2026; Early Access records were assigned to their underlying document type. Abbreviations: NPWT = negative pressure wound therapy; PRISMA = Preferred Reporting Items for Systematic Reviews and Meta-Analyses; WoSCC = Web of Science Core Collection; VAC = vacuum-assisted closure; VSD = vacuum sealing drainage. Please click here to view a larger version of this figure.
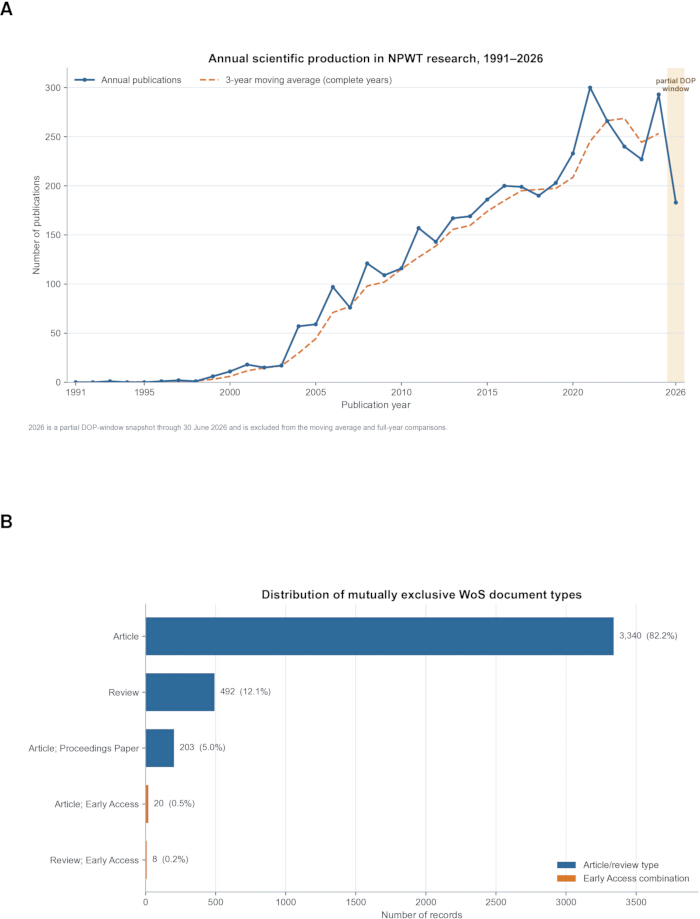
Figure 2. Annual publication output and document-type distribution of NPWT publications from 1991 to 2026. (A) Annual publication volume. (B) Article and Review categories, with Early Access status shown separately. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
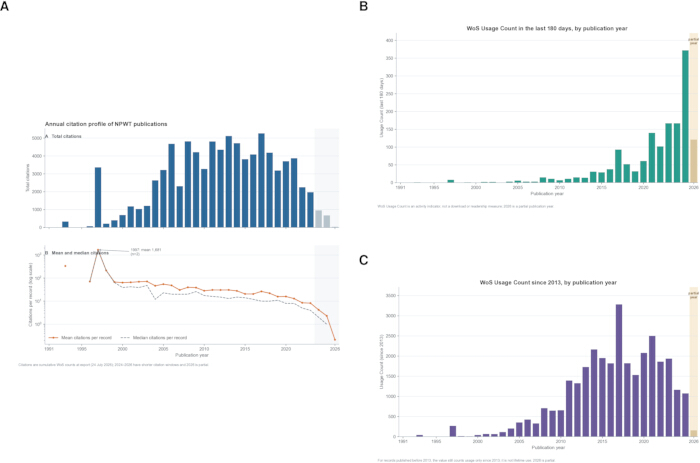
Figure 3. Citation and usage trends of NPWT publications. (A) Total, mean, and median citations by publication year. (B) Recent usage over 180 days. (C) Cumulative usage since 2013. Data were exported from WoSCC on 24 July 2026; recent cohorts have shorter citation and usage windows. Abbreviations: NPWT = negative pressure wound therapy; U1 = 180-day recent usage count; U2 = cumulative usage count since 2013; WoSCC = Web of Science Core Collection. Please click here to view a larger version of this figure.
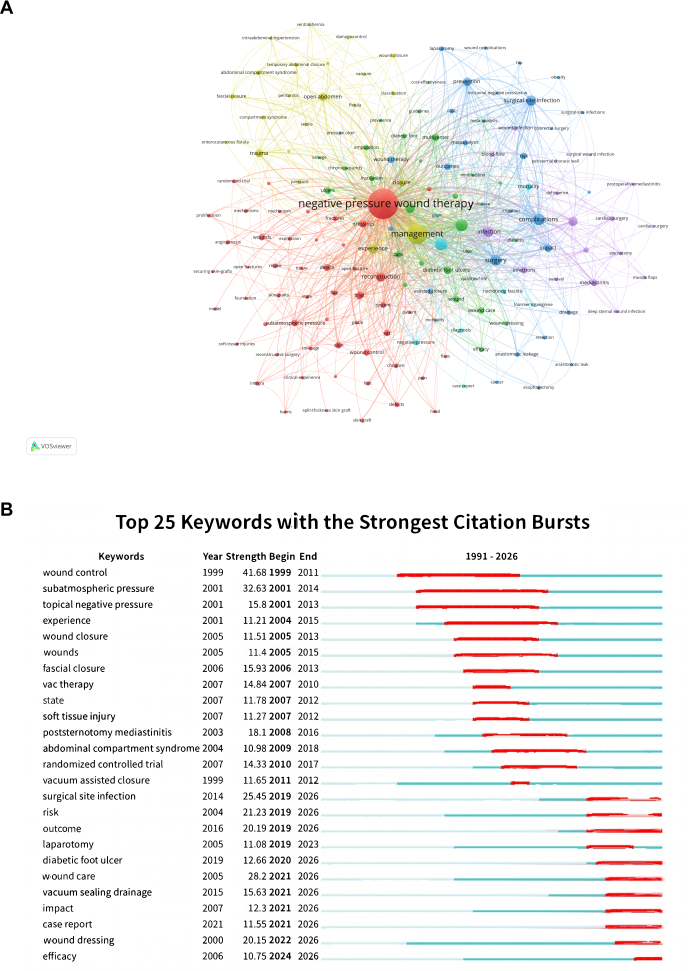
Figure 4. Keyword co-occurrence network and the top 25 burst keywords. (A) Keyword co-occurrence network using a frequency threshold of ≥30. (B) Temporal map of the 25 keywords with the strongest citation bursts. Please click here to view a larger version of this figure.
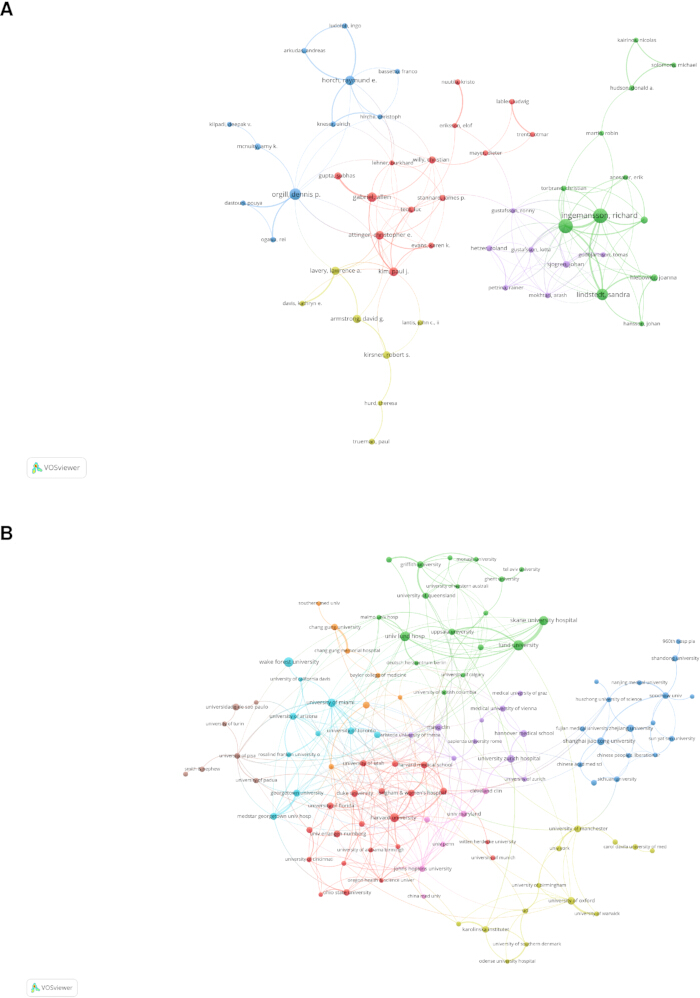
Figure 5. Author and institutional collaboration networks. (A) Core-author collaboration network, with node size proportional to publication count. (B) Institutional collaboration network. Please click here to view a larger version of this figure.
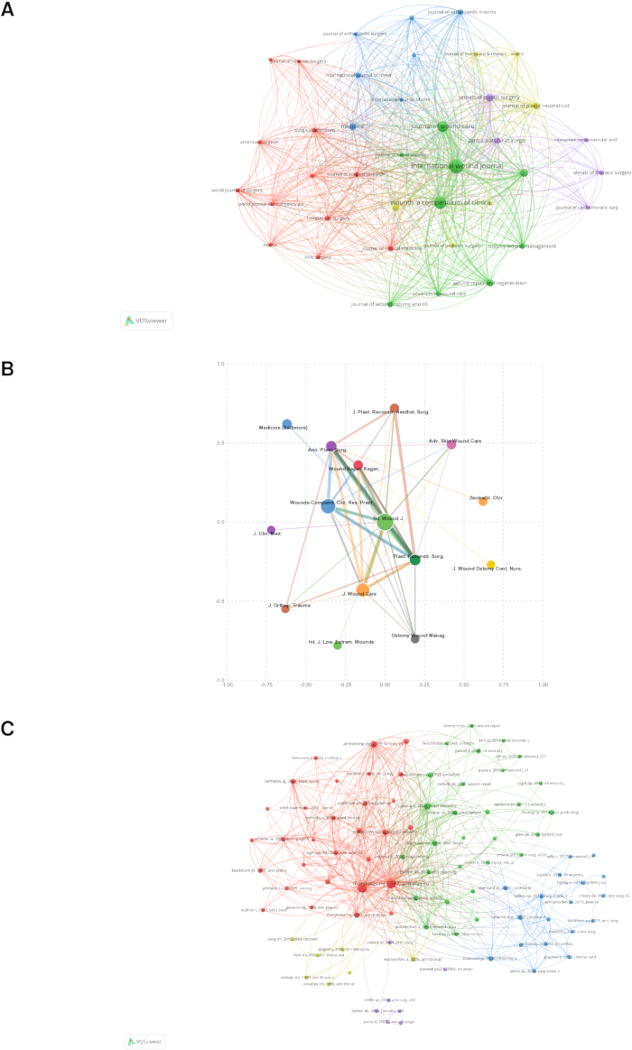
Figure 6. Publication journals and core-literature citation characteristics in NPWT research. (A) Journals with ≥20 NPWT publications. (B) Citation network of the 15 most productive journals. (C) Co-citation network of cited references. Network maps were generated using full counting. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.

Figure 7. Dual-map overlay analysis of journals in NPWT research. The left side represents citing journals, and the right side represents cited journals. Curves indicate major citation pathways; curve width reflects citation-flow strength. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
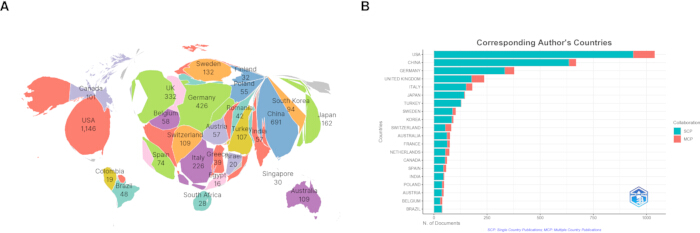
Figure 8. Global country/region output and international collaboration. (A) Publication distribution based on all author affiliations. (B) SCP and MCP distributions based on the corresponding author's country. Abbreviations: MCP = multi-country publications; SCP = single-country publications. Please click here to view a larger version of this figure.
| Rank | Author | Publications | Citations | Country |
| 1 | Ingemansson, Richard | 60 | 2747 | Sweden |
| 2 | Malmsjö, Malin | 54 | 2215 | Sweden |
| 3 | Orgill, Dennis P. | 39 | 3149 | United States |
| 4 | Horch, Raymund E. | 34 | 724 | Germany |
| 5 | Lindstedt, Sandra | 29 | 319 | Sweden |
| 6 | Gabriel, Allen | 21 | 962 | United States |
| 7 | Armstrong, David G. | 21 | 1494 | United States |
| 8 | Liu, Y | 20 | 285 | China |
| 9 | Yu, AX | 20 | 452 | China |
| 10 | Attinger, Christopher E. | 20 | 1662 | United States |
Table 1: Top 10 authors by publication output in NPWT research. The table presents publication and citation counts for the 10 most prolific authors. Abbreviations: NPWT = negative pressure wound therapy.
| Rank | Institution | Publications | Citations | Country |
| 1 | Lund University | 99 | 4291 | Sweden |
| 2 | Skane University Hospital | 94 | 4139 | Sweden |
| 3 | Harvard University | 83 | 5271 | United States |
| 4 | Harvard University Medical Affiliates | 77 | 5085 | United States |
| 5 | University of Texas System | 72 | 2540 | United States |
| 6 | University System of Ohio | 62 | 1339 | United States |
| 7 | Wake Forest University | 53 | 2975 | United States |
| 8 | Harvard Medical School | 52 | 3608 | United States |
| 9 | Brigham & Women's Hospital | 49 | 4127 | United States |
| 10 | University of California System | 46 | 1459 | United States |
Table 2: Top 10 institutions by publication output in NPWT research. The table presents publication and citation counts for the 10 most productive institutions. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Journal | Publications | Share |
| 1 | International Wound Journal | 265 | 6.52% |
| 2 | Wounds-A Compendium Of Clinical Research And Practice | 192 | 4.73% |
| 3 | Journal Of Wound Care | 153 | 3.77% |
| 4 | Plastic And Reconstructive Surgery | 88 | 2.17% |
| 5 | Annals Of Plastic Surgery | 82 | 2.02% |
| 6 | Medicine | 66 | 1.62% |
| 7 | Wound Repair And Regeneration | 64 | 1.58% |
| 8 | Advances In Skin&Wound Care | 61 | 1.50% |
| 9 | Journal Of Plastic Reconstructive And Aesthetic Surgery | 58 | 1.43% |
| 10 | Zentralblatt Fur Chirurgie | 51 | 1.26% |
| 11 | Journal Of Wound Ostomy And Continence Nursing | 48 | 1.18% |
| 12 | Ostomy Wound Management | 46 | 1.13% |
| 13 | International Journal Of Lower Extremity Wounds | 43 | 1.06% |
| 14 | Journal Of Clinical Medicine | 42 | 1.03% |
| 15 | Journal Of Orthopaedic Trauma | 41 | 1.01% |
Table 3: The 15 main journals publishing NPWT research. The table presents publication counts and shares of the complete dataset. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Title | Year | Journal | First author | Total citations | ||
| 1 | Vacuum-assisted closure:A new method for wound control and treatment:Clinical experience | 1997 | Annals Of Plastic Surgery | Argenta, LC | 1708 | ||
| 2 | Vacuum-assisted closure:A new method for wound control and treatment:Animal studies and basic foundation | 1997 | Annals Of Plastic Surgery | Morykwas, MJ | 1654 | ||
| 3 | Chronic Wound Healing:A Review of Current Management and Treatments | 2017 | Advances In Therapy | Han, G | 1641 | ||
| 4 | Intra-abdominal hypertension and the abdominal compartment syndrome:updated consensus definitions and clinical practice guidelines from the World Society of the Abdominal Compartment Syndrome | 2013 | Intensive Care Medicine | Kirkpatrick, AW | 1033 | ||
| 5 | Negative pressure wound therapy after partial diabetic foot amputation:a multicentre,randomised controlled trial | 2005 | Lancet | Armstrong, DG | 700 | ||
| 6 | Update on management of diabetic foot ulcers | 2018 | Annals Of The New York Academy Of Sciences | Everett, E | 671 | ||
| 7 | Pathogenesis and Treatment of Impaired Wound Healing in Diabetes Mellitus:New Insights | 2014 | Advances In Therapy | Baltzis, D | 587 | ||
| 8 | Vacuum-assisted closure:Micro deformations of wounds and cell proliferation | 2004 | Plastic And Reconstructive Surgery | Saxena, V | 545 | ||
| 9 | Moist Wound Healing with Commonly Available Dressings | 2021 | Advances In Wound Care | Nuutila, K | 516 | ||
| 10 | Comparison of negative pressure wound therapy using vacuum-assisted closure with advanced moist wound therapy in the treatment of diabetic foot ulcers:A multicenter randomized controlled trial | 2008 | Diabetes Care | Blume, PA | 451 | ||
Table 4: The 10 most-cited records included in the NPWT bibliometric dataset. Citation counts were exported from the Web of Science Core Collection on 24 July 2026. Abbreviation: NPWT = negative pressure wound therapy.
Supplemental File 1. Raw Web of Science Core Collection export. The records were retrieved using the reported search strategy on 23 July 2026 and exported as plain text on 24 July 2026.Please click here to download this file.
Supplemental File 2. Literature screening log for the NPWT bibliometric dataset. The spreadsheet provides record-level inclusion and exclusion decisions for the retrieved literature. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
Supplemental File 3. Reproducible workflow, code, and analysis outputs for the NPWT bibliometric dataset. The ZIP archive contains the software environment, analysis parameters, data preparation and validation scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
Discussion
The analysis identified a sustained expansion of NPWT research and a clear thematic transition from foundational mechanisms to clinical optimization18. Early studies emphasized sub-atmospheric pressure, tissue perfusion, and biological responses. For example, Morykwas et al. (1999) found that applying negative pressure to partial-thickness burns in pig models prevented wound deepening, revealing a 12-hour treatment window post-injury, with as little as 6 hours of application sufficient to stop injury progression19. Later work also addressed wound-care pathways, surgical-site infection, diabetic foot ulcers, advanced dressings20, and instillation21,22. The concordance between keyword clustering and burst detection corroborates a sequential progression of research—from mechanistic inquiry and clinical translation to dressing optimization, infection prevention, and clinical outcome evaluation 15. Methodologically, clustering reveals the static knowledge structure of the field, while burst detection captures dynamic thematic shifts; the alignment between these two dimensions strengthens the validity of the observed trajectory. Content-wise, this progression is grounded in the literature: early NPWT research centered on mechanistic exploration, exemplified by the foundational work of Morykwas and Argenta (1997). Subsequent studies increasingly addressed how dressing characteristics—such as foam pore size (400–600 µm)—influence microdeformation and cellular responses, alongside comparative assessments of single-use versus conventional canister-based systems23. Contemporary mechanistic understanding has expanded from a simplistic "increased perfusion" model toward more refined frameworks of mechanotransduction and zone-of-influence effects24. A bibliometric visualization of NPWT by Deng et al. (2024) similarly confirmed this thematic shift from fundamental mechanisms toward clinical applications and material optimization, paralleling findings in burn care research where NPWT progressively entered high-frequency keyword rankings over a 22-year period25,26. Thus, both cluster-based thematic structures and burst-detected emerging fronts converge on a clear evolutionary pathway—from understanding mechanisms to optimizing applications and refining material interventions15.
Based on the bibliometric findings, marked geographic differences were observed. China contributed substantially to the publication volume and benefited from large clinical populations and diverse wound-care settings, consistent with recent bibliometric analyses demonstrating China's leading productivity in wound-healing research, as reported by Xing et al. (2025) in a bibliometric analysis of tissue engineering applied to wound healing 27. However, its output was dominated by single-country clinical studies (SCP), while multinational collaboration, basic mechanistic research, biomaterial development, and internationally coordinated trials remained comparatively limited. By contrast, U.S. and European groups occupied central positions in long-standing cross-institutional networks and contributed more extensively to mechanistic, device-development, and multicenter research. Notably, bibliometric data on tissue engineering in wound healing show that China’s SCP/MCP ratio (1,708/343) indicates that multinational collaborations account for only a modest fraction of its total output, whereas U.S. output exhibits a higher proportion of international collaborative publications 27. Against this backdrop, China has nevertheless demonstrated progress in NPWT device innovation and international market access. Foryou Medical Electronics received U.S. FDA 510(k) clearance for its NPWT device (K113236) in 201328. In 2024, the manufacturer reported that its NPWT pumps and dressing kits had obtained certification under the European Union Medical Device Regulation from SGS29. Translating these regulatory milestones into multinational clinical investigations represents an important direction for future development.
Institutional analysis indicated that major contributors to NPWT research were concentrated in Sweden and the United States. Author productivity analysis identified Ingemansson R (60 publications) and Malmsjö M (54 publications) as the two most prolific authors, followed by Orgill DP (39 publications). These findings highlight the prominent contributions of Swedish and U.S. research groups to the NPWT field.
Journal analysis showed that NPWT research was concentrated in wound care, plastic surgery, and related clinical journals. The International Wound Journal, Wounds-A Compendium of Clinical Research and Practice, and the Journal of Wound Care were the most productive publication venues. Most journals in the top 15 were based in the United States or the United Kingdom, reflecting the prominent role of these countries in disseminating NPWT research. These findings may help researchers identify journals that regularly publish work in this field, although journal selection should also consider scope, study design, and target readership.
The most highly cited publications addressed chronic-wound management, advanced wound dressings, abdominal compartment syndrome, diabetic foot ulcers, and clinical applications of NPWT. This pattern shows that the intellectual base of the field extends beyond device-specific studies to broader wound-healing biology, clinical guidelines, and multidisciplinary wound management. Although basic protocols for NPWT have been established, uncertainty persists regarding dressing selection, optimal pressure parameters, and standardized use at specific anatomical sites.
Keyword results reinforced the same developmental sequence. Subatmospheric pressure, perfusion, and randomized trials characterized earlier phases; wound care, wound dressings, surgical-site infection, diabetic foot ulcers, and efficacy became prominent later. This shift suggests that the field is moving from proof of mechanism toward standardized clinical delivery, material innovation, and integrated wound-management strategies.
The integration of NPWT with optimized dressings and standardized wound-care protocols has become an important clinical direction. Foam and gauze dressings each have practical advantages and limitations, but high-certainty comparative evidence supporting individualized selection remains limited. Future development is likely to involve improved biomaterials, sensor-enabled systems, and more precise treatment protocols tailored to wound characteristics and patient risk.
Most publications in the dataset focused on clinical applications, treatment effectiveness, infection control, complication management, and wound-care optimization. By comparison, mechanistic research on cellular responses, molecular pathways, and material-tissue interactions was less prominent. Future studies should combine rigorous clinical trials with experimental research to clarify how NPWT influences healing and infection control. Priorities include identifying early response biomarkers, developing intelligent wound dressings, and establishing individualized treatment strategies through interdisciplinary collaboration.
Several limitations should be acknowledged. Only publications indexed in the Science Citation Index Expanded of WoSCC were included; no language restriction was applied. Relevant publications indexed exclusively in other databases may therefore have been missed. Although two trained reviewers independently screened and extracted the records, residual classification errors remain possible. Variations in author, institution, and journal names may have affected network construction despite standardization. Citation and usage indicators are time-dependent and disadvantage recent publications. Finally, bibliometric indicators describe publication patterns and influence but do not directly measure methodological quality or clinical effectiveness.
NPWT research has progressed from foundational studies of pressure, perfusion, and wound-healing mechanisms toward clinical wound care, infection prevention, advanced dressings, and outcome evaluation. International collaboration in the indexed literature was centered on U.S. and European networks. China contributed substantial publication output, while a comparatively smaller proportion of its corresponding-author publications involved international coauthorship. This finding describes the collaboration structure of the indexed literature and should not be interpreted as an assessment of research quality. Across the field, future opportunities include rigorous clinical trials, translational mechanism studies, intelligent biomaterials, standardized site-specific protocols, and broader cross-regional collaboration.
Disclosures
The authors have no conflicts of interest to declare.
Acknowledgements
This study was supported by the National Natural Science Foundation of China (Youth Program, No. 82305237), the Longyi Scholar (Seedling Program, No. YM2021025), the High-Level Key Discipline—Strengthening the Construction of Evidence-Based Traditional Chinese Medicine Research System (Anorectal Medicine of TCM), and the Shanghai Research Center for Sinus and Fistula Diseases (No. 2023ZZ02003).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| `CiteSpace 7.0.R0 (64-bit) Advanced | Chaomei Chen, Drexel University, USA | https://citespace.podia.com/ | Used for keyword burst analysis and the dual-map overlay. Settings: 1991-2026, 1-year slices, Keyword node type, Top N = 50 per slice, no pruning, and the 25 strongest burst terms. |
| Python 3.12.10; pandas 3.0.3; openpyxl 3.1.5; matplotlib 3.11.0; NetworkX 3.6.1; Microsoft Excel 16.0.20131.20154 | Python Software Foundation; pandas, openpyxl, Matplotlib, and NetworkX development teams; Microsoft Corporation | https://www.python.org/; https://pandas.pydata.org/; https://openpyxl.readthedocs.io/; https://matplotlib.org/; https://networkx.org/; https://www.microsoft.com/microsoft-365/excel | Used for screening, deduplication, data auditing, descriptive analyses, and figure generation. The final dataset contained 4,063 records. NetworkX was used for the Top-15 journal direct-citation network (15 nodes; 56 displayed edges with weights >=45). |
| R 4.6.1; bibliometrix 5.4.1; ggplot2 4.0.3 | R Foundation for Statistical Computing; Massimo Aria and Corrado Cuccurullo; ggplot2 development team | https://www.r-project.org/; https://www.bibliometrix.org/; https://ggplot2.tidyverse.org/ | Used for country/region productivity and collaboration analysis. Full counting was applied to all addresses; SCP/MCP used the corresponding author's country. Taiwan, Hong Kong, and Macao were aggregated under China at the country level only. |
| SCImago Graphica 1.0.55 | SCImago Lab | https://graphica.app/ | Used for final layout and visualization of the journal direct-citation network and country/region maps. |
| VOSviewer 1.6.21 | Centre for Science and Technology Studies (CWTS), Leiden University, the Netherlands | https://www.vosviewer.com/ | Full counting with association-strength normalization. Thresholds and final networks: keywords >=30 (158 nodes; 6,468 edges); authors >=6 documents (51; 134); institutions >=10 documents (109; 351); source journals >=20 documents (39; 741); cited references >=68 citations (91; 3,626). Unit-specific thesauri were applied. |
References
- Wu Y, Shen G, Hao C. Negative pressure wound therapy (NPWT) is superior to conventional moist dressings in wound bed preparation for diabetic foot ulcers: a randomized controlled trial. Saudi Med J. 2023;44(10):1020-9.
- Liu Z, Dumville JC, Hinchliffe RJ, Cullum N, Game F, Stubbs N, et al. Negative pressure wound therapy for treating foot wounds in people with diabetes mellitus. Cochrane Database Syst Rev. 2018;10(10):CD010318.
- Bruhin A, Ferreira F, Chariker M, Smith J, Runkel N. Systematic review and evidence-based recommendations for the use of negative pressure wound therapy in the open abdomen. Int J Surg. 2014;12(10):1105-14.
- Cirocchi R, et al. What is the effectiveness of negative pressure wound therapy (NPWT) in patients treated with open abdomen technique? A systematic review and meta-analysis. J Trauma Acute Care Surg. 2016;81(3):575-84.
- Orgill DP, Bayer LR. Negative pressure wound therapy: past, present and future. Int Wound J. 2013;10 Suppl 1:15-9.
- Robert N. Negative pressure wound therapy in orthopaedic surgery. Orthop Traumatol Surg Res. 2017;103(1 Suppl):S99-103.
- Morykwas MJ, Argenta LC, Shelton-Brown EI, McGuirt W. Vacuum-assisted closure: a new method for wound control and treatment: animal studies and basic foundation. Ann Plast Surg. 1997;38(6):553-62.
- Argenta LC, Morykwas MJ. Vacuum-assisted closure: a new method for wound control and treatment: clinical experience. Ann Plast Surg. 1997;38(6):563-76.
- Saxena V, et al. Vacuum-assisted closure: microdeformations of wounds and cell proliferation. Plast Reconstr Surg. 2004;114(5):1086-96.
- Normandin S, et al. Negative pressure wound therapy: mechanism of action and clinical applications. Semin Plast Surg. 2021;35(3):164-70.
- Kim PJ, et al. Negative pressure wound therapy with instillation: international consensus guidelines update. Int Wound J. 2020;17(1):174-86.
- Yamashiro T, et al. Negative-pressure wound therapy: what we know and what we need to know. In: Adv Exp Med Biol. 2023;1436:131-52.
- Webster J, Scuffham P, Stankiewicz M, Chaboyer WP. Negative pressure wound therapy for skin grafts and surgical wounds healing by primary intention. Cochrane Database Syst Rev. 2014;(10):CD009261.
- Norman G, et al. Negative pressure wound therapy for surgical wounds healing by primary closure. Cochrane Database Syst Rev. 2022;4(4):CD009261.
- Deng K, Yuan Z, Li D. Academic visualization and trend analysis of negative-pressure wound therapy from a global perspective. Asian J Surg. 2024;47(10):4449-51.
- Liu C, et al. Clinical study of early rehabilitation training combined with negative pressure wound therapy for the treatment of deep partial-thickness hand burns. Front Surg. 2023;10:1040407.
- Qian H, Lei T, Hu Y. Negative pressure wound therapy versus gauze dressings in managing open fracture wounds of the lower limbs: a meta-analysis of randomized controlled trials. Foot Ankle Surg. 2022;28(7):1120-8.
- Miller-Mikolajczyk C, Beach K, Silverman RP, Cooper ML. The evolution of commercial negative pressure wound therapy systems over the past three decades. Adv Wound Care (New Rochelle). 2024;13(8):375-90.
- Morykwas MJ, et al. Use of subatmospheric pressure to prevent progression of partial-thickness burns in a swine model. J Burn Care Rehabil. 1999;20(1 Pt 1):15-21.
- Tang L, et al. A biodegradable Janus sponge for negative pressure wound therapy. Biomacromolecules. 2024;25(4):2542-53.
- Agarwal P, Kukrele R, Sharma D. Vacuum-assisted closure (VAC)/negative pressure wound therapy (NPWT) for difficult wounds: a review. J Clin Orthop Trauma. 2019;10(5):845-8.
- Apelqvist J, et al. EWMA document: negative pressure wound therapy. J Wound Care. 2017;26 Suppl 3:S1-S154.
- Malmsjö M, Huddleston E, Martin R. Biological effects of a disposable, canisterless negative pressure wound therapy system. Eplasty. 2014;14:e15.
- Orgill DP, Bayer LR. Update on negative-pressure wound therapy. Plast Reconstr Surg. 2011;127 Suppl 1:105S-15S.
- Li Y, et al. Metabolic response to burn injury: a comprehensive bibliometric study. Front Med (Lausanne). 2024;11:1451371.
- Zhou Y, et al. Frontiers and hotspots in burn wound healing: a visualized bibliometric analysis. Regenesis Repair Rehabil. 2026;2(1):54-64.
- Xing Y, Huang Z, Cao L. Application of tissue engineering in wound healing: a 20-year bibliometric and visualized study. Medicine (Baltimore). 2025;104(35):e43008.
- U.S. Food and Drug Administration. 510(k) Premarket Notification K113236: Foryou NPWT Device. Updated February 12, 2013. Cited 2026 Jul 26. Available from: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfPMN/pmn.cfm?ID=K113236
- 4L Health Co. Ltd., Foryou Medical Electronics Co. Ltd. The first in China: Foryou NPWT entire product line for the EU market has obtained MDR certification. Updated July 2, 2024. Cited 2026 Jul 26. Available from: https://foryounpwt.com/NewsEvents/News_20240702.html