This study integrates a scenario experiment and electroencephalograms to examine how expert and companion role framing is associated with trust across medical task contexts.
Method Article
Role Framing and Trust in Medical AI: Evidence from a Scenario Experiment and EEG
In This Article
Summary
Abstract
Online medical AI has evolved from back-end analytical tools to patient-facing service interfaces, making calibrated trust an increasingly important design and governance problem. Drawing on role congruity theory, this study examined how expert and companion role framing is associated with trust across medical task contexts. Study 1 used a 2 (role: expert vs. companion) × 2 (task: illness consultation vs. health consultation) scenario experiment (N = 300). Expert framing increased perceived professionalism, whereas companion framing increased social presence; both perceptions were independently associated with overall trust when entered simultaneously. The indirect association through professionalism was conditioned by task context, but a direct bootstrap comparison did not show that the two moderated-mediation indices differed for overall trust. Measurement diagnostics indicated substantial overlap between perceived professionalism and cognitive trust and between social presence and affective trust, requiring cautious interpretation. Study 2 compared expert- and companion-framed statements using EEG in 39 paired observations. Expert framing was accompanied by higher frontal-midline theta ERS and a less negative baseline-corrected FCz-F6 theta ΔPLV, while condition-level behavior showed no reliable difference in trust rate, response time, or missing-response rate. These EEG findings are exploratory process-level correlates rather than neural validation of the conditional indirect model. Overall, role cues appear to shape nonexclusive competence-oriented and relationship-oriented evaluations. Role design should support calibrated reliance through capability boundaries, communication of uncertainty, risk-based warnings, and appropriate escalation, rather than simply maximizing trust.
Introduction
Medical AI now spans back-end applications such as image recognition, pathology analysis, and drug discovery, as well as patient-facing service interfaces. Industry analyses project continued healthcare AI market growth through 20331. Large language models enable medical AI systems to answer health questions, interpret test results, summarize information, and provide recommendations in natural language2. This shift changes the user's relationship with the technology. A back-end analytical tool is evaluated by clinicians and organizations, whereas a patient-facing interface must communicate its role, evidence, uncertainty, and limits to users. Medical AI may appear as a diagnostic assistant, a family-doctor interface, or a health-management companion, and each can shape how users understand the system's service identity. As these systems increasingly participate in illness consultation and everyday health management, trust becomes more than an attitude toward technology. It affects whether users disclose information, consider recommendations credible, interact with the system, and act on health guidance. Trust is therefore a central design and governance concern for digital health platforms.
Technical capability alone does not determine whether users regard medical AI as credible and acceptable. Reviews of healthcare conversational agents show that implementation depends on interaction quality, clinical relevance, transparency, and deployment conditions3. Recent work on credible evidence for medical AI likewise argues that model performance is insufficient unless claims are supported by evidence appropriate to the intended use4. Transparency is essential because patients must be able to identify capability boundaries, uncertainty, and the basis of a recommendation rather than infer reliability from fluent language alone5. Information-systems research similarly frames adoption of AI-assisted diagnosis as a trust-configuration problem in which interpretability, privacy protection, and interface cues jointly shape acceptance6. These considerations are important for language-model interfaces. Fluency can make an answer easy to understand while leaving unresolved whether the system has clinical knowledge, whether its recommendation applies to the user's circumstances, and when escalation to a qualified clinician is necessary. The relevant question is not only whether medical AI can produce an answer, but whether users can evaluate it with an appropriate level of reliance.
Trust in medical AI is sensitive to task context. Research on resistance to medical AI shows that users may reject algorithmic recommendations in high-stakes decisions because they believe an algorithm cannot account for their uniqueness7. Resistance is not universal. Algorithm-appreciation research indicates that people may prefer algorithmic judgment when tasks are objective and rules are clearer8. In online health consultation, personalization and carefulness in AI-generated advice affect trust and adoption9. Discrete-choice research comparing conventional, digital, and AI-based consultations likewise finds that preferences and trust expectations vary across formats10. Human-AI teaming can also reduce resistance through trust transfer from human expertise to an AI-supported service arrangement11. Trust in medical AI, therefore, develops through the interaction of perceived risk, task demands, communication style, and system evaluation. Illness consultation makes uncertainty, possible loss, diagnostic consequences, and error costs salient. Health consultation more often concerns diet, exercise, sleep, adherence, and preventive management, where sustained interaction and relational accessibility may carry greater weight. The same interface cue may consequently be interpreted differently when a user seeks help with a possible illness rather than longer-term health management.
Role framing is one interface feature through which these expectations can be communicated. Medical AI may be framed as an expert that emphasizes professional authority, structured reasoning, clinical boundaries, and capability evidence, or as a companion that emphasizes empathy, reassurance, social support, and continuity. This distinction relates to competence and warmth, the two dimensions of social perception, but is not simply a choice between a competent system and a warm system12. Communication style and agency framing influence evaluations of conversational agents13. In mobile medical applications, social cues and privacy concerns jointly affect trust and behavioral intention14. Anthropomorphic cues in healthcare conversational agents can increase social presence, trust, and acceptance, although they may also create expectations that exceed system capabilities15. Research on human-AI teams further shows that warmth and competence predict different forms of receptivity16. In high-risk tasks, trust depends on the fit among team role, task context, and performance violation17. Consistency between a chatbot's social role and performance also affects trust building and repair18. Expert and companion cues, therefore, make different evaluative standards salient rather than merely changing conversational tone.
Two gaps remain. First, research has not explained how the relevance of competence- and relationship-oriented cues changes with medical task demands. Reviews of human trust in AI emphasize context dependence but do not clarify how expert and companion cues operate across illness and health consultations19. Second, studies of trust in medical AI rely on self-reports, providing limited evidence about the processing associated with role-framed evaluation. Privacy, transparency, accountability, and bias also constrain interpretation of front-end role cues20,21. To address these gaps, this study draws on role congruity theory, which explains evaluation through alignment between role cues and context-salient demands22. Study 1 uses a randomized 2 (role: expert vs. companion) x 2 (task: illness consultation vs. health consultation) scenario experiment (N = 300) to examine role framing, task context, and parallel indirect associations through perceived professionalism and social presence. Study 2 uses a separate within-subjects EEG experiment (N = 39) to compare theta-band activity in response to expert- and companion-framed statements. Study 1 evaluates behavioral associations and contextual moderation; Study 2 provides an exploratory process-level comparison rather than a neural validation of the conditional indirect model.
Theoretical framework and hypothesis development
Role framing in medical AI
Medical AI operates in high-stakes settings involving disease risk, treatment recommendations, liability, and ethical boundaries23. Role framing, therefore, matters because front-end language can make the boundaries of capability, evidence, and responsibility more or less salient to users. Transparency research likewise emphasizes that medical AI systems should communicate capability limits and evidence bases5. Expert-style responses convey competence through formal terminology, structured reasoning, boundary statements, and action recommendations, whereas companion-style responses convey relational support through empathy, reassurance, and collaborative wording. These cues are not merely interface decoration: they shape the standards users apply when evaluating a system24,25. Anthropomorphism can elicit social responses but may also create unrealistic expectations and blur liability boundaries26,27. Research on human-AI teams and chatbots further indicates that warmth, competence, role-context fit, and consistency between social role and performance influence acceptance and trust16,17,18. In this study, role congruity refers to the alignment between cues conveyed by an AI response and the evaluative demands salient in the consultation task22.
Dual-path trust: Perceived professionalism and social presence
Role congruity is inferred from the observed role-by-task interaction rather than measured as a separate subjective construct. The interpretation is therefore bound to the experimental interaction and does not imply that participants consciously reported a feeling of role fit. Trust involves cognitive judgments about competence and reliability and affective judgments about relational security and comfort28,29,30. In medical AI use, users assess both whether the system can support a health decision and whether interaction with it feels sufficiently secure and accessible. Expert framing should make competence-oriented evaluation more salient. Evidence from clinical decision-support research indicates that explanations and information about system reasoning affect trust and reliance31. In online health consultations, personalization and care are also associated with trust and acceptance9. Perceived professionalism captures a competence-oriented evaluation relevant to trust25. Research on online health consultation likewise identifies source credibility as relevant to users' acceptance of health suggestions32. The present study, therefore, tests whether expert framing is associated with higher perceived professionalism.
H1: Companion roles generate lower perceived professionalism compared with expert-style Medical AIs.
Companion framing should make relational evaluation more salient. Social presence refers to the perceived interpersonal quality of mediated interaction rather than a belief that the system is human33. It is associated with interaction quality, trust, and acceptance in online services and health conversational agents15,34.
Social presence may reduce the psychological cost of self-disclosure and support information exchange during online consultation32. The present study, therefore, tests whether companion framing is associated with higher social presence.
H2: Expert roles generate lower social presence compared with companion-style Medical AIs.
Perceived professionalism and social presence are treated as parallel, nonexclusive associations with trust. Proper reliance on high-stakes automation depends on system capabilities, boundaries, and task requirements rather than on maximizing trust alone35.
H3: Perceived professionalism and social presence each positively predict trust when modeled simultaneously.
Moderating effect of task context
The same role cues may carry different psychological weight across medical tasks. Task-technology fit provides a contextual rationale for examining whether role cues align with task requirements36. Illness consultation involves higher uncertainty, loss risk, and error costs, making professionalism, accuracy, and clear boundaries especially salient7,37. Expert cues should therefore be more closely aligned with these demands than companion cues. Health consultation centers on long-term health management, behavioral persistence, and continuity of interaction. Reviews of AI-based clinical decision support and health conversational agents emphasize the importance of contextual information, actionability, interaction, and implementation conditions3,38,39.
This study predicts that the expert-companion difference in perceived professionalism will be larger in illness consultation than in health consultation. It does not treat a nonsignificant interaction on social presence as evidence of invariance. The hypothesis is proposed as follows:
H4: Task context significantly moderates the impact of expert roles on perceived professionalism. The impact is stronger in illness consultation than in health consultation.
Protocol
Research overview
The study was conducted in accordance with the Declaration of Helsinki and was approved by the Ethics Committee of Huaqiao University (M2025021), which covered both the online scenario experiment and the EEG experiment. All participants provided informed consent and received compensation upon completion.
This paper contains two complementary studies (see Figure 1). Study 1 is a randomized 2 × 2 scenario experiment that estimates role-framing and task-context effects, evaluates the measurement structure, and tests parallel conditional indirect associations through perceived professionalism and social presence. Study 2 is a within-subjects EEG experiment that compares theta-band activity under expert- and companion-framed statements and is interpreted as an exploratory process-level comparison. The studies provide behavioral and neural evidence at different levels; they are not treated as a single progressive mechanism.
Study 1: Scenario experiment
Participants and design
Study 1 used a balanced 2 × 2 between-subjects design with role framing (expert vs. companion) and task context (illness consultation vs. health consultation). The original G*Power calculation assumed a medium omnibus ANOVA effect (f = 0.25), α = .05, and power = .80, and indicated a minimum of 128 participants40. Because that calculation was not tailored to conditional indirect effects, it is reported as the original recruitment basis rather than as power evidence for moderated mediation. With N = 300 and four balanced cells, a sensitivity analysis indicated 80% power to detect an interaction of f = 0.162 (partial η2 = .026) at α = .05.
We additionally conducted a post hoc simulation-based power analysis for the moderated-mediation indices using the 300-case SPSS questionnaire dataset. The simulation generated 1,000 balanced 2 × 2 samples from the fitted parallel-mediator model by resampling empirical residuals; each simulated dataset used 500 case-resampled percentile-bootstrap confidence intervals. The estimated probabilities that the confidence interval excluded zero were .698 for the professionalism index, .157 for the social-presence index, and .279 for the direct difference between the two indices. This analysis is conditional on the observed coefficients, residual distributions, and model specification and is not an a priori sample-size justification. The complete post hoc simulation-based power analysis is presented in Supplementary Table S1.
Three hundred participants were recruited through Credamo and randomly assigned to four conditions (n = 75 per cell). The sample included 109 men (36.3%) and 191 women (63.7%); 43.7% were aged 21-30 years, 41.3% were aged 31-40 years, and 69.7% held a bachelor's degree. All required questionnaire items were completed. No dedicated attention-check item or preregistered completion-time exclusion was used, and no participant was excluded. Median completion time was 268 s (range = 67-1,894 s). A post hoc robustness analysis excluding responses below the fifth percentile of completion time (<125 s; retained n = 285) assessed sensitivity to unusually rapid responding. Detailed manipulation-check statistics and completion-time sensitivity analyses are reported in Supplementary Table S2.
Experimental stimuli and procedure
The stimulus materials consisted of a task-scenario introduction and an AI-doctor dialogue response, forming four complete experimental sets. The illness consultation scenario asked participants to imagine recurrent nocturnal chest tightness and palpitations, and concern about whether immediate hospital care was required. The health consultation scenario asked participants to imagine being in generally good health and seeking a personalized diet and exercise plan. Each task category was represented by one scenario; conclusions are therefore restricted to these two scenarios rather than generalized to all illness and health consultations.
All four questionnaire screenshots used the same icon and displayed the system name, Medical AI (DiagnosPro), thereby holding the displayed identity constant across conditions. Expert-framed responses used structured analysis, risk or evidence statements, directive language, and explicit action recommendations. Companion-framed responses used empathy, reassurance, collaborative wording, and flexible suggestions. The manipulation, therefore, represented a package of role-congruent communication and informational cues; it did not isolate role framing from specificity, actionability, certainty, medical detail, or emotional support. The shared name DiagnosPro may also have conveyed an expert cue across all conditions. The complete set of stimuli is provided in Supplementary File 1.
Participants first read the informed consent form and were then randomly assigned to one of four experimental conditions. After reading the scenario and dialogue stimulus, they completed the questionnaire based on their responses. The questionnaire began with manipulation checks, followed by measures of perceived professionalism, social presence, trust, and demographics. The procedure took approximately 15 min.
All scales used 7-point Likert scoring, with 1 representing strongly disagree and 7 representing strongly agree. Perceived professionalism was measured with three items: ‘This medical AI is capable of providing medical advice,’ ‘This medical AI seems very professional,’ and ‘This medical AI is an expert in the medical field’ (α = .883)41. Social presence was measured with three items: ‘In the interaction with this medical AI, I felt a human touch,’ ‘The interaction with this medical AI made me feel close,’ and ‘This medical AI seemed sociable during the interaction’ (α = .932)42. Cognitive trust comprised three items: ‘I can rely on this medical AI because it has the skills needed to provide advice,’ ‘I am confident in the accuracy of the advice provided by this medical AI,’ and ‘This medical AI has sufficient capability to handle my health problem’ (α = .837). Affective trust comprised three items: ‘This medical AI makes me feel warmth and care,’ ‘Relying on this medical AI makes me feel safe because it seems to care about my health,’ and ‘I believe this medical AI would not intentionally do anything harmful to me’ (α = .700). Overall trust was the mean of all six trust items (α = .784). These measures were analyzed as competence-oriented, interpersonal, cognitive-trust, affective-trust, and overall-trust outcomes rather than as mutually exclusive constructs.
The analysis proceeded in four steps. First, confirmatory factor analysis compared the proposed four-factor model with two-factor and one-factor alternatives; composite reliability, average variance extracted, latent correlations, and heterotrait-monotrait ratios were examined. Second, full 2 x 2 factorial models estimated main and interaction effects for perceived professionalism, social presence, cognitive trust, affective trust, and overall trust, with cell means, confidence intervals, and partial η2. The estimated marginal means and 95% confidence intervals are shown in Figure 2. Third, PROCESS 4.2 beta Model 7 entered perceived professionalism and social presence simultaneously as parallel mediators, with 5,000 percentile-bootstrap samples43. Role framing was coded 1 = expert and 2 = companion, and task context was coded 1 = illness consultation and 2 = health consultation. A common-resample bootstrap directly contrasted with the two indices of moderated mediation. Fourth, cognitive and affective trust were analyzed separately as exploratory outcomes. Because mediators and outcomes were measured concurrently, the estimates are interpreted as indirect associations consistent with mediation rather than as causal psychological mechanisms.
Study 2: EEG experiment
Participants
Study 2 recruited 40 participants. One participant was excluded because artifact-contaminated trials exceeded 30% in at least one experimental condition, leaving 39 participants in the final EEG analyses. This criterion ensured that every retained participant contributed at least 70% of the trials in each condition. All participants provided written informed consent and received compensation after the experiment. Demographic information could not be linked to all retained EEG records and is therefore not summarized for the final EEG sample.
Experimental stimuli and procedure
The experiment was conducted in a standard EEG laboratory using a within-subjects design, with stimuli presented in E-Prime 2.1. Participants were instructed to imagine interacting with a medical AI system and to assess their trust in the system for each medical consultation scenario. The experiment manipulated the perceived role of the medical AI system, including expert-type and companion-type variants.
A total of 40 Chinese sentence stimuli were constructed. The expert-type condition contained 20 stimuli beginning with ‘Medical AI expert,’ whereas the companion-type condition contained 20 parallel stimuli beginning with ‘Medical AI companion.’ The medical scenarios covered both professional diagnostic functions, such as asking about medical history, analyzing examination reports, assessing heart-rate data, interpreting genetic tests, judging disease risk, and recommending treatment plans, and supportive health-management functions, such as showing concern for physical condition, asking about sleep quality, relieving anxiety, recording health data, encouraging treatment adherence, and providing daily health tips. The conditions, therefore, also differed in semantic content and complexity; no independent stimulus matching or pretest was available.
Before the formal experiment, participants completed a short practice block. Each trial began with a 500 ms fixation cross, followed by a jittered blank interval of 300–500 ms and a Medical AI statement presented for 1,600 ms. Participants then made a self-paced binary trust judgment by pressing the F key to indicate trust or the J key to indicate no trust (see Figure 3). Expert- and companion-framed statements were presented in randomized order. The E-Prime task logs indicated 80 formal trials per task record: 40 expert and 40 companion trials, with each of the 20 unique statements per role presented twice.
Behavioral task data
Behavioral task data were usable for 38 of the 39 participants in the final EEG sample; one participant's E-Prime task record was unusable. Behavioral analyses, therefore, used N = 38. Detailed behavioral outcomes and sample accounting are provided in Supplementary Table S3. Trust was coded as an F-key response; J-key responses indicated non-trust. Blank responses or a recorded response time of 0 ms were coded as missing. Trust rate was calculated among answered trials, and response time was summarized over answered trials. The neural data available for analysis contained condition-aggregated measures but no trial-level EEG indices or verified identifier linking each behavior record to its EEG record; therefore, no trial-level mixed model of EEG and trust judgments was estimated.
EEG recording and analysis
Quik-Gel conductive electrolyte gel was used to maintain electrode-skin impedance below 5 kOhm. FCz was the device’s default online reference, and the sampling rate was 1,000 Hz. Offline referencing the average of the bilateral mastoids was performed with CURRY’s built-in rereferencing function; FCz was retained and automatically reconstructed relative to the new reference, and no custom reconstruction command or script was used. Subsequent offline processing was performed in MATLAB R2020b with EEGLAB44 and ICLabel45. Data were downsampled to 500 Hz and band-pass filtered from 0.1 to 40 Hz. Bad channels and grossly contaminated data segments were identified and removed by visual inspection; no automated interpolation or automated segment-rejection threshold was applied. The default EEGLAB runica implementation (Infomax ICA) was then used, and components were removed when ICLabel assigned a probability of at least .70 to an artifact class (e.g., eye, muscle, cardiac, line-noise, or channel-noise activity). Participants with more than 30% artifact-contaminated trials in either condition were excluded, ensuring at least 70% trial retention in each condition. Epochs spanned −1,000 to 1,996 ms. For functional connectivity analysis, the preprocessed data were further downsampled to 250 Hz, and peripheral electrodes, including P7, P8, F7, and F8, were excluded prior to phase-synchrony estimation.
Theta activity recorded at frontal-midline scalp sites has been associated with computations engaged by cognitive-control demands46. Theta-band phase synchronization between medial and lateral frontal electrode sites has also been associated with coordination during control-related processing47. In particular, enhanced theta-band phase synchronization between sites such as FCz and F6 has been observed following conflict or error detection48. Because these scalp measures are not uniquely specific to cognitive control, they are treated here as convergent process indicators rather than direct readouts of a single cognitive mechanism.
First, frontal-midline theta event-related synchronization (ERS) was quantified in the 4–8 Hz band within the 800–1,000 ms poststimulus window. ERS was calculated using time-frequency analysis, with the relative power change computed relative to the −500 to −200 ms prestimulus baseline. Positive values indicate power enhancement (synchronization), whereas negative values indicate power suppression (desynchronization). Second, functional connectivity was estimated after further downsampling the preprocessed data to 250 Hz and excluding peripheral electrodes, including P7, P8, F7, and F8. A short-time Fourier transform (STFT) was applied before calculating the theta-band phase-locking value between FCz and F6. The baseline-corrected PLV change (ΔPLV) was computed relative to the −600 to −200 ms prestimulus baseline. Raw PLV is bounded between 0 and 1; therefore, negative ΔPLV values indicate a decrease relative to baseline rather than negative phase locking. These scalp measures are interpreted as exploratory patterns associated with control-related processing and prefrontal coordination; they do not directly identify a specific cognitive process or neural source.
Results
Study 1: Scenario-experiment results
Measurement model. The four-factor model fit better than the two-factor and one-factor alternatives, but the absolute fit was mixed: χ2(48) = 223.93, p < .001; CFI = .935; TLI = .911; RMSEA = .111; SRMR = .140. Standardized loadings ranged from .382 to .937. Composite reliability was .886 for perceived professionalism, .932 for social presence, .840 for cognitive trust, and .709 for affective trust; corresponding AVE values were .722, .821, .636, and .474. Discriminant validity was limited: HTMT values were .935 between perceived professionalism and cognitive trust, and .926 between social presence and affective trust. Conditional-process findings are therefore interpreted cautiously, and dimension-specific trust analyses are exploratory (Table 1).
Manipulation checks. Expert-framing participants (n = 150, M = 5.57, SD = 1.18) rated the Medical AI as more expert-like than companion-framing participants (n = 150, M = 3.21, SD = 1.76). Because variances differed, F = 47.42, p < .001, Welch’s test was used, t(259.90) = 13.63, p < .001, mean difference = 2.36, 95% CI [2.02, 2.70]. Illness-condition participants (n = 150, M = 2.51, SD = 1.53) gave lower preventive-health orientation ratings than health-condition participants (n = 150, M = 5.98, SD = 1.22), F = 10.96, p = .001; Welch’s t(284.11) = −21.70, p < .001, mean difference = −3.47, 95% CI [−3.79, −3.16]. Welch degrees of freedom are not equal to N − 2 when variances are unequal; all analyses used N = 300.
Descriptive statistics by experimental condition. For expert framing, illness and health consultation produced perceived-professionalism means of 5.69 (SD = 0.83) and 5.85 (SD = 0.63), social-presence means of 4.28 (SD = 1.54) and 4.25 (SD = 1.64), and overall-trust means of 5.45 (SD = 0.86) and 5.28 (SD = 0.87), respectively. For companion framing, corresponding illness and health means were 4.52 (SD = 1.47) and 5.25 (SD = 0.94) for perceived professionalism, 5.68 (SD = 1.07) and 5.93 (SD = 0.74) for social presence, and 5.30 (SD = 1.02) and 5.61 (SD = 0.64) for overall trust. Table 2 reports all condition-specific confidence intervals and the complete factorial tests.
Complete factorial results. Perceived professionalism showed a role-framing main effect, F(1, 296) = 56.92, p < .001, partial η2 = .161, a task-context main effect, F(1, 296) = 14.37, p < .001, partial η2 = .046, and a role × task interaction, F(1, 296) = 5.89, p = .016, partial η2 = .020. Social presence showed a role-framing main effect, F(1, 296) = 105.57, p < .001, partial η2 = .263, but neither the task main effect, F(1, 296) = 0.59, p = .442, nor the interaction, F(1, 296) = 0.84, p = .359, was significant. This latter result indicates that moderation was not detected; it does not establish equivalence across tasks. For cognitive trust, the role × task interaction was significant, F(1, 296) = 5.60, p = .019, partial η2 = .019; the corresponding interaction was not significant for affective trust, F(1, 296) = 3.48, p = .063, partial η2 = .012. Overall trust showed no role-framing main effect, F(1, 296) = 0.81, p = .369, or task main effect, F(1, 296) = 0.55, p = .459, but the role × task interaction was significant, F(1, 296) = 5.78, p = .017, partial η2 = .019. In illness consultation, overall trust did not differ between companion and expert framing, mean difference = −0.15, SE = 0.14, t(296) = −1.06, p = .288, 95% CI [−0.42, 0.13]. In health consultation, overall trust was higher under companion framing, mean difference = 0.33, SE = 0.14, t(296) = 2.34, p = .020, 95% CI [0.05, 0.60].
Parallel conditional indirect associations. When perceived professionalism and social presence were entered simultaneously, both were positively associated with overall trust: b = 0.4872, SE = 0.0258, p < .001, 95% CI [0.4294, 0.5460], and b = 0.3293, SE = 0.0208, p < .001, 95% CI [0.2762, 0.3829], respectively. The direct role-framing association was not significant, b = 0.0119, SE = 0.0680, p = .861, 95% CI [−0.1071, 0.1361]. Professionalism indirect associations were −0.5695 in illness consultation, 95% bootstrap CI [−0.7687, −0.3851], and −0.2923 in health consultation, 95% bootstrap CI [−0.4288, −0.1634]. Social-presence indirect associations were 0.4625 in illness consultation, 95% bootstrap CI [0.3165, 0.6091], and 0.5532 in health consultation, 95% bootstrap CI [0.3855, 0.7383] (Table 3). The index of moderated mediation through perceived professionalism was 0.2772, 95% bootstrap CI [0.0594, 0.5035], whereas the index through social presence was 0.0907, 95% bootstrap CI [−0.0984, 0.3008]. The direct bootstrap contrast between the indices was not significant, difference = 0.1864, 95% bootstrap CI [−0.0856, 0.4447]. The results therefore support contextual moderation of the indirect association with professionalism, but do not establish statistically different contextual moderation of the two associations.
Exploratory trust-dimension analyses. For cognitive trust, the contrast between the professionalism and social-presence moderated-mediation indices was positive, difference = 0.3707, 95% bootstrap CI [0.0493, 0.6996]. For affective trust, the corresponding contrast was not supported, difference = 0.0022, 95% bootstrap CI [−0.3421, 0.3127]. Both mediators retained positive associations with both trust dimensions, indicating cross-path rather than exclusive effects. Given the high HTMT values, these results should not be interpreted as definitive separation of cognitive and affective mechanisms.
Post hoc moderated-mediation power. Under the fitted model and residual-resampling assumptions, the estimated probability that the percentile-bootstrap confidence interval excluded zero was .698 for the professionalism index, .157 for the social-presence index, and .279 for their direct difference (1,000 simulations; 500 bootstrap resamples per simulation). These observed-design estimates explain why the supported professionalism index and the nonsignificant direct contrast should not be interpreted as conclusive evidence of different contextual moderation.
Completion-time robustness. Excluding the 15 responses below 125 s, 285 cases remained. The overall-trust interaction remained significant, p = .029; the professionalism index remained supported, 95% bootstrap CI [0.0242, 0.4827]; and the contrast between moderated-mediation indices remained nonsignificant, 95% bootstrap CI [−0.1027, 0.4506]. The principal conclusions were not dependent on the fastest 5% of responses.
Study 2: EEG results
Frontal-midline theta ERS. In the final analytic sample (N = 39), theta ERS in the 4–8 Hz, 800–1,000 ms window was higher under expert framing (M = 0.2948, SD = 0.8218) than companion framing (M = −0.0422, SD = 1.2155), mean difference = 0.3369, 95% CI [0.0125, 0.6614], t(38) = 2.10, p = .042, Cohen’s dz = 0.337, partial η2 = .104. The Holm-adjusted p-value for the two reported paired EEG outcomes was .042. This difference indicates differential theta-band processing in this task window; theta ERS alone does not identify a specific psychological process.
FCz-F6 baseline-corrected theta PLV change (ΔPLV). In the final analytic sample (N = 39), theta ΔPLV was less negative under expert framing (M = −0.0111, SD = 0.0546) than companion framing (M = −0.0350, SD = 0.0473), mean difference = 0.0239, 95% CI [0.0058, 0.0420], t(38) = 2.68, p = .011, Cohen’s dz = 0.429, partial η2 = .159. The Holm-adjusted p value across the two reported paired EEG outcomes was .022. This pattern represents a smaller decrease in theta phase consistency from baseline under expert framing; it does not by itself establish stronger prefrontal control or a specific cognitive mechanism (see Figure 4 and Table 4).
Behavioral task results. In the 38 analyzed task records, the trust-response rate was 83.1% (SD = 15.8%) under expert framing and 82.4% (SD = 17.5%) under companion framing, mean difference = 0.7 percentage points, 95% CI [−0.9, 2.4], t(37) = 0.91, p = .371, dz = 0.147. Mean response times were 828.7 ms (SD = 204.6) and 826.1 ms (SD = 208.9), respectively, mean difference = 2.5 ms, 95% CI [−14.0, 19.1], t(37) = 0.31, p = .758, dz = 0.050. Missing-response rates were 6.3% (SD = 7.4%) and 5.2% (SD = 6.3%), respectively, mean difference = 1.1 percentage points, 95% CI [−1.0, 3.1], t(37) = 1.05, p = .302, dz = 0.170.
Data Availability Statement:
De-identified Study 1 questionnaire data, preprocessed EEG files, and aggregate EEG output files supporting Study 2 are publicly available on the Open Science Framework (OSF) at https://doi.org/10.17605/OSF.IO/JKSP7. Supplementary materials include the complete experimental stimuli (Supplementary File 1), manipulation checks, additional behavioral analyses, post hoc power analyses, and supporting methodological information.
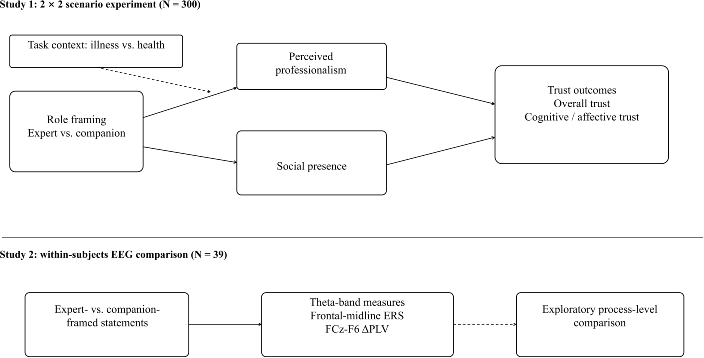
Figure 1. Research framework. Study 1 is a 2 × 2 scenario experiment (N = 300) examining role framing, task context, and parallel indirect associations through perceived professionalism and social presence. Study 2 provides an exploratory electroencephalogram comparison of expert- and companion-framed statements (N = 39); it does not directly test the conditional indirect model. Please click here to view a larger version of this figure.
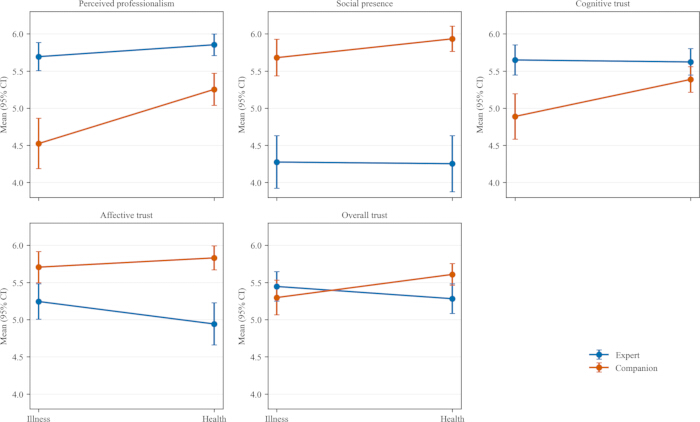
Figure 2. Role-framing × task-context plots for perceived professionalism, social presence, cognitive trust, affective trust, and overall trust. Points show cell means, and error bars show 95% confidence intervals (n = 75 per cell). Please click here to view a larger version of this figure.
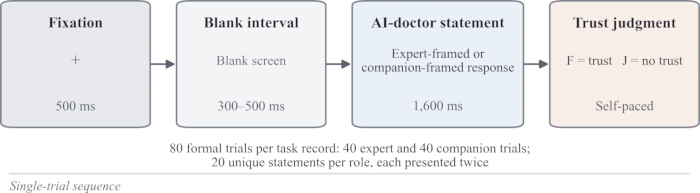
Figure 3. Single-trial sequence in Study 2. Each trial comprised a 500 ms fixation, a jittered 300–500 ms blank interval, a 1,600 ms expert- or companion-framed AI-doctor statement, and a self-paced binary trust judgment. The E-Prime task logs indicated 80 formal trials per task record, with 40 trials per role-framing condition and two presentations of each of the 20 unique statements per condition. Please click here to view a larger version of this figure.
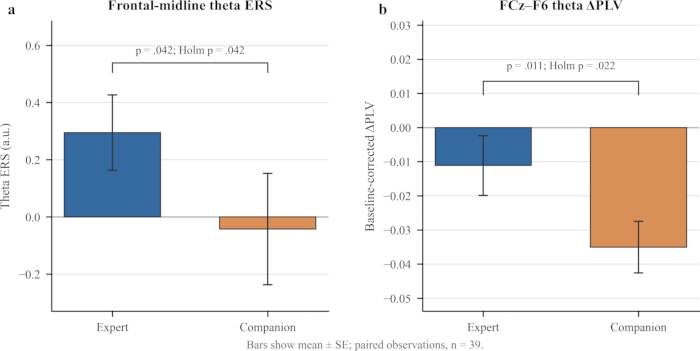
Figure 4. Effects of Medical AI role framing on frontal-midline theta ERS and FCz-F6 theta delta PLV. (A) Frontal-midline theta event-related synchronization. (B) Baseline-corrected FCz-F6 theta phase-locking-value change (ΔPLV); negative values denote a decrease from the pre-stimulus baseline. Bars show mean ± SE for n = 39. Paired t tests yielded p = .042 for theta ERS and p = .011 for ΔPLV; Holm-adjusted p values across these two reported outcomes were .042 and .022, respectively. Abbreviations: Please click here to view a larger version of this figure.
Table 1: Measurement-model diagnostics for Study 1. The table reports standardized loadings, Cronbach’s α, composite reliability, average variance extracted, latent correlations, and HTMT values for perceived professionalism, social presence, cognitive trust, and affective trust. N = 300. The four-factor model fit better than the alternatives, but RMSEA and SRMR indicated weak absolute fit and two HTMT values exceeded .90. Abbreviations: CR = composite reliability; AVE = average variance extracted; HTMT = heterotrait-monotrait ratio. Please click here to download this Table.
Table 2: Four-condition descriptive statistics and complete 2 × 2 factorial tests for Study 1. Cell entries report n, mean, standard deviation, and 95% confidence interval; factorial tests report F, p, and partial η2. N = 300; n = 75 per cell. Role framing was coded 1 = expert and 2 = companion; task context was coded 1 = illness and 2 = health consultation. Coefficients and confidence intervals are unstandardized. Please click here to download this Table.
Table 3: Parallel conditional indirect associations in Study 1. N = 300. Role framing was coded 1 = expert and 2 = companion; task context was coded 1 = illness consultation and 2 = health consultation. Perceived professionalism and social presence were entered simultaneously. Estimates are unstandardized, and percentile-bootstrap confidence intervals used 5,000 resamples. The table includes conditional indirect associations, both indices of moderated mediation, and their direct bootstrap contrast. The direct contrast between the two moderated-mediation indices for overall trust was 0.1864, 95% CI [-0.0856, 0.4447]. Please click here to download this Table.
Table 4: Paired EEG outcomes in Study 2. N = 39 paired observations in the final analytic sample. The table reports condition means, paired mean differences, 95% confidence intervals, paired t tests, Cohen’s dz, partial η2, and Holm-adjusted p values for frontal-midline theta ERS and baseline-corrected FCz-F6 theta ΔPLV. Holm correction covers only the two reported paired EEG outcomes and does not reconstruct any undocumented wider search over electrodes, bands, or time windows. Please click here to download this Table.
Supplementary File 1: Experimental stimuli used in Study 1. The file contains the complete text of the expert-framed and companion-framed medical AI responses used in the illness-consultation and health-consultation scenarios. Both the original Chinese and the English translation are provided.Please click here to download this file.
Supplementary Table S1. Post hoc simulation-based power analysis for the moderated-mediation model. Please click here to download this file.
Supplementary Table S2. Manipulation-check statistics and completion-time sensitivity analyses for Study 1. Please click here to download this file.
Supplementary Table S3. Behavioral task outcomes, sample accounting, and descriptive statistics for Study 2. Please click here to download this file.
Discussion
Theoretical implications
The two studies provide evidence at different levels. Study 1 identifies role-by-task associations and parallel indirect associations in a randomized scenario experiment, whereas Study 2 provides an exploratory process-level EEG comparison. The studies, therefore, support a bounded account of role-framed evaluation rather than a single progressive mechanism. The findings extend role congruity theory to medical AI by treating congruity as the alignment between role cues and task-salient evaluative demands22. This interpretation is distinct from competence-warmth content and task-technology fit. Algorithm-aversion and algorithm-appreciation findings can be understood as context-sensitive evaluations of whether role and capability cues fit the task49,50.
The results also support parallel, nonexclusive associations between role framing, perceived professionalism, social presence, and trust. Because professionalism overlaps with cognitive trust and social presence overlaps with affective trust, the evidence supports differentiated evaluative content but not two cleanly separated mechanisms. The role-by-task interaction on perceived professionalism is consistent with the proposed role-congruity account. The evidence supports contextual moderation of the association with professionalism, but it does not establish statistically asymmetric contextual mechanisms or invariance in the social-presence pathway.
The EEG findings provide an exploratory process-level perspective. Expert-framed statements were accompanied by distinct theta-band patterns, but the conditions also differed in semantic content and complexity, and condition-level behavior showed no reliable difference in trust. The EEG measures, therefore, do not establish a distinct cognitive-control or trust mechanism. The neural findings should be treated as hypothesis-generating. Study 2 did not manipulate task context, measure perceived professionalism or social presence, or link trial-level EEG indices to trust judgments; the EEG results, therefore, complement rather than validate the conditional indirect model.
The findings are compatible with appropriate, rather than maximum, reliance. Automated-system reliance should be calibrated to system capabilities, boundaries, and task requirements35. Related work describes adaptive cognitive mechanisms that may support calibrated trust and reliance51. The NeuroIS perspective supports the use of neural measures as complements to behavioral evidence when examining temporally resolved processes52. Prior fMRI work also shows that neural activity during online trust judgments varies across targets and contexts53.
Managerial implications
For online medical platforms, the practical implication is calibrated reliance rather than simple trust maximization. Role cues should be matched to task demands and combined with uncertainty communication, explicit capability limits, risk-based warnings, and escalation to qualified clinicians.
In high-risk modules involving diagnosis, interpretation of abnormal results, medical advice, or triage, competence-oriented cues may help users recognize the boundaries of evidence and action without conferring unwarranted authority. In lower-urgency modules such as diet, exercise, sleep, adherence, and emotional support, relationship-oriented cues may support engagement without creating false reassurance or inappropriate anthropomorphism.
Role design should be modular and scenario-based rather than a fixed personality setting. Role configuration should be integrated with explanation, privacy prompts, risk labels, and escalation mechanisms. Governance research emphasizes that transparency, accountability, bias management, and privacy must be designed together so that credible front-end role cues do not conceal back-end risks6,20,21.
Research limitations and future directions
Study 1 is a scenario experiment rather than a real consultation. The conditions were not independently pretested on length, word frequency, readability, accuracy, actionability, emotional valence, arousal, risk, familiarity, or complexity. Future studies should use multiple scenarios, neutral system names, content-matched stimuli, independent manipulation or temporally separated measurement, and participant- and stimulus-level random effects.
Study 2 provided process-level EEG evidence, but the final 39-person demographic linkage was incomplete, the EEG statements were not independently matched or pretested on sentence length, word frequency, readability, emotional valence, arousal, perceived risk, familiarity, and complexity, and explicit role labels may have created demand characteristics. The present study used baseline-corrected phase-locking value (ΔPLV) as the predefined measure of functional connectivity. Although the weighted phase lag index (wPLI) is less sensitive to volume conduction, it was not included in the original analysis pipeline. Future studies should examine whether the present findings are replicated using wPLI or other complementary connectivity measures. The available neural outputs are condition-aggregated and cannot be linked to trial-level trust judgments; a trial-level EEG-behavior mixed model was therefore not estimated. Scalp PLV is also sensitive to common-reference and volume-conduction effects. These limitations mean that neural findings should remain exploratory and should not be interpreted as evidence for a unique cognitive-control or trust mechanism.
Disclosures
The authors have no conflicts of interest to declare.
During the preparation of this work, the authors used ChatGPT to improve language. After using this tool/service, the authors reviewed and edited the content as needed and take full responsibility for the publication's content.
Acknowledgements
This research project was supported by the National Social Sciences Funded General Projects, PRC (Grant No. 22BGL006).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Credamo online survey platform | Credamo (Jianshu), China | Not applicable | Online questionnaire, random assignment, and participant recruitment platform used in Study 1. |
| CURRY rereferencing function | Compumedics Neuroscan, USA | Version not specified | Built-in offline rereferencing from the FCz online reference to the bilateral mastoid average; FCz was automatically reconstructed relative to the new reference. |
| EEG electrode cap, 64-channel | Compumedics Neuroscan (Compumedics Limited), Australia | Model/catalog number not specified | 64-channel Ag/AgCl electrode cap used for continuous EEG recording. |
| EEGLAB | Swartz Center for Computational Neuroscience, University of California San Diego, USA | Version 2023.0 | MATLAB toolbox used for EEG preprocessing and independent component analysis. |
| E-Prime | Psychology Software Tools, Inc., USA | Version 2.1 | Stimulus presentation and response collection in Study 2. |
| G*Power | Heinrich Heine University Dusseldorf, Germany | Version 3.1.9.7 | Original a priori sample-size calculation, interaction-sensitivity analysis, and post hoc model-based power analysis for Study 1. |
| IBM SPSS Statistics | IBM Corp., USA | Version 27 | Statistical environment used to run the PROCESS macro. |
| ICLabel | Swartz Center for Computational Neuroscience, University of California San Diego, USA | Version 1.7 | EEGLAB plugin used to classify artifactual independent components. |
| MATLAB | The MathWorks, Inc., USA | Release R2020b | Computing environment used for EEG processing and analysis. |
| PROCESS macro for SPSS | Andrew F. Hayes, Canada | Version 4.2 beta | Model 7 with perceived professionalism and social presence entered simultaneously as parallel mediators, using 5,000 percentile bootstrap samples in Study 1. |
| Quik-Gel conductive electrolyte gel | Compumedics Neuroscan (Compumedics Limited), Australia | Catalog number not specified; 32 oz | Conductive gel used to reduce electrode-skin impedance during EEG recording. |
| SynAmps2 EEG amplifier | Compumedics Neuroscan (Compumedics Limited), Australia | SynAmps2; catalog number not specified | 64-256-channel EEG amplifier configured for 64-channel recording. |
References
- Grand View Research. Artificial intelligence in healthcare market size & share, industry report, 2033 [Internet]. Grand View Research; [cited 2026 Jul 11]. Available from: https://www.grandviewresearch.com/industry-analysis/artificial-intelligence-ai-healthcare-market
- Singhal K, et al. Large language models encode clinical knowledge. Nature. 2023;620(7972):172-80.
- Laranjo L, et al. Conversational agents in healthcare: a systematic review. J Am Med Inform Assoc. 2018;25(9):1248-58.
- Kouzy R, Hong JC, Bitterman DS. One shot at trust: building credible evidence for medical artificial intelligence. Lancet Digit Health. 2025;7(7):100883.
- Kim C, Gadgil SU, Lee SI. Transparency of medical artificial intelligence systems. Nat Rev Bioeng. 2026;4(1):11-29.
- Bian X, Chen Y, Yang A. Configuring trust in AI-augmented healthcare: the role of AI interpretability and data privacy in patient adoption of AI-assisted diagnosis. Int J Inf Manage. 2026;88:103039.
- Longoni C, Bonezzi A, Morewedge CK. Resistance to medical artificial intelligence. J Consum Res. 2019;46(4):629-50.
- Logg JM, Minson JA, Moore DA. Algorithm appreciation: people prefer algorithmic to human judgment. Organ Behav Hum Decis Process. 2019;151:90-103.
- Qin H, et al. Examining the impact of personalization and carefulness in AI-generated health advice: trust, adoption, and insights in online healthcare consultations experiments. Technol Soc. 2024;79:102726.
- Mayer CJ, et al. User preferences and trust in hypothetical analog, digitalized and AI-based medical consultation scenarios: an online discrete choice survey. Comput Human Behav. 2024;161:108419.
- Du G, Zhou C, Cheng X. Reducing consumers’ resistance to AI agents in online healthcare consultations: the role of human-AI teaming from a trust transfer perspective. J Bus Res. 2026;206:115959.
- Fiske ST, Cuddy AJC, Glick P, Xu J. A model of often mixed stereotype content: competence and warmth respectively follow from perceived status and competition. J Pers Soc Psychol. 2002;82(6):878-902.
- Araujo T. Living up to the chatbot hype: the influence of anthropomorphic design cues and communicative agency framing on conversational agent and company perceptions. Comput Human Behav. 2018;85:183-9.
- Zhang J, Luximon Y, Li Q. Seeking medical advice in mobile applications: how social cue design and privacy concerns influence trust and behavioral intention in impersonal patient-physician interactions. Comput Human Behav. 2022;130:107178.
- Li Q, Luximon Y, Zhang J. The influence of anthropomorphic cues on patients’ perceived anthropomorphism, social presence, trust building, and acceptance of health care conversational agents: within-subject web-based experiment. J Med Internet Res. 2023;25:e44479.
- Harris-Watson AM, et al. Social perception in human-AI teams: warmth and competence predict receptivity to AI teammates. Comput Human Behav. 2023;145:107765.
- Schelble BG, et al. Addressing the role of context on trust in human-AI teams: the influence of team role and violation type in high-risk tasks. Ergonomics. 2025. doi:10.1080/00140139.2025.2570300.
- Mou Y, Ye X, Ma W. Building and repairing trust in chatbots: the interplay between social role and performance during interactions. Behav Sci (Basel). 2026;16(1):118.
- Glikson E, Woolley AW. Human trust in artificial intelligence: review of empirical research. Acad Manage Ann. 2020;14(2):627-60.
- Luo Y, Li S, Ye Q, Zheng J. How privacy calculus builds user engagement through trust in AI medical consultation. Electron Mark. 2025;35(1):50.
- Nouis SCE, Uren V, Jariwala S. Evaluating accountability, transparency, and bias in AI-assisted healthcare decision-making: a qualitative study of healthcare professionals’ perspectives in the UK. BMC Med Ethics. 2025;26(1):89.
- Eagly AH, Karau SJ. Role congruity theory of prejudice toward female leaders. Psychol Rev. 2002;109(3):573-98.
- Laï MC, Brian M, Mamzer MF. Perceptions of artificial intelligence in healthcare: findings from a qualitative survey study among actors in France. J Transl Med. 2020;18(1):14.
- Feine J, Gnewuch U, Morana S, Maedche A. A taxonomy of social cues for conversational agents. Int J Hum Comput Stud. 2019;132:138-61.
- Mayer RC, Davis JH, Schoorman FD. An integrative model of organizational trust. Acad Manage Rev. 1995;20(3):709-34.
- Nass C, Moon Y. Machines and mindlessness: social responses to computers. J Soc Issues. 2000;56(1):81-103.
- Epley N, Waytz A, Cacioppo JT. On seeing human: a three-factor theory of anthropomorphism. Psychol Rev. 2007;114(4):864-86.
- McAllister DJ. Affect- and cognition-based trust as foundations for interpersonal cooperation in organizations. Acad Manage J. 1995;38(1):24-59.
- McKnight DH, Choudhury V, Kacmar C. Developing and validating trust measures for e-commerce: an integrative typology. Inf Syst Res. 2002;13(3):334-59.
- Johnson D, Grayson K. Cognitive and affective trust in service relationships. J Bus Res. 2005;58(4):500-7.
- Bussone A, Stumpf S, O’Sullivan D. The role of explanations on trust and reliance in clinical decision support systems [conference paper]. Presented at: 2015 International Conference on Healthcare Informatics; 2015. p. 160-9. doi:10.1109/ICHI.2015.26.
- Li Y, Chen L, Fu L. Vicarious interaction in online health consultation service: the effects of generative AI’s anthropomorphism and social support on intended responses through social presence and source credibility. Int J Hum Comput Interact. 2025;41(17):11209-26.
- Short J, Williams E, Christie B. The social psychology of telecommunications. John Wiley & Sons; London; 1976.
- Gefen D, Straub DW. Consumer trust in B2C e-commerce and the importance of social presence: experiments in e-products and e-services. Omega. 2004;32(6):407-24.
- Lee JD, See KA. Trust in automation: designing for appropriate reliance. Hum Factors. 2004;46(1):50-80.
- Goodhue DL, Thompson RL. Task-technology fit and individual performance. MIS Q. 1995;19(2):213-36.
- Castelo N, Bos MW, Lehmann DR. Task-dependent algorithm aversion. J Mark Res. 2019;56(5):809-25.
- Parsons CS, et al. Task-technology fit of artificial intelligence-based clinical decision support systems: a review of qualitative studies. BMC Med Inform Decis Mak. 2025;25(1):397.
- Wutz M, Hermes M, Winter V, Köberlein-Neu J. Factors influencing the acceptability, acceptance, and adoption of conversational agents in health care: integrative review. J Med Internet Res. 2023;25:e46548.
- Faul F, Erdfelder E, Lang AG, Buchner A. G*Power 3: a flexible statistical power analysis program for the social, behavioral, and biomedical sciences. Behav Res Methods. 2007;39(2):175-91.
- Tadros FJ, et al. Perceived professionalism of a dietitian is not influenced by attire or white coat: a prospective, randomized online study. Top Clin Nutr. 2021;36(3):231-41.
- Shams G, Kim KK, Kim K. Enhancing service recovery satisfaction with chatbots: the role of humor and informal language. Int J Hosp Manag. 2024;120:103782.
- Hayes AF. Introduction to mediation, moderation, and conditional process analysis: a regression-based approach. 3rd ed. Guilford Press; New York; 2022.
- Delorme A, Makeig S. EEGLAB: an open source toolbox for analysis of single-trial EEG dynamics including independent component analysis. J Neurosci Methods. 2004;134(1):9-21.
- Pion-Tonachini L, Kreutz-Delgado K, Makeig S. ICLabel: an automated electroencephalographic independent component classifier, dataset, and website. Neuroimage. 2019;198:181-97.
- Cavanagh JF, Frank MJ. Frontal theta as a mechanism for cognitive control. Trends Cogn Sci. 2014;18(8):414-21.
- Buzzell GA, et al. Adolescent cognitive control, theta oscillations, and social observation. Neuroimage. 2019;198:13-30.
- Cavanagh JF, Cohen MX, Allen JJB. Prelude to and resolution of an error: EEG phase synchrony reveals cognitive control dynamics during action monitoring. J Neurosci. 2009;29(1):98-105.
- Dietvorst BJ, Simmons JP, Massey C. Algorithm aversion: people erroneously avoid algorithms after seeing them err. J Exp Psychol Gen. 2015;144(1):114-26.
- Jussupow E, Benbasat I, Heinzl A. An integrative perspective on algorithm aversion and appreciation in decision-making. MIS Q. 2024;48(4):1575-90.
- Lebiere C, Blaha L, Fallon C, Jefferson BA. Adaptive cognitive mechanisms to maintain calibrated trust and reliance in automation. Front Robot AI. 2021;8:652776.
- Dimoka A, et al. On the use of neurophysiological tools in IS research: developing a research agenda for NeuroIS. MIS Q. 2012;36(3):679-702.
- Riedl R, Hubert M, Kenning P. Are there neural gender differences in online trust? An fMRI study on the perceived trustworthiness of eBay offers. MIS Q. 2010;34(2):397-428.