This article presents a “cranial-first” laparoscopic right hemicolectomy technique with complete mesocolic excision. Early results from 86 cases suggest that the approach is safe and feasible, achieving adequate lymph node yield with acceptable perioperative outcomes.
Method Article
Laparoscopic Right Hemicolectomy Using A Cranial-First Approach: Technical Description and Early Outcomes
In This Article
Summary
Abstract
There are various surgical approaches for laparoscopic radical right hemicolectomy. However, the Henle’s trunk and middle colic vessels often reveal anatomical variations, and improper handling may lead to vascular injury. This protocol presents a “cranial-first” approach combined with complete mesocolic excision (CME) to attempt to overcome the aforementioned technical difficulties. 86 cases were collected from September 2023 to April 2026. First, the gastrocolic ligament was opened to expose the right gastroepiploic vessels and the pancreatic head. The colic branches of Henle’s trunk and the middle colic vein (MCV) were dissected and ligated along the inferior border of the pancreas. Dissection then continued caudally along the superior mesenteric vein (SMV) and laterally along the retroperitoneal plane to the duodenum. Second, a medial approach was adopted. The assistant lifted the transverse and the ileocolic mesocolon. The peritoneum was incised between the jejunal origin and the ileocolic projection. The lymphatic and adipose tissue on the superior mesenteric artery (SMA) and SMV surface was dissected medially to laterally. The middle colic artery (MCA) or its right branch and the ileocolic vessels were ligated. Finally, the ileocecal mesentery was incised, and the right mesocolon was completely mobilized along Toldt’s space. The median operative time was 182.0 min, the blood loss was 45.0 ml, and the number of lymph node dissections was 28.0. The median time to flatus was 3.0 days, and the postoperative hospital stay was 6.0 days. Wound infection occurred in 4 patients, and ileus occurred in 2 patients, but no postoperative death occurred. Preliminary results indicated that this approach was safe and feasible.
Introduction
Since its introduction and rapid acceptance in 19911, laparoscopic radical right hemicolectomy (LRRH) has been consistently associated with reduced intraoperative blood loss, lower postoperative morbidity, and shorter hospital stay compared with open surgery, while achieving comparable long-term oncological outcomes2. In 2009, Hohenberger et al.3 first proposed the concept of complete mesocolic excision (CME) with central vascular ligation for colon cancer. Subsequently, several authors have reported superior survival outcomes with this approach compared with conventional laparoscopic techniques4.
Meanwhile, LRRH remains technically difficult due to the complex anatomical layers of the right mesocolon, the abundance of adjacent structures, and the frequent vascular variations in Henle’s and the surgical trunk region. Previous studies on the cranial approach have two patterns: one is to open the gastrocolic ligament without addressing Henle’s trunk or the middle colic vessels5,6, and the other is to partially ligate the colic branches of Henle’s trunk7,8,9. Early identification of the gastroepiploic and colic vessels allows tracing of Henle’s trunk and the SMV, facilitating anatomical dissection of these key structures. Matsuda et al.10have made preliminary attempts at the cranial approach, reporting management of the tributary veins of Henle’s trunk as well as the middle colic artery and vein (MCA and MCV). However, in clinical practice, achieving root ligation of the MCA through the cranial approach is often difficult, and it offers no significant advantage over the caudal approach, particularly when only the right branch of the MCA needs to be ligated.
In light of these difficulties, this study introduces an approach that prioritizes cranial-side dissection and manipulation, termed “cranial-first LRRH”. This approach reduces surgical difficulty, clearly delineates the anatomical plane, and improves the efficacy of lymph node dissection, thereby providing a new method for the standard procedure of LRRH. This approach offers some advantages in obese patients. The present study described in detail the specific procedural steps involved in this technique to evaluate its applicability in clinical practice.
Protocol
The research was performed in compliance with the institutional guidelines of the human research ethics committee at Guangdong Provincial Hospital of Chinese Medicine (Approval No. ZE2025-345-01). The study was approved by the local Institutional Review Board and performed in accordance with the Declaration of Helsinki. Written informed consent was waived due to the retrospective design. The study flow diagram is presented in Figure 1.
1. Patient selection
- Inclusion criteria
- Confirm right-sided colon adenocarcinoma by preoperative colonoscopic biopsy.
- Verify that the tumor is located in the right hemicolon using preoperative computed tomography (CT).
- Include patients with stage I–III disease.
- Include patients who underwent laparoscopic radical right hemicolectomy (LRRH). Do not exclude patients solely because of a high body mass index (BMI), previous abdominal surgery, or T4b disease.
- Exclusion criteria
- Exclude patients who underwent an open surgical approach or conversion to open surgery. Exclude patients with non-adenocarcinoma histology.
- Exclude patients with preoperative intestinal obstruction requiring emergency surgery, a history of right hemicolectomy, or multiple primary cancers necessitating total colectomy or multisegment resection.
2. Surgical preparation and operative principles
NOTE: Conversion to open surgery was defined as a conversion performed before complete mobilization of the right mesocolon. Standard right hemicolectomy was generally performed for tumors in the ileocecal region or ascending colon and involved routine dissection of group 223 lymph nodes, preservation or right-branch ligation of the middle colic artery (MCA), and either ligation or preservation of the middle colic vein (MCV). Extended right hemicolectomy was typically performed for tumors at the hepatic flexure or in the right transverse colon and included group 223 lymphadenectomy and ligation of both the MCA and MCV. All procedures were performed by Dr. Diao Jingfang, the chief surgeon, who had completed the learning curve for the cranial-first approach.
- Ascertain the tumor location before opening the gastrocolic ligament. Position the patient with the head elevated and the feet lowered.
- Use a combination of sharp and blunt dissection when dissecting the major vessels, pancreas, and duodenum. Exercise care to avoid inadvertent injury to these structures.
- Perform D3 lymph node dissection in all cases to achieve a more complete central lymph node dissection. Extend the dissection boundary to the midline of the superior mesenteric artery (SMA) or its left side.
NOTE: Assess the integrity of the postoperative surgical specimen according to the West grading system4. Classify postoperative complications according to the Clavien–Dindo classification11.
3. Preparation before the laparoscopy procedure
- Induce general anesthesia followed by routine disinfection and sterile draping.
- Make a 1-cm longitudinal skin incision 5 cm below the umbilicus. Insert a 10-mm trocar through it to establish pneumoperitoneum with a pressure of 12–15 mmHg.
- Place a 12-mm trocar at the intersection of the left midaxillary line and a point 2 cm above the umbilicus as the primary operating port. Insert a 5-mm trocar at the junction of the left midclavicular line and a point 4 cm below the umbilicus.
- Position two additional 5-mm trocars symmetrically on the contralateral side to the operator's trocar (Figure 2).
4. Operating procedures for the cranial approach
- In the reverse Trendelenburg position with left tilt (head high, feet low, left lateral tilt), enter the omental sac through the left side of the middle part of the gastrocolic ligament, then to the right side (Figure 3A).
- Simultaneously, divide the adhesions between the transverse mesocolon and the posterior gastric wall, and lower (mobilize downward) the transverse mesocolon (Figure 3B).
- Enter the plane between the gastric mesentery and transverse mesocolon, anterior to the gastroepiploic vascular arch. Expose the RGEV, continue mobilizing the transverse mesocolon downward, and fully expose the descending duodenum and pancreatic head (Figure 3C).
- Dissect and ligate, one at a time, the 1–2 accessory right colic veins (aRCVs; also known as superior right colic veins) draining into the right gastroepiploic vein (RGEV) during opening of the plane. Preserve the RGEV unless infrapyloric lymph node dissection is required (Figure 3D).
- Incise the adhesions between the transverse mesocolon and the gallbladder or liver, and flip the transverse mesocolon caudally (toward the feet) (Figure 3E).
- Along the lower border of the pancreas, incise the attachment of the transverse mesocolon from left to right, layer by layer, expose the superior mesenteric vein (SMV) and the confluence of Henle’s trunk, then dissect the SMV caudally to locate the entry point of the MCV. Dissect and ligate the MCV (Figure 3F).
- Continue to flip the transverse mesocolon, exposing the anterior pancreaticoduodenal space down to the lower border of the horizontal portion of the duodenum. Dissect and ligate the right colic vein (RCV) if it is present (Figure 3G).
- Simultaneously, extend the right retrocolic space to the right, accurately expose Gerota’s fascia, and completely flip the right mesocolon up to the ileocecal region.
- Use a gauze pad as a guide (Figure 3H).
5. Middle turning-page style lymphadenectomy
- Maintain a reverse Trendelenburg position with the head elevated and feet lowered. Lift the middle colic vascular pedicle with the assistant’s left hand and retract the ileocolic vascular pedicle with the right hand to provide appropriate tension (Figure 4A).
- Make a longitudinal incision above or to the left side of the SMA at the junction of the colonic mesentery and small bowel mesentery. Identify the ileocolic artery (ICA), right colic artery (RCA, highly variable and frequently absent), and MCA. Dissect the ICA or RCA, when present, and ligate the identified arteries at their roots. Determine MCA management according to tumor location and bowel perfusion (Figure 4B).
- After ligating the MCA or its right branch, create a communication with the cranial space anterior to the SMV. Continue to extend the right retrocolic space caudally and laterally anterior to the horizontal portion of the duodenum (Figure 4C).
- Transect the omentum and the transverse mesocolon, then divide the transverse colon (Figure 4D,E).
- Identify and ligate the ileocolic vein (ICV) to the right of the SMV. If the ICA courses posterior to the SMV, ligate the vein first, followed by the artery (Figure 4F).
- Continue to divide the ileal mesentery to the planned small bowel transection site, and then divide the small intestine (Figure 4G).
- Apply countertraction to the right colonic mesentery and ileal mesentery. Continue developing the retrocecal space and open the lateral peritoneum to completely mobilize the right retrocolic space (Figure 4H).
6. Anastomosis and specimen extraction methods
- Before performing the intracorporeal anastomosis, inspect the surgical field for bleeding (Figure 5C).
- Perform an intracorporeal isoperistaltic side-to-side anastomosis using a 60-mm linear stapler with blue cartridges, and close the common entry site using a 3-0 running barbed suture (close the intestinal wall with a continuous full-thickness suture, followed by a seromuscular imbricating suture) (Figure 5A,B,D).
- Make a 5-cm longitudinal midline incision in the upper abdomen above the umbilicus, insert a wound protector, and extract the specimen.
- Routinely place a drainage tube in the subhepatic space to drain fluid and facilitate detection of possible chylous or anastomotic leakage.
Results
No conversions to open surgery occurred. Baseline characteristics of the 86 patients are summarized as follows: 40 patients were male, and 46 were female. The median age was 63.0 (45.0–76.0) years, and the median BMI was 23.5 (21.2–28.8) kg/m2. Tumor locations included the ileocecal region (n = 10), ascending colon (n = 36), hepatic flexure (n = 29), and right transverse colon (n = 11). Preoperative clinical staging revealed 12 patients with stage I, 50 with stage II, and 24 with stage III disease. The median operative time was 182.0 (160.0–210.0) min, and the median intraoperative blood loss was 45.0 (15.0–50.0) mL. All specimens were resected en bloc and classified by pathologists as being in the mesocolic plane. The median number of harvested lymph nodes was 28.0 (18.0–32.0). The favorable perioperative outcomes, including shorter operative time, minimal blood loss, and adequate lymph node yield, demonstrated the successful execution of the procedure in all cases.
Postoperative recovery was acceptable, with a median time to flatus of 3.0 (2.0–4.0) days, a median postoperative hospital stay of 6.0 (5.0–10.0) days, and a median abdominal drainage duration of 4.0 (3.0–6.0) days. Postoperative short-term outcomes were assessed within 30 days after surgery through telephone interviews or outpatient visits. The follow-up rate was 100%. Follow-up outcomes included postoperative complications, readmission rate, and mortality within 30 days. Superficial wound infection occurred in 4 patients and ileus in 2 patients, both of which were managed conservatively and resolved prior to discharge (all Clavien–Dindo grade II). The overall postoperative complication rate was 7.0% (6/86). These complications were common to gastrointestinal surgery and not specifically related to this technique, nor were they unique to it. No readmissions or deaths were recorded. These findings further support the perioperative safety of this surgical approach (Table 1).
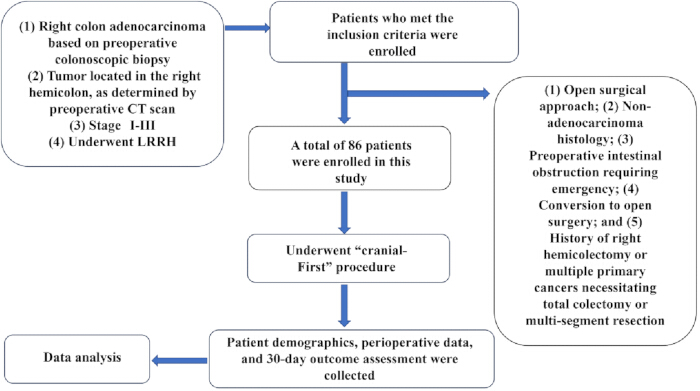
Figure 1: Study design flow diagram. After applying the inclusion and exclusion criteria, 86 patients underwent the cranial-first approach, and their perioperative data were collected for analysis. Please click here to view a larger version of this figure.
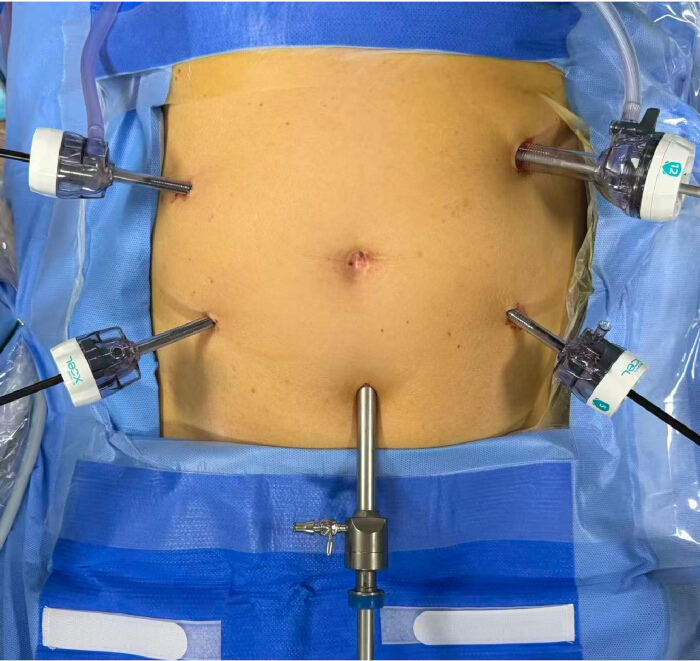
Figure 2: Preoperative configuration of laparoscopic trocar placement. A 1-cm longitudinal skin incision was made 5 cm below the umbilicus, through which a 10-mm trocar was inserted to establish pneumoperitoneum with a pressure of 12–15 mmHg. A 12-mm trocar was placed at the intersection of the left midaxillary line and a point 2 cm above the umbilicus as the primary operating port. A 5-mm trocar was inserted at the junction of the left midclavicular line and a point 4 cm below the umbilicus. Two additional 5-mm trocars were positioned symmetrically on the contralateral side to the operator's trocar. Please click here to view a larger version of this figure.
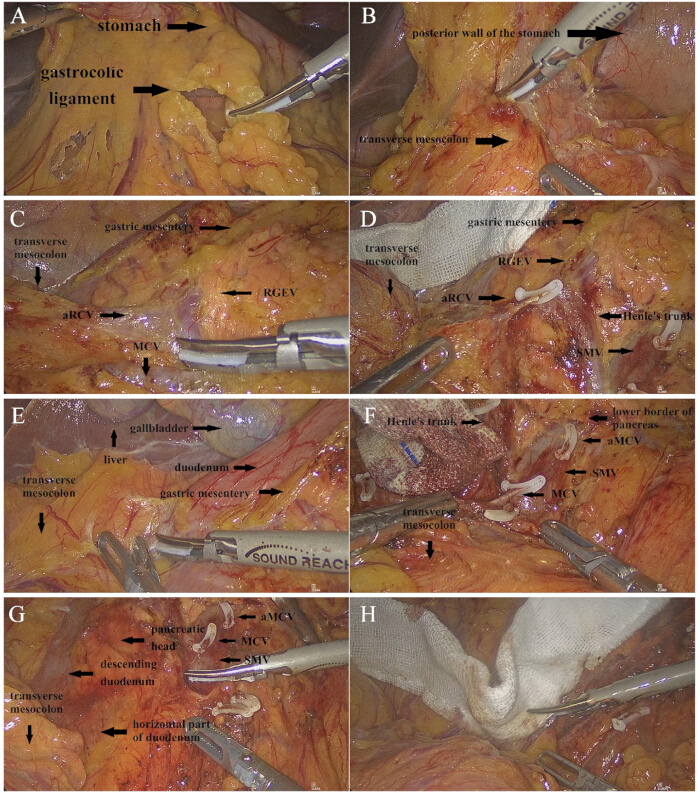
Figure 3: Operating procedures for the cranial approach. (A) Transection of the gastrocolic ligament and exposure of the omental bursa. (B) Division of the adhesions between the transverse mesocolon and the posterior wall of the stomach. (C) Exposure of the RGEV. (D) Ligation 1–2 aRCVs. (E) Incision of the adhesions between the transverse mesocolon and the gallbladder or liver. (F) Exposure of the SMV and the confluence of Henle's trunk, then ligation of the entry point of the MCV. (G) Dissection was continued caudally, exposing the pancreatic head and the horizontal part of the duodenum. (H) Using a gauze pad as a guide. Abbreviation: RGEV = Right Gastroepiploic Vein; aRCV = accessory Right Colic Vein; MCV = Middle Colic Vein; SMV = Superior Mesenteric Vein; aMCV = accessory Middle Colic Vein. Please click here to view a larger version of this figure.
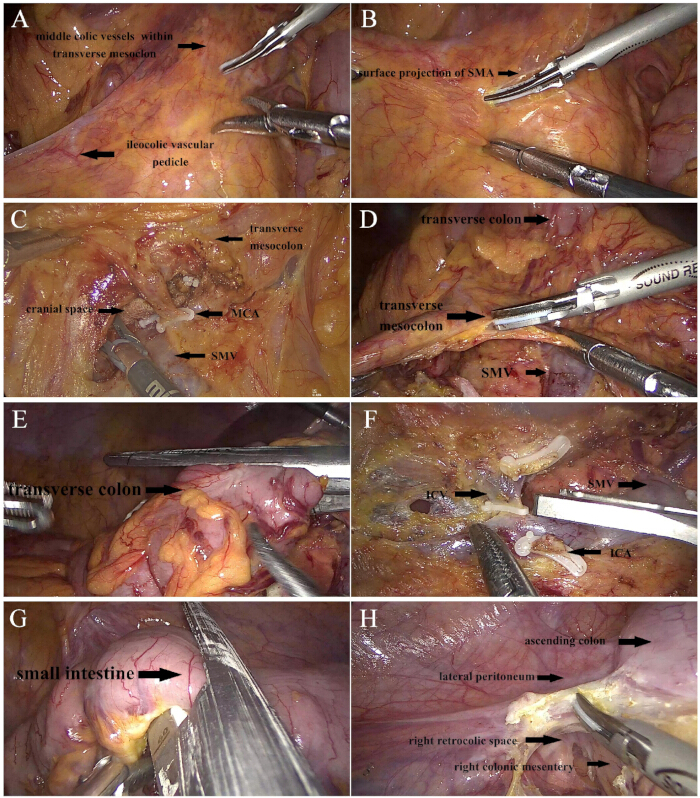
Figure 4: Middle turning-page style lymphadenectomy. (A) Retraction of the transverse mesocolon at the middle colic vessels and the ileocolic vascular pedicle with the left and right hands, respectively. (B) Incision along the surface projection of the SMA. (C) Ligation of the MCA or its right branch and creating a communication with the cranial space anterior to the SMV. (D) Transection of the transverse mesocolon. (E) Division of the transverse colon. (F) Identification and ligation of the ileocolic vessels. (G) Division of the small intestine. (H) Opening the lateral peritoneum to completely mobilize the right retrocolic space. Abbreviation: SMA = Superior Mesenteric Artery; SMV = Superior Mesenteric Vein; MCA = Middle Colic Artery; ICA = Ileocolic Artery; ICV = Ileocolic Vein. Please click here to view a larger version of this figure.
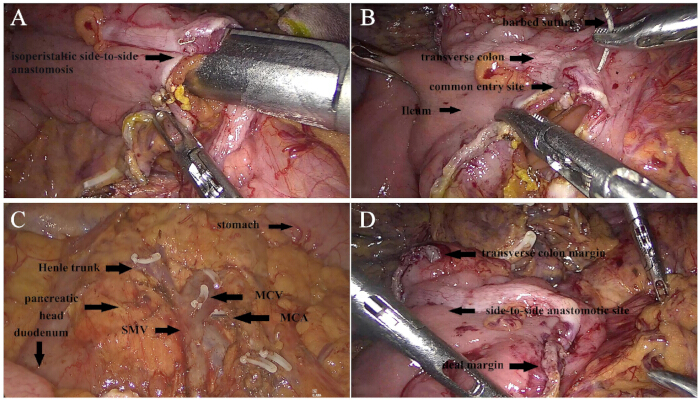
Figure 5: Anastomosis option. (A) Performing a laparoscopic intracorporeal isoperistaltic side-to-side anastomosis. (B) Closing the common entry site using a running barbed suture. (C) Overall view of the surgical field after D3 lymphadenectomy. (D) Overall view of the ileocolic side-to-side anastomosis. Abbreviation: SMV = Superior Mesenteric Vein; MCA = Middle Colic Artery; MCV = Middle Colic Vein. Please click here to view a larger version of this figure.
| General overview | Total number of cases |
| n = 86 / median (P25-P75) a | |
| Age (year) | 63.0 (45.0–76.0) |
| Sex | |
| Male | 40/86 |
| Female | 46/86 |
| BMI (kg/m2) | 23.5 (21.2–28.8) |
| Tumor location | |
| Ileocecal region | 10/86 |
| Ascending colon | 36/86 |
| Hepatic flexure | 29/86 |
| Right transverse colon | 11/86 |
| Preoperative clinical staging | |
| Stage I | 12/86 |
| Stage II | 50/86 |
| Stage III | 24/86 |
| Operative time (min) | 182.0 (160.0–210.0) |
| Blood loss (ml) | 45.0 (15.0-50.0) |
| Number of lymph node dissection | 28.0 (18.0–32.0) |
| Time to flatus (day) | 3.0 (2.0–4.0) |
| Postoperative hospitalization time (day) | 6.0 (5.0–10.0) |
| Indwelling time of the abdominal drainage tube (day) | 4.0 (3.0–6.0) |
| Intraoperative complications | 0/86 |
| Postoperative complications b | 6/86 |
| Superficial wound infection (grade II) | 4/86 |
| Ileus (grade II) | 2/86 |
| Anastomotic leakage | 0/86 |
| Postoperative bleeding | 0/86 |
| Pancreatic fistula | 0/86 |
| Conversion | 0/86 |
| 30-day re-hospital | 0/86 |
| 30-day mortality | 0/86 |
Table 1: Overview of perioperative characteristics. a: categorical variables are presented as percentages, and continuous variables are presented as medians with interquartile range; b: Postoperative complications were classified according to the Clavien-Dindo classification; BMI = body mass index
| Author, publish date | Study type | Operative time | Blood loss | Number of lymph node dissection | Postoperative complications |
| Our study a | Single-cohort | 182.0 (160.0–210.0) | 45.0 (15.0-50.0) | 28.0 (18.0–32.0) | 6/86, (7.0%) |
| Matsuda et al10, 2015 b | Single-cohort | 288 | 83 | 24 | NA (n = 18 cases) |
| Du et al5, 2018 a | Retrospective comparative | 162.5 (140–181.3) | 50 (30–50) | 18 (14.8–24) | 1/90, (1.1%) |
| Yang et al9, 2022 b | Retrospective comparative | 151.35 ± 6.75 | 73.84 ± 17.31 | 17.99 ± 5.22 | 8/82, (9.8%) |
| Nguyen et al8, 2023 a | Single-cohort | 213.91 (160–330) | 70 (20–180) | 38 (22–101) | 0/31, (0%) |
Table 2: Comparison of perioperative key outcomes between the present study and previously reported cranial-first approaches. a: continuous variables are presented as medians with interquartile range; b: mean or with standard deviation; NA = not available.
Discussion
Management of Henle’s trunk remains a technical challenge and a topic of active research in LRRH. Safe and efficient dissection of Henle’s trunk and its branches is critical for surgical success. Failure to accurately identify the origins of these vessels intraoperatively may result in hemorrhage and lead to serious complications11,12,13.
In the present study, a “cranial‑first” approach was employed, which involves incising the gastrocolic ligament to open the omental bursa and then tracing the RGEV to manage Henle’s trunk and its branches, along with the MCV, in preparation for subsequent dissection of the SMV and regional lymphadenectomy. This strategy is similar to that described by Matsuda et al.10, however, the MCA is not ligated from the cranial side in the present approach. Matsuda et al.14 proposed that during the primitive gastrointestinal development, the transverse mesocolon is located between the terminal midgut and the initial hindgut. After the primary intestinal loop undergoes a 270° counterclockwise rotation, the transverse mesocolon fuses with the anterior surface of the duodenum and pancreas. Concurrently, the greater omentum descends from the greater curvature of the stomach, draping over the anterior aspect of the transverse colon, and fuses with the transverse mesocolon. In addition, the draining veins of the right colon simultaneously join the RGEV, forming Henle’s trunk. The anatomical complexity of the transverse mesocolon stems from the rotation and fusion of the gastrointestinal tract during embryogenesis. The key features of this procedure include: facilitating exposure of the pancreas, early division of the aRCV, not ligating the MCA on the cranial side, and ease of dissection along the SMV. The colon and mesocolon are mobilized before vascular ligation, and by readily completing the separation of the transverse colon from the underlying pancreatic head and duodenum, tumor resectability can be assessed early in the operation. Furthermore, the anatomical structures of Henle’s trunk and its tributaries are clearly visualized, thereby avoiding high-risk manipulations of Henle’s trunk and middle colic vessels within a confined operative space. In obese patients or those with a thick colonic mesentery, the surgical difficulty is significantly increased. This is primarily because conventional approaches typically follow a caudal-to-cranial dissection sequence, which is compromised by the “pancreatic step” effect when exposing the inferior border of the pancreas and Henle’s trunk. Moreover, the thick mesenteric fat obscures the surgical field, often leading to ambiguous anatomical planes and inadequate exposure of the tributaries of Henle’s trunk. These challenges substantially increase the risk of inadvertent mesenteric venous injury and bleeding, ultimately resulting in nonuniform and suboptimal quality of lymph node dissection at the vascular roots. In contrast, our “cranial‑first” dissection pathway offers inherent anatomical advantages in pancreatic exposure and Henle’s trunk management. Once surgeons have overcome the learning curve, they can safely and confidently perform the most demanding and critical steps, even in difficult cases such as those involving obesity and mesenteric hypertrophy.
Conventional lymph node dissection at the vascular roots typically begins with an incision in the ileocolic mesentery, followed by gradual caudal-to-cranial dissection along the SMV. In patients with mesenteric hypertrophy and excessive adipose tissue, this approach results in a deeper SMV course and restricted surgical exposure, thereby markedly increasing both anatomical difficulty and the risk of intraoperative bleeding. In this study, a modified strategy was adopted that employs a longitudinal mesenteric incision superior to or left of the SMA, prioritizes artery-first ligation at the root, and uses a left-to-right “page‑turning” dissection technique. This approach preferentially addresses colic arterial branches crossing anterior to the SMV, allowing the entire SMV to be naturally and sequentially exposed through an intermediate “page‑turning” dissection. This modified technique transforms the traditional high‑risk dissection pattern of proceeding from superficial to deep and gradually approaching the SMV. It may simplify the root dissection process, improve the surgical field, and reduce the intraoperative blood loss, thereby making D3 lymphadenectomy more standardized and safer. Finally, priority management of Henle’s trunk and its tributaries allows early ligation of tumor‑feeding vessels, which helps prevent and reduce the risk of tumor dissemination, consistent with the “no‑touch” oncological principle proposed by Turnbull et al.15. The perioperative outcomes of the present study were compared with those of previously reported cranial-first approaches, as shown in Table 2. The present approach resulted in relatively less blood loss compared with previous studies5,8,9,10, along with a relative reduction in operative time8,10.
The limitations of this study include its retrospective, single-center, uncontrolled design and insufficient long-term follow-up data. Future randomized controlled trials (RCTs) are warranted to further validate these findings. Although the “cranial‑first” approach offers some advantages, it demands a higher level of anatomical expertise from the surgeon. Precise establishment of the fusion space between the gastric mesentery and the transverse mesocolon is challenging, and the learning curve is longer compared with the conventional caudal approach. Surgeons with extensive experience in upper abdominal and gastric surgery can acquire the skills for mobilizing this space more rapidly, thereby substantially shortening the learning cycle and accelerating technical proficiency.
In summary, the “cranial‑first” approach combined with intermediate lymphadenectomy is a safe and feasible procedure. It offers clear anatomical planes, reliable vascular management, standardized D3 lymphadenectomy, and favorable short-term clinical outcomes. This approach somewhat improves the technical limitations of conventional approaches in obese patients or those with mesenteric hypertrophy, may contribute to improved high‑quality CME and oncological outcomes, and clinical dissemination. However, the long‑term oncological benefits of this technique warrant further validation through RCTs studies with extended follow‑up.
Disclosures
The authors have no conflicts of interest.
Acknowledgements
This study was supported by Guangzhou Municipal Science and Technology Bureau Joint Funding Program for University- Enterprise Collaboration Projects (No. 2025A03J2486), and Guangdong Medical Research Foundation Project (No. B2025709).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Absorbable Suture | Ethicon LLC | Z451H | |
| Barbed Suture | Ethicon LLC | SXMD2B406 | |
| Bipolar Coagulation Forceps | AESCULAP AG | US611 | |
| Computer Hard Drive | Western Digital Corporation | WDBAGF0040BGY-CESN | |
| Disposable Vascular Clips | Jiangsu Tri-star Medical Instrument Co., Ltd. | LC-1-2 / LC-1-6 | |
| Electrode Hook | Hangzhou Kangji Medical Instrument Co., Ltd. | DJ-DNG05 | |
| Electrosurgical Unit | Zhejiang Shuyou Surgical Instrument Co., Ltd. | SY-IB-0 | |
| Hemostatic Forceps | Hangzhou Kangji Medical Instrument Co., Ltd. | DJ-FL05 | |
| Image Editing Software | Microsoft Paint | microsoft.com | |
| Irrigation and Suction Device | Olympus Medical Systems Corp. | WA51111A | |
| Laparoscopic Monitor | KARL STORZ SE & Co. KG | TM441 | |
| Laparoscopic Trocar | Surgaid Medical (Xiamen) Co., Ltd. | ICR 70-2-A | |
| Linear Cutting Stapler | Tianjin Reach Surgical Instrument Co., Ltd. | IM60BLU | |
| Long Bowel Grasping Forceps | Hangzhou Kangji Medical Instrument Co., Ltd. | KJ-4KFQJ1030L | |
| Monopolar Coagulation Forceps | KARL STORZ SE & CO. KG | 8605N | |
| Non-absorbable Suture | Ethicon, LLC | W1770 | |
| Pneumoperitoneum Machine | KARL STORZ SE & Co. KG | 24941BA | |
| Short Bowel Grasping Forceps | Hangzhou Kangji Medical Instrument Co., Ltd. | DJ-ZQ05 | |
| SPSS Statistical Software (Statistical Package for the Social Sciences) | IBM SPSS Statistics | version 19; https://www.ibm.com/products/spss-statistics | |
| Ultrasonic Scalpel | Tianjin Reach Surgical Instrument Co., Ltd. | CSUS6000 | |
| Video Player | iQIYI, Inc. | https://www.iqiyi.com | |
| Video Recorder | Karl Storz GmbH & Co. KG | L-RecordOR-01 | |
| Wound Protector | Anhui Aofu Medical Equipment Technology Co., Ltd. | YY/T 1980-2025 | |
| WPS Office Suite / WPS Document Processing Software | Beijing Kingsoft Office Software, Inc. | https://www.wps.cn/ |
References
- Schlinkert RT. Laparoscopic-assisted right hemicolectomy. Dis Colon Rectum. 1991;34(11):1030–1031.
- Anania G, et al. A global systematic review and meta-analysis on laparoscopic vs open right hemicolectomy with complete mesocolic excision. Int J Colorectal Dis. 2021;36(8):1609–1620.
- Hohenberger W, et al. Standardized surgery for colonic cancer: complete mesocolic excision and central ligation—technical notes and outcome. Colorectal Dis. 2009;11(4):354–365.
- West NP, et al. Complete mesocolic excision with central vascular ligation produces an oncologically superior specimen compared with standard surgery for carcinoma of the colon. J Clin Oncol. 2010;28(2):272–278.
- Du S, et al. A novel and safe approach: middle cranial approach for laparoscopic right hemicolon cancer surgery with complete mesocolic excision. Surg Endosc. 2018;32(5):2567–2574.
- Morales-Conde S, et al. Laparoscopic right hemicolectomy with complete mesocolon excision and cranial approach. Surg Endosc. 2025;39(1):657–660.
- Kang KM, et al. Cranial-first approach for laparoscopic extended right hemicolectomy. Ann Coloproctol. 2024;40(3):282–284.
- Nguyen NH, et al. Bach Mai Procedure for complete mesocolic excision, central vascular ligation, and D3 lymphadenectomy in total laparoscopic right hemicolectomy: a prospective study. World J Surg Oncol. 2023;21(1):140.
- Yang Y, et al. Priority management of Henle trunk in cranial-to-caudal approach for laparoscopic right hemicolon cancer surgery. Front Surg. 2022;9:883973.
- Matsuda T, et al. Cranial-to-caudal approach for radical lymph node dissection along the surgical trunk in laparoscopic right hemicolectomy. Surg Endosc. 2015;29(4):1001.
- Dindo D, Demartines N, Clavien PA. Classification of surgical complications: a new proposal with evaluation in a cohort of 6336 patients and results of a survey. Ann Surg. 2004;240(2):205–213.
- Sun KK, Zhao H. Vascular anatomical variation in laparoscopic right hemicolectomy. Asian J Surg. 2020;43(1):9–12.
- Alsabilah J, Kim WR, Kim NK. Vascular structures of the right colon: incidence and variations with their clinical implications. Scand J Surg. 2017;106(2):107–115.
- Matsuda T, et al. Anatomy of the transverse mesocolon based on embryology for laparoscopic complete mesocolic excision of right-sided colon cancer. Ann Surg Oncol. 2017;24(12):3673.
- Turnbull RB Jr, Kyle K, Watson FR, Spratt J. Cancer of the colon: the influence of the no-touch isolation technic on survival rates. CA Cancer J Clin. 1968;18(2):82–87.
Reprints and Permissions
This article has been published
Video Coming Soon