This article provides a structured, step-by-step protocol for manual reduction and four-splint immobilization of selected dorsally displaced distal radius fractures, with emphasis on patient selection, reduction maneuvers, splint application, and serial neurovascular assessment.
Artículo de método
A Step-by-Step Protocol for Manual Reduction and Splint Immobilization of Distal Radius Fractures
* These authors contributed equally
En este artículo
Resumen
Resumen
Distal radius fractures (DRFs) are among the most common upper extremity fractures encountered in clinical practice. Closed reduction followed by external immobilization remains a fundamental treatment approach; however, the procedure is highly operator-dependent and lacks standardization. This article presents a step-by-step protocol for manual reduction and four-splint immobilization using volar, dorsal, radial, and ulnar splints for acute DRFs. The protocol encompasses patient selection, anesthesia administration, patient positioning, sustained longitudinal traction with countertraction, restoration of radial length, correction of dorsal or volar translation and angulation, controlled adjustment of wrist position and forearm rotation, and secure four-splint immobilization. A representative case of a 53-year-old woman with a dorsally displaced fracture of the left distal radius is presented. Pre-reduction radiographs showed a volar tilt of approximately -15°, a radial inclination of approximately 1.74°. Immediate post-reduction radiographs showed a volar tilt of 11.4° and a radial inclination of 17.7°. Follow-up radiographs obtained 6 and 15 days after reduction showed volar tilts of 11.7° and 11.4° and radial inclinations of 15.8° and 15.2°, respectively. This article provides a structured visual protocol describing the direction and sequence of reduction forces and the application of four-splint immobilization. The representative case illustrates procedural feasibility and short-term maintenance of alignment; however, it does not establish comparative effectiveness, safety, superiority, or generalizability. These outcomes require evaluation in larger prospective studies.
Introducción
Distal radius fractures are common injuries resulting from both low- and high-energy trauma1. For appropriately selected fractures, closed reduction followed by external immobilization remains an established nonoperative treatment option1. The goals of treatment are to restore acceptable alignment, maintain reduction during healing, preserve neurovascular function, and minimize complications related to immobilization. Common post-reduction immobilization methods include plaster casts, sugar-tong splints, volar-dorsal splints, and short-arm constructs; the choice depends on fracture stability, soft-tissue swelling, patient characteristics, local clinical practice, and available resources2,3. Fracture instability and the risk of secondary displacement should also be considered when selecting patients for continued conservative treatment4. Four-piece Chinese external splinting systems have also been described following successful manipulative reduction5.
Closed reduction of distal radius fractures is highly dependent on the direction and magnitude of applied forces, the sequence of correction, and maintenance of the achieved position during immobilization. Manual traction allows the operator to adjust force based on tactile feedback, whereas other approaches, such as finger-trap traction, provide sustained axial traction. Likewise, post-reduction immobilization can be achieved using several different constructs, and no single method is appropriate for every fracture pattern. These variations highlight the need for a clearly described and reproducible procedural sequence that defines patient selection, reduction maneuvers, splint application, and post-procedure assessment.
The present article describes a patient-specific four-splint immobilization technique used in the authors’ clinical practice. The construct uses separate volar, dorsal, radial, and ulnar splints that can be individually positioned and adjusted after reduction. This technique is presented as an alternative procedural method rather than as evidence of superiority over established plaster or splint constructs. The method is intended for appropriately selected dorsally displaced distal radius fractures in which closed reduction is clinically appropriate and acceptable alignment can be achieved and maintained.
The aim of this article is to provide a detailed, step-by-step visual protocol for manual reduction and four-splint immobilization of selected dorsally displaced distal radius fractures, with emphasis on the direction and sequence of reduction forces, maintenance of reduction during splint application, and serial neurovascular assessment.
Protocolo
The publication of de-identified clinical information, radiographs, clinical images, and the procedural video was approved by the Institutional Review Board of The First Hospital of Hunan University of Chinese Medicine (Approval No. HN-LL-YJSLW-2026-101). The Institutional Review Board waived the requirement for individual informed consent for publication of these de-identified materials. All patient and institutional identifiers were removed before submission. The research tools used in this protocol are listed in the Table of Materials.
1. Patient selection
- Inclusion criteria
- Include patients with an acute, closed distal radius fracture confirmed on standard posteroanterior and lateral wrist radiographs.
- Include fractures showing displacement, angulation, or radial shortening for which an initial trial of closed reduction is clinically appropriate.
- Confirm that the skin is intact. Exclude any open wound communicating with the fracture, threatened skin, or clinical evidence of compartment syndrome.
- Confirm that distal perfusion is preserved. Exclude patients with a progressive median, radial, or ulnar nerve deficit requiring urgent surgical intervention.
- Include simple or moderately displaced metaphyseal fracture patterns. Exclude fractures with severe comminution, an irreducible intra-articular fragment, fracture-dislocation, or soft-tissue interposition.
- Continue conservative treatment only when acceptable alignment is obtained after reduction and can be maintained with the four-splint construct.
NOTE: Define acceptable alignment according to the institution’s prespecified radiographic criteria for volar tilt, radial inclination, radial shortening, ulnar variance, and articular step-off.
- Exclusion criteria
- Exclude open fractures, fractures associated with compartment syndrome, and fractures with threatened skin requiring urgent intervention.
- Exclude severely comminuted, irreducible, unstable intra-articular, or fracture-dislocation patterns that are unlikely to maintain alignment after closed reduction.
- Exclude patients with persistent vascular compromise or progressive neurological dysfunction requiring urgent surgical exploration.
- Exclude fractures that remain outside the predefined acceptable radiographic limits after two reduction attempts. Exclude fractures that immediately redisplace after splint application.
- Exclude patients who cannot tolerate or cooperate with the procedure or who are unlikely to comply with early radiographic follow-up.
2. Preparation
- Patient positioning
- Position the patient in a seated or supine position. Place the affected upper limb on a stable support.
- Flex the affected elbow to approximately 90°. Keep the forearm accessible to both the operator and the assistant.
- Ask the assistant to stabilize the elbow and proximal forearm. Leave the wrist and distal forearm fully accessible for reduction.
- Analgesia, anesthesia, and physiological monitoring
- Record the baseline pain score using a 0–10 numerical rating scale. Measure blood pressure, heart rate, oxygen saturation, and level of consciousness.
- Confirm that the patient has no known allergy to lidocaine or infection at the intended injection site. Exclude any other contraindication to a hematoma block.
- Prepare 10–15 mL of 1% lidocaine without epinephrine in a 20 mL syringe fitted with a 22–25 G needle.
- Calculate the maximum allowable dose according to the patient’s body weight. Do not exceed 4.5 mg/kg.
- Disinfect the dorsal skin over the fracture site using the institutional antiseptic solution. Allow the solution to dry completely.
- Insert the needle toward the fracture hematoma under aseptic conditions. Aspirate gently until dark, non-clotting blood confirms that the needle tip is within the hematoma.
- Inject the lidocaine slowly into the fracture hematoma. Aspirate intermittently to reduce the risk of intravascular injection.
- Remove the needle and apply sterile pressure to the puncture site.
- Wait 10–15 min and reassess the pain score. Proceed with reduction only after adequate analgesia has been achieved and the patient’s physiological status remains stable.
- Monitor blood pressure, heart rate, oxygen saturation, and level of consciousness throughout anesthesia, reduction, and splint application.
- Monitor for perioral numbness, tinnitus, dizziness, altered consciousness, seizure activity, or cardiovascular instability.
- Stop the procedure and initiate appropriate management if any symptom of local-anesthetic systemic toxicity occurs.
- Observe the patient for at least 30 min after completion of reduction and splint application. Continue monitoring blood pressure, heart rate, oxygen saturation, level of consciousness, pain intensity, and distal neurovascular status.
- Extend the observation period if neurological or cardiovascular symptoms develop, if the lidocaine dose approaches the maximum allowable dose, or if any post-procedural abnormality is identified.
- Pre-procedural assessment
- Obtain standard posteroanterior and lateral wrist radiographs. Determine the fracture configuration and displacement pattern.
- Assess capillary refill time, radial and ulnar pulses, skin color and temperature, and active finger flexion and extension. Record all findings before reduction.
- Assess median nerve function using thumb opposition and sensation over the palmar aspect of the index finger.
- Assess radial nerve function using thumb or finger extension and sensation over the first dorsal web space.
- Assess ulnar nerve function using finger abduction and sensation over the palmar aspect of the little finger.
- Document all motor and sensory findings in the clinical record.
- Materials preparation
- Prepare four fir-bark splints: volar, dorsal, radial, and ulnar. Size the splints according to the dimensions of the affected forearm.
- Trim each splint so that its width is slightly narrower than the corresponding aspect of the affected limb.
- Pad the splints appropriately to protect the skin and bony prominences.
- Prepare the fixation straps, bandage, and scissors. Keep all materials readily accessible before reduction.
- Arrange the materials so that immobilization can be applied immediately after satisfactory alignment has been achieved (Figure 1).
3. Manual reduction procedure
- Establishment of traction and countertraction
- Ask the assistant to stabilize the elbow and proximal forearm. Align the assistant’s countertraction force with the longitudinal axis of the forearm.
- Grasp the patient’s distal hand with both hands. Avoid direct pressure over the fracture site.
- Align the operator’s traction force with the longitudinal axis of the forearm (Figure 2).
- Confirm the pre-reduction neurovascular findings immediately before applying traction. Stop the procedure if a new vascular or neurological abnormality is identified.
- Longitudinal traction
- Apply gradual longitudinal traction while the assistant applies equal countertraction in the opposite direction. Avoid sudden or forceful pulling.
- Maintain traction for approximately 3–5 min or until muscle resistance decreases and the impacted fragments become mobile.
- Restore radial length before correcting translation and angulation. Maintain continuous traction during the subsequent corrective maneuvers.
- Angular correction
- For a dorsally displaced fracture, stabilize the proximal fragment and apply volar-directed pressure to the distal fragment.
- Correct radial translation and dorsal angulation in a controlled sequence.
- For a volarly displaced fracture, apply dorsal-directed pressure to the distal fragment while maintaining longitudinal traction.
NOTE: Use this maneuver only for fracture configurations considered suitable for closed reduction. - Adjust the forearm and wrist position incrementally until the clinical deformity is corrected. Avoid excessive flexion, extension, pronation, or supination.
- Confirmation of reduction
- Maintain longitudinal traction and inspect the wrist from the dorsal, volar, and lateral aspects.
- Confirm that the dorsal prominence and radial deviation have improved and that the wrist contour approximates that of the contralateral side.
- Compare the apparent radial length and the relative positions of the radial and ulnar styloids with those of the contralateral wrist.
NOTE: Use this assessment only as a preliminary clinical indicator. Confirm the reduction radiographically as described in section 5.1. - Ask the patient to actively flex and extend all fingers. Confirm that finger movement is smooth and does not produce mechanical blocking or severe pain.
- Stop further manipulation if finger motion becomes restricted or marked pain is elicited.
- Repeat and document the complete distal neurovascular assessment, including capillary refill, radial and ulnar pulses, skin color and temperature, active finger movement, and median, radial, and ulnar nerve motor and sensory function.
- Stop the procedure if any new neurovascular abnormality is identified.
- Maintenance of reduction
- Maintain the corrected wrist in approximately 15°–20° of palmar flexion and 10°–15° of ulnar deviation.
- Maintain the forearm in a neutral position or slight supination of approximately 15°–20°.
- Maintain continuous control of the distal fragment while the assistant applies the pressure pads, protective padding, and four splints.
- Do not release the reduction until all splints and fixation straps have been secured.
- Repeat the complete reduction maneuver no more than two times.
- Discontinue closed reduction and evaluate the patient for surgical treatment if acceptable alignment cannot be achieved or maintained, if the fracture immediately redisplaces, or if neurovascular function deteriorates.
4. Splint immobilization
- Preparation of the limb
- Maintain the reduced wrist position. Apply protective padding over the fracture region and bony prominences.
- Smooth the padding to prevent folds and focal pressure.
- Confirm that the four fir-bark splints have been trimmed according to the patient’s forearm dimensions.
- Ensure that all edges have been smoothed and covered with two layers of gauze.
- Placement of the four splints
- Place the volar and dorsal splints along the corresponding aspects of the forearm while maintaining the reduction.
- Leave the fingers and elbow free for examination and movement.
- Place the radial and ulnar splints along the corresponding sides of the forearm.
- Maintain a small interval between adjacent splints to accommodate swelling and avoid circumferential compression.
- Confirm that the splints cover the fracture region without directly compressing the radial styloid, ulnar styloid, or other bony prominences.
- Adjust the padding where necessary.
- Securing the splints
- Secure the splints using the prepared fixation straps and bandage. Apply the straps in the predetermined sequence while maintaining the corrected wrist position.
- Tighten each strap sufficiently to stabilize the splints. Allow the knot of each strap to slide approximately 1 cm along the long axis of the forearm.
- Use releasable knots so that the construct can be loosened promptly if swelling develops.
- Confirm that the wrist and forearm remain in the intended position after all straps have been secured.
- Re-adjust the construct if alignment is lost.
- Post-splint neurovascular assessment
- Reassess capillary refill time, radial and ulnar pulses, skin color and temperature, and active finger movement immediately after splint application.
- Reassess median, radial, and ulnar nerve motor and sensory function.
- Compare all findings with the pre-reduction and immediate post-reduction records.
- Loosen or remove the splint immediately if the patient develops increasing pain, pallor, cyanosis, reduced skin temperature, delayed capillary refill, numbness, weakness, or loss of pulse.
- Escalate treatment if the abnormality does not resolve promptly.
5. Post-procedure assessment
- Radiographic evaluation
- Obtain post-reduction posteroanterior and lateral radiographs.
- Assess volar tilt, radial inclination, radial shortening, ulnar variance, and articular congruity.
- Define acceptable post-reduction alignment as neutral or volar tilt with no more than 10° of residual dorsal tilt, radial inclination of at least 15°, radial shortening of no more than 3 mm, and an articular step-off or gap of less than 2 mm.
- Repeat the reduction or evaluate the patient for surgical treatment if the predefined alignment criteria are not achieved or cannot be maintained.
- Clinical observation before discharge
- Observe the patient for at least 30 min after completion of reduction and splint application.
- Monitor blood pressure, heart rate, oxygen saturation, pain intensity, and level of consciousness throughout the observation period.
- Repeat and document the complete distal neurovascular assessment at the end of the observation period.
- Confirm that capillary refill, radial and ulnar pulses, skin colour and temperature, active finger movement, and median, radial, and ulnar nerve function remain stable.
- Extend the observation period and initiate appropriate evaluation if the patient develops increasing pain, dizziness, tinnitus, perioral numbness, altered consciousness, cardiovascular instability, or deterioration of distal neurovascular function.
- Discharge the patient only after the vital signs remain stable, adequate pain control is achieved, and no new neurovascular abnormality is identified.
- Provide written instructions to return immediately if increasing pain, numbness, weakness, finger discoloration, reduced skin temperature, excessive swelling, or restricted finger movement occurs.
- Follow-up
- Arrange early clinical and radiographic follow-up according to the institutional protocol.
- Reassess fracture alignment, splint tightness, skin condition, and neurovascular function at each visit.
- Loosen or tighten the fixation straps as swelling changes while maintaining fracture alignment.
- Repeat radiographs if clinical deformity, increasing pain, or loss of splint fit suggests redisplacement.
- Document the date of each radiographic examination and whether the splint remained in place during imaging.
- Document the date immobilization ended and the final clinical status.
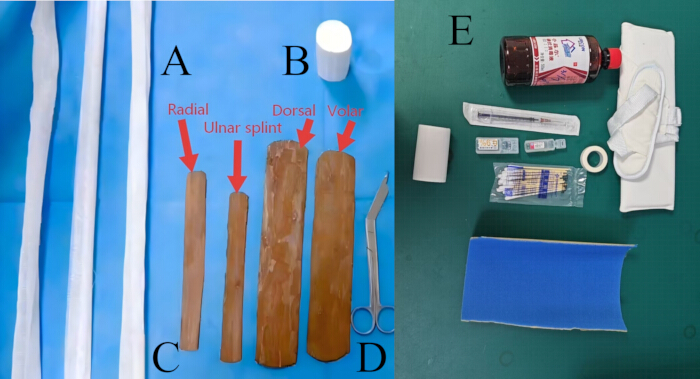
Figure 1: Materials used for manual reduction and four-splint immobilization. (A) Fixation straps. (B) Gauze bandage. (C) Four patient-specific fir-bark splints comprise the radial, ulnar, dorsal, and volar splints. The splints were trimmed according to the dimensions of the patient’s forearm, and their edges were smoothed before application. (D) Scissors. (E) Overview of the materials prepared for the procedure, including antiseptic solution, a syringe and needle, local anesthetic, sterile cotton swabs, adhesive tape, protective padding, fixation straps, and other immobilization materials. Please click here to view a larger version of this figure.
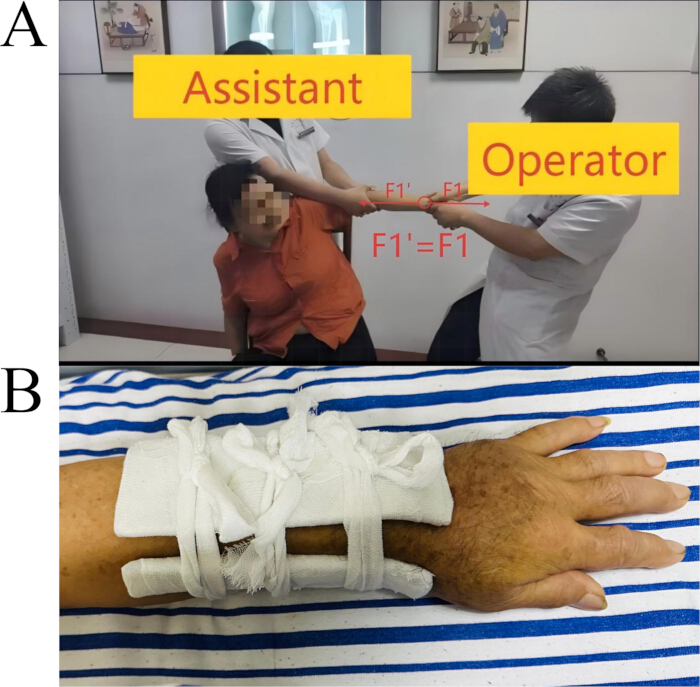
Figure 2: Key steps of manual reduction and four-splint immobilization. (A) Traction and countertraction during closed reduction. The operator applies longitudinal traction to the distal hand while the assistant provides countertraction in the opposite direction. (B) Final appearance after application of the four-splint construct and fixation straps. Please click here to view a larger version of this figure.
Resultados
A representative case is presented to illustrate the application of the manual reduction and four-splint immobilization protocol rather than to demonstrate comparative effectiveness. A 53-year-old woman presented with pain, swelling, and deformity of the left wrist following a fall. Pre-reduction radiographs obtained on May 29, 2026, demonstrated a dorsally displaced Colles-type distal radius fracture. The volar tilt was approximately −15.24°, and the radial inclination was approximately 1.74° (Figure 3).
Manual reduction was performed using longitudinal traction and countertraction, followed by correction of radial shortening, dorsal displacement, and angulation. The corrected position was maintained while the volar, dorsal, radial, and ulnar fir-bark splints were applied. Immediate post-reduction radiographs obtained on May 29, 2026, showed a volar tilt of 11.4° and a radial inclination of 17.7° (Figure 4). Both measurements met the prespecified criteria for acceptable alignment.
At the first follow-up on June 4, 2026, 6 days after reduction, the volar tilt was 11.7°, and the radial inclination was 15.8° (Figure 5). At the second follow-up on June 13, 2026, 15 days after reduction, the volar tilt was 11.4°, and the radial inclination was 15.2° (Figure 6). The radial inclination decreased by 2.5° between the immediate post-reduction examination and the final available follow-up, whereas the volar tilt remained between 11.4° and 11.7°. All measured angles remained within the prespecified criteria for acceptable alignment.
Ulnar variance and articular step-off/gap were not assessed in the available records. The four-splint construct remained in place during the available radiographic follow-up. Active finger movement and distal perfusion were preserved, and no new neurovascular abnormality was documented. The splint was discontinued 8 weeks after reduction, after which the patient gradually resumed normal use of the affected limb under medical guidance. These findings demonstrate only short-term maintenance of alignment in this illustrative case and do not establish effectiveness, superiority, or fracture union.
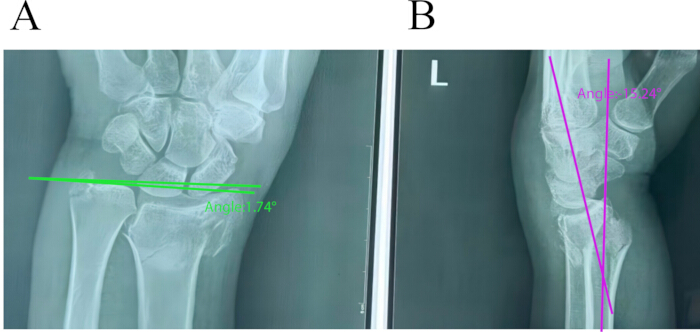
Figure 3: Pre-reduction radiographs of the left distal radius fracture. (A) Posteroanterior radiograph showing loss of radial inclination, with a measured angle of approximately 1.74°. (B) Lateral radiograph showing dorsal angulation of the distal fragment, corresponding to a volar tilt of approximately −15.24°. Measurement lines and values are shown on the radiographs. Please click here to view a larger version of this figure.
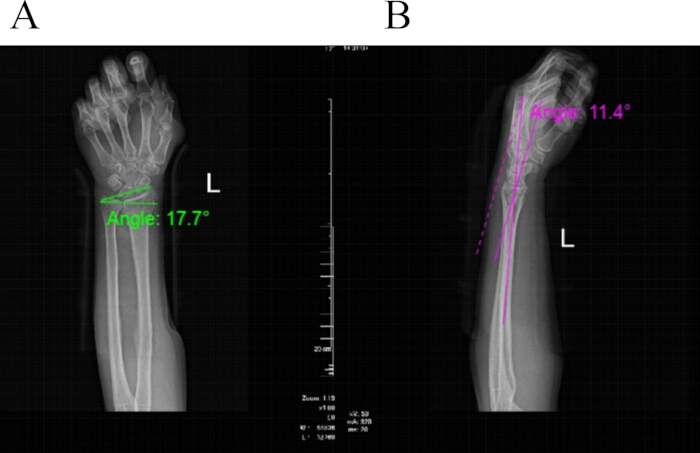
Figure 4: Immediate post-reduction radiographs of the left distal radius fracture. Posteroanterior (A) and lateral (B) radiographs obtained immediately after manual reduction and four-splint immobilization. The radial inclination was 17.7°, and the volar tilt was 11.4°. Measurement lines and corresponding values are shown on the radiographs. The four-splint construct remained in place during imaging. Please click here to view a larger version of this figure.
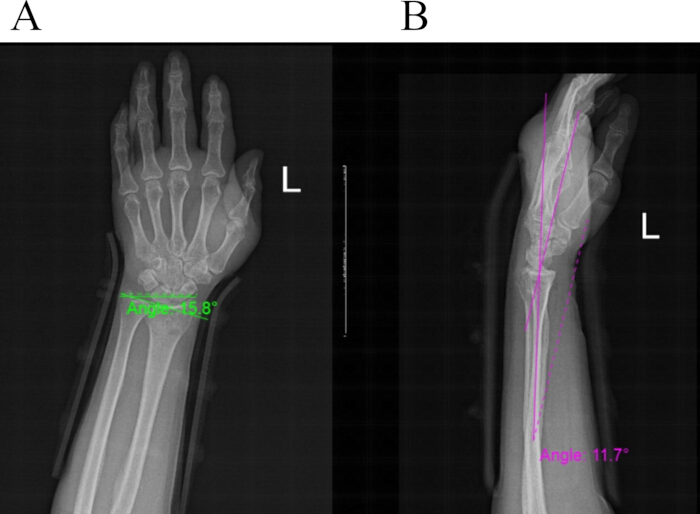
Figure 5: First follow-up radiographs of the left distal radius fracture. Posteroanterior (A) and lateral (B) radiographs obtained 6 days after reduction. The radial inclination was 15.8°, and the volar tilt was 11.7°. The measurements remained within the prespecified criteria for acceptable alignment. The four-splint construct remained in place during imaging. Please click here to view a larger version of this figure.
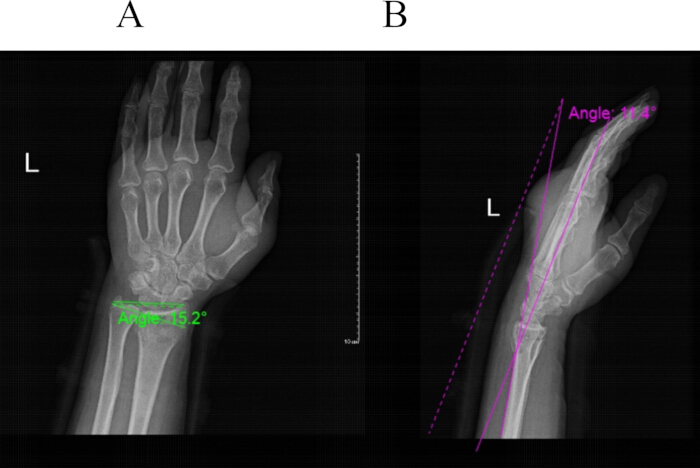
Figure 6: Second follow-up radiographs of the left distal radius fracture. Posteroanterior (A) and lateral (B) radiographs obtained 15 days after reduction. The radial inclination was 15.2°, and the volar tilt was 11.4°. The measurements remained within the prespecified criteria for acceptable alignment. These images demonstrate short-term maintenance of alignment but do not establish fracture union. The four-splint construct remained in place during imaging. Please click here to view a larger version of this figure.
Discusión
This article describes a structured protocol for manual reduction followed by four-splint immobilization of selected dorsally displaced distal radius fractures. The critical steps include appropriate patient selection, adequate analgesia, controlled traction and countertraction, correction of shortening and angulation, maintenance of reduction during splint application, and repeated neurovascular assessment. Closed treatment should be discontinued when acceptable alignment cannot be achieved or maintained, or when progressive neurovascular compromise occurs1.
Manual traction allows the operator to adjust the direction and magnitude of force according to tactile feedback, whereas finger-trap traction provides more sustained axial traction. Prospective and systematic evidence has not demonstrated a clear overall superiority of either reduction method6,7. After reduction, commonly used immobilization strategies include sugar-tong, volar-dorsal, short-arm, and cast constructs. Comparative studies suggest that no single construct is optimal for all fracture patterns, and the choice should consider fracture stability, swelling, patient comfort, local expertise, and follow-up availability2,8.
The present four-splint construct uses separate volar, dorsal, radial, and ulnar fir-bark splints secured with adjustable straps. This arrangement permits individualized contouring and adjustment as swelling changes. However, the present single-case report does not demonstrate that this technique is superior to conventional plaster, fiberglass, or other splinting methods. Loss of reduction remains an important concern during conservative treatment, particularly in fractures with instability features or inadequate reduction and molding9,10. Therefore, early radiographic follow-up, reassessment of splint fit and alignment, and prompt adjustment or surgical evaluation are required when alignment deteriorates. The duration of immobilization should also be individualized according to fracture stability and follow-up findings11.
This report is limited by the inclusion of only one illustrative case, the absence of a comparator group, and short-term radiographic follow-up. The findings demonstrate procedural feasibility and short-term maintenance of alignment but do not establish effectiveness, safety, reproducibility, fracture union, or broad applicability.
CONCLUSION:
This article describes a step-by-step protocol for manual reduction and four-splint immobilization of selected dorsally displaced distal radius fractures. The protocol is intended to provide a visual and procedural framework for training and replication. The single illustrative case demonstrates procedural feasibility and short-term maintenance of alignment but does not establish effectiveness, safety, reproducibility, superiority, fracture union, or broad clinical applicability. Comparative prospective studies with larger sample sizes and longer follow-up are required.
Divulgaciones
The authors report no conflicts of interest. During the preparation of this work, the authors used ChatGPT to improve the English language and readability of the manuscript. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
Agradecimientos
The authors acknowledge financial support from the National Natural Science Foundation of China (82274543); the National Key Clinical Specialty Program of Chinese Medicine for Orthopedics and Traumatology (czxm-gsk- 2024002); the 2024 Hunan Provincial Clinical Specialty Cluster Program of Chinese Medicine for Orthopedics and Traumatology (czxm-gsk- 2024004); the Natural Science Foundation of Hunan Province (2026JJ81038); and the Hunan Provincial Administration of Traditional Chinese Medicine (C2023014).
Materiales
| Nombre | Empresa | Número de catálogo | Comentarios |
|---|---|---|---|
| 0.9% sodium chloride injection | China Otsuka Pharmaceutical Co., Ltd. | 25C74J4 | Used to dilute lidocaine to the final concentration, if applicable. |
| Adjustable fixation straps | N/A | N/A | Used to secure the four splints while allowing approximately one finger beneath each strap. |
| Arm sling | Changsha Huafeng Kangcheng Medical Devices Co., Ltd. | 20260515 | Used for post-procedure support of the immobilized upper limb, if applicable. |
| Disposable sterile syringe and needle | Jiangxi Hongda Medical Device Group Co., Ltd. | 20260302 | 20 mL syringe fitted with a 22–25 G needle, as specified in the protocol. |
| Fir-bark splints | Locally sourced and patient-specific | N/A | Four splints (volar, dorsal, radial, and ulnar), approximately 2–4 mm thick and trimmed according to the dimensions of the contralateral forearm. |
| Gauze bandage | Xinxiang Daofang Medical Equipment Manufacturing Co., Ltd. | 2.60306E+11 | Approximately 8 cm × 600 cm; used for wrapping and securing the splints. |
| Gauze scissors | Shanghai Hongzun Medical Equipment Co., Ltd. | 2023090422 | 18 cm; used to trim gauze, padding, and bandage. |
| Lidocaine hydrochloride injection | Hunan KELUN Pharmaceutical Co., Ltd. | R26031501 | Final concentration of 1%, without epinephrine; 10–15 mL used for hematoma block. |
| Medical adhesive tape | Henan Yadu Industrial Co., Ltd. | 2508JW0437 | Used to secure padding or local dressings when required. |
| Povidone-iodine antiseptic solution | Shandong Lierekang Medical Technology Co., Ltd. | 20250516 | Used for skin antisepsis before hematoma block. |
| Protective orthopedic padding | N/A | N/A | Applied over the fracture region and bony prominences to prevent focal pressure. |
| Soft foam padding sheet | N/A | N/A | Used as additional cushioning material, if applicable. |
| Sterile cotton swabs | Yixin Medical Devices Co., Ltd. | 260305878 | Used for antiseptic skin preparation. |
| Sterile gloves | Shandong Yuyuan Latex Gloves Co., Ltd. | 2.60411E+12 | Used for aseptic hematoma-block injection. |
Referencias
- Kamal RN, Shapiro LM. American Academy of Orthopaedic Surgeons/American Society for Surgery of the Hand clinical practice guideline SHORT ABSTRACT: Management of distal radius fractures. J Am Acad Orthop Surg. 2022;30(4):e480–e486.
- Jackson T, et al. A comparison of sugar-tong and volar-dorsal splints for provisional immobilization of distal radius fractures in the adult population. Eur J Orthop Surg Traumatol. 2021;31(2):229–234.
- Gamba C, et al. Which immobilization is better for distal radius fracture? A prospective randomized trial. Int Orthop. 2017;41(9):1723–1727.
- Mackenney PJ, Mcqueen MM, Elton R. Prediction of instability in distal radial fractures. J Bone Joint Surg Am. 2006;88(9):1944–1951.
- Futami T, Yamamoto M. Chinese external fixation treatment for fractures of the distal end of the radius. J Hand Surg Am. 1989;14(6):1028–1032.
- Sosborg-Wurtz H, Corap Gellert S, Ladeby Erichsen J, Viberg B. Closed reduction of distal radius fractures: A systematic review and meta-analysis. EFORT Open Rev. 2018;3(4):114–120.
- Earnshaw SA, Aladin A, Surendran S, Moran CG. Closed reduction of Colles fractures: Comparison of manual manipulation and finger-trap traction: A prospective, randomized study. J Bone Joint Surg Am. 2002;84(3):354–358.
- Chaudhry YP, et al. Comparison of short-arm immobilization and long-arm immobilization in conservatively managed distal radius fractures: A meta-analysis and systematic review. Cureus. 2024;16(3):e55813. doi: 10.7759/cureus.55813.
- Alemdaroglu KB, et al. Three-point index in predicting redisplacement of extra-articular distal radial fractures in adults. Injury. 2010;41(2):197–203.
- Lafontaine M, Hardy D, Delince P. Stability assessment of distal radius fractures. Injury. 1989;20(4):208–210.
- Van Delft EaK, et al. Four weeks versus six weeks of immobilization in a cast following closed reduction for displaced distal radial fractures in adult patients: A multicentre randomized controlled trial. Bone Joint J. 2023;105-B(9):993–999.
Reimpresiones y permisos
Este artículo ha sido publicado
Video próximamente