Patient-derived organoid cultures of pancreatic ductal adenocarcinoma are a rapidly established 3-dimensional model that represent epithelial tumor cell compartments with high fidelity, enabling translational research into this lethal malignancy. Here, we provide detailed methods to establish and propagate organoids as well as to perform relevant biological assays using these models.
Method Article
Isolation and Characterization of Patient-derived Pancreatic Ductal Adenocarcinoma Organoid Models
In This Article
Summary
Abstract
Pancreatic ductal adenocarcinoma (PDAC) is amongst the most lethal malignancies. Recently, next-generation organoid culture methods enabling the 3-dimensional (3D) modeling of this disease have been described. Patient-derived organoid (PDO) models can be isolated from both surgical specimens as well as small biopsies and form rapidly in culture. Importantly, organoid models preserve the pathogenic genetic alterations detected in the patient's tumor and are predictive of the patient's treatment response, thus enabling translational studies. Here, we provide comprehensive protocols for adapting tissue culture workflow to study 3D, matrix embedded, organoid models. We detail methods and considerations for isolating and propagating primary PDAC organoids. Furthermore, we describe how bespoke organoid media is prepared and quality controlled in the laboratory. Finally, we describe assays for downstream characterization of the organoid models such as isolation of nucleic acids (DNA and RNA), and drug testing. Importantly we provide critical considerations for implementing organoid methodology in a research laboratory.
Introduction
Pancreatic ductal adenocarcinoma (PDAC) is a lethal disease characterized by late diagnosis in most patients, a lack of effective therapies, and a resultant low 5-year overall survival rate that remains less than 10%1. Only 20% of patients are diagnosed with a localized disease suitable for curative surgical intervention2,3. The remaining patients are typically treated with a combination of chemotherapeutic agents that are effective in a minority of patients4,5. To address these pressing clinical needs, researchers are actively working on early detection strategies and the development of more effective therapies. To accelerate clinical translation of important discoveries, scientists are employing genetically engineered mouse models, patient derived xenografts, monolayer cells lines, and, most recently, organoid models6.
Three-dimensional epithelial organoid culture using growth factor and Wnt-ligand rich conditions to stimulate proliferation of untransformed progenitor cells were first described for the mouse intestine7 and were quickly adapted to normal human pancreatic tissue8. In addition to normal ductal tissue, organoid methodology allows for the isolation, expansion, and study of human PDAC8. Importantly, the method supports the establishment of organoids from surgical specimens, as well as fine and core needle biopsies, allowing researchers to study all stages of the disease9,10. Interestingly, patient-derived organoids recapitulate well-described tumor transcriptomic subtypes and may enable development of precision medicine platforms9,11.
Current organoid protocols for PDAC enable the successful expansion of more than 70% of patient samples from chemo-naïve patients9. Here we present the standard methods employed by our laboratory to isolate, expand, and characterize patient-derived PDAC organoids. Other PDAC organoid methodologies have been described12,13 but no comparison of these method has been thoroughly performed. As this technology is relatively new and advancing quickly, we expect that these protocols will continue to evolve and improve; however the principles of tissue handling and organoid culture will continue to be useful.
Protocol
All human tissue collection for research use was reviewed and approved by our Internal Review Board (IRB). All of the following protocols are performed under aseptic conditions in a mammalian tissue culture laboratory environment.
1. Media Preparation
- Conditioned media preparation.
NOTE: The human pancreatic organoid media requires abundant growth factors and nutrients as well as conditioned media supplementation to provide sufficient growth stimulation for organoid expansion. Both conditioned mediums described below are prepared from commercially available cell lines (see Table of Materials). For complete protocols and materials, please refer to the manufacturers' websites.- Produce R-spondin1 conditioned media according to the manufacturer's protocol.
- First, expand the 293T cells expressing R-spondin1 using appropriate antibiotic (Zeocin) selection methods in the presence of abundant serum (10%). When producing conditioned media, withdraw and wash away the antibiotic selection and serum such that no antibiotic and serum are present in the final conditioned media. Importantly, the conditioned media must be filter sterilized after collection (0.2 µm) to prevent cross-contamination.
- Store aliquoted conditioned media at 4 °C for short term use (within 6 months) or at -20 °C for long term storage (more than 6 months). Freeze-thaw cycles should be avoided.
- Produce L-Wnt-3A conditioned media according to the manufacturer's protocol.
- First, expand the L-M(TK-) cells expressing L-Wnt-3A using appropriate antibiotic (G-418) selection methods in the presence of abundant serum (10%). When producing conditioned media, withdraw and wash away the antibiotic selection such that no antibiotic is present in the final conditioned media; however, maintain the serum throughout the culturing and conditioning. Importantly the collected conditioned media must be filter sterilized (0.2 µm) to prevent cross contamination.
- Store the aliquoted conditioned media at 4 °C for short term use, or -20 °C for long term storage. Freeze-thaw cycles should be avoided.
- For quality control, perform a TOPFLASH assay to test the Wnt activity of R-spondin1 and the L-Wnt-3A conditioned media alone and in combination according to a previously published protocol14.
- Produce R-spondin1 conditioned media according to the manufacturer's protocol.
- Basal media preparation: Use basal media for preparation of complete organoid media as well as washing steps for organoid work. Supplement advanced DMEM/F-12 with Glutamine at a final concentration of 1x, HEPES (10 mM), and Penicillin/Streptomycin (100 U/mL). Store basal media at 4 °C.
- Organoid Complete media preparation: Supplement the basal media with R-spondin1 conditioned media at a final concentration of 10% v/v, L-Wnt-3A conditioned media at a final concentration of 50% v/v, Human EGF (50 ng/mL), Human FGF (100 ng/mL), Human Gastrin I (10 nM), Mouse Noggin (100 ng/mL), A83-01 (500 nM), B27 supplement (1x), Nicotinamide (10 mM), N-acetylcysteine (1.25 mM), and Primocin (100 µg/mL).
- For primary organoid isolations, thawed organoid cultures, and cultures starting with single cells, include Rho kinase inhibitor Y-27632 at a final concentration of 10.5 µM.
- Prepare the human organoid complete media on ice and store at 4 °C for use within one month. For this reason, we recommend fresh weekly preparation of media.
2. Isolation of PDAC Organoids
NOTE: Thaw the basement membrane extract (BME) solution (growth factor reduced; see Table of Materials) on ice in a 4 °C environment (fridge or cold room) for at least 12 h prior to use. Incubate the tissue culture plates for organoid culture in a 37 °C incubator for at least 12 h prior to use.
- Collect and transport a surgically removed tumor specimen for research in a buffered storage solution to maintain viability of the tissue. Use basal media or a commercially available tissue storage solution.
- Proceed to isolate organoids as soon as possible after receiving the specimen. Tissue can be stored in the storage solution up to 24 h post-surgery and still yield organoids.
- Once in the laboratory, transfer tumor to a 10 cm tissue culture dish and remove storage solution.
- While handling the tissue with metallic forceps, mince the tumor with a #10 scalpel into small fragments of 1 mm3 or smaller. Larger fragments will take longer to digest; therefore, aim to generate homogenous tissue fragment sizes. If tissue is already disaggregated or in smaller than 1 mm3 fragments, skip this step.
- Transfer the tissue fragments to a 15 mL conical tube containing 10 mL of basal media. Mix by inverting the tube several times. Centrifuge the tube at 200 x g for 5 min. After spin, remove the basal media carefully to avoid losing tissue fragments.
- To the tube containing the tissue fragments add 9 mL of basal media and 1 mL of 10x Gentle Collagenase/Hyaluronidase solution. To avoid clumping of cells during digestion, supplement this solution with 20 µL of 10 mg/mL DNAse I solution. Mix by inverting the tube several times.
- Incubate the enzymatic digestion at 37 °C on a nutator or rotator. For adequate mixing during digestion, the tissue fragments must constantly be moving through the solution.
NOTE: Timing for this enzymatic dissociation of the tumor must be determined empirically for every specimen. A successful digestion of the tumor is characterized by the decrease in size of the tissue fragments until they are not clearly discernable to the naked eye. Concomitantly, the opacity of the solution will increase as microscopic tissue fragments are released. - After 30 min, remove the conical tube from the 37 °C incubator and observe. If the tissue fragments are still clearly visible, continue the dissociation at 37 °C with constant mixing. Repeat this observation every 30 min until most or all tissue fragments have been dissociated. Depending on the stringency of mixing as well as the size and amount of tumor fragments, this step can take as little as 30 min for small specimens or as long as 12 h for larger tumor samples.
- Once the enzymatic dissociation is complete, centrifuge the tube at 200 x g for 5 min. After spin, a cell pellet should be visible and the supernatant should be clear, indicating that all cells have been spun out of solution. If that is not the case, repeat the spin.
- Carefully remove the supernatant to avoid losing the cell pellet. Immediately wash the cells with 10 mL basal media by gently mixing the tubes with inversion. Centrifuge the tube at 200 x g for 5 min. Carefully remove the basal media to avoid losing cells and repeat this washing step one more time for a total of two washes.
- After the second wash, remove all of the basal media carefully and place the tube on ice for 5 min.
- At this time, place an aliquot of organoid complete media in a 37 °C water bath to pre-warm.
- Mix the cell pellet with ice cold BME while maintaining the tube on ice. Seeding density should be high for organoid isolation. For a small pellet (~50 µL volume) use 200 µL of BME, while for a large pellet (~200 µL volume) use 800 µL of BME. Mix the cells and BME on ice using a p200 pipette until the solution appears homogenous while avoiding creating bubbles in the solution.
- Spot a 100 µL dome in the center of a well of a pre-warmed 12 well plate using a p200 pipette. Repeat this until all of the BME solution have been dispensed. Carefully transfer the plate to the 37 °C incubator to allow the BME gel to solidify.
- After 10 min, retrieve the plate and add 1 mL of pre-warmed organoid complete media per well. Dispense the media on the side of the well to avoid disruption of the BME dome.
- Observe the cell fragments using an inverted tissue culture microscope using a 4x lens in brightfield.
NOTE: Single cells and microscopic tissue fragments should be clearly visible. A successful isolation is characterized by the appearance of more than 10 organoids after 24–48 h; the culture should be confluent within one week. As tumor specimens are heterogenous, some organoid isolations are more challenging as only a few organoids grow per well, as shown in Figure 1. In this case, allow the culture to continue for up to two weeks to maximize the number of cells available for passaging. To account for media consumption and evaporation during culture, top up the cultures with 200 µL of pre-warmed organoid complete media every 5 days.
3. Passaging of PDAC Organoids
- Retrieve the plate from tissue culture incubator. With a sterile cell lifter, gently lift the BME dome such that it is floating in the complete media. Avoid scraping the bottom of the well so as to not remove any monolayer cells attached to the plastic, as these are typically fibroblasts.
- With a p1000 pipette, carefully transfer the BME dome and media to a 15 mL conical tube. Repeat this step for every organoid-containing well.
- Gently wash each well that was harvested with 1 mL of cold basal media, and transfer to the 15 mL tube containing the organoids.
- Thoroughly mix the solution and organoids with a p1000 pipette and spin down at 200 x g for 5 min. After spinning, a BME layer containing organoids in suspension and an organoid pellet will appear at the bottom of the tube. Carefully remove the supernatant, avoiding loss of the BME/organoid layer. Place the tube on ice.
- Add 10 mL of ice-cold cell recovery solution (CRS) to the tube and thoroughly mix by inversion. This will depolymerize the protein matrices of the gelled BME at 4 °C. Incubate on ice for 30 min while mixing every 3 min by inversion. If available, place the tube on a rotating mixer in a cold room or 4 °C fridge for 30 min.
- After the 30 min incubation, spin down at 200 x g for 5 min. The organoid pellet should be apparent while the BME layer should be gone. If the BME layer is decreased in size but still visible, incubate for an additional 30 min at 4 °C with mixing and repeat spin.
- Once the BME has been depolymerized, remove the CRS leaving behind the organoid pellet. Wash the organoids with 10 mL basal media by mixing with inversion. Spin down at 200 x g for 5 min and remove the supernatant. Place the tube with the organoid pellet on ice for at least 5 min.
- Optionally, if a single cell preparation is desired, incubate the organoids with 3 mL trypsin supplemented with 30 µL of 10 mg/mL DNAse I solution to avoid clumping of cells during digestion.
- Incubate the enzymatic reaction at 37 °C with gentle inversion mixing every 2 min for up to 10 min. Monitor and confirm successful single cell dissociation under brightfield microscope.
- To stop the enzymatic reaction, add 10 mL of ice cold basal media and spin down at 200 x g for 5 min.
- Wash cells with 10 mL basal media by mixing with gentle inversion. Spin down at 200 x g for 5 min and remove the supernatant and repeat the wash one more time. Place the tube with the cell pellet on ice for at least 5 min.
NOTE: We recommend performing this step every 3-5 passages during regular maintenance of the organoids to generate homogeneous culture with a large number of organoids.
- Add ice cold BME to the cell pellet and mix gently on ice until solution is homogenous using a p200 pipette. While avoiding generating bubbles in the mixture, pipette up and down at least 5–10x, placing the tip of the pipette close to the bottom of the tube to help mechanically break up the organoids. As a guide, use 4–6x the volume of the BME/cell pellet such that the splitting ratio is no more than 1:2 from one passage to the other.
- Spot a 100 µL dome in the center of a well of a pre-warmed 12 well plate using a p200 pipette; repeat until all of the BME solution has been dispensed. Carefully transfer the plate to the 37 °C incubator to allow the BME gel to solidify. After 10 min, retrieve the plate and add 1 mL of pre-warmed organoid complete media per well. Dispense the media on the side of the well to avoid disruption of the BME dome.
- Organoids should reform and start growing within 24 h. Organoid cultures are typically passaged ever 7-10 days depending on the culture density and cell proliferation. If necessary, top up the cultures with 200 µL of pre-warmed organoid complete media every 5 days to compensate for growth factor depletion and evaporation.
4. Freezing and Thawing of PDAC Organoids
- To freeze down the organoids, proceed to harvest the organoids and depolymerize the BME as described in steps 3.1–3.7.
- To the cell pellet, add 1 mL of freezing media, mix gently, and transfer the mixture to a pre-labeled cryovial.
- Place the cryovial in a freezing container to maintain a safe constant temperature decrease and place in a -80 °C freezer. After 24 to 48 h, transfer the frozen vials to liquid nitrogen storage. Organoids can be cryopreserved for months to years using this method.
- To thaw the organoids, retrieve the frozen cryovial from liquid nitrogen storage. Transport the frozen vial on dry ice to the tissue culture room.
- Place the frozen cryovial in the 37 °C water bath to rapidly thaw the organoids and transfer the contents of the vial to a 15 mL conical tube containing 9 mL of basal media warmed to room temperature.
- Spin down at 200 x g for 5 min and remove the supernatant. Place the tube with the organoid pellet on ice for at least 5 min.
- Proceed to resuspend in BME and plate the organoids as described in steps 3.9–3.11.
NOTE: Organoid cultures recover slowly after a freeze/thaw cycle, therefore cultures may be grown for up to two weeks before passaging.
5. Characterization of PDAC Organoids
NOTE: The characterization of the organoids should be performed on an established culture after several passages to diminish the risk of contamination from non-epithelial cell types such as fibroblasts and immune cells.
- Nucleic acid extraction from PDAC organoids
- Plate organoids on a 12 well plate dedicated to nucleic acid extraction. Plate no more than 100 µL of BME per well. For adequate DNA/RNA yield, plate at least 2–4 wells per culture. Grow organoids for up to 5 days until cultures are close to confluent but devoid of the excessive cell debris that accumulates in longer term cultures.
- Retrieve the plate from the 37 °C incubator and completely remove all trace of organoid complete media, leaving only the BME dome containing the organoids on the plate.
- Add 900 µL of acid phenol reagent (see Table of Materials) to each well and mix thoroughly using a p1000 pipette until solution becomes homogeneous. The BME will be completely dissolved in the acid phenol reagent and organoids will lyse after a short 5 min incubation.
CAUTION: Acid phenol is a hazardous chemical that can cause chemical burns. Handle with care using appropriate protections and technique. - Transfer the homogenous solution to a 2 mL tube and add 200 µL of chloroform. Incubate 5 min and centrifuge at 12,000 x g for 15 min at 4 °C.
- Proceed to the RNA and DNA extraction according to manufacturer's protocol. RNA can be extracted from the aqueous phase while DNA can be extracted from the interphase and organic phase. Once purified and quantified, RNA and DNA isolated from different wells of the same culture can be pooled to increase yield.
NOTE: (1) While we strongly recommend using this nucleic acid extraction method for RNA, there are many good methods for isolating DNA from cultured cells. (2) To ascertain the presence of tumor cells within the organoid culture, we recommend sequencing the DNA using your preferred next generation sequencing method to identify mutations within PDAC hallmark genes (KRAS, TP53, SMAD4, CDKN2A).
- Pharmacotyping of PDAC organoids
- Isolate single cells from organoids as described above in steps 3.1–3.8. To maximize cell number, harvest at least 10 confluent wells of a 12 well plate
- Resuspend single cells in 1 mL human organoid complete media. The presence of small cell clumps (~2–10 cells) is acceptable, however larger cell clumps will negatively affect the downstream analysis.
- Count cells using an automated cell counter and record cell viability. Calculate the total number of cells and viable cells present in the 1 mL suspension.
- For therapeutic testing, plate 1,000 viable cells per well of a 384 well plate. For a 384 well plate we estimate we will use 400,000 viable cells (calculated for 400 wells).
- Prepare cells for plating by mixing on ice 800 µL of BME with 7.2 mL of organoid complete media containing the cells. Keep mixture on ice and plate 20 µL per well of a 384 well plate. Use a 12-channel pipette and reservoir kept on ice to efficiently plate the cells. To avoid excessive evaporation from the plate, the outer wells can be used as a reservoir (60 µL PBS or water per well), but this will lead to a loss of 76 experimental wells.
- Spin the plate down at 100 x g for 1 min in a swing bucket. This allows the small 20 µL volume and organoids to settle at the bottom of the plate.
- Place plate in the 37 °C tissue culture incubator to allow organoids to form. After 24 h,check for presence of organoids using a brightfield microscope.
- Proceed to dosing therapeutic compounds dissolved in DMSO onto the plate using a drug printer or equivalent instrument. Test each drug dose in at least triplicate wells. To perform an effective dose-response analysis, determine dose range for each drug empirically, starting with a low, ineffective, dose and ending with a high dose where maximum effect is observed. Examples of dose ranges for chemotherapeutic compounds have been recently published9.
- Expose the cells to the therapeutic compounds for 3–5 days.
- Optionally, at the end of the assay, image the plate to evaluate the therapeutic effect on organoid size, number, and morphology.
- Assess viability using 20 µL per well of luminescence cell viability reagent (see Table of Materials) according to manufacturer's protocol. A luminometer will be necessary for data acquisition and a graphing software for data analysis.
Results
To illustrate the challenges associated with isolating organoids from PDAC, we show the establishment of a patient derived organoid culture from a small hypocellular tumor sample. After initial plating, only a few organoids were visible per well, as shown in Figure 1. Organoids were allowed to grow larger over the span of 2 week and were passaged according to our protocol to establish a more robust culture, as shown in the early and late passage 1 representative pictures (Figure 1). It is important to note that the larger cystic organoids observed in the late primary isolate were easily broken down into smaller fragments during the mixing of organoids with ice-cold BME, as described in step 2.13.
To demonstrate the outcome of the pharmacotyping protocol, we prepared single cells from an established and fast growing representative PDAC organoid as described in this protocol. 1,000 viable cells were plated per well and allowed to recover over 24 h before cytotoxic chemotherapeutic agents, Gemcitabine and Paclitaxel, were dosed. We performed a 9-point dose response assay in triplicate starting with a low dose of 100 pM and ending with a high dose of 2 µM. After 5 day treatment, representative pictures were taken for vehicle (DMSO), 2 µM Gemcitabine, and 2 µM Paclitaxel treated wells (Figure 2). Immediately after taking the pictures, cell viability was assessed using luminescence cell viability reagent and plotted using graphing software (Figure 2).
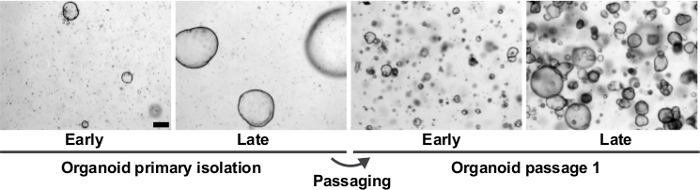
Figure 1: Representative pictures are shown for a PDAC organoid isolation as well as after the first passage. Both early (1–3 days) and late (7–10 days) time points are shown to illustrate organoid growth over time. Scale bar = 200 µm. Please click here to view a larger version of this figure.
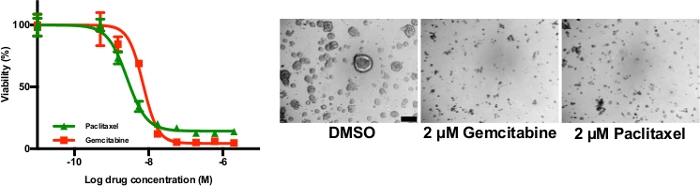
Figure 2: Dose response analysis. (Left) Representative dose response analysis obtained using an established PDAC organoid culture, with standard deviation of triplicates shown as error bars. (Right) Pictures illustrating the effect at the end of the assay of vehicle (DMSO) treatment as well as 2 µM Gemcitabine and 2 µM Paclitaxel. Scale bar = 100 µm. Please click here to view a larger version of this figure.
Discussion
Here, we present current protocols for isolating, expanding and characterizing patient-derived PDAC organoids. Our current success rate of establishing organoid culture is over 70%; therefore, these methods have not yet been perfected and are expected to improve and evolve over time. Important consideration should be given to sample size, as PDAC has a low neoplastic cellularity. Consequently, small specimens will contain few tumor cells, and will only generate a handful of organoids. Additionally, many patients receive chemotherapy and/or chemoradiation-based neoadjuvant treatment prior to surgical intervention15. If the treatment is effective for a particular patient, the tumor tissue may be devoid of viable cells. Acquisition of chemo-naive patient samples is preferred for initial optimization of these methods, but this is not always possible. Interestingly we have found that ischemia time following surgical removal of the tumor tissue is not a major criterion for successful organoid isolation, as long as the sample is processed within 24 h.
Pancreatic ductal adenocarcinoma is a disease characterized by a strong desmoplastic reaction and deposition of a dense stromal matrix. While organoids are an excellent tool for the rapid isolation and expansion of the epithelial compartment, the model does not recapitulate the complex stroma of PDAC. Other methodologies such as patient derived xenografts16 or air liquid interface culture17 allow for a stromal compartment, however they may be challenging to expand quickly. When choosing a model system, the researcher should carefully consider the strengths and weaknesses of each6.
The heterogeneous biology of this disease impacts organoid establishment as some patient-derived organoids grow extremely well in our conditions while other are much slower by comparison. The protocols above describe a Wnt ligand rich condition to isolate and expand all patient-derived organoids, yet others have shown that some patient's tumors are able to grow in the absence of Wnt conditioned media11,12. Further testing will be required to determine if using a range of media conditions enhances the successful establishment of organoids, as was recently demonstrated for ovarian cancer organoids18. This multiplex approach is however limited by the low number of tumor cells that can be isolated from small patient samples. Additionally, normal untransformed ductal organoids can arise from an organoid isolation, particularly if the tumor tissue is adjacent to normal tissue9. To reduce the risk of normal organoid contamination, larger tissue samples can be subdivided into smaller independent fragments using morphological differences such as well vascularized (blood is visible) versus hypovascular regions, and hard nodules versus soft tissue.
The methods and protocols described here are the current standard approaches used in our laboratory for organoid isolation and they should be tested and adapted for each laboratory environment. For instance, the enzymatic dissociation (steps 2.6 to 2.9) of the tumor tissue is particularly important to optimize. Small equipment differences (nutator vs rotator mixer) can lead to significantly different timing for this step. Furthermore, the tissue dissociation can be fine-tuned by increasing or reducing the concentration of the Collagenase/Hyaluronidase mixture. Care must be taken to not treat all samples in the same manner. For example, in some cases organoids can be isolated from ascites fluid from advanced PDAC patients without mechanical or enzymatic dissociation.
DNA sequencing is the current gold standard to determine the presence or absence of tumor organoids as PDAC is driven by frequent mutations in KRAS, TP53, SMAD4 and CDKN2A. Transcriptomic analysis can reveal different tumor subtypes while pharmacotyping can uncover patient-specific therapeutic vulnerabilities9. These protocols enable PDAC researchers to develop their own library of patient-derived organoids and to profile the biology of these models.
Disclosures
The authors have nothing to disclose.
Acknowledgements
We are grateful for the support of the UC San Diego Moores Cancer Center Biorepository and Tissue Technology Shared Resource, members of the Lowy laboratory, and the UC San Diego Department of Surgery, Division of Surgical Oncology. AML is generously supported by NIH CA155620, a SU2C CRUK Lustgarten Foundation Pancreatic Cancer Dream Team Award (SU2C-AACR-DT-20-16), and donors to the Fund to Cure Pancreatic Cancer.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 12 channel pipette (p20, p100, or p200) with tips | |||
| 12 well plates | Olympus | 25-106 | |
| 15 ml LoBind conical tubes | Eppendorf | EP0030122208 | |
| 15 ml tube Rotator and/or nutator | |||
| 37 °C CO2 incubator | |||
| 37 °C water bath | |||
| 384 well plates | Corning | 4588 | Ultra low attachment, black and optically clear |
| A 83-01 | TOCRIS | 2939 | |
| ADV DMEM | ThermoFisher | 12634010 | |
| Animal-Free Recombinant Human EGF | Peprotech | AF-100-15 | |
| Automated cell counter | |||
| B27 supplement | ThermoFisher | 17504044 | |
| Cell Recovery Solution | Corning | 354253 | Reagent that depolymerizes the Basement Membrane Extract at 4 °C |
| CellTiterGlow | Promega | G7570 | Luminescence cell viability reagent |
| Chloroform | Sigma | C2432 | |
| Computer | |||
| CryoStor CS10 | StemCELL Tech | 07930 | Cell Freezing Solution |
| Cultrex R-spondin1 (Rspo1) Cells | Trevigen | 3710-001-K | |
| DMEM | ATCC | 30-2002 | |
| DNase I | Sigma | D5025 | |
| Drug printer | Tecan | D300e | This is the drug printer we use in our laboratory |
| Excel | For data analysis | ||
| Extra Fine Graefe Forceps | Fine Science Tools | 11150-10 | |
| FBS | ThermoFisher | 16000044 | |
| G-418 | ThermoFisher | 10131035 | |
| Gastrin I (human) | TOCRIS | 3006 | |
| Gentle Collagenase/hyaluronidase | STEMCELL Tech | 7919 | |
| GlutaMAX | ThermoFisher | 35050061 | Glutamine solution |
| GraphPad Prism | For data analysis | ||
| HEPES | ThermoFisher | 15140122 | |
| Laminar flow tissue culture hood | |||
| Luminometer | |||
| L-Wnt-3A expressing cells | ATCC | CRL-2647 | |
| MACS Tissue Storage Solution | Miltenyi biotec | 130-100-008 | |
| Matrigel Matrix | Corning | 356230 | Basement Membrane Extract (BME), growth factor reduced |
| Mr. Frosty Freezing Container | ThermoFisher | 5100-0001 | |
| N-Acetylcysteine | Sigma | A9165 | |
| Nicotinamide | Sigma | N0636 | |
| p1000 pipette with tips | |||
| p200 pipette with tips | |||
| PBS | ThermoFisher | 10010049 | |
| Penicillin/Streptomycin | ThermoFisher | 15630080 | |
| primocin | InvivoGen | ant-pm-2 | |
| Rapid-Flow Filter Units (0.2 µm) | ThermoFisher | 121-0020 | |
| Recombinant Human FGF-10 | Peprotech | 100-26 | |
| Recombinant Murine Noggin | Peprotech | 250-38 | |
| Sterile Disposable Scalpels, #10 Blade | VWR | 89176-380 | |
| Tissue culture centrifuge | |||
| Tissue Culture Dishes 10 cm | Olympus | 25-202 | |
| TRIZol | ThermoFisher | 15596018 | Acid Phenol solution |
| TrypLE Express | ThermoFisher | 12605010 | |
| Y-27632 | Sigma | Y0503 | |
| Zeocin | ThermoFisher | R25001 |
References
- Siegel, R. L., Miller, K. D., Jemal, A. Cancer statistics, 2018. CA: A Cancer Journal for Clinicians. 68 (1), 7-30 (2018).
- Khorana, A. A., Mangu, P. B., Katz, M. H. G. Potentially Curable Pancreatic Cancer: American Society of Clinical Oncology Clinical Practice Guideline Update Summary. Journal of Oncology Practice. 13 (6), 388-391 (2017).
- Winter, J. M., et al. 1423 pancreaticoduodenectomies for pancreatic cancer: A single-institution experience. Journal of Gastrointestinal Surgery. 10 (9), 1210-1211 (2006).
- Von Hoff, D. D., et al. Increased survival in pancreatic cancer with nab-paclitaxel plus gemcitabine. New England Journal of Medicine. 369 (18), 1691-1703 (2013).
- Conroy, T., et al. FOLFIRINOX versus gemcitabine for metastatic pancreatic cancer. New England Journal of Medicine. 364 (19), 1817-1825 (2011).
- Baker, L. A., Tiriac, H., Clevers, H., Tuveson, D. A. Modeling pancreatic cancer with organoids. Trends in Cancer. 2 (4), 176-190 (2016).
- Sato, T., et al. Single Lgr5 stem cells build crypt-villus structures in vitro without a mesenchymal niche. Nature. 459 (7244), 262-265 (2009).
- Boj, S. F., et al. Organoid models of human and mouse ductal pancreatic cancer. Cell. 160 (1-2), 324-338 (2015).
- Tiriac, H., et al. Organoid Profiling Identifies Common Responders to Chemotherapy in Pancreatic Cancer. Cancer Discovery. 8 (9), 1112-1129 (2018).
- Tiriac, H., et al. Successful creation of pancreatic cancer organoids by means of EUS-guided fine-needle biopsy sampling for personalized cancer treatment. Gastrointestinal Endoscopy. , (2018).
- Seino, T., et al. Human Pancreatic Tumor Organoids Reveal Loss of Stem Cell Niche Factor Dependence during Disease Progression. Cell Stem Cell. 22 (3), 454-467 (2018).
- Huang, L., et al. Ductal pancreatic cancer modeling and drug screening using human pluripotent stem cell- and patient-derived tumor organoids. Nature Medicine. 21 (11), 1364-1371 (2015).
- Walsh, A. J., Castellanos, J. A., Nagathihalli, N. S., Merchant, N. B., Skala, M. C. Optical Imaging of Drug-Induced Metabolism Changes in Murine and Human Pancreatic Cancer Organoids Reveals Heterogeneous Drug Response. Pancreas. 45 (6), 863-869 (2016).
- Zhao, C. Wnt Reporter Activity Assay. Bio-Protocol. 4 (14), 1183(2014).
- Conroy, T., et al. FOLFIRINOX or Gemcitabine as Adjuvant Therapy for Pancreatic Cancer. New England Journal of Medicine. 379 (25), 2395-2406 (2018).
- Jimeno, A., et al. A direct pancreatic cancer xenograft model as a platform for cancer stem cell therapeutic development. Molecular Cancer Therapeutics. 8 (2), 310-314 (2009).
- Neal, J. T., et al. Organoid Modeling of the Tumor Immune Microenvironment. Cell. 175 (7), 1972-1988 (2018).
- Kopper, O., et al. An organoid platform for ovarian cancer captures intra- and interpatient heterogeneity. Nature Medicine. 25 (5), 838-849 (2019).
Reprints and Permissions
