The present protocol establishes a circulating glioma model by the lateral ventricle injection to investigate the therapeutic effect of chimeric antigen receptor T-cell therapy in vivo.
Method Article
Circulating Glioma Model for Chimeric Antigen Receptor T-Cell Therapy Investigations
* These authors contributed equally
In This Article
Summary
Abstract
Circulating tumor cells in cerebrospinal fluid (CSF) are a significant factor in tumor recurrence and intracranial metastasis in glioma. Many studies are attempting to identify effective strategies to target and eliminate the circulating tumor in CSF. Chimeric antigen receptor (CAR) T-cell therapy has been frequently used for various circulating tumors. However, research is limited due to the lack of a suitable circulating glioma model. Here, a circulating glioma model was developed and applied in CAR T-cell therapy investigations. This model was constructed using the lateral ventricle injection, which is widely used in the local treatment of intracranial disease. The glioma cells were injected into the lateral ventricle to form the intracranial primary tumor. The tumors that were shed from the lateral ventricle were used to indicate the circulating tumor in CSF. The model is easy to build and can be applied in various studies on the CAR T-cell therapy of circulating glioma. As a result, the circulating glioma model provides a unique glioma metastasis model for effective CAR T-cell therapy studies of the circulating tumor.
Introduction
Glioma is the most common primary malignant brain tumor in adults1,2. Current treatments, including surgery, radiotherapy, and chemotherapy, show limited efficacy, with a median survival of only 14-15 months3,4,5. Circulating glioma cells in CSF play a crucial role in tumor recurrence and intracranial metastasis6,7. Hence, there is an urgent need to develop more effective treatment strategies to eliminate the circulating glioma cells.
Recent research on glioma has mainly focused on intracranial primary tumors8,9. However, the most important problem that needs to be addressed in the clinic is how to target and eliminate the circulating glioma cells. Therefore, studies on the circulating glioma before or after surgery need more attention. Chimeric antigen receptor (CAR) T-cell therapy is the most common strategy used in studies on circulating tumor cells10,11. However, due to the special anatomical structure of intracranial tumors, it is difficult to develop a suitable circulating glioma model, which is critical for the study of circulating glioma12,13,14,15,16.
This study has generated a unique circulating glioma model based on the lateral ventricle injection. In this model, the glioma cells are injected into the lateral ventricle, and the intracranial primary tumor and circulating tumor in CSF are detected by in vivo bioluminescent imaging and flow cytometry analysis in day 10. CAR-T therapy was initiated when the tumor burden in the circulating glioma model mice reached approximately 6.5 × 10⁵p/s. Tumor burden was monitored every 5 days to assess the therapeutic effect of CAR-T cells. This model mimics the tumor cell desquamating state of glioma patients and can be used in various studies on circulating glioma.
Protocol
The animal experiments in this study were all approved and supervised by the Institutional Review Board and the Animal Ethics Committee of Nanjing Medical University (IACUC-1905048). C57BL/6J female mice, aged 6-8 weeks old, were used for the present study. The reagents and the equipment used are listed in the Table of Materials.
1. Animal preparation
- House the mice in a barrier, 12 h/12 h light/dark cycle, ambient temperature of 24 °C, and relative humidity of 50% cage.
- Weigh the mice, and anesthetize them (following institutionally approved protocols) with an intraperitoneal injection of 50 mg/kg pentobarbital sodium and 10 mg/kg xylazine17.
NOTE:The combination of pentobarbital sodium and xylazine is widely used in mouse stereotaxic injection procedures.Proper anesthetization was confirmed by the lack of response to a toe pinch, ensuring that the animal was fully unconscious prior to surgery. To prevent corneal dryness and damage, veterinary ophthalmic ointment was applied to the eyes during anesthesia. - Remove the hair on the head of a mouse with a laboratory animal shaver and fix the head and limbs of the mouse on the stereotaxic apparatus.
- Sterilize the head of the mouse using the iodophor with a cotton swab, and cover the rest of the body of the mouse with the sterile surgical towel.
- Cut the scalp about 1 cm along the midline on the top of the right forehead with a scalpel.
NOTE:All surgical instruments should be properly sterilized before use to prevent infection. Care should be taken to handle instruments with caution to avoid injury, and all procedures should be performed in a sterile environment. - Adjust the nasal clip and the ear rod, making sure that the height difference of the Z-axis between the lambda suture and the bregma is less than or equal to 0.05 mm.
2. Construction of the circulating glioma model
- Mark the point 1.5 mm to the right side of the midline and 1.1 mm to the posterior side of the bregma using a cotton swab dipped with gentian violet (coordinates: AP -1.1 mm, ML -1.5 mm from bregma).
- Using a miniature cranial drill with a diameter of 0.5 mm, drill holes at the target coordinates to expose the dura mater.
- Rinse with saline to remove bone debris.
- Draw up 5 µL of tumor cell suspension using a microsyringe with depth-limiting stopper (GL261-Luc-Gfp, 1×10⁵ cells/µL in PBS containing 0.1% BSA).
- Insert the needle at a rate of 0.2 mm/s to a depth of 3.0 mm and return the needle by 0.5 mm, pause for 10 s to stabilize tissue pressure.
- Inject cells at 1 µL/min using a calibrated microinjection pump, with a 10-min dwell time post-injection to minimize backflow.
- Withdraw the microsyringe slowly, apply pressure to the injection site with a sterile cotton swab for 30-60 s.
- Suture the scalp with absorbable surgical suture (6-0), and re-disinfect the incision with iodophor.
- Place the mouse on a precision-controlled 37 °C heating pad for rewarming and monitor its health status.
- Return the mouse to a clean cage after demonstrating sustained righting reflex and spontaneous locomotion.
- Image the mouse with an in vivo bioluminescent imaging system (IVIS Spectrum) to detect the transplanted tumor on the 10th day after tumor-bearing.
- Inject the mouse intraperitoneally with D-luciferin potassium salt (150 mg/kg).
NOTE:Dilute D-Luciferin potassium salt using sterile D-PBS. - Induce anesthesia using 2% isoflurane in 1 L/min O2 during the 10-min waiting period.
NOTE: Isoflurane should be used in a ventilated chemical hood to minimize exposure to anesthetic vapors. This is to ensure the safety of both the animals and the researchers during the procedure. - Maintain anesthesia at 1.5% isoflurane via nose cone.
- Perform bioluminescent imaging using the IVIS Spectrum.
- Perform CSF collection by puncturing the cerebellomedullary cistern in the mouse.
NOTE:CSF was collected by puncturing the cerebellomedullary cistern in mice under isoflurane anaesthesia. All procedures, including anaesthesia, surgical exposure, and sample collection, were performed under SPF conditions to minimize contamination and infection risk. Mice were placed in a prone position on a stereotaxic frame, and the cisterna magna was carefully exposed under a dissecting microscope. A 27 G Hamilton syringe needle was used to puncture the cistern and collect CSF using a free-hand technique. Approximately 5-10 µL of clear CSF was obtained from each mouse. To further reduce the risk of infection, the surgical site was sterilized with Iodophor prior to puncture, and all surgical instruments were autoclaved. Following CSF collection, the puncture site was gently compressed with sterile cotton to stop any fluid leakage. Mice were then placed on a warming pad and continuously monitored until full recovery from anaesthesia. Postoperative analgesics were administered to alleviate discomfort. Animals were observed daily for at least three consecutive days to ensure the absence of neurological symptoms or signs of infection. - Perform flow cytometry to detect tumor cells in CSF.The GFP+ population represents tumor cells.
NOTE: The murine glioma cell line GL261 has been engineered to carry the luciferase (Luc).When the fluorescence value reaches ~5 × 10⁵p/sand tumor cells are detected in the CSF, the procedure is successful.The imaging software used was Living Image 4.5.2, and the imaging parameters were set to Luminescent. - Select the mice with successful tumor-bearing to evaluate CAR-T cell therapeutic efficacy.
3. Treatment of circulating glioma by CAR-T cell injection into the lateral ventricle
- When the tumor size in the circulating glioma model mice becomes ~6.5 × 10⁵ p/s, select these mice for CAR-T treatment.
- Weigh the circulating glioma model mice, and anesthetize the mice with an intraperitoneal injection of 50 mg/kg pentobarbital sodium and 50 mg/kg xylazine.
- Repeat the process of steps 1.3−1.5.
- Separate the scalp and skull, and precisely pinpoint the drilling hole made during the construction of the circulating glioma model,and follow the procedure mentioned in steps 2.2-2.3.
- Aspirate 10 µL of CAR-T cell suspension with a micro syringe, carefully insert the needle into the lateral ventricle of the mouse, adjust the injection depth using the stereotactic apparatus, and slowly administer the CAR-T cell solution.
NOTE: Consistent with the injection of GL261 cells, CAR-T cells were injected into the right lateral ventricle (coordinates: AP -1.1 mm, ML -1.5 mm from bregma), with an injection depth of 2.5 mm.The control group was treated with PBS instead of CAR-T cells. - Retain the needle for 10 min, then slowly remove the needle and lightly press the injection point with sterile gauze to prevent any bleeding after completing the injection. Suture the scalp with absorbable surgical suture (6-0), and disinfect the incision.
- Place the mouse on a precision-controlled 37 °C heating pad for rewarming and monitor its health status.
- Return the mouse to a clean cage after demonstrating sustained righting reflex and spontaneous locomotion.
- Perform in vivo bioluminescent imaging to monitor the growth of tumors in mice.Optical imaging allows for the evaluation of CAR-T cell therapeutic efficacy.
- Weigh the mice every other day, and perform BLI imaging every 5 days to more accurately track tumor growth until the terminal endpoint is reached.
- Euthanize the mouse and fix the brain tissue in 4% paraformaldehyde for 24-48 h.
- Embed the tissues in paraffin and section them into 5 µm thick slices.
- Deparaffinize the sections, rehydrate through graded alcohols, stain with hematoxylin, counterstain with eosin, and mount the sections with a coverslip.
NOTE: For the present study, the terminal endpoint was day 30, and the mice were euthanized by an overdose of pentobarbital sodium with an intraperitoneal injection.The mouse carcasses were handed over to the Medical Experimental Animal Center of Nanjing Medical University for disposal. Discarded needles were placed in a sharps container and handed over to the Laboratory and Equipment Management Department of Nanjing Medical University for centralized disposal.
Results
The schematic diagram of the circulating glioma model for CAR-T therapy is shown in Figure 1. CAR-T cells were injected into the lateral ventricle using a microsyringe to demonstrate their therapeutic effect. This method allows direct delivery of the CAR-T cells to the brain, targeting the circulating glioma cells. The injection procedure was performed on day 11, following the implantation of GL261 cells into the mouse lateral ventricle. At various time points (days 15, 20, 25, and 30), tumor response was monitored using in vivo bioluminescence imaging and flow cytometry to detect GFP+ tumor cells in the CSF, thereby confirming the successful administration of CAR-T cells.
The experimental timeline is outlined in Figure 2A. As seen in Figure 2B,C, tumors in the CAR-T group were significantly smaller compared to the control group, suggesting that CAR-T therapy effectively reduced tumor size. To further confirm the successful ventricular delivery and antitumor effects of CAR-T cells, histological analysis was performed on brain sections. H&E staining (Figure 2D) revealed a significant reduction in tumor burden compared to untreated controls, with residual tumor foci predominantly localized to periventricular regions, consistent with CAR-T-mediated clearance of ventricular tumor cells. In contrast, the control group exhibited tumor expansion beyond the lateral ventricle, with tumor cells infiltrating surrounding brain tissue. A significant reduction in the proportion of circulating tumor cells (GFP+ cells) in the CSF following CAR-T therapy, further confirming the successful delivery of CAR-T cells and the reduction of tumor burden in Figure 2E.
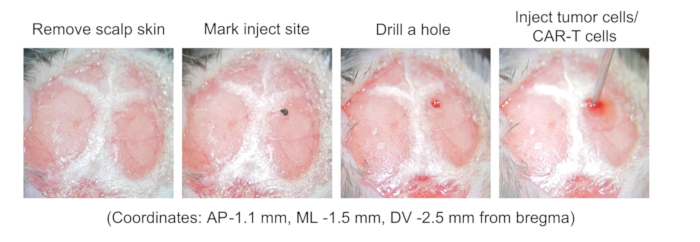
Figure 1: Schematic diagram of the injection sites for tumor cells and CAR-T cells in the circulating glioma model. Please click here to view a larger version of this figure.
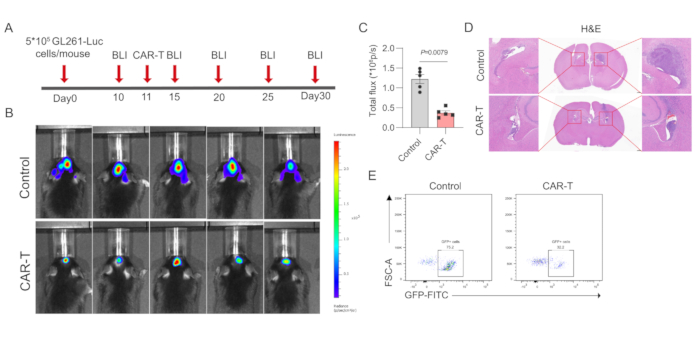
Figure 2: Schedule of the experimental design and the in vivo bioluminescent imaging of mice in the circulating glioma model. (A) The schedule of the experimental design is as follows: CAR-T cell injection was performed on day 11, and in vivo bioluminescent imaging (BLI) was conducted on days 10, 15, 20, 25, and 30. (B) The tumor size was significantly decreased on day 20 after CAR-T cell administration in the circulating glioma model, N = 5. (C) The total luminescent flux was quantified and plotted. The statistical significance was evaluated using a two-tailed Student's T-test. Results were expressed as the mean ± SEM. (D) Representative H&E staining image of brain tissue after CAR-T cell administration. The brain tissue was collected on day 30. Scale bars: 500 µm. (E) Representative flow cytometry detection of circulating tumor cells in the CSF after CAR-T cell administration on day 15. Please click here to view a larger version of this figure.
Discussion
The circulating glioma model established in this study using lateral ventricle injection provides a significant advancement, offering several advantages over existing models. The lateral ventricle injection technique is highly reproducible, enabling consistent tumor modeling in a relatively short time frame. This makes it a valuable tool for researchers seeking to investigate tumor cell dissemination into the CSF and assess the effectiveness of therapies, such as CAR-T cells. Unlike traditional intravenous CAR-T infusion, which encounters difficulties in crossing the blood-brain barrier, intraventricular injection enables precise delivery of CAR-T cells to the tumor periphery10,18. A 2024 study published in The New England Journal of Medicine reported that three patients with recurrent GBM experienced significant tumor regression within 1-5 days following novel CAR-T therapy, with one patient's tumor nearly disappearing19. Several critical steps are essential for the successful implementation of this method. Precise positioning and drilling of the cranial window, along with accurate stereotactic injection into the lateral ventricle, are crucial steps to ensure consistent tumor modeling. Use of a microinjection pump with a controlled injection rate, together with sufficient dwell time post-injection, helps to minimize backflow and ensures reliable delivery of both tumor cells and CAR-T cells.
One of the key strengths of this protocol is its ability to model the process of tumor cell shedding into the CSF, a clinically relevant phenomenon associated with glioma recurrence and metastasis. Real-time monitoring using in vivo bioluminescent imaging further enhances the method by allowing noninvasive tracking of tumor burden and therapeutic response over time. This imaging approach reduces animal-to-animal variability and allows for longitudinal studies within the same cohort. However, there are certain limitations to this method. The lateral ventricle injection requires skilled operators to avoid off-target injection, damage to brain tissue, and inconsistent cell delivery. Additionally, while the model recapitulates aspects of glioma cell dissemination in CSF, it may not fully represent the complexity of human glioma metastasis, including the interactions with immune and stromal cells in the brain microenvironment. Furthermore, the immune status and genetic background of the experimental mice may influence the reproducibility of the results.
To address these challenges, refinements such as image-guided injection or the use of genetically engineered mice may improve accuracy and biological relevance. It is also important to standardize the concentration and volume of cell suspensions and ensure consistent anesthetic and postoperative care to minimize variability. For troubleshooting, if tumor establishment rates are low, operators should verify the accuracy of stereotactic coordinates, the viability of the injected cells, and the condition of the injection apparatus.
Compared to alternative methods, such as intracranial parenchymal injection, this lateral ventricle approach more faithfully simulates tumor cell dissemination through CSF, which is particularly relevant for studies of recurrence and leptomeningeal metastasis. This method provides an efficient platform for evaluating the efficacy of local immunotherapies, including CAR-T cells, in a physiologically relevant context.
In summary, the circulating glioma model established via lateral ventricle injection offers an important tool for preclinical research. It allows for the investigation of new therapeutic strategies targeting circulating tumor cells in CSF and provides a basis for further methodological innovation. The protocol is adaptable and can be applied to studies investigating drug delivery, immunotherapy, and tumor microenvironment interactions. Future improvements should focus on increasing the physiological relevance of the model and expanding its application to other central nervous system malignancies.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
This study was funded by the National Natural Science Foundation of China (82230059), the Jiangsu Provincial Key Research Development Program of China (BE2022770).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Absorbable surgical suture | Shanghai Pudong Jinhuan Medical Products Co.,Ltd | R611 | |
| CAR-T | Creative Biolabs | ||
| D-Luciferin potassium salt | MCE | HY-12591B | |
| GL261-Luc-Gfp | Shanghai Zhong Qiao Xin Zhou Biotechnology Co.,Ltd. | ZQ0932 | |
| In vivo bioluminescent imaging system | Tanon | Tanon ABL X6 | |
| Laboratory animal shaver | Beyotime Biotechnology | FS600 | |
| Mice | Animal Core Facility of Nanjing Medical University | ||
| Microinjection pump | RWD | R462 | |
| Microsyringe | Hamilton | 87943 | |
| Mini cranial drill | RWD | 78001 | |
| Pentobarbital sodium | ChemSrc | 57-33-0 | |
| Stereotaxic apparatus | RWD | 68043 | |
| Xylazine | ChemSrc | 7361-61-7 |
References
- Lim, M., Xia, Y., Bettegowda, C., Weller, M. Current state of immunotherapy for glioblastoma. Nat Rev Clin Oncol. 15 (7), 422-442 (2018).
- Weller, M., et al. Glioma. Nat Rev Dis Primers. 10 (1), 33(2024).
- Van Den Bent, M. J., et al. Primary brain tumours in adults. Lancet. 402 (10412), 1564-1579 (2023).
- Capper, D., et al. Eano guideline on rational molecular testing of gliomas, glioneuronal, and neuronal tumors in adults for targeted therapy selection. Neuro Oncol. 25 (5), 813-826 (2023).
- Nicholson, J. G., Fine, H. A. Diffuse glioma heterogeneity and its therapeutic implications. Cancer Discov. 11 (3), 575-590 (2021).
- Schaff, L. R., Mellinghoff, I. K. Glioblastoma and other primary brain malignancies in adults: A review. JAMA. 329 (7), 574-587 (2023).
- Wang, A. P. A review of glioblastoma and other primary brain malignancies. JAMA. 330 (2), 188-189 (2023).
- Steeg, P. S. The blood-tumour barrier in cancer biology and therapy. Nat Rev Clin Oncol. 18 (11), 696-714 (2021).
- Sun, S., et al. Targeting golph3l improves glioblastoma radiotherapy by regulating Sting-NLRP3-mediated tumor immune microenvironment reprogramming. Sci Transl Med. 17 (788), eado0020(2025).
- Bagley, S. J., et al. Intrathecal bivalent CAR-T cells targeting EGFR and IL-13Rα2 in recurrent glioblastoma: Phase 1 trial interim results. Nat Med. 30 (5), 1320-1329 (2024).
- Nikanjam, M., Kato, S., Kurzrock, R. Liquid biopsy: Current technology and clinical applications. J Hematol Oncol. 15 (1), 131(2022).
- Akhoundi, M., Mohammadi, M., Sahraei, S. S., Sheykhhasan, M., Fayazi, N. CAR T cell therapy as a promising approach in cancer immunotherapy: Challenges and opportunities. Cellular Oncol. 44 (3), 495-523 (2021).
- Das, A. K., et al. T-cell therapy: A potential treatment strategy for pediatric midline gliomas. Acta Neurol Belgica. 124 (4), 1251-1261 (2024).
- Lin, H. L., Cheng, J. L., Mu, W., Zhou, J. F., Zhu, L. Advances in universal CAR-T cell therapy. Front Immunol. 12, 744823(2021).
- Lin, Y. J., Mashouf, L. A., Lim, M. CAR-T cell therapy in primary brain tumors: Current investigations and the future. Front Immunol. 13, 817296(2022).
- Zhu, Y. X., Feng, J. G., Wan, R. X., Huang, W. H. CAR T cell therapy: Remedies of current challenges in design, injection, infiltration and working. Drug Design Develop Ther. 17, 1783-1792 (2023).
- Aswendt, M., Adamczak, J., Couillard-Despres, S., Hoehn, M. Boosting bioluminescence neuroimaging: An optimized protocol for brain studies. Plos One. 8 (2), e55662(2013).
- Vaughn-Beaucaire, P., Choi, M. J., Liang, O. L., Lawler, S. E. Intracranial CAR-T cell delivery in glioblastoma patients. Trends Cancer. 10 (6), 478-480 (2024).
- Choi, B. D., et al. Intraventricular carv3-team-e T cells in recurrent glioblastoma. New England J Med. 390 (14), 1290-1298 (2024).