A protocol for the assessment of diastolic function using Doppler ultrasonography in a preclinical model of pulmonary hypertension due to left heart disease is presented.
Method Article
Pulsed Wave Doppler Assessment of Diastolic Dysfunction in the ZSF-1 Rat Model of Pulmonary Hypertension Due to Left Heart Disease
In This Article
Summary
Abstract
Diastolic dysfunction and heart failure with preserved ejection fraction (HFpEF) are significant contributors to pulmonary hypertension (PH) due to left heart disease. Standard in vivo evaluation of relaxation abnormalities in preclinical models includes two-dimensional (2D) echocardiography with Doppler assessment of transmitral flow and tissue relaxation, which is complex, expensive, and requires sophisticated echocardiographic equipment. Here, a valuable surrogate method to evaluate diastolic dysfunction in PH due to left heart disease is demonstrated in a well-established rodent model using pulsed wave Doppler ultrasound without 2D echocardiography. Diastolic transmitral flow pattern is identified from the apical window and is correlated with a simultaneously recorded ECG tracing. Indices of diastolic function are collected, and the identification of these indices is described in this protocol. This low-cost, readily implemented technique identifies relevant markers of diastolic dysfunction associated with PH, cardiovascular disease, and HFpEF. Moreover, it reproducibly detects its progression over time, when 2D echocardiography is not preferred or available. The primary limitations of this method are related to the absence of visualization of cardiac structures, the potential for inaccuracies due to the angle dependence of the Doppler signal, as well as the animal's body habitus, which can be mitigated by adjusting the location of the probe and optimizing its alignment with blood flow.
Introduction
Pulmonary hypertension (PH) is a deadly disease without a cure that is characterized by increased pulmonary blood pressure1. Left heart disease (LHD) is by far the most common cause of PH worldwide and is associated with high cost and significant morbidity2,3. Cardiac culprits of PH-LHD include multiple different entities that result in either systolic or diastolic dysfunction, such as heart failure, which is a multifaceted clinical syndrome that continues to be among the leading causes of mortality worldwide4. Among patients with heart failure, HFpEF accounts for over half of the incident-based hospital admissions4,5. Diastolic dysfunction has been identified as one of the most important precursors of, and a fundamental feature in the interplay between HFpEF and PH due to LHD (PH-LHD)6,7. Due to the lack of suitable preclinical models that recapitulate most clinical and subclinical features of PH and HFpEF, the understanding of the mechanisms underlying these diseases is incomplete7.
Diastolic dysfunction is a hallmark of PH-LHD and can be assessed by 2D and Doppler echocardiography8. Two-dimensional and Doppler methods for the assessment of left ventricular diastolic function include among other parameters the peak early diastolic E-wave velocity, peak late diastolic A-wave, mitral valve A duration (time interval from A-wave onset to end of A wave at zero baseline), mitral valve E/A ratio, E-wave deceleration time (DT, time interval from peak E-wave extrapolated to the zero-velocity baseline), tissue Doppler imaging (TDI) of the septal mitral valve annulus (e', echocardiographic parameter of tissue relaxation of the mitral valve annulus), and IVRT (isovolumic relaxation time, time between the closure of the aortic valve and the opening of the mitral valve). Echocardiographic markers of impaired relaxation include a combination of reduced or reversed E/A ratio in the setting of A-wave augmentation and E-wave reduction, prolonged IVRT, reduced E-wave deceleration time, delayed tissue Doppler indices (prolonged e' velocity, increased average septal E/e'), and a lower absolute value of global longitudinal strain (GLS)9. Studies comparing echocardiographic and invasive hemodynamic measurements have demonstrated that echocardiographic measurements and invasive measurements are comparable and are a reliable method for evaluating cardiac hemodynamics10. However, 2D echocardiography is complex, expensive, and requires sophisticated echocardiographic equipment and personnel. These factors are a major limitation in following the progression of the disease in animals. Consequently, investigators either rely on two measures (start and end of study) for longitudinal studies or single measurements in a cross-sectional study design.
Amongst these parameters of diastolic dysfunction, E, A, E/A, A duration, DT, and IVRT can be assessed by pulsed wave Doppler echocardiography, obviating the need for 2D echocardiography. In this article, a protocol for the Doppler assessment of diastolic function is demonstrated in the well-established ZSF-1 rat model of PH-LHD11. A total of 25 (10 genetically obese and 15 genetically lean) male ZSF1 rats were longitudinally followed and evaluated sonographically for the development of diastolic dysfunction for sixteen weeks between 8 and 24 weeks of age. The same echocardiographic parameters were evaluated across the two cohorts. All animals were evaluated at baseline (8 weeks of age). Doppler evidence of diastolic dysfunction was manifested by 16 weeks of age, when the interim measurements were taken. End-point measurements were taken at 24 weeks of age. While the investigator performing data collection was unable to be blinded due to the obvious weight gain in the obese cohort, the investigator performing data analysis was blinded to the animals' phenotype. While this readily implementable method offers a route for longitudinal assessment of disease progression in rodents, limitations of this technique include the angle dependence of a good-quality Doppler signal, which may be challenging to obtain depending on the probe alignment and animal size.
Protocol
All procedures were conducted in accordance with the Johns Hopkins University Animal Care and Use Committee (ACUC) approval for protocol RA21M273. No animals were exposed to discomfort for data collection or the purposes of the measurements. The reagents and the equipment used are listed in the Table of Materials.
1. Preparation of the equipment and the animal
- Clean the anesthetizing chamber with 70% ethyl alcohol and wipe down all surfaces.
- Pad the chamber with a disposable changing pad and paper towels. Ensure that the gas inflow and outflow orifices are not obstructed.
- Take the following Safety and Anesthesia Handling precautions:
- Ensure the anesthetizing station is set up in a well-ventilated area.
- Inspect the anesthesia equipment for leaks and malfunctions.
- Avoid turning on the vaporizer until the circuit is connected to the animal.
- Maintain continuous oxygen flow throughout the experiment.
- Ensure the scavenging system is continuous with the anesthetic circuit system.
- Occlude the gap between the nose cone and the animal's nose with a piece of tape to reduce anesthetic spillage and prevent escape of air contaminants into the air.
- Reduce fresh gas flow rates in the anesthetic circuit system during the maintenance phase of anesthesia. Use of the lowest possible fresh gas flow rate is recommended.
- At the conclusion of the experiment, continue to administer oxygen at a high flow rate to flush any residual anesthetic agent and the breathing system.
- Open oxygen tank (100%) and allow free flow of oxygen into the anesthetizing chamber.
- Open the animal cage and place the animal into the anesthetizing chamber.
- Securely lock the chamber.
- Open the isoflurane vaporizer and allow a free flow of 2% to 3% isoflurane into the anesthetizing chamber, mixed with oxygen (2 L/min).
- Allow the animal to inhale the oxygen-isoflurane gas mixture for up to 3 min, or until adequate depth of general anesthesia is achieved.
NOTE: Anesthesia is considered adequate when the animal does not respond to non-noxious or noxious stimuli before the commencement of the experiment, while continuing to breathe spontaneously and unlabored.
2. Obtaining an ECG tracing
- Turn on the tablet connected to the ECG tracing pad. Select RSMonitor from the available apps. Turn on the ECG pad by pressing the round button in front.
NOTE: A blinking green light indicates that the ECG Pad is pairing with the tablet. A solid green light indicates the completion of pairing. - Tap SETTINGS in the right lower corner of the user interface.
- Select PRESETS from the dropdown menu of experimental settings.
- Tap the dropdown menu under Saved Presets.
- Select Rat CV and hit OK in the bottom right corner.
NOTE: The pad should be in the "Rat" mode to allow for detection of the ECG via the paws. - Clean the ECG pad with 70% ethyl alcohol to remove any ECG gel residue.
- Get highly conductive electrode gel for the ECG, and water-soluble hypoallergenic ultrasound gel for the Doppler.
- Open the gas mixture flow to the nose cone.
- Place the anesthetized animal supine on the noninvasive ECG pad, with the nose in the appropriately sized nose cone. Set the vaporizer output between 1.5%-2% (oxygen flow at 1 L/min). Ensure the free flow of isoflurane into the nose cone.
- Turn the gas flow off towards the anesthetizing chamber.
- Apply a small amount of electrode gel to the dorsal surface of the forepaws using a cotton-tipped applicator and on the plantar side of the hind paws. Secure the paws with tape on the electrode contact surface of the ECG pad, and ensure the electrode gel has sufficient contact with the ECG pad.
NOTE: Mice need a smaller nose cone compared to rats. - Remove the animal's chest and abdominal hair using a gentle depilator cream to facilitate better skin-probe contact. Wipe off any residual depilator cream to avoid skin irritation.
NOTE: The depilatory cream should be applied for the minimal amount of time necessary and thoroughly removed to prevent skin irritation. - Ensure the isoelectric baseline and the P-QRS-T waveform on the ECG tracing are displayed on the computer monitor.
NOTE: Depending on the heart rate, P and T amplitudes may not be distinguishable from the QRS complex, and the R wave is the most important element to determine the timing of the Doppler waveforms.
3. Setup of computer
- Turn on the computer.
- Create a folder on the computer identifying the animal and the data of interest. The snapshots taken during the experiment will be saved in this folder.
- Turn on the Pulsed Doppler Transceiver device in the front and in the back (large blue box).
- Turn on the Doppler Signal Processor (small black box).
- Open the Doppler Signal Processing Workstation icon to run the software.
NOTE: The initial system settings are the following: 10 MHz or 20 MHz in System Settings, Sampling rate: 125 kHz, Sample size: 512, Low pass filter: 150 kHz, which is adequate for most experiments. - Click on Setup in the top left corner.
- Select System Setup.
- Select the appropriate probe frequency for the experiment (20 MHz for mice and small rats, 10MHz for large rats).
NOTE: The interface has two panels: an upper panel for the display of the Doppler velocity spectrograms and a lower panel to display the ECG. - Plug in the 20 MHz probe when investigating a young rat or mouse. Use a 10 MHz probe for older, bigger, or obese rats. Of note, both probes can be plugged in simultaneously, and the Doppler transceiver module allows for easy switching between the frequencies/probes (toggle switch on front).
- Set Doppler settings on the transceiver module:
- Ensure the handheld probe transducer is set to channel A or B receptacle.
NOTE: The receptacle selection will not have an impact on data acquisition, nor will it prompt changes in the software. - Select the appropriate 10/20 MHz channel to operate the 10/20 MHz handheld probe, respectively.
- Set Pulse Repetition Frequency (PRF) at 62 kHz for optimal range ambiguity to increase the maximum velocity that can be detected with PW Doppler from the most proximal sample volume while minimizing aliasing.
- Set the DIRECTION switch to TWD to display any flow coming toward the probe as a waveform above the zero-flow baseline.
NOTE: Any flow moving away from the probe will be displayed as a waveform below the zero-flow baseline. - Adjust the RANGE to 2.5 - 3.5 mm for mice and 4-6 mm for rats to select the depth at which the sample volume will be placed.
NOTE: A rat's heart is within the first 1 cm from the transducer face, while a mouse's heart is within the first 0.5 cm. Distance is measured from the skin-probe interface to the middle of the sample volume, and the range to detect transmitral flow will vary based on the animal's size, age, and body habitus. - Set FILTER to 15 to smooth the phasic velocity output to "damped", to avoid over- or underestimation of velocities and to ensure optimal estimation of velocities.
- Ensure the handheld probe transducer is set to channel A or B receptacle.
- Press GO in the top left corner of the user interface screen. A pop-up window will appear.
- In the new window, enter the relevant Acquisition Information (animal type, gender, date of birth, age on acquisition date, weight, etc.).
- Select the desired pre-created folder from the dropdown menu at Directory (for creating the folder, see step 3.2) with the animal and experiment identifiers.
- Press OK.
NOTE: The initial file number is set to _00. - Adjust the ECG baseline by shifting it upwards or downwards using the scale bar on the left (left click on the axis and drag up or down), so that the R waves are clearly visible.
NOTE: The baseline can be shifted by keeping the cursor on the ECG panel, right clicking the mouse and moving the mouse forward and backward.
4. Performing Doppler measurements
- Apply a small amount of ultrasound gel to the substernal/epigastric region of the animal's chest and abdomen to facilitate ultrasound transmission between the probe and the skin.
- Place the Doppler probe midline under the diaphragm below the sternum (just below and slightly to the left of the xyphoid), head pointing cephalad and to the left ear of the animal, and start scanning for flow by slowly moving the probe in a small circular motion with increasing radius (1mm at a time), using fine hand movement.
- Maintain gentle pressure of the probe onto the skin under the diaphragm at all times.
- If mitral flow is not detected, adjust the RANGE as needed by turning the RANGE dial in 0.5 mm increments to detect transmitral waveform (Figure 1A), repeating the circular scanning motion with each turn of the dial.
NOTE: An M-shaped diastolic antegrade flow pattern will appear above the zero baseline (when the direction switch is set to "TWD" (toward)), indicating a diastolic flow pattern that is consistent with flow across the mitral valve that occurs with opening of the mitral valve. Of note, the majority of flow should be above the baseline for a mitral valve flow pattern, while an asymmetric V-shaped waveform that is mainly below the baseline is indicative of systolic flow through a different valve, such as the aortic valve. If a waveform consistent with an aortic flow pattern is encountered, move the tip slightly to the animal's right and tilt it upwards (requires minimal movement of one millimeter or two). All signals are displayed in real-time. Diastolic flow across the tricuspid valve will appear as a similar M-shaped waveform above baseline; however, due to a lower pressure gradient between the right atrium and the right ventricle, the peak velocities will be significantly lower (Figure 1B). If a waveform is encountered that is consistent with tricuspid valve flow, slide the probe slightly to the animal's left without changing its angle in relation to the skin. - Ensure the simultaneous display of the Doppler waveform and the ECG on the screen.
NOTE: ECG sweep speed can be adjusted to a comfortable level by clicking on the up/down arrows in the bottom right corner of the panel. 4-5 beats visible per screen are optimal.
5. Obtaining data from Doppler ultrasonography
- Create snapshots using the foot pedal once the correct flow is identified. This can be repeated multiple times as needed for optimal data quality.
NOTE: An ideal image will display a clear definition of spectral borders, no spectral broadening, no spectral fill-in, no simultaneous display of forward and reverse flow, and simultaneous display of diastolic transmitral and systolic aortic flows. The snapshots are automatically saved when pressing the foot pedal. - Stop data acquisition when satisfied with data quality by clicking on the STOP button in the upper right corner of the user interface. A minimum of 3 replicates of a pair of ECG and Doppler waveforms is necessary for reliable representation of average velocities and contraction/relaxation times.
- Click on the File menu in the upper function bar.
- Select Open from the dropdown menu.
- Select the highest data quality file from the pre-created folder for analysis.
- Click on Analysis in the top left corner. A pop-up window will appear.
- Select Step 2: General Setup
- Data type: Doppler
- Signal: Mitral Inflow
- Animal: Select the appropriate model for the experiment.
- Set "All measurement names" under default measurement names.
- Select Step 2: General Setup
- Go to and click on Step 5: R peak editor from the Analysis Control dropdown menu. Select Display beat and R peak markers. Select Auto calculate.
NOTE: Green markers of the R peak will appear. Align the green markers with the tip of the R waves. Undesired beat markers can be removed from the panel by placing the cursor on the marker and performing a swift right-forward movement with the mouse while holding a right-click. - Click on Step 6: Beat editor from the Analysis Control dropdown menu. Select Display beat and R peak markers and click on Select all beats.
- Click on Step 7: Marker editor from the Analysis Control dropdown menu. Click on Display analysis markers. Select the desired parameter for measurement under "Current Marker Selected".
- Ensure that the following parameters are required for the completeness of the data (Figure 1):
- ES: early start. This is the start of the upstroke of the early diastolic flow, measured at the baseline.
- EPV: early peak velocity. The first peak velocity above the baseline reflects the left atrial (LA) - left ventricular (LV) pressure gradient during early diastole (this is the peak velocity of the passive flow from LA to LV due to the pre-existing LA-LV pressure gradient).
- EEAS: early end, atrial start. Reflects the pressure equalization and cessation of flow between the LA and LV (diastasis).
- APV: atrial peak velocity. The second peak velocity above the baseline reflects the left atrial-left ventricular pressure gradient during late diastole. This is the peak velocity of the blood flow during the "atrial kick".
- AE: atrial end. Reflects the cessation of flow at the end of late diastole, and pressure equalization between the LA-LV.
- IVCTE: isovolumic contraction time end. This is the time interval between the closure of the mitral valve and the opening of the aortic valve at the onset of systole.
- IVRT: isovolumic relaxation time starts. This is the time interval between the closure of the aortic valve and the opening of the mitral valve at the onset of diastole.
- After taking the above measurements, select Step 8: Measurement results from the Analysis Control dropdown menu.
- Copy the data into an Excel file by clicking on Copy Results to Clipboard. Save the Excel data.
- Close the "Analysis Control" window.
- Click on File in the left upper corner and select Save. This will save the performed measurements.
- Exit the Doppler Signal Processing Workstation.
- Ensure that the following parameters are required for the completeness of the data (Figure 1):
6. Ending the experiment
- Turn off isoflurane, and remove the tape from the animal's paws.
- Remove the animal from the electrode pad.
- Clean off any remaining depilator cream and electrode gel.
- Place the animal back in its cage with free access to water and food.
- Allow the animal to recover from anesthesia while being monitored as per institutional protocol.
- Turn off the oxygen.
- Clean the anesthetizing chamber.
Results
This method allows longitudinal assessment of diastolic function in PH-LHD. For the most accurate assessment of diastolic function, antegrade and retrograde flow patterns related to the opening and closing of the mitral and aortic valve need to be visualized within the same cardiac cycle over multiple cycles (Figure 1). The closure of the aortic valve marks the beginning of diastole, the earliest phase of which is the isovolumic relaxation, preceding the opening of the mitral valve and the subsequent commencement of the biphasic transmitral flow during early and late diastole. Diastole ends with the cessation of blood flow and the closure of the mitral valve. These flow pattern changes are shown in Figure 1 where the systolic transaortic flow is depicted below the zero-flow baseline, isovolumic relaxation is represented by zero flow between the closure of the aortic valve and the opening of the mitral valve, the biphasic diastolic transmitral flow is depicted as an M-shaped pattern above the baseline, followed by zero flow between the closure of the mitral valve and the opening of the aortic valve. In the absence of the simultaneous detection of the aortic or transmitral flow by spectral Doppler, isovolumic contraction and relaxation times cannot be determined.
In addition, there are multiple indices that can be determined using this model from the biphasic flow pattern (Figure 2), such as: E (normal value for rats: 72.5 cm/s ± 13.9 cm/s), A (normal value for rats: 46.9 cm/s ±15.4 cm/s), E/A ratio (normal value for rats: 1. 7 ± 0.6), and E deceleration time (DT) indicating the deceleration time of the early peak filling velocity (normal value for rats: 48.8 ms ± 13.9 ms)12. However, while these parameters are frequently utilized in humans, they have proven unreliable in rodent models13,14. In the context of this article the IVRT (normal value for rats: 25.5 ±6.3 ms), which is the time interval between the end of systole marked by the cessation of aortic flow, and the beginning of diastole, marked by the commencement of the biphasic transmitral flow, is of special interest for PH-LHD as an indicator for diastolic dysfunction in rodents and has been proven to be reliable for diastolic dysfunction in these models13,14. This diastolic dysfunction is indicated by an initially reversed, then normalized and increased E/A ratio, shortened DT, and prolonged IVRT15. Here, IVRT is a valuable descriptor of left ventricular diastolic function and reflects the speed of relaxation during the earliest, isovolumic phase of diastole. IVRT prolongation suggests an impaired, slower rate of relaxation. This has been found to be the earliest echocardiographic manifestation of PH-LHD in a HFpEF model16 (Figure 3). Additionally, end-point measurements, both 2D and Doppler echo on each animal at the conclusion of the experiment, were performed, and it was found that the measurements obtained were comparable (2D echo 22.64 ms ± 0.90 ms vs. Doppler 23.61 ms ± 1.29 ms). These IVRTs are also consistent with the data reported in the literature, obtained via 2D echo12.
In this model (ZSF1 rats), there is a prolongation of the IVRT over a period of multiple weeks, which can be detected as early as 16 weeks of age, and that continues to increase in obese animals over time, as demonstrated by using Doppler echocardiography only (Figure 3).
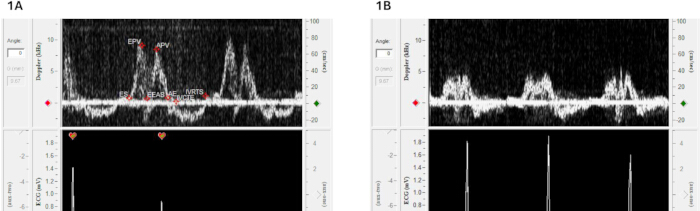
Figure 1: Representative Doppler image. (A) This figure shows a representative tracing of the Doppler signal measuring blood flow across the mitral valve (top) and the R wave of the ECG (below). (B) This figure shows a representative tracing of the Doppler signal measuring blood flow across the tricuspid valve (top) and the R wave of the ECG (below). Abbreviations: ES: early start; EPV: early peak velocity; EEAS: early end, atrial start; APV: atrial peak velocity; AE: atrial end; IVCTE: isovolumic contraction time end; IVRT: isovolumic relaxation time start. Please click here to view a larger version of this figure.
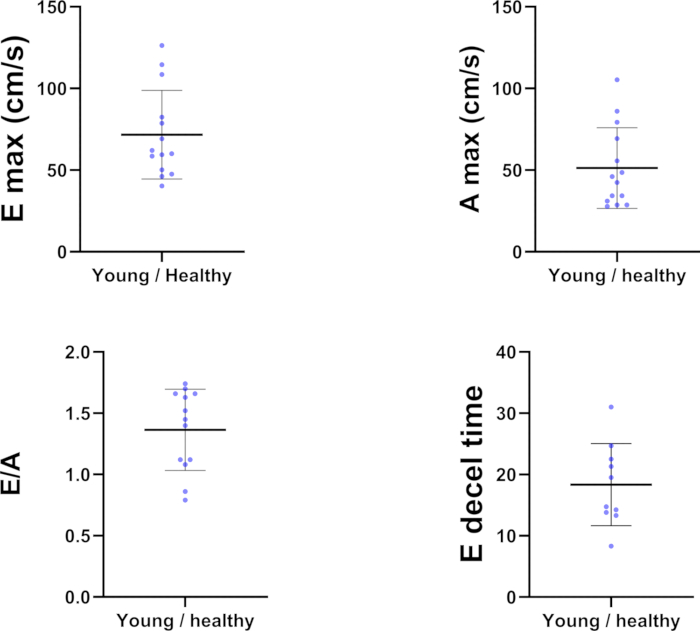
Figure 2: Doppler Indices for Mitral valve flow. Depicted here are multiple indices (mean +/- standard deviation) that can be determined from the biphasic flow pattern across the mitral valve in young (8-week-old) male healthy (lean ZSF1) rats: E (n = 14, 71.71 cm/s ± 27.14 cm/s), A (n = 14, 51.25 cm/s ± 24.69 cm/s), E/A ratio (n = 13, 1.364 ± 0.33), and E deceleration time (DT, n = 10, 18.35 ms ± 6.69 ms). Please click here to view a larger version of this figure.
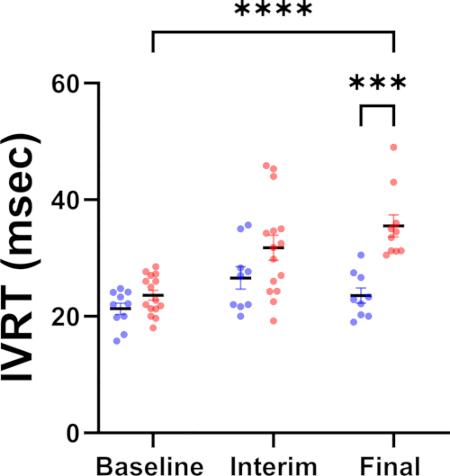
Figure 3: Longitudinal determination of IVRT. This figure shows that the isovolumic relaxation time (IVRT) increases in the ZSF1 rat model of PH-LHD during aging. The values were obtained at the following timepoints: baseline (8 weeks, lean: 21.30 ms ± 3.12 ms, obese:23.61 ms ± 3.33 ms), interim (16 weeks, lean: 26.59 ms ± 5.78 ms, obese: 31.77 ms ± 5.99 ms), and final (24 weeks of age, lean: 23.59 ms ± 3.87 ms, obese: 35.52 ms ± 5.99 ms). Blue represents lean control male rats (n = 10, 9, and 9 at baseline, interim, and final measurements), and red represents ZSF1 obese male rats (n =15, 15, and 10 at baseline, interim, and final measurements) that develop PH-LHD by 24 weeks of age. P<0.0001 by two-way ANOVA. Please click here to view a larger version of this figure.
Discussion
In this article, a surrogate method to evaluate diastolic dysfunction in PH-LHD is demonstrated in a well-established rodent model using pulsed wave Doppler ultrasound without 2D echocardiography. Diastolic transmitral flow pattern is identified from the apical window and is correlated with a simultaneously recorded ECG tracing, which allows for the determination of indices of diastolic function. This low-cost technique identifies markers of diastolic function and dysfunction longitudinally, avoiding the need for costly 2D echocardiography.
Diastolic dysfunction is a key feature of PH-LHD and is characterized by increased passive ventricular stiffness and impaired active relaxation. Decreased diastolic compliance of the left ventricle leads to increased left ventricular end-diastolic pressure (LVEDP) and pulmonary capillary wedge pressure (PCWP) at rest (≥15 mmHg) and during exercise (≥25 mmHg), which, while diagnostic of HFpEF and a precursor for PH-LHD, are challenging to determine without invasive techniques or advanced imaging modalities17,18. The current gold standard for obtaining these values is cardiac catheterization; however, this is not always feasible (e.g., longitudinal measurements) or affordable (high cost of surgery or core services) in preclinical models of PH-LHD19. Given the difficulty in obtaining those values directly, it is important to use additional markers of diastolic dysfunction that can be obtained non-invasively, like the peak rate of early filling (E), peak rate filling rate during atrial systole (A), E/A ratio, E deceleration time, and IVRT11. This can be accomplished using echocardiographic modalities, including image-guided pulse wave Doppler echocardiography, which is considered the standard noninvasive method to evaluate diastolic function both in the clinical and in the preclinical setting; however, this too is an expensive technique, especially in rodents9. Diastolic transmitral flow characteristics and their temporal relation to tissue relaxation and cardiac events can be assessed from the apical 4-chamber view using 2D echocardiography, by aligning the ultrasound beam with the blood flow, and placing the sample volume at the level of leaflet coaptation20. A major limitation of this technique is the fact that E, E/A, and IVRT are load and heart rate-dependent indices of diastolic function, hence the inherent difficulty in controlling for loading conditions. Indeed, in these studies, only heart rate control was attempted by titrating inhaled anesthetic concentration to a heart rate of 300-350 beats/min across the cohorts. Therefore, the potential for bias could not be fully eliminated13.
Using Doppler to evaluate transmitral blood flow has several advantages. First, it is a noninvasive technique that can be done in sedated animals at various timepoints without exposing the animals to surgical manipulation and its associated complications. It is suitable to assess velocities across valves and other cardiovascular structures at a precise location. The cost of the setup is only a fraction of the equipment and upkeep cost of a 2D echocardiography setup, and it can be done without core facility support or specialized training in advanced 2D echocardiography.
Limitations
The downsides of this technique are first and foremost that it is a non-image guided technique, and it may be difficult to align the ultrasound beam with blood flow across the mitral valve, with a risk of assessing tricuspid valve velocities instead of mitral valve flows21. However, the tricuspid valve annulus is larger than the mitral valve annulus; therefore, even if the pressure is equal across both valves, the flow pattern across the tricuspid valve would still be slightly less than across the mitral valve. Though with additional valve disease, a rare situation of these velocities being similar may occur, however, in the vast majority of models that focus on a single disease, it is unlikely to be identical. Also, this technique requires a dedicated operator who has practiced this on many animals to be facile with the fine motor adjustments required to obtain a reliable and valid signal. Lastly, this technique does not allow for visual inspection of other cardiac structures or function that might be relevant for a certain pathology. It is therefore most useful for investigators with training in cardiovascular science and ultrasound imaging, who would need to longitudinally follow diastolic heart function in a large number of animals, while minimizing cost. Utilizing this technique assumes an understanding of cardiac physiology and rodent anatomy.
Critical steps
To ensure good signal quality and valid measurements, proper animal positioning, probe selection and positioning, and selection of the optimal signal sampling range are required. Among the commonly encountered challenges is the difficulty in obtaining a Doppler signal. Here, it is recommended that the probe frequency be matched to the animal's body, and the ultrasound beam aligned with the blood flow to the extent possible. This is best accomplished with the ultrasound probe tip placed subcostally, just beside the xyphoid, to the left of the midline and pointed towards the left ear of the animal (see step 4.2). Signal quality is considered adequate when the spectrogram is crisp and in line with the expected flow velocities (Figure 1A). This can be improved by fine adjustment of the range of signal sampling (see step 4.4). An adequate diastolic flow pattern below the baseline warrants the setting of the "Direction" switch to "TWD" (toward). Blunted, low biphasic velocities above the baseline raise suspicion for detecting trans-tricuspidal flow (Figure 1B). Here, a slight leftward movement of the probe tip is recommended, without changing its angle in relation to the skin (see step 4.2).
An important research application of this technique is the noninvasive longitudinal assessment of diastolic function in rodent preclinical models of PH and HFpEF to identify a cohesive time course in this disease, in particular in females pre-, peri-, and post-menopause.
In summary, this low-cost technique identifies relevant markers of diastolic dysfunction associated with PH-LHD, and reproducibly detects its progression over time, when 2D echocardiography is not preferred or available. The primary limitation of this method is related to the absence of visualization of cardiac structures and the potential for inaccuracies due to the angle dependence of the Doppler signal, as well as the animal's body.
Disclosures
The authors have no financial relationships with any manufacturers of the materials used.
Acknowledgements
This work was supported by the Career Development Award of the American Heart Association to MB (24CDA1267633), an NHLBI R56 award to JS (1R56HL169285), and an NHLBI award to LS (R01HL14811201).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Anesthesia setup | VetEquip Inc. | 901806 | |
| Computer | Dell | 7420 Plus | |
| Cotton swab | Puritan Medical Products Company | 806-WC | |
| Depilator cream | Church and Dwight | 300725 | |
| Doppler probe 10 and 20MHz | INDUS Instruments | NA | |
| Doppler setup | INDUS Instruments | NA | |
| ECG pad | INDUS Instruments | NA | |
| Electrode gel | Parker Laboratories | 45993 | |
| Isoflurane vaporizer | VetEquip Inc. | 911103 | |
| Ultrasound gel | Parker Laboratories | 45659 | |
| Vented anesthetizing induction chamber | VetEquip Inc. | 942102 |
References
- Simonneau, G., et al. Haemodynamic definitions and updated clinical classification of pulmonary hypertension. Eur Respir J. 53 (1), 1801913(2019).
- Ghoreishi, M., et al. Pulmonary hypertension adversely affects short- and long-term survival after mitral valve operation for mitral regurgitation: Implications for timing of surgery. J Thorac Cardiovasc Surg. 142 (6), 1439-1452 (2011).
- Charalampopoulos, A., et al. Pathophysiology and diagnosis of pulmonary hypertension due to left heart disease. Front Med (Lausanne). 5, 174(2018).
- Dunlay, S. M., Roger, V. L., Redfield, M. M. Epidemiology of heart failure with preserved ejection fraction. Nat Rev Cardiol. 14 (10), 591-602 (2017).
- Savarese, G., et al. Global burden of heart failure: A comprehensive and updated review of epidemiology. Cardiovasc Res. 118 (17), 3272-3287 (2023).
- Thenappan, T., et al. Clinical characteristics of pulmonary hypertension in patients with heart failure and preserved ejection fraction. Circ Heart Fail. 4 (3), 257-265 (2011).
- Bauer, M., Gadkari, M., Martinez Yus, M., Santhanam, L., Steppan, J. Sexual dimorphism in animal models of heart failure with preserved ejection fraction. J Appl Physiol (1985). 138 (6), 1449-1473 (2025).
- Cameron, D. M., Mclaughlin, V. V., Rubenfire, M., Visovatti, S., Bach, D. S. Usefulness of echocardiography/Doppler to reliably predict elevated left ventricular end-diastolic pressure in patients with pulmonary hypertension. Am J Cardiol. 119 (5), 790-794 (2017).
- Nagueh, S. F., et al. Recommendations for the evaluation of left ventricular diastolic function by echocardiography and for heart failure with preserved ejection fraction diagnosis: An update from the American Society of Echocardiography. J Am Soc Echocardiogr. 38 (7), 537-569 (2025).
- Yavuz, Y. E., Soylu, A., Gurbuz, A. S. The relationship of systemic and pulmonary arterial parameters with HFPEF scores (h(2) fpef, hfa-peff) and diastolic dysfunction parameters in heart failure patients with preserved ejection fraction. J Clin Ultrasound. 52 (1), 39-50 (2024).
- Villalba-Orero, M., Garcia-Pavia, P., Lara-Pezzi, E. Noninvasive assessment of HFPEF in mouse models: Current gaps and future directions. BMC Med. 20 (1), 349(2022).
- Watson, L. E., Sheth, M., Denyer, R. F., Dostal, D. E. Baseline echocardiographic values for adult male rats. J Am Soc Echocardiogr. 17 (2), 161-167 (2004).
- Kass, D. A. Assessing and interpreting diastolic function in animal models of heart disease. J Mol Cell Cardiol. 197, 1-4 (2024).
- Schnelle, M., et al. Echocardiographic evaluation of diastolic function in mouse models of heart disease. J Mol Cell Cardiol. 114, 20-28 (2018).
- Westenberg, J. J. Cmr for assessment of diastolic function. Curr Cardiovasc Imaging Rep. 4 (2), 149-158 (2011).
- Robinson, S., et al. The assessment of left ventricular diastolic function: Guidance and recommendations from the British Society of Echocardiography. Echo Res Pract. 11 (1), 16(2024).
- Del Buono, M. G., et al. Heart failure with preserved ejection fraction diagnosis and treatment: An updated review of the evidence. Prog Cardiovasc Dis. 63 (5), 570-584 (2020).
- Little, W. C., Oh, J. K. Echocardiographic evaluation of diastolic function can be used to guide clinical care. Circulation. 120 (9), 802-809 (2009).
- Reddy, Y. N. V., Carter, R. E., Obokata, M., Redfield, M. M., Borlaug, B. A. A simple, evidence-based approach to help guide diagnosis of heart failure with preserved ejection fraction. Circulation. 138 (9), 861-870 (2018).
- Ram, R., Mickelsen, D. M., Theodoropoulos, C., Blaxall, B. C. New approaches in small animal echocardiography: Imaging the sounds of silence. Am J Physiol Heart Circ Physiol. 301 (5), H1765-H1780 (2011).
- Anavekar, N. S., Oh, J. K. Doppler echocardiography: A contemporary review. J Cardiol. 54 (3), 347-358 (2009).
Reprints and Permissions
