This case report describes an individualized, sequential multimodal treatment approach for depersonalization-derealization disorder, involving transcranial direct current stimulation followed by pharmacotherapy, with longitudinal assessment of dissociative symptoms, affective symptoms, and cognitive performance.
Case Report
Clinical Improvement Following Multimodal Treatment in Depersonalization-Derealization Disorder: A Case Report
In This Article
Summary
Abstract
Depersonalization-derealization disorder (DPD) is characterized by persistent or recurrent detachment from the self or the surrounding environment with preserved reality testing. Because established treatment evidence remains limited, individualized therapeutic strategies are often required. This report describes a patient with derealization, emotional blunting, poor memory, slowed reactions, and impaired attention. Psychiatric evaluation showed marked depersonalization-derealization symptoms, with a Cambridge Depersonalization Scale (CDS) score of 147, a 24-item Hamilton Depression (HAMD-24) Rating Scale score of 8, a 14-item Hamilton Anxiety (HAMA-14) Rating Scale score of 5, and a MATRICS Consensus Cognitive Battery (MCCB) composite T-score of 49. The patient underwent a stepwise multimodal treatment approach that included transcranial direct current stimulation, pharmacotherapy with duloxetine and tandospirone, duloxetine dose optimization, lamotrigine augmentation and titration, and later gradual medication tapering under follow-up monitoring. Clinical improvement was observed during longitudinal assessment. This case highlights the practical value of a monitored, sequential, and multimodal treatment strategy for a patient with DPD. Although the findings are limited to a single case, the observed temporal association between intervention and improvement provides a hypothesis-generating clinical observation and supports the need for systematic studies of multimodal treatment approaches in DPD.
Introduction
Depersonalization-derealization disorder (DPD) is defined by persistent or recurrent experiences of detachment from the self or the surroundings, as well as emotional numbness and distorted, anomalous subjective experiences1. Clinical descriptions emphasize the need to distinguish DPD from psychosis, primary mood disorders, panic-related dissociation, substance-related states, and neurologic conditions2. A recent systematic review estimated that DPD affects approximately 1%–2% of the general population, with symptoms commonly emerging in adolescence or early adulthood3. Although some individuals describe symptoms as subtle or episodic at onset, chronic symptoms can impair academic, occupational, and social functioning4.
Treatment evidence remains limited. A systematic review examined clinical evidence for various treatment methods along with their efficacy and deficiencies, highlighting gaps in studies compared to the high prevalence of DPD5. Studies of psychotherapy, pharmacotherapy, and neuromodulation for DPD were heterogeneous and often small, with few controlled trials and no universally accepted medication protocol5. Recent reviews have also continued to frame DPD as a disorder with neurobiological correlates rather than a purely nonspecific complaint, including trauma-related neural models and preliminary immune-system findings6,7. However, these data do not establish a standard intervention pathway.
Several treatments are relevant to the present case. Neuromodulation approaches have included repetitive transcranial magnetic stimulation of the temporoparietal junction, a region implicated in self-location and bodily self-processing, but the evidence is still based on small samples8. Transcranial direct current stimulation (tDCS) has broader mechanistic and clinical relevance in psychiatric research, yet its role in DPD remains exploratory9. Evidence regarding lamotrigine treatment for DPD remains limited. A retrospective series suggested that lamotrigine might be beneficial when used as an adjunct to antidepressant treatment, whereas a placebo-controlled crossover trial did not demonstrate efficacy for lamotrigine monotherapy10,11. Duloxetine, a serotonin-norepinephrine reuptake inhibitor (SNRI), has shown potential benefit in an exploratory study of patients with DPD, with a trend toward earlier improvement in emotional numbness; however, evidence supporting its efficacy remains preliminary12. Case reports remain useful for generating testable hypotheses when interpreted cautiously13.
Evidence for the treatment of DPD remains limited, leaving uncertainty regarding treatment selection and sequencing in clinical practice5. This case report describes an individualized, stepwise treatment course involving an initial trial of tDCS, subsequent pharmacotherapy with duloxetine and adjunctive tandospirone, and later lamotrigine augmentation. In this report, the use of neuromodulation and pharmacotherapy at different stages of care is reported as a multimodal treatment regime. The contribution of this case lies in documenting the rationale for sequential treatment adjustments alongside longitudinal symptom and cognitive assessments. The aim is to generate hypotheses concerning individualized multimodal care for DPD.
Case presentation:
The patient was an 18-year-old male who first presented to the outpatient clinic in November 2020 with persistent derealization. Intermittent episodes had begun in January 2013, during the sixth grade of elementary school, and initially did not interfere with daily life. In 2017, during high school, the symptoms worsened and became persistent, remaining present until the initial consultation.
At the first visit, the patient described the surrounding world as unreal and reported a robot-like experience, comparable to being a controlled character in a virtual-reality environment. The patient also reported emotional blunting, limited emotional fluctuation, poor memory, slowed reactions, and impaired concentration, with associated difficulties in academic and social functioning.
As for mental status examination, the patient showed clear consciousness, intact orientation, cooperative contact, and preserved insight. Reality testing was intact. The patient denied persistent low mood, elevated mood, and psychotic symptoms. Physical examination showed no obvious abnormal signs. Electroencephalogram (EEG), electrocardiogram (ECG), and magnetic resonance imaging (MRI) findings were all within normal limits.
In terms of personal background, the patient was generally healthy, denied a drug or food allergy history, and had no family history of mental illness or inherited physical disease. The patient denied psychoactive substance use, illicit drug use, or head trauma before or after onset.
Diagnosis, assessment, and plan:
The diagnosis of DPD was established independently by two psychiatrists through clinical interviews based on DSM-5 criteria. Physical illnesses and other psychiatric disorders that could account for the symptoms were excluded. The diagnosis was supported by persistent derealization and emotional detachment, preserved reality testing, intact orientation, preserved insight, and clinically meaningful academic and social impairment.
Differential diagnosis was considered clinically. Psychotic disorder was less likely because the patient retained reality testing and did not show delusions, hallucinations, or disorganized thought. Major depressive disorder with dissociative symptoms was less likely because the dominant complaint was chronic derealization rather than a sustained depressive syndrome, and the patient denied persistent depressed or elevated mood. Anxiety-related dissociation was less likely because symptoms were persistent rather than limited to panic attacks or acute anxiety episodes. Substance-or medication-induced symptoms were less likely because symptoms began years before treatment, and the patient denied psychoactive substance and illicit drug use. Post-traumatic stress disorder was considered less likely because the patient denied a history of psychological trauma. Other dissociative disorders, particularly dissociative identity disorder, were considered less likely because the patient denied identity-state switching and autobiographical memory gaps beyond ordinary forgetting. Borderline personality disorder was considered less likely given the reported good interpersonal relationships and absence of emotional instability.
Temporal lobe epilepsy was also considered in the differential diagnosis. The patient reported no history of physical illness, including known epilepsy. The persistent nature of the symptoms over several years was less suggestive of an ictal phenomenon. Neurological examination revealed no obvious abnormalities, and EEG and brain MRI findings were within normal limits. However, a normal EEG does not exclude epilepsy.
Baseline symptom and cognitive assessment included the Cambridge Depersonalization Scale (CDS), Self-Rating Depression Scale (SDS), Self-Rating Anxiety Scale (SAS), Hamilton Depression Rating Scale (HAMD), Hamilton Anxiety Rating Scale (HAMA), and MATRICS Consensus Cognitive Battery (MCCB). The CDS was used to quantify depersonalization and derealization symptoms14. At baseline, scores were CDS 147, SDS 46, SAS 37, HAMD 8, HAMA 5, and MCCB composite T-score 49.
An individualized multimodal treatment approach was implemented sequentially, with intervention selection and subsequent adjustments guided by patient preferences, persistent symptoms, clinical response, and tolerability. The patient initially preferred not to take medication and declined psychotherapy because of concerns about the overall treatment duration and the time required for individual sessions, expressing a preference for an approach expected by the patient to provide more rapid relief. tDCS was therefore selected as an initial nonpharmacological trial, considering the patient’s preference and its generally favorable tolerability reported in other populations. After a transient improvement that did not persist, duloxetine 60 mg/day and tandospirone 10 mg three times daily were started. Duloxetine was selected to target persistent DPD symptoms, including emotional numbness, based on the treating team’s prior clinical experience of favorable responses in patients with DPD and its potential relevance to serotonergic and noradrenergic mechanisms. Tandospirone was used as an adjunct for residual anxiety and somatic tension. Duloxetine was later optimized to 120 mg/day. Lamotrigine was then added and titrated because derealization persisted despite improvement in emotional symptoms and concentration. The patient was monitored through outpatient and online contacts, repeated scale assessments, and adverse-effect review.
Protocol
Written informed consent was obtained from the patient for treatment, follow-up assessment, and publication of this case report. Ethics approval was not required for this single-patient case report under the policy of Beijing Anding Hospital, Capital Medical University.
1. Initial clinical evaluation
- On 2020-11-13, the patient’s demographic information, medical and psychiatric history, family history, medication history, and history of symptom onset and progression were obtained through a clinical interview.
- A mental status examination was performed to assess consciousness, orientation, attention, thought content, affect, insight, and reality testing.
- A physical examination was performed to identify neurological or systemic conditions associated with the patient’s symptoms.
2. Baseline psychometric, cognitive, and auxiliary assessments
- The Cambridge Depersonalization Scale (CDS), Self-Rating Depression Scale (SDS), Self-Rating Anxiety Scale (SAS), Hamilton Depression Rating Scale (HAMD), and Hamilton Anxiety Rating Scale (HAMA) were administered at baseline. The HAMD and HAMA were rated by a psychiatrist based on clinical assessments. The SAS, SDS, and CDS were completed by the patient, with guidance from a psychiatrist who also checked for missing responses.
NOTE: The CDS comprises 29 items assessing the frequency and duration of depersonalization and derealization experiences, with a total score ranging from 0 to 290. Higher scores indicate greater symptom severity. A screening cutoff of 70 has been proposed14; this threshold does not independently establish a diagnosis or define complete symptom resolution. HAMD-24 scores range from 0 to 76, with higher scores indicating greater depressive symptom severity. Scores below 8 are commonly interpreted as being within the normal range, whereas scores of 8–20 suggest possible depressive symptoms. HAMA-14 scores range from 0–56, with higher scores indicating greater anxiety symptom severity. Scores ranging from 0–7 are commonly interpreted as no or minimal anxiety, 8–14 for mild anxiety, 15–23 for moderate anxiety, and 24–56 for severe anxiety. These thresholds were used as interpretive guides rather than standalone diagnostic criteria. The SDS and SAS each contain 20 items, yielding raw total scores of 20–80 after the required reverse scoring. Higher scores indicate greater symptom severity. Raw total scores are reported in this case. For interpretation, index scores are calculated by multiplying raw scores by 1.25, yielding a range of 25–100. Commonly used screening thresholds in Chinese populations are index scores of 53 for the SDS and 50 for the SAS. These screening thresholds do not independently establish depressive or anxiety disorders15. - Cognitive performance was assessed using the MATRICS Consensus Cognitive Battery (MCCB), administered by the psychiatrist who also conducted the HAMD and HAMA assessments.
NOTE: Although originally developed for schizophrenia research, the MCCB was selected to characterize the patient’s reported difficulties with memory, concentration, and processing speed across multiple cognitive domains and to document changes during follow-up. Its use in this case was not intended to establish the diagnosis of DPD. - The assessment system generated standardized T-scores and an overall composite T-score using Chinese normative data16. These scores were extracted directly from the system-generated reports. T-scores have a normative mean of 50 and a standard deviation of 10, with higher scores indicating better cognitive performance. The composite T-score was used to summarize overall cognitive performance.
- Electrocardiography (ECG) was performed to assess baseline cardiac status and inform the subsequent selection of psychotropic medications, considering the potential of some psychotropic agents to prolong the QTc interval. Electroencephalography (EEG) and brain magnetic resonance imaging (MRI) were performed to investigate potential neurological causes of the symptoms.
3. Transcranial direct current stimulation (tDCS)
- tDCS was initiated on 2020-11-13 after the initial clinical evaluation, using a DC-STIMULATOR device with conductive rubber electrodes measuring 5 × 7 cm. The electrodes were covered with sponge sleeves soaked in a low-concentration sodium chloride solution to improve conductivity.
- Electrode placement was determined using the International 10–20 EEG system. The anode was positioned at F3 to target the left dorsolateral prefrontal cortex, and the cathode was positioned over the contralateral supraorbital region at FP2.
- Stimulation was delivered at 2 mA for 20 min per session. A gradual current ramp was used to reduce tingling and discomfort associated with abrupt current changes, with the target intensity reached over 15 s.
- Treatment was administered five times per week for 2 weeks, for a total of 10 sessions, and was discontinued at the end of this course. No further tDCS sessions were administered because the reported improvement was transient and did not provide sustained symptom relief.
- The patient was positioned comfortably and monitored for discomfort and adverse events during and after each treatment session.
- The clinical response to tDCS was assessed at the follow-up visit on 2020-12-14.
4. Initiation of duloxetine and tandospirone
- At the outpatient visit on 2020-12-16, duloxetine was initiated at 60 mg/day because the patient’s symptoms persisted after discontinuation of tDCS.
- Tandospirone was initiated concurrently at 10 mg three times daily as an adjunct for residual anxiety and somatic tension.
- At the follow-up visit on 2020-12-23, sleep, daytime alertness, gastrointestinal symptoms, and other potential adverse effects were assessed.
- The duloxetine and tandospirone regimen was continued after the tolerability assessment. Tandospirone was maintained at 10 mg three times daily and discontinued on 2021-03-26 following improvement in anxiety symptoms.
5. Duloxetine dose optimization
- At the follow-up visit on 2021-01-13, changes in depersonalization and derealization symptoms, overall functioning, medication adherence, and adverse effects were assessed.
- During an online consultation on 2021-02-24, the duloxetine dose was increased from 60 mg/day to 120 mg/day because symptoms persisted.
- The patient was instructed to continue the prescribed dose and report any new or worsening adverse effects.
6. Lamotrigine augmentation and titration
- At the outpatient visit on 2021-03-26, lamotrigine was added at 25 mg/day while duloxetine was at 120 mg/day because derealization symptoms persisted.
- Before initiating lamotrigine, the patient was informed of potential adverse effects and was instructed to seek medical attention if a skin rash or other clinically significant reaction developed.
- Medication adherence, symptom changes, and adverse effects were assessed at each subsequent follow-up visit.
- Lamotrigine was maintained at 25 mg/day from 2021-03-26 until the dose was increased to 100 mg/day on 2021-04-30.
- Lamotrigine was then maintained at 100 mg/day until 2021-06-04, when the dose was increased to 150 mg once daily. Duloxetine was maintained at 120 mg/day during this period.
7. Follow-up symptom and cognitive assessment
- Clinical status, medication adherence, adverse effects, and changes in depersonalization and derealization symptoms were assessed at each follow-up contact.
- Symptom-rating scales were repeated on 2020-12-14, 2021-01-13, 2021-02-24, 2021-03-26, and 2021-11-16.
- The MCCB was repeated on 2020-12-14, 2021-03-26, and 2021-11-16.
- The same scale versions and scoring procedures were used at baseline and follow-up.
- Any adverse events reported by the patient or documented during clinical assessment were recorded at each follow-up visit.
8. Medication tapering and discontinuation
- On 2021-09-15, the duloxetine dose was reduced from 120 mg/day to 80 mg/day after sustained clinical improvement had been established.
- On 2021-10-13, the duloxetine dose was reduced to 40 mg/day, and the lamotrigine dose was reduced to 100 mg/day.
- On 2021-11-12, duloxetine was maintained at 40 mg/day, and lamotrigine was reduced to 50 mg/day.
- On 2021-12-10, duloxetine was reduced to 20 mg/day, and lamotrigine was reduced to 25 mg/day.
- On 2022-01-14, both medications were discontinued, following a period of clinical stability.
- The patient was instructed to report recurrence or worsening of symptoms after medication discontinuation. During follow-up through 2022-05-15, no recurrence was reported. Mood remained stable, and no discomfort was reported.
Results
Clinical improvement was observed over serial follow-up and was temporally associated with the multimodal treatment sequence described above. CDS score decreased from 147 at baseline on 2020-11-13 to 47 at the 2021-11-16 assessment (Figure 1A). Intermediate CDS scores were 146 on 2020-12-14, 110 on 2021-01-13, 111 on 2021-02-24 and 98 on 2021-03-26. The CDS score decreased from above the proposed screening cutoff at baseline to below this threshold at the final assessment.
Cognitive performance also changed over time. MCCB composite T-score increased from 49 at baseline to 53 on 2020-12-14, 52 on 2021-03-26, and 59 on 2021-11-16 (Figure 1B). The direction of change suggests improvement. The baseline MCCB composite T-score of 49 was close to the normative mean, and the final score of 59 represented a 10-point increase in cognitive test performance. The patient also reported improvements in memory and concentration, with an increase in efficiency when completing academic tasks.
HAMD-24 scores ranged from 2 to 13 during follow-up, indicating low levels of clinician-rated depressive symptoms, while HAMA-14 scores remained within the no or minimal anxiety range throughout the period. SDS raw scores changed from 46 at baseline to 47 on 2021-11-16, corresponding to index scores of 57.5 and 58.75, respectively. Both were above the commonly used threshold of 53. SAS raw scores decreased from 37 to 35, corresponding to index scores of 46.25 and 43.75, respectively. Both were below the threshold of 50. These results do not independently establish depressive or anxiety disorders. Over the same period, HAMD-24 scores decreased from 8 to 2 and HAMA-14 scores from 5 to 0 (Figure 1C). Tandospirone was administered at 10 mg three times daily from December 16, 2020, until its discontinuation on March 26, 2021, as an adjunct targeting residual anxiety and somatic tension. Its individual contribution to the observed outcomes could not be determined because it was administered concurrently with duloxetine. Table 1 provides the clinical timeline, treatments, assessment dates, outcomes, and adverse effects. Early awakening and mild nausea were recorded after medication initiation, brief dizziness was reported when medication was missed, and no severe adverse effects were recorded. Duloxetine and lamotrigine were discontinued on 2022-01-14. During follow-up through 2022-05-15, the patient reported no recurrence of symptoms or discomfort, and mood remained stable.
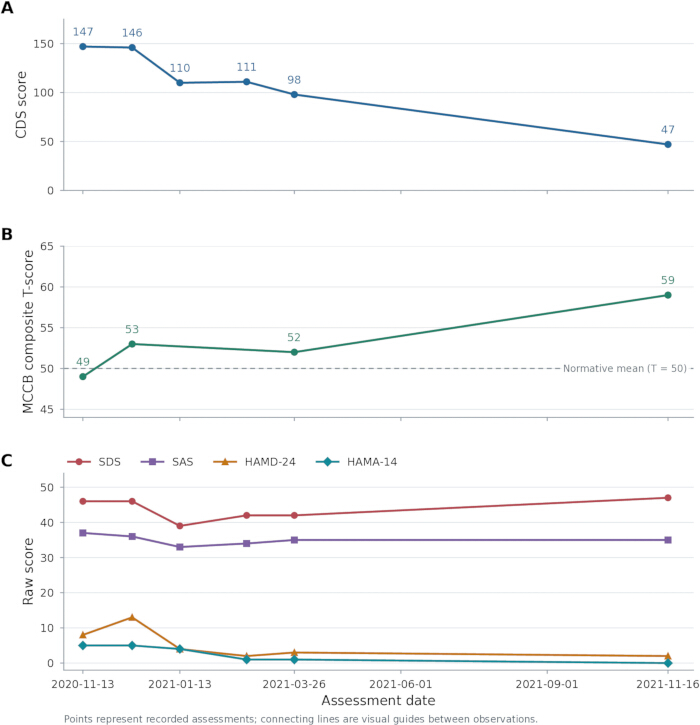
Figure 1: Clinical symptoms and cognitive-assessment scores over time. (A) Cambridge Depersonalization Scale (CDS) scores. (B) MATRICS Consensus Cognitive Battery (MCCB) composite T-scores; the dashed horizontal line indicates the normative mean of 50. (C) Raw total scores on the Self-Rating Depression Scale (SDS), Self-Rating Anxiety Scale (SAS), 24-item Hamilton Depression Rating Scale (HAMD-24), and 14-item Hamilton Anxiety Rating Scale (HAMA-14). Points represent recorded assessments, and connecting lines serve as visual guides between observations. Please click here to view a larger version of this figure.
| Date | Relative time | Visit/contact | Clinical status | Assessment scores | Treatment | Outcome/adverse effects |
| 2013-01 | Symptom onset | No clinical visit | The patient reported occasional feelings that the surrounding environment was unreal during sixth grade of elementary school; symptoms did not affect daily life. | Not assessed | None | No treatment sought. |
| 2017 | High school period | No clinical visit | Derealization became persistent, accompanied by emotional blunting, poor memory, slowed reactions, and impaired attention. | Not assessed | None | Symptoms persisted and affected study efficiency. |
| 2020-11-13 | Baseline | 1st outpatient visit | 18-year-old male university student with more than 3 years of persistent derealization and emotional blunting; reality testing and orientation were intact. | CDS 147; SDS 46; SAS 37; HAMD 8; HAMA 5; MCCB composite T-score 49. ECG, EEG and MRI normal. | tDCS initiated; no medication at baseline. | No obvious abnormal physical signs were observed. |
| Late November 2020 | End of two-week tDCS course | Treatment completion | Improvement was transient and did not provide sustained symptom relief. | Not assessed | Completed 10 sessions over two weeks (five sessions/week; 2mA for 20 min/session). tDCS was discontinued at the end of the course. | No further tDCS sessions were administered because improvement was transient. |
| 2020-12-14 | After tDCS | Research follow-up assessment | Within several hours after tDCS, derealization was slightly improved but the effect did not persist; the patient reported increased sleep need after tDCS. | CDS 146; SDS 46; SAS 36; HAMD 13; HAMA 5; MCCB composite T-score 53. | No medication recorded at this assessment. | Transient improvement only, no serious adverse effect observed. |
| 2020-12-16 | Month 1 | 2nd outpatient visit | tDCS had some effect, but symptoms persisted after treatment stopped. | Not assessed | Duloxetine 60mg/day; tandospirone 10mg three times daily as an adjunct for residual anxiety and somatic tension. | Treatment changed to medication. |
| 2020-12-23 | Month 1 | 3rd outpatient visit | The patient reported early awakening after medication, was not sleepy during the day, and had mild nausea. | Not assessed | Continued duloxetine 60 mg/day and tandospirone 10 mg three times daily. | Mild nausea; no severe adverse effect observed. |
| 2021-01-13 | Month 2 | 4th outpatient visit | The patient perceived approximately 20%-30% improvement and reported no discomfort. | CDS 110; SDS 39; SAS 33; HAMD 4; HAMA 4. | Continued current treatment. | Medication side effects had gradually eased. |
| 2021-02-24 | Month 3 | Online consultation | Emotional depersonalization was partly relieved, whereas derealization showed little change; the patient reported brief dizziness when medication doses were occasionally missed. | CDS 111; SDS 42; SAS 34; HAMD 2; HAMA 1. | Online consultation. Duloxetine increased to 120 mg/day and tandospirone 10 mg three times daily. | Mood and attitude were more positive. |
| 2021-03-26 | Month 4 | 5th outpatient visit | Emotional unreality had recovered, but derealization persisted; concentration and memory were improved. | CDS 98; SDS 42; SAS 35; HAMD 3; HAMA 1; MCCB composite T-score 52. | Lamotrigine initiated at 25 mg/day for persistent derealization; tandospirone discontinued following improvement in anxiety symptoms. Duloxetine maintained at 120 mg/day. | No severe adverse effect observed. |
| 2021-04-30 | Month 5 | 6th outpatient visit | Symptoms recurred after the patient stopped medication for several days; the patient perceived further improvement after adding lamotrigine. | Not assessed | Lamotrigine increased from 25 to 100mg/day; duloxetine maintained at 120 mg/day. | Recurrence was temporally associated with medication interruption. |
| 2021-06-04 | Month 7 | 7th outpatient visit | The patient reported continued progress after lamotrigine; daytime symptoms were reduced, while nighttime symptoms persisted. | Not assessed | Lamotrigine increased from 100 to 150 mg/day; duloxetine maintained at 120 mg/day. | No other discomfort reported. |
| 2021-09-15 | Month 10 | 8th outpatient visit | The patient reported recovery, continued taking medication, and reported no discomfort. | Not assessed | Duloxetine reduced to 80 mg/day; other treatment unchanged. | Dose tapering began after sustained improvement. |
| 2021-10-13 | Month 11 | 9th outpatient visit | The patient reported symptom alleviation after duloxetine reduction to 80 mg/day while taking lamotrigine 150 mg/day; tapering was smooth. | Not assessed | Duloxetine reduced to 40 mg/day; lamotrigine 50mg morning and evening. | No discomfort reported. |
| 2021-11-12 | Month 12 | 10th outpatient visit | Medication reduction was smooth. | Not assessed | Duloxetine 40 mg/day; lamotrigine 50 mg each morning. | No adverse reaction was observed at this assessment. |
| 2021-11-16 | Month 12 | Research follow-up assessment | Symptoms had improved, with mild residual derealization and emotional blunting. | CDS 47; SDS 47; SAS 35; HAMD 2; HAMA 0; MCCB composite T-score 59. | Duloxetine 40 mg/day; lamotrigine 50 mg each morning. | No adverse reaction was observed at this assessment. |
| 2021-12-10 | Month 13 | 11th outpatient visit | The condition was stable and no discomfort was reported after dose reduction. | Not assessed | Duloxetine 20 mg/day; lamotrigine 25 mg each morning. | Stable during tapering. |
| 2022-01-14 | Month 14 | 12th outpatient visit | Clinically stable, with no discomfort reported. | Not assessed | Both medications were discontinued on 2022-01-14. | Advised to report any recurrence or worsening of symptoms after medication discontinuation. |
| Follow-up through 2022-05-15 | Month 18 | Follow-up | Mood remained stable. | No scale scores assessed for this follow-up. | Both medications remained discontinued. | No recurrence of symptoms or discomfort was reported during follow-up. |
| Note: CDS, Cambridge Depersonalization Scale; SDS, Self-Rating Depression Scale; SAS, Self-Rating Anxiety Scale; HAMD, Hamilton Depression Rating Scale; HAMA, Hamilton Anxiety Rating Scale; MCCB, MATRICS Consensus Cognitive Battery; tDCS, transcranial direct current stimulation; ECG, electrocardiography; EEG, electroencephalography; MRI, magnetic resonance imaging. | ||||||
Table 1: Clinical timeline, assessment scores, treatments, and outcomes. The table summarizes symptom history, outpatient visits, online contacts, medication changes, assessment scores, and recorded adverse effects.
Discussion
This case describes a patient with persistent DPD symptoms, emotional numbness, and subjective difficulties with concentration and memory that affected academic and social functioning. Treatment proceeded from an initial trial of tDCS to duloxetine with adjunctive tandospirone, followed by lamotrigine augmentation for persistent derealization. Improvement in DPD symptoms and cognitive assessment scores was observed during follow-up. The CDS score decreased from 147 at baseline to 47 at the final assessment, reflecting a reduction in symptom severity with residual symptoms. The significance of this case lies in illustrating the application of neuromodulation and pharmacotherapy within an individualized, sequential multimodal approach. The initial use of tDCS accommodated the patient’s preference for a nonpharmacological intervention, while subsequent medication adjustments addressed persistent DPD symptoms and residual anxiety and somatic tension. The clinical improvement observed during treatment with duloxetine and adjunctive lamotrigine suggests potential benefit from this combination and provides a case-based reference for further investigation of pharmacological options for DPD.
To date, DPD remains a relatively under-researched clinical disease. Persistent DPD symptoms can be associated with impairment in academic, occupational, and social functioning4.
Psychotherapy, neuromodulation, and pharmacotherapy have been investigated as treatment approaches for DPD2. An open study of cognitive behavioural therapy and a case report of mindfulness-based cognitive therapy described potential benefits17,18. However, the uncontrolled designs of these reports limit conclusions about treatment efficacy. Psychotherapy was discussed as a potential treatment option, but was not undertaken because the patient declined this intervention.
As for tDCS, while the application in treating DPD is still being explored, its use in depression, anxiety, and other mental disorders has provided some references for its usage for DPD. Several studies have investigated the effects of tDCS on modulating brain neural activity and emotion9. These mechanisms may point out some relevance to the pathophysiological processes of DPD. In the present case, tDCS was used as an initial nonpharmacological trial in accordance with the patient’s treatment preference. The improvement was transient and did not provide sustained symptom relief, prompting a transition to pharmacotherapy. This clinical course explains the treatment change in this patient, but does not establish the comparative efficacy of tDCS and medication for DPD.
As for pharmacological treatment, no specific medication has been universally approved for DPD5. Some reports suggested that SSRIs may alleviate DPD symptoms19,20. Additionally, the use of lamotrigine in treating DPD has also been reflected in several articles. A retrospective case series showed that lamotrigine demonstrated efficacy as an adjunct to SSRIs10. However, a placebo-controlled crossover trial did not support its beneficial effect as a sole medication11. Some research suggested that certain dual-action antidepressants, especially those acting on both serotonin and norepinephrine, may be promising for DPD treatment. Previous pharmacological studies have suggested that serotonergic dysregulation may contribute to the pathophysiology of depersonalization21. However, evidence supporting the efficacy of SSRIs for DPD remains limited2. Another study found that urinary norepinephrine was increased in patients with DPD and was significantly inversely correlated with symptom severity22. This indicated that DPD patients may have abnormal norepinephrine function. SNRIs inhibit the reuptake of both serotonin and norepinephrine and may therefore modulate neurochemical systems potentially relevant to dissociative and affective symptoms.
In this patient, duloxetine was selected primarily to address persistent DPD symptoms, including emotional numbness, rather than a prominent depressive or anxiety syndrome. The choice was informed by the treating team’s prior clinical experience of favorable responses in patients with DPD. The temporal relationship between symptom improvement and medication treatment suggests a possible contribution but does not establish causality. A subsequent exploratory study from the same team also reported potential benefit with duloxetine and a trend toward earlier improvement in emotional numbness12. These findings provide support for its use but do not establish superiority over venlafaxine, desvenlafaxine, or tricyclic antidepressants. Lamotrigine was added for persistent derealization after an incomplete response to duloxetine, consistent with preliminary evidence concerning its use as an adjunct to antidepressants rather than as monotherapy10,11. The treatment sequence reflected clinical response and tolerability.
Tandospirone, a partial 5-HT1A receptor agonist23, was used as an individualized adjunct for residual anxiety and somatic tension despite the low overall anxiety scores. A randomized dose-comparison trial in generalized anxiety disorder reported reductions in anxiety symptoms, including somatic symptoms, during tandospirone treatment23. Its availability is limited, and evidence supporting its use specifically for DPD has not been established. Its inclusion, therefore, reflected symptom-targeted clinical judgment rather than an established DPD treatment strategy.
Critical steps in implementing this multimodal approach included defining the target symptoms and intended role of each intervention, monitoring response and tolerability, and reassessing whether an intervention should be continued, adjusted, or discontinued. Transient improvement after tDCS prompted a transition to pharmacotherapy. Persistent symptoms led to an increase in duloxetine from 60 mg/day to 120 mg/day, followed by lamotrigine augmentation for residual derealization. Tandospirone was discontinued on 2021-03-26, following improvement in anxiety symptoms. Monitoring included repeated symptom assessments, review of medication adherence, and adverse effects. Medication interruption was followed by symptom recurrence, highlighting the importance of considering adherence when interpreting changes in clinical status. Following sustained improvement, duloxetine and lamotrigine were reduced gradually and discontinued on 2022-01-14. During follow-up through 2022-05-15, no recurrence was reported, mood remained stable, and no discomfort was reported.
The clinical course should also be interpreted in the background of the patient’s developmental stage. Improvement occurred during the transition from late adolescence to early adulthood. Research in nonclinical populations has identified age-related differences in emotion regulation strategies across adolescence and adulthood24. Developmental factors, therefore, warrant consideration as possible influences on the observed clinical course, although this evidence does not establish that maturation leads to improvement in DPD. Changes in academic demands or psychosocial circumstances may also have contributed, but these factors were not systematically assessed in this case. The contribution of these factors cannot be distinguished from treatment effects.
Several limitations should be acknowledged. The diagnosis was based on independent clinical interviews by two psychiatrists, but no structured diagnostic interview was administered. Although the patient denied a history of psychological trauma, no structured trauma history or standardized assessment of childhood adversity was obtained. Dissociative symptoms beyond depersonalization and derealization were not systematically assessed, limiting the evaluation of trauma-related factors and coexisting dissociative symptoms. The patient denied substance use and showed no clinical signs of intoxication. However, toxicology screening was not performed, as toxicology screening of adolescents is not generally undertaken in medical institutions in China. Reliance on self-reported substance-use history without toxicological confirmation remains a limitation of this case.
The reported improvement in functioning was based on the patient’s account of increased efficiency in completing academic tasks, attributed by the patient to better memory and concentration. These reports were not corroborated by objective academic performance data or a standardized assessment of social functioning. The MCCB was developed for schizophrenia research, and its validity and sensitivity to change in DPD have not been established. Accordingly, the observed score changes should be interpreted as exploratory findings concerning cognitive test performance. Practice effects from repeated testing may also have contributed to the observed changes.
Although approximately 2–3 weeks elapsed between completion of tDCS in November 2020 and initiation of pharmacotherapy on 2020-12-16, this interval was not a prespecified washout period designed to distinguish the effects of the interventions. Potential carryover effects of tDCS cannot be excluded. Moreover, the uncontrolled, sequential introduction of pharmacological treatments prevents attribution of the observed improvement to any single intervention. Placebo effects, nonspecific effects of clinical contact, natural symptom fluctuation, spontaneous remission, and regression to the mean may also have contributed to the observed improvement. The uncontrolled design prevents these influences from being separated from treatment-specific effects.
Follow-up after medication discontinuation was extended for approximately 4 months, which was insufficient to establish the durability of improvement or the longer-term risk of recurrence. The findings from this single uncontrolled case cannot establish the generalizability of the treatment sequence.
Future research should use controlled designs to distinguish the effects of individual treatments from those of augmentation and treatment sequencing. Comparisons of antidepressant treatment, especially duloxetine with and without lamotrigine augmentation, would help clarify any additional benefit for persistent DPD symptoms. Longer follow-up during dose reduction and after medication discontinuation is needed to assess the durability of improvement and recurrence. Any proposed synergistic effect would require a study specifically designed to test treatment interactions.
In this patient, tDCS was associated with transient improvement, whereas more sustained improvement was observed during subsequent pharmacotherapy with duloxetine and later lamotrigine augmentation. The clinical contribution is the documentation of how different interventions were selected, reassessed, and modified within ongoing care. The findings support further investigation of multimodal treatment components and sequencing.
Disclosures
Use of artificial intelligence: ChatGPT (OpenAI) assisted with language editing and interpretation of scale scores. The authors reviewed and verified the content and take full responsibility for the manuscript.
Acknowledgements
This work was supported by Capital's Funds for Health Improvement and Research (Grant no. 2024-4-21211), National Natural Science Foundation of China (Grant no.8240152532), and Beijing Natural Science Foundation (Grant no. L2510128).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Cambridge Depersonalization Scale | Sierra and Berrios | Not applicable | Self-report scale used to assess the frequency and duration of depersonalization-derealization symptoms. |
| Duloxetine (Cymbalta / Xinbaida) | Eli Lilly and Company | www.lilly.com | Serotonin-norepinephrine reuptake inhibitor used as part of the pharmacological treatment regimen. |
| ECG system (ECG-1350P) | Nihon Kohden Corporation, Japan | www.nihonkohden.com | Model: ECG-1350P. Used for baseline ECG assessment, findings were normal. |
| EEG system (64 channels) | Brain Products GmbH, Germany | www.brainproducts.com | 64 channel EEG system used for baseline assessment, findings were normal. Specific hardware model not available. |
| Hamilton Anxiety Rating Scale | Max Hamilton | Not applicable | Clinician-rated 14-item version (HAMA-14) used during serial assessments. |
| Hamilton Depression Rating Scale | Max Hamilton | Not applicable | Clinician-rated 24-item version (HAMD-24) used during serial assessments. |
| Lamotrigine (Lamictal / Libitong) | GlaxoSmithKline (GSK) | www.gsk.com | Used as an augmentation medication and titrated during follow-up. |
| MATRICS Consensus Cognitive Battery | MATRICS Assessment Inc. | Not applicable | Neurocognitive battery used to assess cognitive performance. T-scores and the overall composite T-score were generated by the assessment system using Chinese normative data. No commercial catalog number for the version used. |
| MRI scanner (MAGNETOM Prisma, 3.0 T) | Siemens Healthineers | www.siemens-healthineers.com/magnetic-resonance-imaging | Model: MAGNETOM Prisma; field strength: 3.0 T. Used for baseline brain MRI, findings were normal. |
| Self-Rating Anxiety Scale | W.W.K. Zung | Not applicable | Self report 20-item anxiety scale used during serial assessments. |
| Self-Rating Depression Scale | W.W.K. Zung | Not applicable | Self report 20-item depression scale used during serial assessments. |
| Tandospirone citrate (Xide) | Sumitomo Pharma | www.sumitomo-pharma.com | Used as an adjunct for residual anxiety and somatic tension during the early pharmacological regimen. |
| Transcranial direct current stimulation system (DC-STIMULATOR) | NeuroConn, Germany | www.neurocaregroup.com/technology/dc-stimulator | Model: DC-STIMULATOR. Used after the initial evaluation. Electrode size: 5×7cm; stimulation: 2mA for 20 min/session, five sessions/week for two weeks. |
References
- American Psychiatric Association. Diagnostic and statistical manual of mental disorders. 5th ed. Arlington (VA): American Psychiatric Association; 2013.
- Hunter ECM, Charlton J, David AS. Depersonalisation and derealisation: assessment and management. BMJ. 2017;356:j745.
- Yang J, Millman LSM, David AS, Hunter ECM. The prevalence of depersonalization-derealization disorder: a systematic review. J Trauma Dissociation. 2023;24(1):8-41.
- Michal M, et al. A case series of 223 patients with depersonalization-derealization syndrome. BMC Psychiatry. 2016;16:203.
- Wang S, et al. The treatment of depersonalization-derealization disorder: a systematic review. J Trauma Dissociation. 2024;25(1):6-29.
- Murphy RJ. Depersonalization/derealization disorder and neural correlates of trauma-related pathology: a critical review. Innov Clin Neurosci. 2023;20(1-3):53-59.
- Zheng S, et al. The role of the immune system in depersonalisation disorder. World J Biol Psychiatry. 2024;25(5):291-303.
- Mantovani A, et al. Temporo-parietal junction stimulation in the treatment of depersonalization disorder. Psychiatry Res. 2011;186(1):138-140.
- Chase HW, Boudewyn MA, Carter CS, Phillips ML. Transcranial direct current stimulation: a roadmap for research, from mechanism of action to clinical implementation. Mol Psychiatry. 2020;25(2):397-407.
- Sierra M, et al. Lamotrigine as an add-on treatment for depersonalization disorder: a retrospective study of 32 cases. Clin Neuropharmacol. 2006;29(5):253-258.
- Sierra M, et al. A placebo-controlled, crossover trial of lamotrigine in depersonalization disorder. J Psychopharmacol. 2003;17(1):103-105.
- Zheng S, Song M, Song N, Zhu H, Jia H. A preliminary study on the therapeutic efficacy of duloxetine in the treatment of depersonalization-derealization disorder. J Capital Med Univ. 2023;44(4):578-582.
- Weber SR. Use of mixed amphetamine salts in a patient with depersonalization/derealization disorder. Innov Clin Neurosci. 2020;17(1-3):45-48.
- Sierra M, Berrios GE. The Cambridge Depersonalisation Scale: a new instrument for the measurement of depersonalisation. Psychiatry Res. 2000;93(2):153-164.
- Dunstan DA, Scott N. Assigning clinical significance and symptom severity using the Zung scales: levels of misclassification arising from confusion between index and raw scores. Depress Res Treat. 2018;2018:9250972.
- Shi C, et al. The MATRICS Consensus Cognitive Battery (MCCB): co-norming and standardization in China. Schizophr Res. 2015;169(1-3):109-115.
- Hunter ECM, et al. Cognitive-behaviour therapy for depersonalisation disorder: an open study. Behav Res Ther. 2005;43(9):1121-1130.
- Mishra S, Das N, Mohapatra D, Mishra BR. Mindfulness-based cognitive therapy in depersonalization-derealization disorder: a case report. Indian J Psychol Med. 2022;44(6):620-621.
- Ratliff NB, Kerski D. Depersonalization treated with fluoxetine. Am J Psychiatry. 1995;152(11):1689-1690.
- Hollander E, et al. Treatment of depersonalization with serotonin reuptake blockers. J Clin Psychopharmacol. 1990;10(3):200-203.
- Simeon D, et al. Induction of depersonalization by the serotonin agonist meta-chlorophenylpiperazine. Psychiatry Res. 1995;58(2):161-164.
- Simeon D, et al. Basal norepinephrine in depersonalization disorder. Psychiatry Res. 2003;121(1):93-97.
- Li Q, et al. Relative safety and efficacy of two doses of tandospirone citrate for generalized anxiety disorder: a multicenter randomized controlled trial. Neuropsychiatr Dis Treat. 2022;18:1653-1664.
- Zimmermann P, Iwanski A. Emotion regulation from early adolescence to emerging adulthood and middle adulthood: age differences, gender differences, and emotion-specific developmental variations. Int J Behav Dev. 2014;38(2):182-194.
Reprints and Permissions
This article has been published
Video Coming Soon