This protocol details the application of implantable telemetry for continuous and reliable arterial pressure monitoring in conscious rodents, covering surgical implantation, postoperative care, data acquisition, and comparison with the tail-cuff method.
Method Article
Continuous Arterial Pressure Monitoring in Conscious Rodents Using Implantable Telemetry and Comparison with the Tail-Cuff Method
In This Article
Summary
Abstract
Radio telemetry enables reliable, continuous arterial blood pressure (BP) monitoring in conscious rodents under physiological conditions, while minimizing operator-related artifacts. The implantable transmitter includes a pressure-sensing catheter, and the implantation procedure varies depending on the species used and the purpose of the study. In rodents, the most common approaches are implantation through the carotid artery or the abdominal aorta. The carotid artery approach is often favored for its direct path to the aortic arch, facilitating accurate central pressure measurement, while the abdominal aorta approach is also widely utilized for chronic studies. Compared with non-invasive methods such as tail-cuff, implantable telemetry provides more accurate and consistent measurements, making it especially useful for hypertension studies that require precise long-term BP monitoring. This protocol details anesthesia, surgical implantation techniques, and postoperative care, as well as procedures for acquiring and analyzing hemodynamic parameters-systolic, diastolic, and mean arterial pressure and heart rate (HR)-together with a comparative evaluation against tail-cuff measurements.
Introduction
Accurate and continuous monitoring of arterial blood pressure (BP) in conscious rodents is essential for cardiovascular research, especially in hypertension studies where dynamic hemodynamic changes require precise measurement1,2,3. Traditional non-invasive methods, such as the tail-cuff method, are widely used but limited by intermittent sampling, stress-related artifacts, and failure to capture circadian BP variations4,5. These issues compromise accuracy and reproducibility, restricting their use in long-term hemodynamic studies6.
Radio telemetry systems offer more accurate and consistent BP measurements. It enables continuous, high-quality BP monitoring in freely moving animals, eliminating variability from operator handling and stress caused by restraint7,8,9,10. This approach is particularly useful in hypertension research, where it is important to capture the onset, magnitude, and stability of BP elevation, as well as circadian patterns11,12,13. In addition, continuous telemetry allows detection of transient fluctuations during disease progression and provides a detailed assessment of pharmacological interventions, advantages that traditional tail-cuff methods cannot offer14.
The radio telemetry system uses an implantable transmitter with a pressure-sensing catheter, which is surgically placed at anatomical sites chosen based on the species and study design. In mice, the catheter is typically inserted through the carotid artery into the aortic arch to ensure stable signals9. For certain experiments, such as long-term studies in older or heavier mice, placement in the abdominal aorta may be preferred. In rats, the abdominal aorta is the standard site for reliable long-term recordings15. These implantation strategies allow precise measurement of systolic, diastolic, and mean arterial pressures, as well as heart rate (HR), making the telemetry system a valuable tool for phenotyping hypertensive models and evaluating therapeutic interventions16.
This protocol outlines detailed procedures for anesthesia, surgical implantation (including catheter placement options), postoperative care, and data acquisition and analysis, alongside a comparative evaluation with the tail-cuff method.
Protocol
All experimental procedures were approved by the Institutional Animal Care and Use Committee (IACUC) of Xi'an Jiaotong University (No. XJTUAE2025-2784) and were conducted in accordance with institutional and national guidelines for the care and use of laboratory animals. Eight-week-old male spontaneously hypertensive rats (SHRs) and C57BL/6 mice were used in the experiments.
1. Animal preparation
- Housing conditions: House all animals in environmentally controlled rooms. Maintain an ambient temperature of 21 °C and a relative humidity of 60%. Set a 12 h light/12 h dark cycle. Provide standard laboratory chow and water ad libitum.
- Recommended weight for telemetry implantation: Select mice weighing 20-35 g to ensure adequate catheter implantation length and accommodate the size of the telemetry transmitter (HD-X11: 33 x 33 x 14 mm; HD-S10: 42 x 42 x 18 mm). Choose mice of 20 g or more for carotid artery catheterization and use mice of around 30 g for abdominal aorta implantation. For rats, select animals weighing ≥ 170 g to ensure proper fit and minimize surgical complications. Use the abdominal aorta implantation approach for rats.
NOTE: This weight range balances surgical feasibility with animal welfare considerations for chronic telemetry monitoring.
2. Preoperative preparation
- Telemetry implant model verification: For mice, use the HD-X11 transmitter. For rats, use the HD-S10 transmitter. Confirm the model number and coding on the transmitters (Figure 1).
- Surgical aseptic preparation: Prior to surgery, disinfect the surgical area thoroughly and sterilize all instruments by autoclaving at 121 °C for 20 min (Supplementary Figure 1A). Prepare sterile drapes, surgical saline, and required reagents (Table of Materials). Wear appropriate personal protective equipment (gloves, mask, and cap) and arrange instruments on a sterile tray, confirming sterility indicators before use. Maintain strict aseptic technique throughout the procedure. After surgery, ensure proper disposal of contaminated materials and prompt re-sterilization of reusable instruments.
- Pretreatment of transmitters
- Peel back the white package cover from the clear plastic tray to open the sterile package.
- Lift the clear tray cover, flood the catheter channel with sterile saline, and immediately replace the cover. Avoid contact with the transmitter or inner tray to maintain sterility.
- Set the package aside and allow the catheter to hydrate for 15 min before transferring it to the sterile field. Ensure the catheter tip appears uniformly translucent and gel-filled. Identify any opaque or white tips as insufficiently hydrated and rehydrate before proceeding.
- Retain the white cover (contains calibration data) and the sterile package (for potential return).
NOTE: Ensure proper catheter hydration because of its hydrophilic properties. Implantation in a non-hydrated state causes the catheter to absorb water from the blood, leading to expansion. This expansion results in gel recession and void formation at the catheter tip, thereby increasing the risk of thrombus formation.
- Anesthetic induction
- Inhalational anesthesia: Place the animal in an induction chamber and anesthetize with 5% isoflurane in oxygen at a flow rate of 0.5 L/min. Once the righting reflex is lost, transfer the animal to a temperature-controlled surgical platform (37 °C) and maintain anesthesia by a nosecone delivering 2% isoflurane with 0.5 L/min oxygen flow throughout the procedure17.
- Injectional anesthesia: Anesthetize the mice by intramuscular injection of a Zoletil-xylazine mixture (1:2 v/v) at a dose of 20 µL per 20 g body weight18.
- Use a vet ointment on the eyes to prevent dryness while under anesthesia.
- Surgical site preparation: Fix the limbs with tape and remove neck hair using depilatory cream, then wipe the area clean. Disinfect the incision site with benzalkonium bromide using three circular scrubs, followed by two scrubs with povidone-iodine after placing a sterile drape.
3. Surgical telemetric transmitter implantation
NOTE: Perform the surgical implantation either through the carotid artery or abdominal aorta catheterization (Figure 2).
- Carotid artery implantation
- Make a 1-1.5 cm incision along the midline of the skin below the chin and create bilateral subcutaneous spaces using blunt dissection.
- Gently retract the parotid and submandibular glands using blunt instruments to expose the tracheal muscles. Identify the left carotid artery adjacent to the trachea using blunt dissection (Figure 3A).
- Free the carotid artery from surrounding tissues. Carefully dissect the accompanying vagus nerve, a distinctive white strand, away from the arterial wall over a 10 mm segment to expose the bifurcation.
NOTE: Carefully dissect the vagus nerve without traction to avoid functional impairment, as it is essential for autonomic regulation. - Pass three saline-soaked, nonabsorbable 6-0 sutures beneath the isolated carotid artery segment and position them at the cranial, caudal, and middle locations, respectively (Figure 3B). Carefully lift the vessel to avoid vascular injury.
- Place the more anterior suture adjacent to the carotid bifurcation and then securely ligate the vessel with a permanent knot. The caudal suture provides temporary vascular occlusion, while the middle suture forms a loose loop for catheter stabilization post-insertion. Lift both ends of the sutures with vascular clamps to distend the vessel (Figure 3C).
NOTE: The bifurcation of the internal and external carotid arteries serves as an important landmark for determining the appropriate insertion length of the implanted catheter. - Bend the tip of a 1 mL syringe needle to about 100° and carefully puncture the arterial wall near the cranial ligature. Use the needle as a guide to advance the catheter into the artery, gently sliding it along the vessel with catheter-holding forceps (Supplementary Figure 1B-C).
- Withdraw the needle using a steady hand and replace it with fine forceps to gently advance the catheter deeper into the vessel. Monitor the depth markers on the catheter, stop insertion once the predetermined position is reached (Supplementary Figure 2A-B). Tighten the middle suture to secure the catheter in place. Firmly tie the distal suture for additional fixation. Loop the proximal suture around the external portion of the catheter and ligate it to prevent dislodgement. Cut the ends of sutures as short as possible (Figure 3D).
- Confirm catheter depth using the marker and ensure it reaches the aortic arch. Check for blood leakage or bubbling at the puncture site or around the catheter. Apply corrective action immediately if leakage occurs. Gently tug on the catheter to ensure it remains securely in place by sutures or adhesive.
- Using blunt forceps, create a subcutaneous pocket from the incision toward the left abdominal flank. Inject 200 µL of pre-warmed (37 °C) saline to expand the space, then insert the telemetry transmitter into the pocket and position it subcutaneously in the left abdominal region (Figure 4A-C).
- Optional: Perform this step when using implants with ECG leads (HD-X11). Position the colorless ECG lead wire subcutaneously over the right pectoral muscle and secure the red lead wire in the left lower abdominal subcutaneous space. Close the incision with interrupted sutures to prevent wound dehiscence (Figure 4D-E).
NOTE: The procedure shown was performed in a euthanized animal. All survival surgeries were conducted under strict aseptic conditions with sterile draping to ensure animal welfare and experimental success. - Keep the closed incision clean and apposed. Check for active subcutaneous bleeding, such as rapid swelling, hematoma formation, or blood seeping through the suture line.
- Abdominal aorta implantation
- Position the animal in supine orientation with the head directed away from the surgeon.
- Make a 3-4 cm midline abdominal skin incision, followed by blunt dissection between the skin and abdominal wall.
- Incise the linea alba along the midline and gently retract the intestines with moist gauze to expose the retroperitoneal space.
- Identify the pulsatile abdominal aorta adjacent to the inferior vena cava, then carefully dissect surrounding fat/connective tissue with cotton swabs to expose the aortic segment from the left renal vein (superiorly) to the iliac bifurcation (inferiorly), clearing all ventral surface tissue (Figure 5A).
NOTE: The left renal vein crossing the ventral aortic surface serves as the critical landmark for proximal aortic mobilization. - Pass two saline-moistened 4-0 nonabsorbable sutures beneath the isolated abdominal aorta. Place the cranial suture at the left renal vein-aortic crossing and the caudal suture at the iliac bifurcation. Temporarily tighten both sutures to occlude blood flow (Figure 5B).
- Bend the tip of a 5 mL syringe needle to roughly 100°, then puncture the aortic wall just below the caudal mesenteric artery with care. Using the needle as a guide, advance the catheter into the aorta through the entry site with specialized catheter-holding forceps, gently sliding it rostral along the vessel.
- Withdraw the needle and carefully advance the catheter cranially until its distal tip encounters slight resistance at the anterior occlusion suture (Figure 5C and Supplementary Figure 2C-D).
- Apply one drop of tissue adhesive to the catheter entry site and allow it to cure for 30 s. Gradually release the caudal traction suture while closely monitoring for any bleeding at the insertion site (Supplementary Figure 3A). Confirm the catheter tip is positioned cranial to the left renal vein.
- Prepare a 5 mm x 3 mm fibrous membrane patch and position it over the catheter insertion site (Supplementary Figure 3B), then secure it with biocompatible adhesive to stabilize the catheter (Figure 5D).
- Under clear visualization, check for active blood leakage from the puncture site or around the catheter. Stop immediately if bubbling or seepage occurs and apply corrective action. Gently tug on the catheter to ensure it remains securely in place by the sutures and/or adhesive.
NOTE: When performing procedures on hypertensive animals, start with atraumatic clamps. Restore pressure gradually using a staged clamp-release protocol: release the distal clamp first to test the seal under low pressure, then release the proximal clamp only after confirming hemostasis. - Remove all abdominal gauze and gently reposition the intestines. Rinse the abdominal cavity with pre-warmed (37 °C) saline and then confirm hemostasis at the catheter entry site.
- Place the transmitter intra-abdominally among intestinal loops and secure it to the parietal peritoneum using 6-0 nonabsorbable sutures (Figure 6A).
- Optional: Perform this step when using implants with ECG leads (HD-X11). Insert an 18 G needle through the abdominal wall near the right lateral incision (animal's right side) into the peritoneal cavity, avoiding internal organs. Thread the negative lead (clear catheter) through the needle and exteriorize it from the abdomen. Withdraw the needle while maintaining lead position. Repeat the procedure on the opposite side to exteriorize the positive lead (red catheter) (Figure 6B-C).
- Abdominal wall closure: Suture the abdominal wall using a simple interrupted pattern with 5-0 or 6-0 nonabsorbable sutures.
- Lead preparation and placement: Trim excess lead length, leaving a small coil; remove ~1 cm of terminal silicone to expose wires and secure tubing with 5-0/6-0 sutures. Tunnel the positive lead to the left caudal rib and the negative lead to the right pectoral muscle, anchoring each with stay sutures (Figure 6D).
- Close the incision with interrupted sutures to prevent wound dehiscence (Figure 6E).
NOTE: This study performs the procedure on a euthanized animal for demonstration. Conduct all survival surgeries under strict aseptic conditions with sterile draping to ensure animal welfare and procedural success.
4. Surgical recovery
- Anesthesia termination: Discontinue gas anesthesia and remove the delivery apparatus. Transfer the animal to a 37 °C warming pad to maintain normothermia until spontaneous movement fully resumes. Do not leave the animal unattended until it has regained sufficient consciousness to maintain sternal recumbency.
- Postoperative analgesia: Administer meloxicam subcutaneously at 5 mg/kg body weight for postoperative pain relief19,20,21,22.
NOTE: To prevent pain proactively, preemptive analgesia may be administered prior to surgery. - Recovery monitoring: Systematically monitor mice for pain and infection after surgery. Assess spontaneous pain using the Mouse Grimace Scale (MGS) by scoring orbital tightening, nose bulge, cheek bulge, ear position, and whisker change. Record daily clinical observations, including weight loss, reduced food or water intake, hunched posture, piloerection, decreased activity, and social isolation. Examine the surgical site daily for redness, swelling, heat, or discharge (Supplementary Table 1). Administer analgesics or consult a veterinarian according to predefined humane endpoints if abnormal behavior or appearance is observed23,24,25,26,27. After full recovery (typically 10 days post-surgery), individually house mice in standard cages on telemetry receiver plates for continuous data acquisition.
5. Data recording and analysis
- Transmitter implantation and operation: Control the implantable transmitter by using a strong magnet to switch it ON or OFF. Confirm successful activation by verifying the presence of an audible signal on a nearby FM radio.
- Transmitter configuration and data acquisition
- Acquire data using the software (Ponemah v5.00). Refer to Supplementary File 1 for configuration options.
- Open Ponemah v5.00, create a new experiment or open an existing one. Go to Configuration > Hardware and click Edit APR Configuration to select an empty receiver.
- Open Hardware > Edit MX2 Configuration to connect the implant. Select the Receiver Associated with the Implant and configure the following parameters: name, implant model, signal type, sample rate, and serial number.
- Click Search for HD Implant. Activate the implant using a magnet and place it on the designated detection plate until the system recognizes the signal. Click Save to confirm.
- Configure Subject Details by setting the subject name, gender, and species, then select the Detection Items Corresponding to the Implant Type.
- Select Target Transmitter(s), click and choose Play Button (triangle initial symbol) to initiate signal acquisition. Click OK to confirm.
- Click the Pause Button to end the recording.
- For experimental data collection, sample according to experimental requirements.
- Data analysis
- Load telemetry data. In the software, navigate to File > Load Data. Select Target Parameters. Choose Transmitters from the Form List and set the analysis timeframe according to recorded start/stop times.
- Determine BP offset: Extract data from the 30 min period preceding sampling termination. Calculate and report values as Mean ± SEM.
- Export cardiovascular parameters, including pulse pressure, systolic BP (SBP), diastolic BP (DBP), mean arterial pressure (MAP), HR, and activity counts (Figure 7A). Use the tail-cuff method5,6,28 (Supplementary File 2) to measure BP in mice via the Volume Pressure Recording (VPR) principle and generate pressure curves for analysis (Figure 7B).
- Statistical analysis: Express data as mean ± SEM. Conduct statistical analyses using GraphPad Prism 8.0. Evaluate differences between group means with an unpaired Student's t test, and analyze 24 h continuous data by two-way ANOVA followed by Bonferroni's post hoc test. A p-value < 0.05 is considered to indicate statistical significance.
6. Retrieval of transmitters
- Euthanize the animal using standard techniques. Do not use cervical dislocation, as it may damage the catheter.
- Incise the subcutaneous pocket containing the transmitter with fine surgical scissors. Start at the caudal end of the pocket and extend the incision cranially, avoiding contact with the catheter. Remove the transmitter from the pocket and continue the incision cranially toward the ventral neck region, taking care not to damage the catheter.
- Free the catheter from all connective tissue. Gently lift the transmitter and place it on the surgical field near the animal's head to prevent accidental transection of the catheter.
- Make a midline abdominal incision with fine surgical scissors and extend it cranially to section the diaphragm and sternum. Create bilateral incisions through the lateral rib cage to fully expose the thoracic cavity.
- Identify the heart. Carefully dissect and remove the thymus gland, which appears as white tissue, to visualize the aortic arch. Grasp only the thymus during dissection to avoid damaging underlying vessels, as the catheter lies within the aortic arch beneath the thymus.
- Locate the aortic arch after thymus removal. Gently isolate it from surrounding tissues and place fine-tipped forceps beneath the arch to locate the catheter tip. Incise the aortic arch at this site to expose the catheter tip, taking care not to damage the catheter.
- Trace the catheter tip and carefully incise the aorta retrograde toward the common carotid artery up to the ligation suture site. Gently cut the suture knot to expose the insertion point and retrieve the entire catheter.
7. On-site cleaning and re-sterilization of transmitters
- Removal of tissue and debris: Prepare a 1% Tergazyme solution. Soak the transmitter in the solution for 24 h to remove blood, serum proteins, and tissue debris. Rinse thoroughly under running water.
- Decontamination: Work under a fume hood. Immerse the transmitter in glutaraldehyde within a sealed 50 mL centrifuge tube for 24 h. Rinse thoroughly with sterile saline and store in a sterile package.
8. Regel syringe preparation and catheter filling
- Wear clean gloves. Purge air from the syringe by expressing a small amount of gel from the needle tip.
- For HD-S10, insert the needle tip into the catheter without touching its edges. Advance it below the surface of any residual material. Inject gel under gentle pressure while slowly withdrawing the needle until the tip is fully filled and free of bubbles or debris.
- For HD-X11, avoid needle insertion. Place a small droplet of gel on a sterile surface. Gently compress the catheter bulb to expel air or thrombi. Contact the orifice with the gel droplet. Release to allow retrograde filling via capillary action and negative pressure.
Results
Continuous telemetric recording of BP and HR in C57BL/6 Mice
Eight-week-old male C57BL/6 mice were randomized to undergo transmitter implantation by carotid artery cannulation (CAC) or abdominal aorta cannulation (AAC). After 10 days of recovery, baseline BP was recorded. Continuous 24 h monitoring confirmed stable and reliable signals with the expected circadian rhythm, showing slightly higher nocturnal than diurnal values. Compared with CAC, AAC resulted in higher SBP (Figure 8A), no differences in DBP (Figure 8B), a modest increase in MAP (Figure 8C), and no differences in HR (Figure 8D) during either light or dark phases. As shown in Supplementary Figure 4A-D, per min averages of SBP, DBP, MAP, and HR are also presented. Daily mean SBP (Figure 8E), DBP (Figure 8F), MAP (Figure 8G), and HR (Figure 8H), derived from continuous recordings, followed the same trends as the circadian profiles.
Comparison between telemetric and tail-cuff BP measurements in C57BL/6 mice
To evaluate the accuracy of non-invasive methods, the tail-cuff method was performed in parallel. Tail-cuff recordings showed higher SBP and greater intra-group variability than CAC or AAC. AAC also produced significantly higher SBP than CAC measurements (Figure 9A). In contrast, DBP (Figure 9B) and MAP (Figure 9C) did not differ significantly among these methods.
Comparative analysis of telemetric and tail-cuff BP data in hypertensive rats and mice
To validate implantable telemetry for hypertension research, we used SHRs29 and L-NAME-induced hypertensive mice30. Telemetry transmitters were implanted by AAC in rats and CAC in mice, with parallel tail-cuff measurements for comparison. Figure 10A-C and Supplementary Figure 5A-C showed SBP, DBP, and MAP in SHRs. Tail-cuff recordings overestimated DBP relative to telemetry, whereas SBP and MAP did not differ between these two methods (Figure 10D). In L-NAME (0.5 mg/mL in drinking water for 15 days) treated mice, SBP, DBP, and MAP were shown in Figure 10E-G and Supplementary Figure 5D-F. Tail-cuff measurements yielded higher SBP than telemetry, with no significant differences in DBP or MAP (Figure 10H).
These results validate the implantable telemetry method by demonstrating its capability to continuously record high-fidelity arterial pressure in conscious rodents under physiological conditions. Moreover, the clear detection of circadian BP rhythms in both normotensive and hypertensive models confirms the system's reliability and sensitivity to dynamic physiological changes.
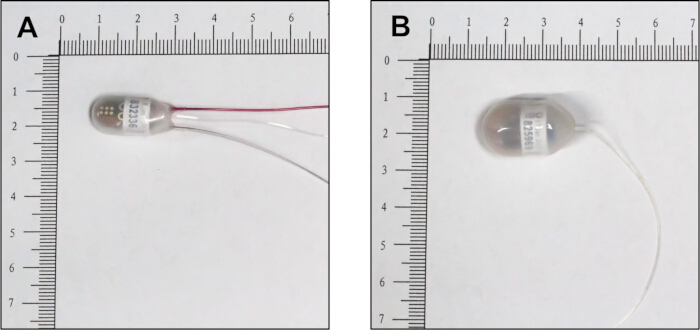
Figure 1: Characteristics of the telemetry transmitters. (A) Specifications of the HD-X11 transmitter. (B) Specifications of the HD-S10 transmitter. Please click here to view a larger version of this figure.
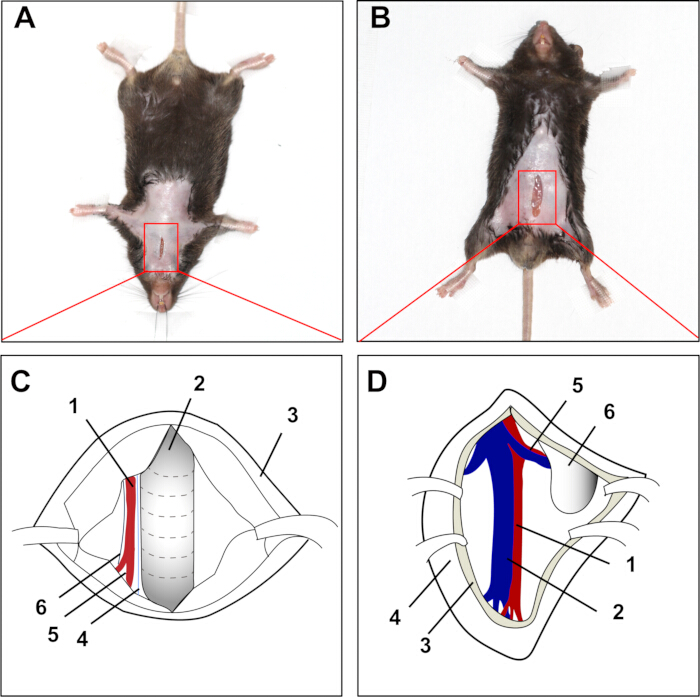
Figure 2: Surgical incisions and anatomical landmarks for transmitter implantation. (A) Midline cervical incision for carotid artery catheterization. (B) Midline abdominal incision for abdominal aorta catheterization. (C) Anatomical view of exposed structures after a midline cervical incision. 1. left common carotid artery; 2. air tube; 3. skin; 4. vagus nerve; 5. branches of the common carotid artery; 6. sympathetic trunk. (D) Anatomical view of exposed viscera and vasculature after a midline lower abdominal incision. 1. abdominal aorta; 2. inferior vena cava; 3. muscularis; 4. skin; 5. renal vein; 6. kidney. Please click here to view a larger version of this figure.
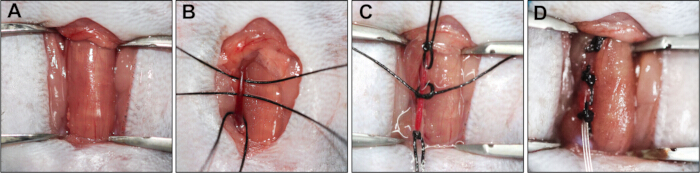
Figure 3: Schematic of BP transmitter implantation through the left carotid artery. (A) Trachea exposure to locate the left carotid artery laterally. (B) Blunt dissection to isolate the artery from surrounding tissues and the vagus nerve; sutures are placed cranially and caudally as shown. (C) Cranial suture permanently ligated; middle suture tied with a slipknot for temporary occlusion; caudal suture tightened to temporarily block blood flow. (D) A catheter was inserted using a vessel dilator and advanced to the correct position, then secured by tying the suture. Please click here to view a larger version of this figure.
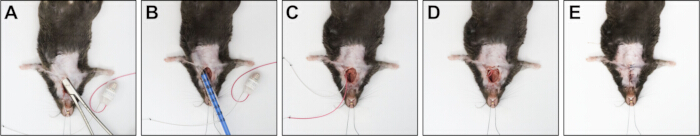
Figure 4: Subcutaneous placement of ECG electrodes and transmitter body following carotid artery cannulation. (A) Formation of a subcutaneous pocket in the left inguinal region using blunt-ended scissors after catheter insertion. (B) Injection of 200 µL of sterile saline (37 °C) into the pocket for lubrication and irrigation. (C) Careful placement of the transmitter body into the subcutaneous pocket. (D) Fixation of the negative ECG lead (uncolored) onto the right pectoral muscle and the positive lead (red) onto the left intercostal muscle. (E) Skin closure after subcutaneous tunneling of ECG leads and catheter. Please click here to view a larger version of this figure.
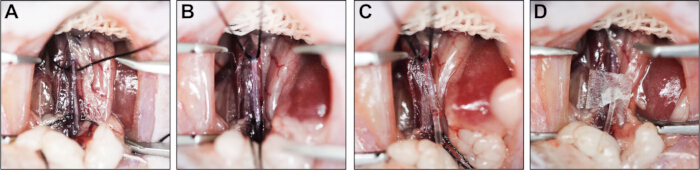
Figure 5: Schematic of the BP transmitter implantation procedure through the abdominal aorta. (A) Exposure of the abdominal aorta adjacent to the inferior vena cava; blunt dissection and placement of sutures at designated anatomical landmarks. (B) Sutures remain untied to preserve collateral blood flow; vessels are temporarily lifted and occluded to briefly interrupt blood flow. (C) Catheter insertion into the vessel using a vessel dilator. (D) After advancing the catheter to the correct position, a biological membrane is applied over the insertion site, followed by adhesive biological glue to achieve hemostasis. Sutures are then released and removed once bleeding is confirmed to be absent. Please click here to view a larger version of this figure.
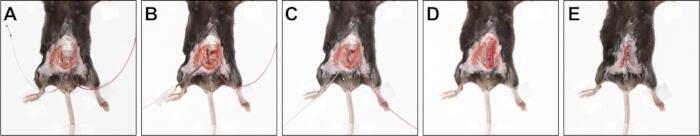
Figure 6: Subcutaneous placement of ECG electrodes and transmitter body following abdominal aorta cannulation. (A) Packing gauze is carefully removed to avoid catheter dislodgement, and the abdominal cavity is irrigated with 100 µL of sterile saline (37 °C). Gentle intestinal massage is applied to reposition organs. The transmitter is positioned above the intestines, parallel to the body axis, with leads directed caudally. (B) An 18 G needle is inserted through the right abdominal wall, and the negative (white) lead is passed through and externalized. (C) The positive (red) lead is externalized on the left side using the same approach. (D) The abdominal wall is sutured, with the positive lead secured subcutaneously 1 cm left of the xiphoid and the negative lead positioned subcutaneously over the right pectoral muscle. (E) Skin closure. Please click here to view a larger version of this figure.
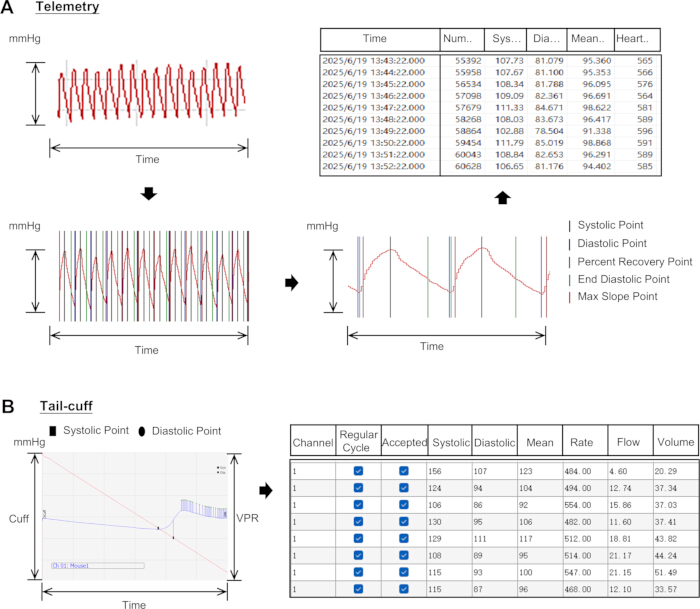
Figure 7: BP data acquisition and analysis. (A) Representative telemetry recording. The raw arterial pressure trace is shown with automatically detected reference points: systolic (black), diastolic (dark blue), percent recovery (green), end-diastolic (light blue), and maximum slope (red). These markers define key parameters for quantitative BP assessment. Data are processed into minute-by-minute values for statistical analysis. (B) Representative tail-cuff recording. The cuff pressure decay curve (red) and pulsatile volume-pressure waveform (blue), reflecting distal blood flow, are displayed. Systolic (square) and diastolic (circle) values are automatically identified. Data from 5 cycles per animal are exported to Excel for further analysis. Please click here to view a larger version of this figure.
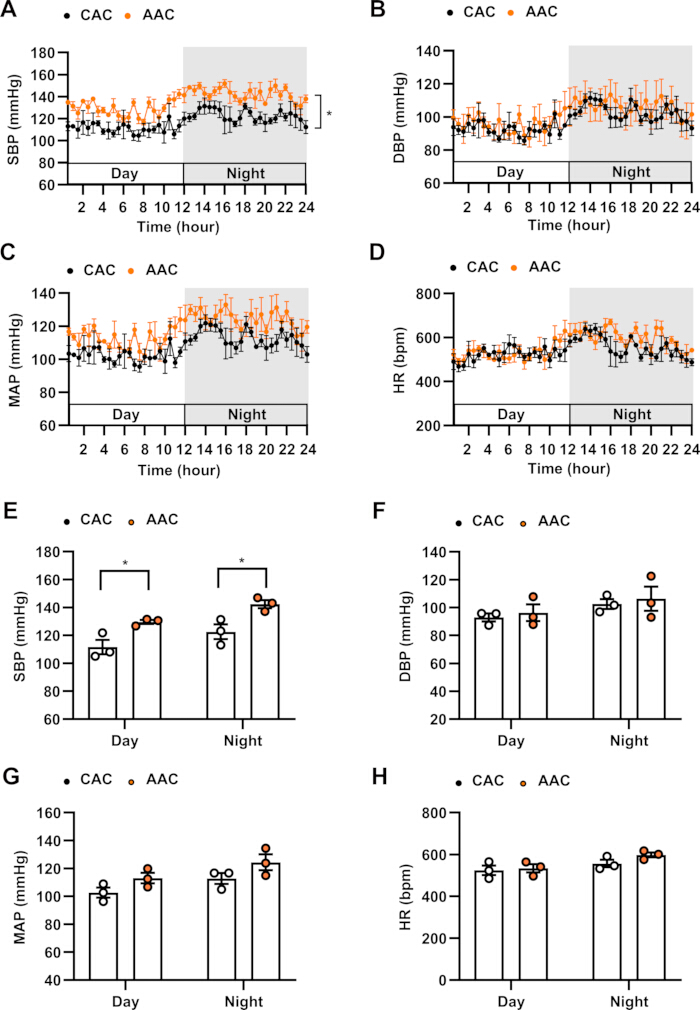
Figure 8: Continuous BP and HR monitoring in C57BL/6 mice via CAC or AAC. (A-D) Continuous 24 h recordings of SBP (A), DBP (B), MAP (C), and HR (D) in mice with CAC or AAC, averaged in 30 min intervals. (E-H) Day- and night-period analysis of mean SBP (E), DBP (F), MAP (G), and HR (H). Data are presented as mean ± SEM. *p <0.05. Please click here to view a larger version of this figure.
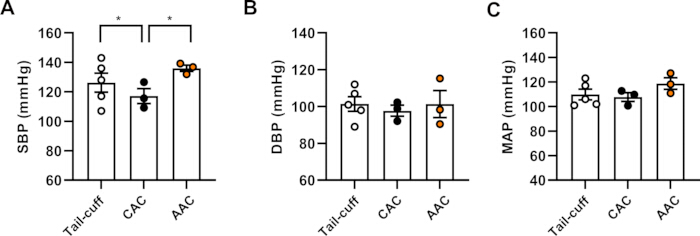
Figure 9: Comparison of BP measurements by telemetry and tail-cuff in the same animal. (A-C) Mean SBP (A), DBP (B), and MAP (C) recorded by tail-cuff, CAC, and AAC (n = 3-5). Data are presented as mean ± SEM. *p < 0.05. Please click here to view a larger version of this figure.
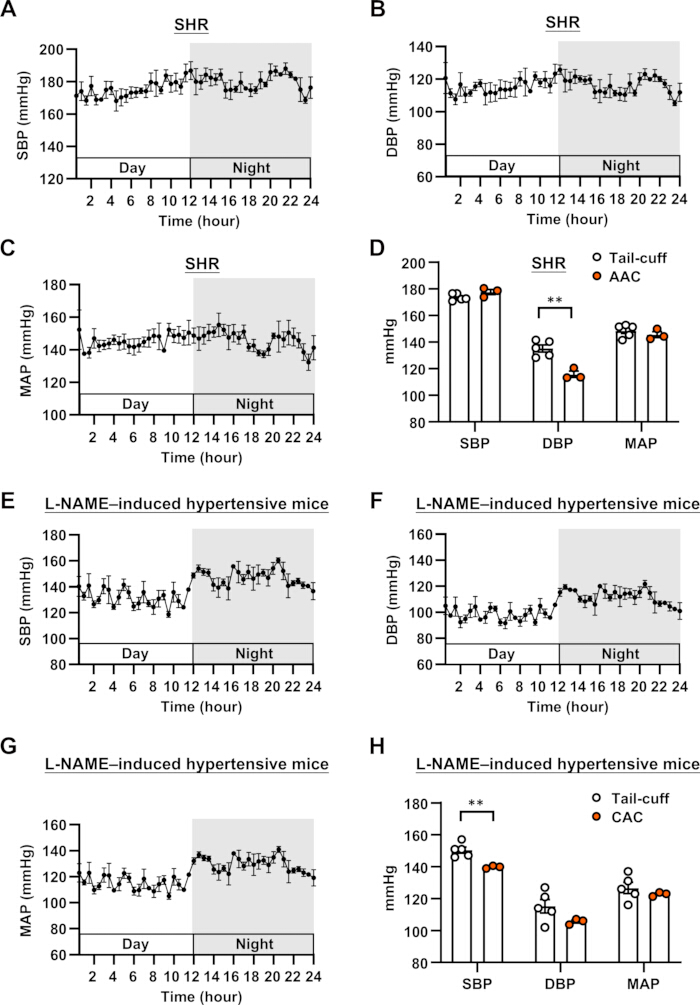
Figure 10: Telemetric versus tail-cuff BP measurements in hypertensive models. (A-C) Continuous 24 h recordings of SBP (A), DBP (B), and MAP (C) in 8-week-old SHR rats implanted by AAC, averaged in 30 min intervals. (D) Comparison of tail-cuff and AAC telemetry measurements in the same SHR rat (n = 3-5). (E-G) Continuous 24 h SBP (E), DBP (F), and MAP (G) recordings in 8-week-old C57BL/6 mice treated with L-NAME (0.5 mg/mL, 15 days) and implanted by CAC, averaged in 30 min intervals. (H) Comparison of tail-cuff and telemetry measurements in the same mice (n = 3-5). Data are presented as mean ± SEM. **p < 0.01. Please click here to view a larger version of this figure.
Supplementary Figure 1: Specialized surgical instruments for telemetry transmitter implantation. (A) Instruments used for implantation surgery (left to right): catheter-holding forceps (x 2), needle holder, fine-tip forceps, dissecting scissors, and hemostat. (B) Magnified view of the tip of the catheter-holding forceps. (C) Custom vessel dilator, designed for precise and controlled entry into blood vessels during catheterization to minimize vascular trauma. Please click here to download this File.
Supplementary Figure 2: Schematic of sensing catheter implantation depth. (A) Telemetry catheter structure of HD-X11. (B) Catheter implantation depth through the carotid artery. (C) Telemetry catheter structure of HD-S10. (D) Catheter implantation depth through the abdominal aorta. Please click here to download this File.
Supplementary Figure 3: Catheter fixation with adhesive and patch. (A) Tissue adhesive. (B) Fiber patch (Trim to pattern as shown). Please click here to download this File.
Supplementary Figure 4: Continuous BP and HR monitoring in C57BL/6 mice by CAC or AAC. (A-D) Continuous 24 h recordings of SBP (A), DBP (B), MAP (C), and HR (D), shown as per-minute averages. Please click here to download this File.
Supplementary Figure 5: Telemetric BP measurements in hypertensive models. (A-C) 24 h recordings of SBP (A), DBP (B), and MAP (C) in 8-week-old SHR rats implanted with AAC, shown as 1 min averages. (D-F) 24 h SBP (D), DBP (E), and MAP (F) in 8-week-old C57BL/6 mice treated with L-NAME (0.5 mg/mL, 15 days) and implanted with CAC, shown as per-minute averages. Please click here to download this File.
Supplementary Table 1: Postoperative monitoring sheet for mice. A standardized form used to systematically record postoperative recovery, pain assessment (Mouse Grimace Scale, MGS), vital signs, and analgesic administration in mice. Please click here to download this File.
Supplementary File 1: Configuration steps for implantable transmitters. The file shows the main setup window for performing the configuration. Please click here to download this File.
Supplementary File 2: Tail-cuff BP measurement method. This file outlines the key steps for performing non-invasive BP assessment using the tail-cuff system. Please click here to download this File.
Discussion
Critical steps within the protocol
Implantable telemetry is widely recognized as the gold standard for continuous, high-fidelity cardiovascular monitoring in conscious, freely moving rodents31,32. A critical step is the selection of the catheter implantation site, either the carotid artery or the abdominal aorta, based on experimental goals. Carotid artery implantation offers technical simplicity and allows catheter advancement into the ascending aorta for high-fidelity pulsatile pressure recordings, suitable for acute studies or central pressure measurements. However, this approach may affect cerebral perfusion in long-term studies and requires careful anticoagulation to prevent thromboembolic complications33,34,35,36. Alternatively, abdominal aorta implantation provides greater stability for chronic recordings with minimal impact on visceral organ blood flow and reduced motion artifacts but demands advanced surgical skill and is generally limited to larger rodents. Meticulous surgical techniques, including precise catheter placement and secure fixation, as well as thorough postoperative care, are essential to ensure data reliability and animal welfare.
Building on established protocols7,37, we implemented optimized steps for hypertensive animal surgery to address inherent pathophysiological challenges. Vascular fragility was mitigated through microsurgical atraumatic clamping, layered hemostasis using gelatin sponge and fibrin sealant, and gradual pressure restoration via a staged clamp-release approach. Catheter stability was reinforced with multi-point fixation and an elastic buffer loop to absorb pulsatile stress. Collectively, these refinements enhance surgical success and preserve signal fidelity in high-pressure models, thereby improving the reliability and reproducibility of experimental measurements.
Troubleshooting
To ensure proper function of the implantable transmitter and the accuracy of pressure measurements, several troubleshooting and preventive steps should be followed. The transmitter should first be checked for activation by using an AM radio to detect a humming tone when a magnet is applied; if no sound is detected, a sufficiently strong magnet should be held within 1 inch of the transmitter for at least 2 s, ensuring proper placement. The transmitter should also be inspected for any physical damage that may have occurred during storage or handling, and it must have been stored under appropriate conditions in a cool, dry environment away from magnetic fields. Additionally, the manufacturing date should be verified to ensure the battery remains within its valid warranty period, ruling out depletion as the cause of malfunction. To address pressure signal drift or inaccuracy, the catheter must be properly hydrated by immersing it in sterile saline for at least 15 min prior to implantation, and the catheter tip should be examined under magnification to check for gel leakage or air bubbles38. The tip must then be positioned optimally within the target vessel, specifically in the aortic arch for carotid cannulation or the abdominal aorta for aortic cannulation, and the pressure offset should be accurately recorded and applied during calibration. In cases of catheter occlusion or suspected blood clot formation indicated by a lost or dampened pressure signal, it is essential to ensure that the catheter tip is sufficiently advanced into the vessel, minimize handling to prevent gel displacement, perform a re-gel procedure if gel loss is suspected, and maintain adequate anticoagulation at the catheter tip39. All troubleshooting steps should be performed post hoc through anatomical verification to ensure the success of subsequent surgical procedures. Finally, to prevent postoperative complications such as inflammation, abscess, or wound dehiscence at the implantation site, appropriate perioperative antibiotics and analgesics should be administered as approved by the institutional veterinary staff, a strict sterile field must be maintained during surgery, and the device should be verified to have undergone and passed all required sterilization procedures prior to implantation.
Limitations of the method
Measurement site affects results. Carotid cannulation reflects central arterial pressure, whereas abdominal aortic cannulation represents peripheral pressure. SBP is mainly determined by ventricular ejection and is similar across sites, while DBP depends on vascular resistance and arterial compliance, leading to slight site-dependent differences32,40,41,42.
In addition to these physiological considerations, telemetry is invasive, requiring surgical implantation and recovery, and is sensitive to animal size, vessel diameter, and catheter positioning. Device-related issues such as battery depletion, signal drift, or mechanical damage can affect data quality. In hypertensive models, peripheral vascular changes (e.g., increased resistance or arterial stiffening) may influence local pressures, requiring careful interpretation. Other limitations include the need for specialized surgical skills and a higher cost43. Consider site-specific constraints as well. Carotid implantation may reduce cerebral blood flow in long-term studies, while abdominal aorta implantation is technically challenging, suitable only for larger animals, and may attenuate high-frequency signals, affecting pulsatile pressure analysis.
Significance with respect to existing methods
Implantable telemetry enables continuous, stress-free BP monitoring with superior temporal resolution, allowing detection of dynamic BP changes that intermittent methods may miss. Although more technically demanding and costly, telemetry delivers more physiologically relevant data crucial for studying disease progression and treatment effects44.
Future applications of the technique
Future developments in telemetry technology are expanding its applications and impact. Miniaturization of devices now allows implantation in juvenile and small animal models, enhancing translational relevance in developmental and genetic studies45. Integration with advanced waveform analysis, neural modulation techniques (e.g., optogenetics), and multimodal imaging facilitates deeper mechanistic insights and early biomarker discovery. Furthermore, clinical-grade implantable telemetry devices, such as CardioMEMS, are transforming patient management of resistant hypertension and autonomic dysfunction, underscoring the translational bridge between preclinical models and human health46. These innovations are expected to further extend the utility of implantable telemetry in cardiovascular research and therapeutic development.
In conclusion, implantable telemetry represents a transformative technology that overcomes the limitations of traditional BP measurement methods. By enabling continuous, high-resolution monitoring in conscious animals, it captures the complex dynamics of cardiovascular regulation and pathology. The outlined protocol and considerations provide practical guidance for optimizing surgical approaches and data interpretation, facilitating robust preclinical studies that inform translational research.
Disclosures
The authors have nothing to disclose.
Acknowledgements
This work was supported by the Natural Science Foundation of China (grant 82230012, 81830015 to N. Wang, grant 91939108, 82570478 to L. Xiao).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| APR-1 Ambient Pressure Reference | Data Sciences International (DSI) | The APR-1 Ambient Pressure Reference is a required component of each DSI telemetry system where pressure measurements are being monitored in order to dynamically compensate for the effects change in barometric pressure has on the absolute (relative to vacuum) measurements taken by the telemetry implants | |
| Cellulose patch kit | Data Sciences International (DSI) | 370-0036-001 | |
| Glutaraldehyde | MetriCide | 89132-856 | |
| Graefe Forceps-curved, with teeth | Data Sciences International (DSI) | 11054-10 | |
| Implant(HD-S10) | Data Sciences International (DSI) | 825969 | |
| Implant(HD-S10) | Data Sciences International (DSI) | 910265 | |
| Implant(HD-X11) | Data Sciences International (DSI) | 1315981 | |
| Implant(HD-X11) | Data Sciences International (DSI) | 1315986 | |
| isoflurane | RWD Life Science | R510-22-10 | |
| Lexar-Baby Scissors-straight, 10 cm | Data Sciences International (DSI) | 14078-10 | |
| Matrix 2.0 (MX2) | Data Sciences International (DSI) | The Matrix 2.0 (MX2) manages communication between PhysioTel and PhysioTel HD telemetry implants and the acquisition computer. | |
| Moria Instrument Case | Data Sciences International (DSI) | 20311-21 | |
| Normal Saline | Kelong Pharmaceutical | C1250213B1 | |
| Olsen-Hegar Needle Holder-extra delicate | Data Sciences International (DSI) | 12002-12 | |
| pentobarbital sodium | Sigma-Aldrich | P3761 | |
| RPC-1 receivers | Data Sciences International (DSI) | 34668 | The RPC-1 receiver is most often used for monitoring animals housed in plastic cages that can be placed on top of the receiver. The RPC-1 receiver provides reliable reception of data transmitted via digital telemetry and has two receiving antennae oriented at right angles to minimize dropouts due to directionality of the transmission pattern. |
| RPC-1 receivers | Data Sciences International (DSI) | 34669 | |
| Tergazyme | Sigma-Aldrich | Z273287 | |
| Vessel Cannulation Forceps, 11 cm long | Data Sciences International (DSI) | 00608-11 | |
| Vessel Dilator-45 degree angled tip, 13.5 cm long | Data Sciences International (DSI) | 00276-13 | |
| Vetbond Tissue Adhesive | Minnesota Mining and Manufacturing Company (3M) | 1469SB | |
| Xylazine 20 | Sigma-Aldrich | X1251 | |
| Zoletil 50 | Virbac Laboratories |
References
- Van Vliet, B. N., Chafe, L. L., Montani, J. P. Characteristics of 24 h telemetered blood pressure in enos-knockout and c57bl/6j control mice. J Physiol. 549 (Pt 1), 313-325 (2003).
- Braga, V. A., Prabhakar, N. R. Refinement of telemetry for measuring blood pressure in conscious rats. J Am Assoc Lab Anim Sci. 48 (3), 268-271 (2009).
- Morgan, T. O., et al. Cardiac hypertrophy depends upon sleep blood pressure: A study in rats. J Hypertens. 18 (4), 445-451 (2000).
- Kurtz, T. W., Griffin, K. A., Bidani, A. K., Davisson, R. L., Hall, J. E. Recommendations for blood pressure measurement in animals. Arteriosclerosis Thrombosis Vasc Biol. 25 (3), 478-479 (2005).
- Wang, Y., Thatcher, S. E., Cassis, L. A. Measuring blood pressure using a noninvasive tail cuff method in mice. Methods Mol Biol. 1614, 69-73 (2017).
- Feng, M., et al. Validation of volume-pressure recording tail-cuff blood pressure measurements. Am J Hypertens. 21 (12), 1288-1291 (2008).
- Mancarella, S., Parks, C., Alam, M. A. Long-term blood pressure measurement in freely moving mice using telemetry. J Vis Exp. (111), e53991(2016).
- Butz, G. M., Davisson, R. L. Long-term telemetric measurement of cardiovascular parameters in awake mice: A physiological genomics tool. Physiol Genomics. 5 (2), 89-97 (2001).
- Mills, P. A., et al. A new method for measurement of blood pressure, heart rate, and activity in the mouse by radiotelemetry. J Appl Physiol (1985). 88 (5), 1537-1544 (2000).
- Huetteman, D. A., Bogie, H. Direct blood pressure monitoring in laboratory rodents via implantable radio telemetry. Methods Mol Biol. 573, 57-73 (2009).
- Popova, A., et al. Adaptation to a blood pressure telemetry system revealed by measures of activity, agility and operant learning in mice. J Pharmacol Toxicolog Methods. 85, 29-37 (2017).
- Lemmer, B., Mattes, A., Böhm, M., Ganten, D. Circadian blood pressure variation in transgenic hypertensive rats. Hypertension. 22 (1), 97-101 (1993).
- El-Mas, M. M., Abdel-Rahman, A. A. Longitudinal studies on the effect of hypertension on circadian hemodynamic and autonomic rhythms in telemetered rats. Life Sciences. 76 (8), 901-915 (2005).
- Anderson, N. H., et al. Telemetry for cardiovascular monitoring in a pharmacological study: New approaches to data analysis. Hypertension. 33 (1 Pt 2), 248-255 (1999).
- Kapsdorferová, V., Grešová, S., Švorc, P. Measurement of blood pressure in rats: Invasive or noninvasive methods. Physiol Rep. 12 (17), e70041(2024).
- Hilliard, L. M., et al. Gender differences in pressure-natriuresis and renal autoregulation. Hypertension. 57 (2), 275-282 (2011).
- Gargiulo, S., et al. Mice anesthesia, analgesia, and care, part ii: Anesthetic considerations in preclinical imaging studies. Ilar J. 53 (1), E70-E81 (2012).
- Chang, M. Y., et al. A mice model of chlorhexidine gluconate-induced peritoneal damage. J Vis Exp. (182), e63903(2022).
- Carbone, E. T., Lindstrom, K. E., Diep, S., Carbone, L. Duration of action of sustained-release buprenorphine in 2 strains of mice. J Am Assoc Lab Anim Sci. 51 (6), 815-819 (2012).
- Kuchinsky, S., Ascher, J. Postoperative multimodal pain management. Lab Animal. 44 (4), 132-134 (2015).
- Busch, U., et al. Pharmacokinetics of meloxicam in animals and the relevance to humans. Drug Metab Dispos. 26 (6), 576-584 (1998).
- Bourque, S. L., Adams, M. A., Nakatsu, K., Winterborn, A. Comparison of buprenorphine and meloxicam for postsurgical analgesia in rats: Effects on body weight, locomotor activity, and hemodynamic parameters. J Am Assoc Lab Anim Sci. 49 (5), 617-622 (2010).
- Oliver, V. L., Pang, D. S. J. Pain recognition in rodents. Vet Clin North Am Exot Anim Pract. 26 (1), 121-149 (2023).
- Matsumiya, L. C., et al. Using the mouse grimace scale to reevaluate the efficacy of postoperative analgesics in laboratory mice. J Am Assoc Lab Anim Sci. 51 (1), 42-49 (2012).
- Mogil, J. S., Pang, D. S. J., Silva Dutra, G. G., Chambers, C. T. The development and use of facial grimace scales for pain measurement in animals. Neurosci Biobehav Rev. 116, 480-493 (2020).
- Le Moëne, O., Larsson, M. A new tool for quantifying mouse facial expressions. eNeuro. 10 (2), (2023).
- Jacobsen, K. R., Kalliokoski, O., Teilmann, A. C., Hau, J., Abelson, K. S. Postsurgical food and water consumption, fecal corticosterone metabolites, and behavior assessment as noninvasive measures of pain in vasectomized balb/c mice. J Am Assoc Lab Anim Sci. 51 (1), 69-75 (2012).
- Daugherty, A., Rateri, D., Hong, L., Balakrishnan, A. Measuring blood pressure in mice using volume pressure recording, a tail-cuff method. J Vis Exp. (27), e1291(2009).
- Safar, M., Chamiot-Clerc, P., Dagher, G., Renaud, J. F. Pulse pressure, endothelium function, and arterial stiffness in spontaneously hypertensive rats. Hypertension. 38 (6), 1416-1421 (2001).
- Jama, H. A., et al. Rodent models of hypertension. Br J Pharmacol. 179 (5), 918-937 (2021).
- Pickering, T. G., et al. Recommendations for blood pressure measurement in humans and experimental animals: Part 1: Blood pressure measurement in humans: A statement for professionals from the subcommittee of professional and public education of the American Heart Association Council on High Blood Pressure Research. Circulation. 111 (5), 697-716 (2005).
- Gunasekaran, D., Turner, J. M. Current and developing technologies for bp monitoring. Curr Cardiol Rep. 25 (10), 1151-1156 (2023).
- Faraci, F. M., Heistad, D. D., Mayhan, W. G. Role of large arteries in regulation of blood flow to brain stem in cats. J Physiol. 387, 115-123 (1987).
- Santillan, A., et al. Cannulation of the internal carotid artery in mice: A novel technique for intra-arterial delivery of therapeutics. J Neurosci Methods. 222, 106-110 (2014).
- Sasaki, T., et al. A novel model of occlusive thrombus formation in mice. Lab Invest. 84 (11), 1526-1532 (2004).
- Flores Gerónimo, J., Corvera Poiré, E., Chowienczyk, P., Alastruey, J. Estimating central pulse pressure from blood flow by identifying the main physical determinants of pulse pressure amplification. Front Physiol. 12, 608098(2021).
- Rötzer, R. D., et al. Implantation of combined telemetric ecg and blood pressure transmitters to determine spontaneous baroreflex sensitivity in conscious mice. J Vis Exp. (168), e62101(2021).
- Mccormick, D., et al. Frequency response of implantable blood pressure telemetry systems. Clin Exp Pharmacol Physiol. 37 (8), 862-869 (2010).
- Wang, Y., Thatcher, S. E., Cassis, L. A. Blood pressure monitoring using radio telemetry method in mice. Methods Mol Biol. 1614, 75-85 (2017).
- Pichler, G., et al. Pulse pressure amplification and its determinants. Blood Press. 25 (1), 21-27 (2016).
- Mattson, D. L. Comparison of arterial blood pressure in different strains of mice. Am J Hypertens. 14 (5 Pt 1), 405-408 (2001).
- Westerhof, N., Lankhaar, J. W., Westerhof, B. E. The arterial windkessel. Med Biol Eng Comput. 47 (2), 131-141 (2009).
- Safar, M. E., et al. Central pulse pressure and mortality in end-stage renal disease. Hypertension. 39 (3), 735-738 (2002).
- Drüeke, T. B., Devuyst, O. Blood pressure measurement in mice: Tail-cuff or telemetry. Kidney Int. 96 (1), 36(2019).
- Cruz-López, E. O., Merkus, D., Danser, A. H. J. Blood pressure monitoring through radiotelemetry: Exploring the viability of its application in multihoused small laboratory animals. Hypertension. 81 (5), 947-950 (2024).
- Leung, C. C. Current role of the cardiomems device for management of patients with heart failure. Curr Cardiol Rep. 21 (9), 98(2019).