Here, we present a protocol to detect tumor somatic mutations in circulating DNA present in patient biological fluids (biofluids). Our droplet digital polymerase chain reaction (dPCR)-based method enables quantification of the tumor mutation allelic frequency (MAF), facilitating a minimally invasive complement to diagnosis and temporal monitoring of tumor response.
Method Article
Detection and Monitoring of Tumor Associated Circulating DNA in Patient Biofluids
In This Article
Summary
Abstract
Complications associated with upfront and repeat surgical tissue sampling present the need for minimally invasive platforms capable of molecular sub-classification and temporal monitoring of tumor response to therapy. Here, we describe our dPCR-based method for the detection of tumor somatic mutations in cell free DNA (cfDNA), readily available in patient biofluids. Although limited in the number of mutations that can be tested for in each assay, this method provides a high level of sensitivity and specificity. Monitoring of mutation abundance, as calculated by MAF, allows for the evaluation of tumor response to therapy, thereby providing a much-needed supplement to radiographic imaging.
Introduction
Due to limitations in the availability of tumor tissue for molecular analyses, there is a need for the development of highly sensitive methods capable of detecting tumor somatic mutations in patient biofluids, including plasma, serum and cerebrospinal fluid (CSF). For example, pediatric diffuse midline gliomas (DMGs) present a challenge due to their neuroanatomical location. Over the past decade, molecular profiling of DMG tissue specimens has uncovered driver mutations in this tumor type1 and has revealed spatial and temporal heterogeneity of mutations, making biopsy necessary for characterizing a patient within a disease subgroup and promoting molecularly-targeted therapies2. As such, clinical trials advocate for integrating surgical biopsies for tumor molecular profiling at upfront diagnosis3,4,5,6. During treatment, monitoring of therapeutic response in DMGs is limited to MRI, which lacks sensitivity to detect small changes or tumor genomic evolution. MRI is also prone to detect pseudoprogression, transient inflammation at the site of the tumor that mimics true progression on imaging and may misinform interpretation of tumor response7. Thus, DMGs represent a tumor type with a high need for an alternative, minimally invasive means of detecting tumor mutations and monitoring clinical response. In order to address these needs, we developed and optimized a protocol for detecting, and quantifying the allelic frequency of, tumor mutations in cfDNA from plasma, serum and CSF of children with midline gliomas8. Given that childhood DMGs often (>80%) harbor a somatic lysine-to-methionine mutation at position 27 of histone variant H3.1 (H3.1K27M, 20% of cases) or H3.3 (H3.3K27M, 60% of cases)1, these and other mutations characteristic of DMGs (i.e., ACVR1, PIK3R1) were targeted for mutant allele quantification using cfDNA8. This assay can be tailored to detect hotspot mutations in other tumor types using sequence-specific primers and probes. The versatility of this approach makes it applicable to a variety of cancers which would benefit from the integration of cfDNA-based diagnostic tools and therapeutic monitoring.
To sensitively detect low allelic frequency mutations in cfDNA, we employ a droplet digital PCR (dPCR)-based approach. In this method, the PCR reaction mixture is partitioned into a theoretical maximum of 10 million droplets using the dPCR platform (e.g., RainDance), with 7-9 million droplets per PCR well typically seen experimentally. Due to the high degree of sample partitioning, at most only one to two DNA molecules can be present in each droplet. PCR amplification and sequence-specific fluorescent probe hybridization can occur in each droplet, such that millions of reactions take place. This maximizes the sensitivity and enables detection of rare mutant alleles, which might otherwise go undetected against a background of wildtype DNA. The utilization of locked nucleic acid (LNA) probes enhances the specificity of the assay by restricting mismatch hybridization and supporting accurate mutation detection9,10,11. Here, we describe our methods of sample processing, cfDNA extraction, preamplification of target alleles, dPCR and data analysis.
Protocol
All methods described here have been approved by the Institutional Review Board of the University of California San Francisco (San Francisco, CA; IRB #14-13895) and the Children's National Health System (Washington, D.C.; IRB #1339). Specimens were collected and studied after obtaining informed consent from the patient or patient's guardian.
1. Consenting Patients Under IRB Protocol for Collection and Storage of Biological Specimens
- Collect patient samples after written informed consent is obtained from each patient, or the patient's guardian, for participation in a clinical trial or for biorepository as approved by the respective Institutional Review Board.
- Patients included in this study were diagnosed with a brain tumor radiographically. No exclusion criteria were used. Specimens were collected and studied after obtaining informed consent from the patient or patient's guardian.
2. Blood Collection and Separation of Plasma or Serum
- Collect the blood sample using a 10.0 mL draw into blood collection tubes. If collecting blood for plasma, use K2- or K3-EDTA tubes, heparin or cfDNA blood collection tubes. If collecting blood for serum, use gel-barrier tubes containing the clot activator and gel to separate serum.
NOTE: While 10 mL is recommended to enable replicate experiments, a minimum of 3 mL will suffice. - Carefully invert the collection tube 10 times to mix the blood sample with the collection tube reagents.
- Leave the blood samples from which the serum will be collected at room temperature for 30 min to allow blood to clot. If processing blood to obtain plasma, proceed immediately to step 2.4.
NOTE: Samples being processed for plasma may be kept on ice for a maximum of 2 h prior to centrifugation. However, a rapid transition from the blood draw to processing minimizes cfDNA degradation. - Centrifuge blood collection tubes at 2,000 x g for 15 min in a centrifuge set to 4 °C to separate plasma or serum from white and red blood cell layers.
- Taking care not to disturb the white blood cell layer (which forms a thin line between the upper plasma/serum layer and lower layer of packed red blood cells), pipette the top layer of plasma/serum (which may be clear, yellow, or pink in color) equally in 1 mL aliquots into sterile polypropylene screw-cap cryovials.
- Record the subject identification number, specimen type (plasma or serum), and collection date on the label of the cryovials.
- Store cryovials in the -80 °C freezer until use. If a -80 °C freezer is not available, store the samples at -20 °C for up to one week.
3. CSF Collection and Processing
- Collect CSF from a shunt, lumbar puncture, or surgery.
NOTE: Such procedures should only be conducted if deemed necessary by clinicians. Extra sample beyond that which is necessary for clinical use may be used for research purposes. - Measure the volume of CSF collected and make note of its color (bloody, yellow, clear).
- Centrifuge the collection tube at 10,000 x g for 10 min at 4 °C to pellet the cellular debris.
- Transfer the CSF supernatant equally in 500 µL aliquots into polypropylene screw cap cryovials.
- Record the subject identification number, specimen type, and date of specimen collection on the label of the cryovials. Store at -80 °C until use.
4. Extraction of cfDNA from Liquid Specimens
- Perform cfDNA extraction protocol as per the instructions in the cfDNA extraction kit handbook12.
- Clean the bench space and equipment with 10% bleach and 70% ethanol.
NOTE: Use of a PCR hood, regular changing of gloves and frequent decontamination of the bench space and equipment with 10% bleach and 70% ethanol during all steps of the protocol is important to avoid sample contamination. - Prepare aliquots of reagents, e.g., wash buffers, from the extraction kit to avoid cross-contamination.
- Clean the bench space and equipment with 10% bleach and 70% ethanol.
- Thaw patient samples on ice prior to beginning the extraction. For plasma/serum, thaw 1 mL aliquot of sample. For CSF, thaw 500 µL aliquot of sample.
NOTE: Lysis steps (4.5-4.8) of the extraction protocol differ between plasma/serum and CSF, but from step 4.9 onwards, the protocol is identical for both types of biofluids. - Set a heating block to 60 °C for use during the lysis step (4.6).
- Prepare the lysis buffer and carrier RNA mixture in a 15 mL tube by adding 5.6 µL of carrier RNA and 0.9 mL of lysis buffer per sample12.
- For plasma/serum, add 100 µL proteinase K, 1 mL of sample, and 0.8 mL of lysis buffer/carrier RNA mixture prepared in step 4.4 to a labeled 2.0 mL tube. Mix by pulse vortexing for 30 s at high speed12.
- For CSF, add 125 µL proteinase K, 500 µL of the sample, 1 mL of lysis buffer/carrier RNA mixture, and 250 µL tissue lysis buffer to a 2.0 mL tube. Bring the full volume up to 2 mL by adding 125 µL of 1x phosphate-buffered saline (PBS). Mix by pulse vortexing for 30 s at high speed12.
- Incubate samples for 30 min at 60 °C in the heating block12.
- Remove samples from the heating block and lower the temperature to 56 °C. Return samples to the bench and transfer the lysate into new labeled 15 mL tubes.
- For plasma/serum, add 1.8 mL of nucleic acid binding bufferand mix for 30 s by pulse vortexing12.
- For CSF, add 3.6 mL of nucleic acid binding buffer and mix for 30 s by pulse vortexing12.
- Incubate samples for 5 min on ice12.
- Insert the column into the vacuum connector. Open the column and insert a 20 mL tube extender into the column12.
- Pipette the contents of the 15 mL tube directly into the bottom of the tube extender, avoiding leaving droplets on the walls of the tube extender.
- With the switch of the vacuum connector closed, switch on the vacuum pump. Once the pressure has built to 900 mbar, open the valve of the vacuum connector. The sample will now flow through the column.
- Once all the lysate has been drained from the column, turn off the pump and open the trapdoor to the vacuum connector, relieving the pressure gradient. Once the pressure reaches 0 mbar, close the valve of the vacuum connector and the trapdoor.
- Remove the 20 mL tube extender, being careful not to pass the extender of one column over a neighboring column, as this can cross-contaminate samples. Dispose of the tube extender.
- Add 600 µL of first wash buffer to the column12.
- Leave lids of tubes open and turn on the vacuum pump. Let the pressure gauge reach 900 mbar, then turn the switch on the vacuum connector to the open position to draw the wash buffer through the column.
- Turn off the vacuum pump, open the trapdoor to release pressure, and relieve the pressure to 0 mbar. Turn valve of the vacuum connector to the closed position.
- Add 750 µL of second wash buffer to the column and repeat steps 4.16-4.1712.
- Add 750 µL of MB grade ethanol to the column and repeat steps 4.16-4.1712.
- Close the lid of the column and place the column inside a new 2.0 mL collection tube. Dispose of the vacuum connector12.
- Centrifuge the tube with the column at 20,000 x g for 3 min at room temperature12.
- Place the column into a new collection tube and open the lid of the tube. Place a laboratory tissue over the top and incubate at 56 °C for 10 min12.
- Place the column into a clean 1.5 mL PCR-clean tube and pipette 100 µL of elution buffer (or molecular biology grade H2O (MB H2O)) directly into the center of the column. Do not touch the column with a pipette tip. Close the lid and leave at room temperature for 3 min.
- Centrifuge at 20,000 x g at room temperature for 1 min to elute cfDNA12.
- Pipette the eluate back into the column and incubate at room temperature for 3 min.
- Repeat the centrifugation at full speed for 1 min to elute cfDNA a second time to increase yield (as per manufacturer's recommendation).
- Store cfDNA in labeled DNase/RNase free PCR-clean tubes at 4 °C or proceed directly to step 5.
5. Vacuum Concentration of cfDNA
- Insert and balance the tubes containing eluted cfDNA into holders on the vacuum concentrator. Open the lids of the tubes. Set the temperature of vacuum concentrator to 23 °C.
- Turn on the vacuum concentrator, then turn on the vapor trap. Centrifuge samples for 40 min or until a final volume of 10.5-11 µL is reached.
- If the volume is below 10.5 µL, add DNA suspension buffer or MB H2O to reach a final volume of 10.5 µL.
- Pipette the full volume along the walls of the tube to remove residual DNA fragments.
- Briefly centrifuge the samples on a tabletop centrifuge to collect droplets on the walls of the tubes.
- Proceed directly to the preamplification step (step 8) or store samples at 4 °C.
- Wrap lids of tubes in a laboratory film to avoid contamination if they are stored for later use.
6. Design and Preparation of Primers and Probes
- Design forward and reverse primers, and wildtype and mutant LNA probes, for the target(s) of interest. Commercially order lyophilized primers and probes (refer to Table of Materials).
NOTE: Sequences for primers and probes targeting H3F3A p.K27M and other target mutations for pediatric midline gliomas can be found in Supplementary Table 3 of Panditharatna et al., 20188. - Prior to opening the lyophilized primers and probes, briefly centrifuge the tubes. Add the appropriate volume of DNA suspension buffer or MB H2O, as noted on the product specification sheet, to resuspend the lyophilized primers and probes to a concentration of 100 µM.
- Gently vortex, pipette up and down several times to mix and briefly centrifuge primers and probes using a tabletop centrifuge.
- Prepare 10 µM aliquots of primers and probes by adding 10 µL of 100 µM stock to 90 µL of DNA suspension buffer or MB H2O.
- Prepare 1 µM aliquots of forward and reverse primers (to be used for preamplification), by adding 10 µL of the 10 µM primer to 90 µL of DNA suspension buffer or MB H2O.
- Store primers and probes at 4 °C in air-tight dark containers. Wrap laboratory film around lids to avoid contamination, and cover probes in aluminum foil to avoid exposure to light. Store probes at -20°C for long term storage if they are not being used regularly.
7. Selection of Positive Controls
- Select tumor tissue genomic DNA (gDNA) sample(s) with known DNA concentration, which harbors the mutation of interest at a known allelic frequency to be used as a positive control.
- Use 0.025 ng of positive control tumor tissue DNA in the preamplification step (step 8).
NOTE: This DNA input provides a robust positive signal on dPCR (as determined by performing serial dilutions of tumor tissue gDNA harboring H3F3A p.K27M mutation8) while minimizing the amount of sample required.
- Use 0.025 ng of positive control tumor tissue DNA in the preamplification step (step 8).
8. Preamplification of Target Alleles
NOTE: Preamplification protocol is as per Jackson et al., 201613.
- Clean the bench space and equipment with 10% bleach and 70% ethanol.
- Obtain 1 µM forward and reverse primers, cfDNA samples, gDNA positive controls, and DNA polymerase master mix, and set on ice.
- Calculate the volume of reagents needed to preamplify the desired number of cfDNA samples and positive control, for either singleplex or multiplex preamplification as follows:
- For singleplex preamplification (to preamplify wildtype and mutant alleles for a single mutation of interest), prepare PCR reaction mixture by adding 17.5 µL of DNA polymerase master mix, and 3.5 µL of forward and reverse primers (100 nM) per sample13.
- For multiplex preamplification (to preamplify two sets of wildtype and mutant alleles for two mutations of interest), prepare PCR reaction mixture by adding 17.5 µL of DNA polymerase master mix and 1.75 µL of each set of forward and reverse primers (50 nM) per sample13.
NOTE: Prepare enough PCR reaction mixture for the number of samples plus 10% extra to account for any pipetting error.
- Dispense 24.5 µL of PCR reaction mixture into each well of an 8-well PCR strip tube13.
- Dispense 10.5 µL of DNA sample into the appropriate well to bring the total reaction volume to 35 µL13. Gently pipette the full volume up and down 10 times to mix.
- Perform PCR amplification at 98 °C for 3 min; 9 cycles of 98 °C for 10 s, annealing temperature for 3 min, 72 °C for 30 s; and an extension at 72 °C for 2 min13.
- Transfer the full volume of preamplified product to labeled DNase/RNase free PCR-clean tubes and dilute in 140 µL TE DNA suspension buffer (pH 8.0)13.
- Wrap the lids of the tubes in laboratory film. Store the preamplified product at 4 °C. For long term preservation, store at -20 °C.
9. Detection and Quantification of Target DNA Using dPCR
- Clean the bench space and equipment with 10% bleach and 70% ethanol.
- Set 10 µM primers and probes, genotyping master mix, and DNA samples on ice. Store the droplet stabilizing oil at room temperature.
- Gently vortex and briefly centrifuge all reagents except droplet stabilizing oil.
- Ensure that the compressed nitrogen gas cylinder attached to the droplet-generating instrument and the quantification instrument (Table of Materials) is set at 90 psi.
- Turn on the drop-generating instrument and the computer with the instrument software. Launch the software and click Start Initializing.
- Run a high-pressure flush on the drop generating instrument if it has not been used in one week or more.
- Prepare the dPCR reaction mixture for 8 wells of the PCR strip tube plus 10% extra, by adding 220 µL of genotyping master mix, 8.8 µL each of 10 µM wildtype and mutant probes, 39.6 µL each of 10 µM forward and reverse primers, and 17.6 µL of droplet stabilizing oil14.
- Gently mix the dPCR reaction mixture by pipetting the full volume up and down 10-20 times. Do not vortex or centrifuge after droplet stabilizing oil has been added to the reaction mixture.
- Obtain a PCR 8-well strip tube and dispense 38 µL of dPCR reaction mixture directly into the bottom of each well14. Remove any bubbles with a clean pipette tip.
NOTE: PCR strip tubes that are interlocked or packed tightly together can result in static electric charges, causing coalescence and noisy signal when analyzing dPCR data. To avoid this, aliquot strip tubes into separate biohazard bags, avoid over-packing the bags, and keep the tubes from rubbing together. - Add 12 µL of preamplified DNA sample to the appropriate wells of the PCR strip tube. For the negative control, add 12 µL of MB H2O.
NOTE: Analyze cfDNA samples in replicate wells. For CSF, analyze at least in duplicate, and for plasma/serum analyze each sample in triplicate. - Gently pipette the full volume up and down 10 times to mix the reaction mixture with the DNA sample.
- Obtain a new droplet-generating instrument chip and pipette the full volume from wells 1-8 of the PCR strip tube into the corresponding channels A-H in the chip. Avoid touching the bottom of the channels with a pipette tip.
- Obtain a new clean PCR strip tube and insert into the droplet-generating instrument. Scan or manually enter the droplet-generating instrument chip ID into the software on the instrument computer. Enter names for each of the 8 channels. Click Start the run to begin dropletizing samples.
- When the dropletization has completed, remove the PCR strip tube and apply strip tube caps.
- Transfer the strip tube to a thermal cycler and balance with another strip tube containing 80 µL of water per well.
- Program the thermal cycling conditions14 as: 95 °C for 10 min; 45 cycles of two temperatures: 95 °C for 30 s and annealing temperature for 2 min; 98 °C for 10 min; and hold at 10 °C.
- Set the ramp rate to 0.5 °C/s and set the sample volume to 80 µL14.
- When thermal cycling is complete, remove the strip tube and transfer to the quantification instrument. Remove PCR strip caps and replace with high speed caps.
- Turn on the quantification instrument and the connected computer with instrument software. Launch the instrument software and click Setup a Run.
- Place the strip tube into the quantification instrument.
- Obtain a new quantification instrument chip and scan or manually enter the chip ID into the instrument. Insert the chip into the machine.
- Place the metal shield on top of the chip and close the lid of the instrument.
- In the computer software, enter a name for the dPCR run and for each of the 8 channels (A-H). Select Fast Mode (which must be used with high speed caps) and click Start to begin the quantification.
- When quantification is complete, remove the metal shield (to be saved and reused) and dispose of the PCR strip tube and chip. On the instrument computer, the Run Log will contain result files for each run. Use the .fcs files for each sample to analyze with the analyst software.
10. Data Analysis
- Launch the analyst software and open the .fcs files to analyze raw spectral data. Under Analysis View, select Intact. Under Sample View, click the boxes next to each of the 8 samples so that there is a check mark in each box. The software will plot signals for the mutant (FAM) and wildtype (HEX) alleles along the x- and y-axes, respectively .
- Use the calculated matrix function to apply for the spectral compensation on intact droplets, as per the manufacturer's instructions15.
- Adjust the axis settings under Axis Options. Set the x-axis to a minimum of 0 and maximum of 30,000, and the y-axis to a minimum of -5,000 and maximum of 10,000. When droplet clusters have been identified, adjust axes to reduce empty space in the graph.
NOTE: The position of mutant and wildtype clusters will depend on the probes used, the fluorophore and their concentration. - Select the sample corresponding to the positive control tumor tissue gDNA to set the negative (cluster closest to the origin), mutant (cluster closest to the x-axis), and wildtype (cluster closest to the y-axis) gates. Ensure that the clusters are distinct and easily identified in a successful assay.
- Apply the gate settings for the positive control to all samples by right-clicking on the positive control sample and clicking the option to Apply all settings to selected samples.
- Under the graphical view, click Multiple Samples tab to view plots for all selected samples. Export the image as a .TIF file.
- Under the Workspace tab at the top left of the screen, select Export Analysis (csv) and save the analyzed data file as a .csv file.
- Open the .csv file in spreadsheet software to view negative, wildtype, and mutant droplet counts for each sample. Calculate the MAF by dividing the Poisson corrected mutant droplet count by the sum of the Poisson corrected mutant plus wildtype droplet counts for each sample.
NOTE: Use the Poisson corrected count because Poisson statistics account for that fact that positive droplets may contain more than a single copy of target DNA, and thus summing the positive droplets may not yield an accurate count16.
Results
Figure 1 shows representative results for successful detection of H3F3A p.K27M mutation in preamplified plasma (top left panel) and CSF (top right panel) cfDNA from two children with DMG. cfDNA samples were analyzed in replicate but only one representative graph is shown for each sample type. The dPCR plots show successful droplet generation, with 7-9 million droplets per PCR well (most of which are negative droplets that do not contain target DNA). A minimum of 7 million droplets per PCR well indicates a successful dropletization, while fewer than 7 million indicate failure of the assay, in which case the user should not proceed with data analysis. Figure 1 shows a clear separation between mutant and wildtype clusters along the x and y-axes, respectively. Robust wildtype clusters indicate that the cfDNA extraction was successful because template DNA is present. Mutant clusters show a MAF of 1.60% and 39.92% for the plasma and CSF samples, respectively, demonstrating positive detection of the mutation. For these patients, dPCR results are in accordance with tumor mutation status, as confirmed by genomic analysis of biopsy tumor tissue8. The negative control (bottom left panel) shows 0 mutant and 0 wildtype droplets, indicating that there was no contamination of the PCR reaction mixture. The positive control tumor tissue gDNA (bottom right panel) shows the mutation being detected at the expected allelic frequency for the particular tumor sample selected.
In Figure 2, representative results are shown for unsuccessful detection of the mutation of interest, H3F3A p.K27M, in plasma cfDNA from a child with DMG. Mutation status was confirmed by genomic analysis of tumor tissue8. Representative results from two replicate PCR wells are shown (top panels). The total number of droplets, including negative droplets, is between 7-9 million per PCR well, indicating successful dropletization. The wildtype clusters, plotted along the y-axis, show approximately 7-8,000 wildtype droplets per PCR well for the plasma cfDNA, indicating successful cfDNA extraction (as there is target wildtype DNA in the sample). However, 0 mutant droplets are detected in the plasma sample. The bottom left panel shows negative control (MB H2O) with no wildtype or mutant droplets; and the bottom right panel shows the positive control preamplified tumor tissue gDNA (0.025 ng) with positive mutation detection. As shown in this figure, the absence of mutation detection in plasma may not necessarily mean the patient is wildtype for the mutation of interest, as false negatives do occur8. In some cases, when the mutation is missed in the plasma collected at upfront biopsy, it is detected in the plasma obtained from the same patient at a later time point8.
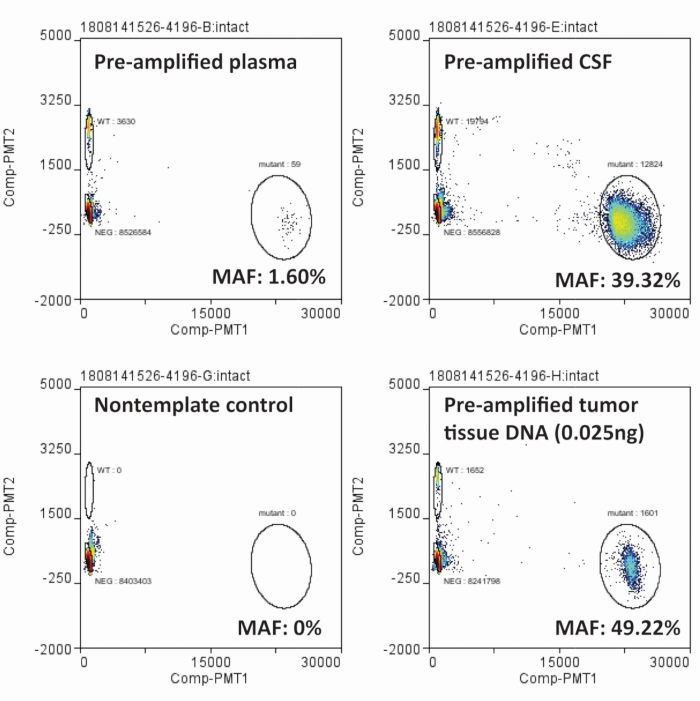
Figure 1: Successful detection of H3F3A p.K27M mutation in preamplified plasma and CSF cfDNA from children with midline gliomas. Please click here to view a larger version of this figure.
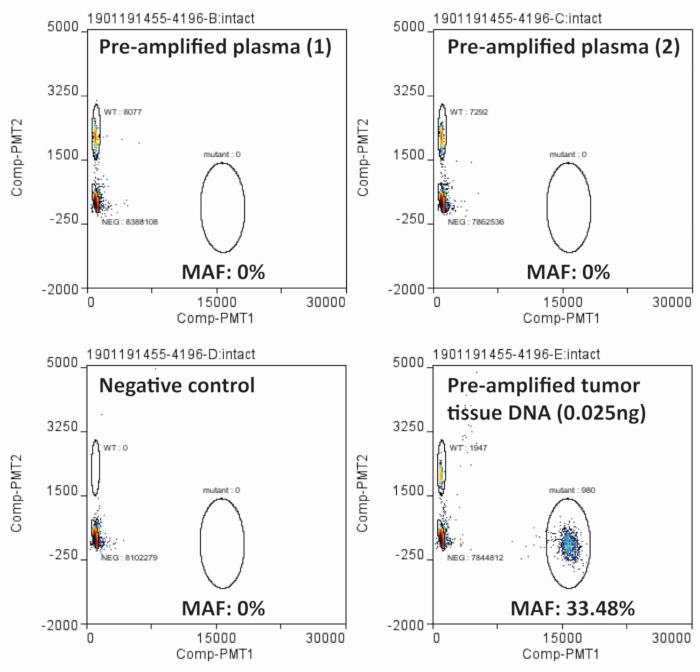
Figure 2: False negative results obtained from analysis of a preamplified plasma cfDNA sample from a patient known to harbor the mutation of interest, H3F3A p.K27M, in the tumor. Please click here to view a larger version of this figure.
Discussion
Here we have presented our method for detecting and quantifying the allelic frequency of tumor mutations in cfDNA from patient liquid biopsy. We emphasize critical steps for the success of this method, including pre-analytical sample processing, cfDNA extraction, PCR assay design, and data analysis. To limit the sample volume used, cfDNA is extracted from 1 mL of plasma but only 500 µL of CSF. When extracting from CSF, the protocol for extraction from 1 mL of urine (following the cfDNA extraction kit handbook12) is used, as per the manufacturer's recommendation. The difference in sample volume required between plasma and CSF is due to lower levels of tumor-specific cfDNA in plasma compared to CSF of patients with brain tumors, necessitating larger sample volumes for mutation detection8. If the sample is available, more than 1 mL of plasma may be extracted from to produce higher DNA yield. However, in the case of pediatric patients, it is important to minimize the amount of blood used whenever possible, as even a simple procedure such as blood draw is fatiguing to pediatric patients with cancers undergoing radiation therapies. Extracting from 1 mL aliquots of plasma also enables replicate extractions, such that the assay can be repeated (e.g., in cases of failure in DNA extraction or sample contamination).
In an effort to reduce any sample use that is not strictly necessary, cfDNA is typically not quantified. However, we have found a range of cfDNA concentrations between 0.2-2 ng/µL and 0.6-13 ng/µL in plasma and CSF, respectively. Given the low amount of cfDNA, and the fact that tumor-specific mutant alleles are present at a low frequency, a pre-amplification step using the same set of primers used for dPCR is necessary to significantly increase the amount of target DNA in the sample, aiding in mutation detection8. Diluting the pre-amplified product in DNA suspension buffer provides sufficient volume for technical replicates, which aids in distinguishing true positives. Because the number of mutant droplets can be low (for example, between 0-2 mutant droplets in a plasma sample), the inclusion of technical replicates is key for resolving mutation status. While one PCR well may yield 0 mutant droplets, the other two may yield 1-2 for a single plasma sample analyzed in triplicate; thus, the inclusion of replicates allows for greater accuracy when determining mutation status. The MAF is then calculated as the average of the replicate values.
Multiplexed pre-amplification (preamplifying wildtype and mutant alleles of two mutations of interest) increases the utility of a single sample, as the same starting material can be used to test for two mutations. Importantly, a multiplex preamplification product can be analyzed in singleplex during dPCR for greater simplicity, as described here. However, both preamplification PCR and dPCR may be multiplexed. When multiplexing, conditions must be optimized for both sets of primers and probes: primer annealing temperatures must be similar to run together in PCR amplification, and probes should be designed to generate distinct clusters (based on fluorescent signal and intensity). When validating a new set of primers and probes, run an annealing temperature gradient to determine optimum annealing temperature based on the range suggested by the manufacturer. Before testing probes on patient cfDNA specimens, validate them using synthetic DNA constructs and/or tumor tissue gDNA of different inputs (i.e., up to 10 ng).
For the detection of mutant alleles with greater specificity and reduced mismatches in the hybridization of probe to the target DNA, locked nucleic acid (LNA) probes are used. LNA is a nucleic acid analog with a methylene bridge connecting the 2'-oxygen and 4'-carbon of the ribose ring9. The methylene bridge locks the nucleic acid into a rigid bicyclic conformation that restricts flexibility, increases thermal duplex stability, and improves the specificity of probe hybridization to target DNA10,18,19. If a single base mismatch exists between LNA probe and template DNA, duplex formation between probe and target will destabilize. As such, LNA probes improve the specificity of probe binding and result in a higher signal-to-noise ratio11. Analysis of plasma and CSF from non-CNS-diseased pediatric patients has established the specificity of our assay with LNA probes targeting H3F3A p.K27M, to determine that an allelic frequency of equal to or less than 0.001% is considered a false positive8. For additional considerations for optimizing the design of probes and primers, including GC content, amplicon size, probe reporter dyes, and quenchers, refer to the dPCR manufacturer guidelines14,17. Although our method is optimized for use with the RainDance system, the protocol may be adapted for use with other dPCR platforms.
The method presented here draws strength from the high sensitivity and target enrichment achieved by dPCR, which remains the platform of choice for detecting rare tumor mutations in cfDNA. Although powerful, dPCR is limited in the number of mutations that can be tested for in a single assay. An alternative to dPCR is next generation sequencing (NGS), which may detect multiple mutations across many genes, increasing the utility of a single sample. NGS can detect mutations in CSF and plasma of patients with brainstem gliomas20, however, is currently less sensitive than dPCR at detecting tumor mutations in cfDNA, with detection limits of 0.1-10% MAF compared to 0.001% in PCR-based approaches21. dPCR also achieves faster turnaround time than NGS, enabling rapid detection of mutations of interest.The PCR approach is applicable across cancer types and can be expanded to detect hotspot mutations and methylated cfDNA22.
The liquid biopsy is indeed in its infancy and will require further development for tailoring to specific diseases. Tumor monitoring in the context of tumor evolution will be the next challenge, where a platform capable of detecting emerging mutations with high sensitivity would be required. Additionally, platforms capable of detecting a variety of biomolecules (peptides, cytokines, RNA) will be highly beneficial in assessing tumor response to treatment, as well as advancing personalized clinical interventions.
Disclosures
The method described in this manuscript is included in an International patent application "Methods for detecting cancer biomarkers" by Javad Nazarian & Eshini Panditharatna.
Acknowledgements
The authors would like to acknowledge the generosity of all patients and their families. This work was supported by funding from the Smashing Walnuts Foundation (Middleburg, VA), the V Foundation (Atlanta, GA), The Gabriella Miller Kids First Data Resource Center, Clinical and Translational Science Institute at Children's National (5UL1TR001876-03), Musella Foundation (Hewlett, NY), Matthew Larson Foundation (Franklin Lake, NJ), The Lilabean Foundation for Pediatric Brain Cancer Research (Silver Spring, MD), the Childhood Brain Tumor Foundation (Germantown, MD), the Children's Brain Tumor Tissue Consortium (Philadelphia, PA), and Rally Foundation for Childhood Cancer Research (Atlanta, GA).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 10 mM Tris-HCl, 0.1 mM EDTA DNA Suspension Buffer (pH 8.0) | Teknova | T0227 | |
| BD Vacutainer K2-EDTA 7.2 mg Blood Collection Tubes (10 mL) | Becton Dickinson Diagnostics | 367525 | For plasma collection |
| BD Vacutainer Plastic Serum tube with Red BD Hemogard Closure (10 mL) | Becton Dickinson Diagnostics | 367895 | For serum collection |
| Bleach | General Lab Supplier | ||
| Buffer ATL | Qiagen | 19076 | |
| Cell-Free DNA Blood Collection Tubes | Streck | 218961 | cfDNA blood collection tubes (optional) |
| CentriVap Concentrator | Labconco | 7810010 | |
| Forward Primer | Integrated DNA Technologies, Inc. | Custom design | |
| MiniAmp Thermal Cycler | Thermofisher Scientific | A37834 | |
| Molecular Biology Grade Absolute Ethanol (200 proof) | General Lab Supplier | ||
| Mutant Probe | Integrated DNA Technologies, Inc. | Custom design | |
| PAXgene Blood ccfDNA tubes | PreAnalytiX | 768115 | cfDNA blood collection tubes (optional) |
| PCR 8 well strip tube caps | VWR | 10011-786 | |
| PCR 8 well strip tubes | Axygen | PCR-0208-C | |
| Pipette (p20, p200, p1000) | General Lab Supplier | ||
| Pipette filter tips (p20, p200, p1000) | General Lab Supplier | ||
| Q5 Hot Start High-Fidelity 2x Master Mix | New England Biolabs Inc | M0494S | |
| QIAamp Circulating Nucleic Acid HandBook | Qiagen | cfDNA extraction kit handbook (2013 edition) | |
| QIAamp Circulating Nucleic Acid Kit | Qiagen | 55114 | cfDNA extraction kit (Protocol Step 4) |
| QIAamp MinElute Virus Spin Kit | Qiagen | 57704 | Optional kit for DNA extraction from small (< or =200 µL) sample volumes |
| Qiavac 24 Plus | Qiagen | 19413 | For use with QIAamp Circulating Nucleic Acids kit |
| Raindance Consumable Kit | Bio-Rad | 20-04411 | Contains droplet-generating instrument chips, quantification instrument chips, PCR strip caps including high-speed caps, and droplet stabilizing oil |
| Raindance Sense Instrument | Bio-Rad | Quantification instrument (used in Protocol Step 9) | |
| Raindance Source Instrument | Bio-Rad | Droplet-generating instrument (used in Protocol Step 9) | |
| RainDrop Analyst II Software | RainDance Technologies | Analyst software used for Data Analysis (Protocol Step 10) | |
| Refrigerated Vapor Trap | Savant | RVT5105-115 | |
| Reverse Primer | Integrated DNA Technologies, Inc. | Custom design | |
| Smartblock 2 mL | Eppendorf | 05 412 506 | |
| TaqMan Genotyping Master Mix | Thermofisher Scientific | 4371353 | |
| Thermomixer C | Eppendorf | 14 285 562PM | |
| WT Probe | Integrated DNA Technologies, Inc. | Custom design |
References
- Mackay, A., et al. Integrated molecular meta-analysis of 1,000 pediatric high-grade and diffuse intrinsic pontine glioma. Cancer Cell. 32, 520-537 (2017).
- Hoffman, L. M., et al. Spatial genomic heterogeneity in diffuse intrinsic pontine and midline high-grade glioma: implications for diagnostic biopsy and targeted therapeutics. Acta Neuropathologica Communications. 4 (1), (2016).
- Puget, S., et al. Biopsy in a series of 130 pediatric diffuse intrinsic pontine gliomas. Child's Nervous System. 31 (10), 1773-1780 (2015).
- Leary, S., et al. Year one in the molecular era of pediatric brain tumor diagnosis: application of universal clinical targeted sequencing in an unselected cohort of children. Neuro-Oncology. 19 (4), iv21(2017).
- Mueller, S., et al. DIPG-40. PNOC003: Precision medicine trial for children with diffuse intrinsic pontine glioma. Neuro-Oncology. 19 (4), iv14(2017).
- Kilburn, L., et al. DIPG-76. PNOC-003: Precision medicine trial for children with diffuse intrinsic pontine glioma: preliminary experience with multi-agent personalized therapy recommendations. Neuro-Oncology. 20 (2), i64(2018).
- Aquino, D., Gioppo, A., Finocchiaro, G., Bruzzone, M. G., Cuccarini, V. MRI in glioma immunotherapy: evidence, pitfalls, and perspectives. Journal of Immunology Research. 2017, 5813951(2017).
- Panditharatna, E., et al. Clinically relevant and minimally invasive tumor surveillance of pediatric diffuse midline gliomas using patient-derived liquid biopsy. Clinical Cancer Research. , (2018).
- Singh, S. K., Koshkin, A. A., Wengel, J., Nielsen, P. LNA (locked nucleic acids): synthesis and high-affinity nucleic acid recognition. Chemical Communications. 29 (4), 455-456 (1998).
- Owczarzy, R., You, Y., Groth, C. L., Tataurov, A. V. Stability and mismatch discrimination of locked nucleic acid-DNA duplexes. Biochemistry. 50 (43), 9352-9367 (2011).
- Priya, N. G., Pandey, N., Rajagopal, R. LNA probes substantially improve the detection of bacterial endosymbionts in whole mount of insects by fluorescent in-situ hybridization. BMC Microbiology. 12, 81(2012).
- Qiagen. QIAamp Circulating Nucleic Acid Handbook. , 1090257(2013).
- Jackson, J. B., et al. Multiplex preamplification of serum DNA to facilitate reliable detection of extremely rare cancer mutations in circulating DNA by digital PCR. The Journal of Molecular Diagnostics. 18 (2), 235-243 (2016).
- Rain Dance Technologies. RainDrop Assay Guidelines. , LCN 50-04334 Rev. D (2016).
- Rain Dance Technologies. RainDrop Analyst II Operator's Manual. , LCN 50-08157, Rev. A (2015).
- Majumdar, N., Banerjee, S., Pallas, M., Wessel, T., Hegerich, P. Poisson Plus quantification for digital PCR system. Scientific Reports. 7, 9617(2017).
- Biorad. Droplet Digital PCR Applications Guide. , Life Science Group. Bulletin 6407 Rev. A. 13-0579 0214 Sig 1213 (2018).
- Mouritzen, P., Nielsen, A. T., Pfundheller, H. M., Choleva, Y., Kongsbak, L., Moller, S. Single nucleotide polymorphism genotyping using locked nucleic acid (LNA). Expert Review of Molecular Diagnostics. 3 (1), 27-38 (2013).
- Ugozzoli, L. A., Latorra, D., Puckett, R., Arar, K., Hamby, K. Real-time genotyping with oligonucleotide probes containing locked nucleic acids. Analytical Biochemistry. 324 (1), 143-152 (2004).
- Pan, C., et al. Molecular profiling of tumors of the brainstem by sequencing of CSF-derived circulating tumor DNA. Acta Neuropathologica. , (2018).
- Stewart, C. M., Tsui, D. W. Y. Circulating cell-free DNA for non-invasive cancer management. Cancer Genetics. , (2018).
- Barault, L., et al. Discovery of methylated circulating DNA biomarkers for comprehensive non-invasive monitoring of treatment response in metastatic colorectal cancer. Gut. 67 (11), 1995-2005 (2018).
Reprints and Permissions
