The protocol describes how to measure knee hyperalgesia in mice. We show examples in mouse models of acute knee pain as well as in models of osteoarthritis (OA).
Method Article
Assessment of Knee Hyperalgesia in Mice using Pressure Application Measurement
In This Article
Summary
Abstract
Assessment of knee hyperalgesia provides a robust assay for measuring peripheral sensitization in the knee, and represents a clinically relevant pain-dependent behavior that can be used in rodent models of arthritis. Several methods have been reported to determine the threshold for responses to knee compression in rodents. Here, we aimed to adapt existing methods to develop a standardized method for assessing knee hyperalgesia in adult mice, using a Pressure Application Measurement (PAM) device. The protocol includes detailed steps, training recommendations for new experimenters, and tips for achieving consistent results. We provide suggestions for optimal training of a new experimenter. Finally, representative outcomes are provided for both acute models of transient hyperalgesia and experimental osteoarthritis (OA) models, which are characterized by chronic pain. This method is highly sensitive to pharmacological interventions, making it suitable for evaluating the effects of mediators like cytokines and for medium-throughput drug screening assays. In summary, the described approach provides a robust and clinically relevant method for quantifying knee hyperalgesia.
Introduction
Osteoarthritis (OA), the most common form of arthritis, is characterized by progressive cartilage degradation, synovitis, bone remodeling, and osteophyte growth1, and presents clinically as pain and loss of joint function. OA is one of the major sources of chronic pain in the world, profoundly impacting patients' lives due to reduced mobility and associated health issues such as anxiety and depression2,3. Commonly prescribed drugs for OA pain include nonsteroidal anti-inflammatory drugs (NSAIDs), visco-supplementation, corticosteroids, and opioids, but their efficacy is limited, and their prolonged use is associated with serious adverse effects or risk of addiction1,4.
In recent years, large cohort studies have attempted to carefully describe the pain experienced during progressive OA5. As part of this effort, several studies have performed quantitative sensory testing (QST) in subjects with OA, with the overall goal of identifying sensitization and determining associations between QST measures and OA symptoms and severity, as well as response to treatment (reviewed in6). The International Association for the Study of Pain defines sensitization as an increased responsiveness of nociceptive neurons to their normal input, and/or recruitment of a response to normally subthreshold inputs7. It is becoming increasingly clear that sensitization is a key process underlying chronic pain in OA. One particular QST finding that robustly distinguishes subjects with symptomatic OA from controls is a reduction in pain pressure threshold (PPT). A meta-analysis of PPT values (both at the knee and sites distant from the knee) of 1,003 participants with and without knee OA reported a significant standard mean difference (SMD, difference in means divided by standard deviation) in PPT between persons with OA and controls8.
The observation that OA patients display sensitization to mechanical stimuli, which is manifested as lowered pain pressure thresholds when a force is applied to the joint, suggests underlying mechanisms of peripheral and central sensitization that result from changes in the pain pathway6. The molecular and cellular underpinnings of these changes can be studied in rodent models of OA. In recent years, sophisticated mouse models have been developed to model the slowly progressive nature of knee OA, and this approach has revealed that distinct pain mechanisms operate in a time-dependent manner, which may have important translational significance9. For example, in the course of surgically induced experimental knee OA, mice develop mechanical allodynia in the operated hind paw early on in the course of the disease, while weight-bearing deficits only become apparent in late-stage disease9.
As in patients with OA, mice with experimental OA develop a lowered pain threshold for pain applied to the knee early on in the course of experimental knee OA10. This is indicative of sensitization of knee-innervating nociceptors, which can indeed be visualized and quantified by in vivo calcium imaging of the lumbar dorsal root ganglia11. Assessment of knee hyperalgesia provides a robust and relatively straightforward assay for measuring peripheral sensitization, thus representing a clinically relevant pain-dependent behavior that can be used in rodent models of arthritis. Several methods have been reported to determine the threshold for responses to knee compression in rodents. Older studies report squeezing the knee between the thumb and the forefinger, and recording a subjective withdrawal response or a vocalization response in the animal12,13,14 In 2007, Barton et al. reported pressure application measurement (PAM) as a novel behavioral technique to record mechanical hypersensitivity at the rat knee in inflammatory arthritis15. The method was subsequently validated in mice with antigen-induced arthritis of the knee 16. PAM is a technique that uses a force transducer to put an increasing force on the affected knee while providing visual feedback, thus enabling compression of the knee in a reproducible manner, which increases its sensitivity and reproducibility. These two previously published studies focused on models of inflammatory arthritis, where knee swelling is prominent. Therefore, we aimed to adapt these methods15,16 to develop a standardized method for assessing knee hyperalgesia in mice, which can be readily applied to models of OA and is highly responsive to pharmacological intervention, as described here.
Protocol
All experimental protocols were approved under the category E by the Rush University Institutional Animal Care and Use Committee. The protocol described is to assess knee hyperalgesia in the right knee in response to a mechanical stimulus in adult C57BL/6 mice (10 weeks- 2 years of age) of either sex. To measure knee hyperalgesia in the left knee, switch hands.
1. Setting up the Pressure Application Measurement (PAM) device
- Connect one cable from the PAM device to the computer and the second cable from the PAM device to the force transducer.
- Turn on the computer and start the PAM software. Set the maximum pressure to 450 g.
NOTE: The software and small transducer can measure up to 500 g. Therefore, the experimenter can choose a plateau anywhere between 450 g and 500 g, but the maximum cutoff should not change within an experiment. - Leave the mice in the testing room for 15-30 min until they are acclimatized and have settled down. Ensure that the testing room is a separate room from where the mice are housed and that the room is quiet. Use the same testing room throughout the study.
- Perform pre-acclimatization, if needed, to calm mice down before the study is started - in this case, restrain the animals by holding the mouse in the left hand, by restraining the back and firmly holding the tail down with the 4th and 5th fingers (as they would be for the test), 2 days before the first testing day in order to acclimatize the mice to the assay. Within a given experiment, acclimatize all mice the same way.
- After the acclimatization, ensure the mouse is calm and does not wriggle when restrained. If the mouse is not calm, return it to its cage and postpone testing for a few days.
2. Training for measurement of knee hyperalgesia
- Start with naïve animals and learn how to recognize responses when the animals are calm. This will inform the experimenter to recognize what a normal response is for that assay.
- Use an experimental model where knee hyperalgesia has been characterized by an experienced tester to know what to expect. Recognize that in experimental OA, the responses may be less obvious than in acute models or inflammatory models.
- Use lidocaine or an opiate in order to reverse the pain behavior - this will help to assess how to tell the difference between a stress response versus a real pain-related response.
- Perform all testing in a manner blinded to group allocation. Perform an OA model experiment with known analgesics in a vehicle-controlled experiment. Confirm that the tester can distinguish these groups and get reproducible measurements.
- Expect that completing the training may take several weeks.
3. Baseline measurement of knee hyperalgesia using PAM
NOTE: Many experimental models of inflammatory arthritis or osteoarthritis are unilateral (for example, surgically induced knee OA). To assess knee hyperalgesia in these models, we always measure knee withdrawal threshold first in the contralateral knee of all the mice to be tested. After that, we test the ipsilateral knee. As an example, this protocol can be applied to measure knee hyperalgesia in experimental OA induced by DMM. In this model, joint damage is accompanied by knee hyperalgesia, developing by week 2 after surgery, and maintained up to week 1617.
- Cradle the mouse in the left hand, restraining the back and firmly holding the tail down with the 4th and 5th fingers.
- Loop the index finger of the other hand (right hand) through the tie of the transducer (Figure 1A). Then, place the index finger with the transducer into a transparent plastic bag (e.g., a sandwich bag). This will prevent the transducer from getting soiled, for example, by mouse urine.
NOTE: The transducer is fragile and easily breaks if it is not protected from liquids or when too high a force is applied. - Using the right thumb and middle finger, take hold of the right leg and use the middle finger to gently pin the paw down onto the thenar of the left hand (Figure 1B). The correct position of the knee at the start of testing is around 90° flexion.
- With the knee in 90° flexion, the right thumb touches the lateral side of the knee. With the index finger touching the medial side of the transducer, slowly apply pressure against the knee. As directed by the computer software (blue line on the graph), apply increasing force at a constant rate (30 g/s), up to 450 g or until the mouse shows pain-related behaviors such as vocalization, muscle twitching, body wriggling, or whisker movement.
- Once the mouse shows pain-related behavior, retract the finger with the transducer from the knee and record the pressure displayed on the screen (Figure 1C). If the mouse does not display pain-related behavior when 450 g is reached, still let go of the transducer and assign a value of 450 g as the withdrawal threshold for that test.
NOTE: Each individual mouse expresses a pain response in its own way. Therefore, the tester has to determine which pain-related behaviors individual mice express. However, some mice do not express pain-related behaviors at all, and in this case, the tester can either re-test the contralateral knee to determine that mouse's individual pain response a couple of days later or continue to measure the ipsilateral side and determine the behavior pattern. The latter option requires many hours of experience, so the first option is recommended for a beginner. - Return the mouse to the cage and proceed to test the next mouse. When one knee has been tested in all the mice, go back to the first mouse and repeat the testing. Test each knee 2x and take an average of the two test results as the final result. This number is termed the withdrawal threshold.
- If there is a difference of ≥ 60 g between the 1st and 2nd measurements, take a 3rd measurement and use the average of the three measurements as the final result. Try not to stress out the mice and avoid multiple consecutive measurements in the same mouse. This is why there has to be some time between each consecutive measurement.
- Test knee hyperalgesia under blind conditions in order to avoid bias. Use individual ear tags to facilitate blinding. Determining whether the mouse's behavior is indicative of pain requires practice, experience, and confidence because the tester has to use their judgment. This is why blinding to experimental groups is important.
4. Measuring knee hyperalgesia in a model of acute knee pain
- After baseline measurement of knee hyperalgesia, shave the fur around the knee.
- Anesthetize the animal with isoflurane and check proper anesthesia using the toe pinch reflex. Use vet ointment on the eyes to prevent dryness while under anesthesia. Inject 5 µL of Pam3CSK4 (1 µg or 3 µg dissolved in sterile water) or vehicle control (5 µL) through the patellar tendon into the intra-articular space of the right or left knee, using a Hamilton syringe with a 30G needle.
- Assess knee hyperalgesia 1 h, 2 h, 4 h, 6 h, and 24 h after the injection under blinded conditions.
- To assess the effect of lidocaine, inject either lidocaine (20 mg/kg in saline) or saline intraarticularly 4 h after injection of Pam3CSK4. Then, assess knee hyperalgesia after 0.5 h, 2 h, and 20 h.
5. Longitudinal assessment of knee hyperalgesia in a protracted model of OA
- Assess baseline knee hyperalgesia in male 12-week-old C57BL/6 mice.
- Perform destabilization of the medial meniscus (DMM) or sham surgery in one knee, as described in18.
- Assess knee hyperalgesia at 2 weeks, 4 weeks, 8 weeks, 12 weeks, and 16 weeks after surgery.
- To assess the effect of intra-articular lidocaine, assess knee hyperalgesia 4 weeks after DMM, and then inject lidocaine (20 mg/kg in 5 µL) or saline under isoflurane anesthesia as described in step 4.
- Assess knee hyperalgesia 20 min, 120 min, and 240 min after lidocaine injection.
Results
Time course of knee hyperalgesia in a model of acute knee pain
All results shown have been previously reported by our group, and we refer to10for a detailed description. The first example shows a model for inducing acute, transient knee hyperalgesia. In this experiment, we injected Pam3CSK4, a synthetic toll-like receptor 2 (TLR2) ligand (1 µg or 3 µg, dissolved in sterile water) at 5 µL, into the knee cavity of 10-week-old naïve male C57BL/6 mice, using a Hamilton syringe with a 30G needle under isoflurane anesthesia. This caused knee hyperalgesia in a dose-dependent fashion (Figure 2A), peaking 4 h after injection and returning to baseline by 24 h. In order to show that this behavior is mediated by intra-articular nociceptors, we performed an experiment where lidocaine (5 µL of 200 mg/mL) was injected intra-articularly at the peak of Pam3CSK4-induced knee hyperalgesia. This resulted in the reversal of knee hyperalgesia (Figure 2B).
Time course of knee hyperalgesia in experimental OA
In this experiment, experimental OA was induced by destabilization of the medial meniscus (DMM) in the right knee of 10-week-old male C57BL/6 mice, while a separate group of mice underwent sham surgery in the right knee10. Knee hyperalgesia was assessed before surgery (baseline) and then at week 2, 4, 8, 12, and 16 after surgery. DMM surgery caused pronounced knee hyperalgesia 2 weeks after surgery, slowly recovering through week 16 (Figure 3A). Sham-operated mice also developed pronounced knee hyperalgesia after surgery, but knee hyperalgesia recovered faster and was at any given time less pronounced than in the DMM group (Figure 3A). At 4 weeks after DMM, we injected lidocaine (5 µL for a concentration of 200 mg/mL) or vehicle intra-articularly, showing that lidocaine resulted in an immediate reversal of knee hyperalgesia (within 30 min) - with the analgesic effect apparent at 30 min but lost by 4 h after injection (Figure 3B). Again, this suggests that the behavior is mediated by intra-articular nociceptors.
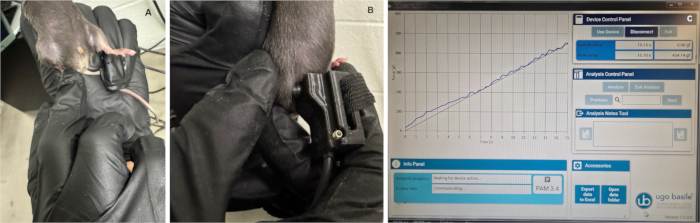
Figure 1: Correct position for holding the mouse and the transducer. (A) Correct position for holding the mouse, with theknee around 90° flexion. (B) Correct position of the transducer against the medial side of the knee. (C) The blue line on the monitor is the actual force applied, which needs to follow the black guiding line. Please click here to view a larger version of this figure.

Figure 2: Intra-articular injection of Pam3CSK4 causes knee hyperalgesia in naïve mice. (A) Intra-articular injection of vehicle or Pam3CSK4, 1 µg or 3 µg (5 µL; n = 4 mice/treatment). **** p < 0.0001; mean ± SEM. Repeated-measures 2-way ANOVA with Bonferroni's post hoc tests reveals significance between the vehicle and treatment group. (B) In a separate experiment, all mice received an intra-articular injection of Pam3CSK4 (3 µg) following the baseline assessment (time 0). At 4 h after injection, after the development of knee hyperalgesia was confirmed, mice received a second intra-articular injection of either vehicle (triangles) or lidocaine (5 µL for a concentration of 200 mg/mL; circles; n = 5 mice/treatment). The arrow indicates the time of the second injection. **** p < 0.0001; mean ± SEM. Repeated-measures 2-way ANOVA with Bonferroni's post hoc tests reveal significance between the vehicle and treatment groups. This figure has been modified from10. Please click here to view a larger version of this figure.

Figure 3: Intra-articular injection of lidocaine reversed knee hyperalgesia 4 weeks after DMM surgery. (A) Time-course of knee hyperalgesia in C57BL/6 mice following sham or DMM surgery (n = 6-8 mice/group). * p < 0.05, ** p < 0.01, *** p < 0.001, **** p < 0.0001; mean ± SEM. Repeated-measures 2-way ANOVA with Bonferroni's post hoc tests reveals significance between the vehicle and treatment groups. (B) Intra-articular injection of lidocaine (5 µL for a concentration of 200 mg/mL; n = 4 mice/treatment) 4 weeks after DMM surgery in male C57BL/6 mice. **** p < 0.0001; mean ± SEM. Repeated-measures 2-way ANOVA with Bonferroni's post hoc tests reveals significance between the vehicle and treatment groups. This figure has been modified from10. Please click here to view a larger version of this figure.
Discussion
Measurement of knee hyperalgesia in mice offers a relatively fast and straightforward means of assessing knee hyperalgesia associated with experimental arthritis. As can be observed from the representative results shown, the assay can detect acute onset and transient hyperalgesia (Figure 2A). We have reported this behavior in response to several mediators injected into the knee joint, including an aggrecan fragment10, a neurotrophin, nerve growth factor (NGF)19, and a TLR4 ligand, lipopolysaccharide (LPS)20. Importantly, the assay can be used for longitudinal monitoring of knee hyperalgesia in models of experimental OA, as shown in Figure 3A. We have also reported this in other OA models, including the partial meniscectomy model21,22 and in the closed injury anterior cruciate ligament rupture model23. In primary age-associated OA in mice, knee OA develops in both knees24. In that case, knee hyperalgesia has to be assessed in both knees, which is tricky because the contralateral knee cannot be used to determine the individual pain responses in each mouse. Therefore, the tester needs to pay extra attention to determine what is the pain-related behavior each mouse is displaying. Assessing the mice multiple times on different days can be considered in order to determine this.
Knee hyperalgesia is highly sensitive to pharmacological intervention, as shown in Figure 2B and Figure 3B for the response to intra-articular lidocaine. We have tested the response to experimental drugs injected into the joint, for example, C-C chemokine 2 receptor antagonist (CCR2RA)25. Knee hyperalgesia can also be reversed by systemic delivery of drugs, for example, morphine17 or CCR2RA25. Hence, we propose that the assay is convenient for medium throughput testing of novel compounds, either locally or systematically administered. Importantly, lidocaine or morphine can be used, respectively, as positive controls.
It is critical that the experimenter approaches the assay in an unbiased manner and is blinded to the experimental groups. To improve judgment, we recommend practicing using both positive and negative controls to learn how to recognize pain-related behaviors. As we show in Figure 3A, sham surgery itself can induce knee hyperalgesia, and therefore, it is also useful to include baseline measurements of all groups.
Additionally, modification of the cut-off threshold may be necessary depending on experimental conditions. For example, another group that followed this training protocol found that in their laboratory, applying forces greater than 450 g was necessary in order to generate responses in their model26. Thus, they did not use a maximum value but instead continued to apply increasing amounts of force at the rate of 30 g/s until a response was noted. In other cases, a lower maximum threshold may be necessary if naïve animals of a particular background strain or housed in certain conditions, exhibit reproducible responses prior to reaching 400 g- 450 g of force. Before changing this maximum cutoff value, another modification that can be tried is to switch to using the larger transducer provided, as this may allow for more reproducible force to be applied to the joint.
The limitation of this technique is that large numbers of mice are required to obtain reliable data, but this is inherent in animal behavior testing. Furthermore, the testing can be time-consuming, especially since, quite often, testing needs to be postponed because of restless mouse behavior. Furthermore, a dedicated, quiet, insulated room is needed for optimal results, and the experimenter has to be well-trained.
In summary, the PAM technique described is a robust, reproducible method for quantifying knee hyperalgesia in mice with acute knee pain, as well as in experimental knee OA. Knee hyperalgesia is clinically relevant, since patients with knee OA have lowered knee pain pressure thresholds. The methods can assess sensitizing effects of mediators such as cytokines and offer a medium-throughput screening assay for testing the analgesic effect of drugs. Finally, since the method can readily be applied longitudinally in long-term models of disease, it offers a tool for assessing the relationship of sensitization to pathological changes in knee joint tissues10,17.
Disclosures
AMM is a consultant for Novartis, Merck, Roivant, and Averitas. She has received research support from Orion and Eli Lilly. SI and REM have nothing to disclose.
Acknowledgements
Our research is funded by the National Institute of Arthritis and Musculoskeletal and Skin Diseases, Grant/Award Numbers: P30AR079206 (AMM), R01AR060364 (AMM), R01AR064251 (AMM), UC2AR082186 (AMM), R21AR085242-01 (AMM), and R01AR077019 (REM).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| C-C chemokine 2 receptor antagonist (CCR2RA) | Tocris | RS 504393 | |
| computer (any type) | windows 7 minimum | ||
| Lidocaine | Sigma | L5647 | |
| Pressure Application Measurement (P.A.M) | Ugo Basile | 38500 | included transducer, computer, cables |
| sandwich bag | whole food market | 6-1/2 x 5-7/8 | cover the transducer |
| toll-like receptor 2 ligand Pam3CSK4 | invitrogen | tlrl-pms |
References
- Tang, S., et al. Osteoarthritis. Nat Rev Dis Primers. 11 (1), 10(2025).
- Allen, K. D., Thoma, L. M., Golightly, Y. M. Epidemiology of osteoarthritis. Osteoarthritis Cartilage. 30 (2), 184-195 (2022).
- Schmukler, J., et al. 36-40% of Routine Care Patients With Osteoarthritis or Rheumatoid Arthritis Screen Positive for Anxiety, Depression, and/or Fibromyalgia on a Single MDHAQ. ACR Open Rheumatol. 6 (10), 641-647 (2024).
- Smith, S. R., Deshpande, B. R., Collins, J. E., Katz, J. N., Losina, E. Comparative pain reduction of oral non-steroidal anti-inflammatory drugs and opioids for knee osteoarthritis: systematic analytic review. Osteoarthritis Cartilage. 24 (6), 962-972 (2016).
- Neogi, T. The epidemiology and impact of pain in osteoarthritis. Osteoarthritis Cartilage. 21 (9), 1145-1153 (2013).
- Arant, K. R., Katz, J. N., Neogi, T. Quantitative sensory testing: identifying pain characteristics in patients with osteoarthritis. Osteoarthritis Cartilage. 30 (1), 17-31 (2022).
- Loeser, J. D., Treede, R. D. The Kyoto protocol of IASP Basic Pain Terminology. Pain. 137 (3), 473-477 (2008).
- Fingleton, C., et al. Pain sensitization in people with knee osteoarthritis: a systematic review and meta-analysis. Osteoarthritis Cartilage. 23 (7), 1043-1056 (2015).
- Miller, R. E., Malfait, A. M. Osteoarthritis pain: What are we learning from animal models. Best Pract Res Clin Rheumatol. 31 (5), 676-687 (2017).
- Miller, R. E., et al. An aggrecan fragment drives osteoarthritis pain through Toll-like receptor 2. JCI Insight. 3 (6), e95704(2018).
- Miller, R. E., et al. Visualization of Peripheral Neuron Sensitization in a Surgical Mouse Model of Osteoarthritis by In Vivo Calcium Imaging. Arthritis Rheumatol. 70 (1), 88-97 (2018).
- Gauldie, S. D., et al. A robust model of adjuvant-induced chronic unilateral arthritis in two mouse strains. J Neurosci Methods. 139 (2), 281-291 (2004).
- Knights, C. B., Gentry, C., Bevan, S. Partial medial meniscectomy produces osteoarthritis pain-related behaviour in female C57BL/6 mice. Pain. 153 (2), 281-292 (2012).
- Yu, Y. C., et al. Two variables that can be used as pain indices in experimental animal models of arthritis. J Neurosci Methods. 115 (1), 107-113 (2002).
- Barton, N. J., et al. Pressure application measurement (PAM): a novel behavioural technique for measuring hypersensitivity in a rat model of joint pain. J Neurosci Methods. 163 (1), 67-75 (2007).
- Leuchtweis, J., et al. Validation of the digital pressure application measurement (PAM) device for detection of primary mechanical hyperalgesia in rat and mouse antigen-induced knee joint arthritis. Methods Find Exp Clin Pharmacol. 32 (8), 575-583 (2010).
- Miller, R. E., et al. Chemogenetic Inhibition of Pain Neurons in a Mouse Model of Osteoarthritis. Arthritis Rheumatol. 69 (7), 1429-1439 (2017).
- Glasson, S. S., Blanchet, T. J., Morris, E. A. The surgical destabilization of the medial meniscus (DMM) model of osteoarthritis in the 129/SvEv mouse. Osteoarthritis Cartilage. 15 (9), 1061-1069 (2007).
- Obeidat, A. M., et al. Piezo2 expressing nociceptors mediate mechanical sensitization in experimental osteoarthritis. Nat Commun. 14 (1), 2479(2023).
- Wang, L., et al. Notch signaling is activated in knee-innervating dorsal root ganglia in experimental models of osteoarthritis joint pain. Arthritis Res Ther. 25 (1), 63(2023).
- Obeidat, A. M., et al. Intra-articular sprouting of nociceptors accompanies progressive osteoarthritis: comparative evidence in four murine models. Front Neuroanat. 18, 1429124(2024).
- Geraghty, T., et al. Acute systemic macrophage depletion in osteoarthritic mice alleviates pain-related behaviors and does not affect joint damage. Arthritis Res Ther. 26 (1), 224(2024).
- Bergman, R. F., et al. Sexual dimorphism of the synovial transcriptome underpins greater PTOA disease severity in male mice following joint injury. Osteoarthritis Cartilage. 32 (9), 1060-1073 (2024).
- Geraghty, T., et al. Age-Associated Changes in Knee Osteoarthritis, Pain-Related Behaviors, and Dorsal Root Ganglia Immunophenotyping of Male and Female Mice. Arthritis Rheumatol. 75 (10), 1770-1780 (2023).
- Ishihara, S., et al. The role of intra-articular neuronal CCR2 receptors in knee joint pain associated with experimental osteoarthritis in mice. Arthritis Res Ther. 23 (1), 103(2021).
- Liu, H., et al. Sirt5 regulates chondrocyte metabolism and osteoarthritis development through protein lysine malonylation. bioRxiv. , (2024).
Reprints and Permissions
