This study evaluates the clinical and technical outcomes of synthetic ligament-based revision anterior cruciate ligament (ACL) reconstruction for postoperative re-rupture.
Research Article
Retrospective Evaluation of Synthetic Ligament-Based Revision of Anterior Cruciate Ligament Reconstruction for Postoperative Re-Rupture
In This Article
Summary
Abstract
Re-rupture following anterior cruciate ligament (ACL) reconstruction remains a challenging complication, necessitating effective revision strategies. To evaluate the clinical and technical outcomes of synthetic ligament-based revision ACL reconstruction for postoperative re-rupture, a retrospective analysis was conducted on patients undergoing synthetic ligament revision ACL reconstruction between January 2023 and January 2024. Preoperative assessments included laboratory tests (ESR, CRP, tuberculosis antibodies), radiographic imaging (X-ray, CT, MRI), and functional scoring (VAS, IKDC, Lysholm). Surgical protocols emphasized meticulous tunnel planning, arthroscopic debridement, synthetic ligament placement, and dual fixation with metallic interference screws. Postoperative care involved early mobilization, systematic rehabilitation, and regular follow-ups. Results showed that the procedure demonstrated technical feasibility, with successful ligament fixation and no intraoperative complications. Postoperative evaluations revealed improved functional scores (IKDC, Lysholm) and reduced pain (VAS). Imaging confirmed proper ligament positioning and graft integrity. No instances of infection, graft failure, or significant joint instability were reported during follow-up. Those results indicate that synthetic ligament revision ACL reconstruction offers a reliable solution for re-rupture cases, combining precise surgical techniques with rigorous postoperative rehabilitation. This approach addresses anatomical challenges, restores knee stability, and enhances patient outcomes, supporting its adoption in complex revision scenarios.
Introduction
Anterior cruciate ligament (ACL) injuries are among the most prevalent musculoskeletal disorders, particularly affecting active individuals and athletes, often leading to knee instability and functional impairment1,2. Primary ACL reconstruction, utilizing autografts or allografts, remains the gold standard for restoring knee stability and enabling return to activity. Postoperative re-rupture occurs in approximately 3%-15% of cases, necessitating revision surgery3,4. While multiple revisions yield inferior results compared to primary reconstructions, they can still provide functional stability5.
Ideal candidates for revision ACL reconstruction include patients with ACL re-rupture after primary reconstruction6, particularly those with limited autograft/allograft options such as prior hamstring harvest or allograft rejection, while exclusions comprise severe osteoarthritis (Kellgren-Lawrence grade ≥3)7, active knee infection, or multi-ligamentous instability requiring concurrent procedures. Primary indications are re-ruptures with moderate tunnel widening (<12 mm diameter) and patients needing immediate mechanical stability, with secondary considerations including prior graft failure due to biological incorporation issues or contraindications to biological grafts. Procedural limitations include severe osteolysis (>12 mm tunnel diameter)8, which may require adjunctive bone grafting and delay rehabilitation, and the need for advanced arthroscopic skills to ensure precise tunnel planning and avoid graft impingement.
Revision ACL reconstruction presents unique challenges, including compromised bone tunnel integrity, altered anatomy from prior procedures, and potential graft failure mechanisms, which demand innovative surgical strategies to optimize outcomes9,10. Traditional revision approaches often rely on autografts or allografts, yet these materials may be limited by donor site morbidity, graft availability, or biological incorporation issues11. Synthetic ligaments, composed of biocompatible polymers, have re-emerged as a viable alternative, offering advantages such as immediate mechanical strength, avoidance of harvest-related complications, and precise intraoperative customization12,13,14. Despite these benefits, concerns regarding long-term durability, synovitis, and foreign body reactions persist, with limited evidence supporting their efficacy in revision scenarios. This study evaluates the clinical and technical outcomes of synthetic ligament-based revision ACL reconstruction, addressing a critical gap in the literature by analyzing its feasibility in overcoming anatomical complexities and restoring knee function. Through a retrospective analysis of surgical techniques, postoperative rehabilitation, and objective outcome measures, this work aims to establish a protocol-driven framework for managing re-rupture cases, ultimately contributing to improved patient care in complex revision settings.
Protocol
All procedures in this study were approved by the Ethics Committee of the Sixth Affiliated Hospital of Xinjiang Medical University. All patients provided consent for the publication of their clinical data under the condition that their identities remain undisclosed. From January 2023 to January 2025, a retrospective analysis was conducted on the clinical and imaging data of patients undergoing revision surgery for re-rupture after ACL reconstruction using synthetic ligaments. Diagnosis of re-rupture was confirmed through imaging studies, specialized physical examinations, and arthroscopy. The consumables and equipment used are listed in the Table of Materials.
1. Preoperative preparation
To optimize surgical outcomes, preoperative preparation included comprehensive patient evaluation, advanced imaging, and meticulous planning to address the unique challenges of revision ACL reconstruction.
- Routine laboratory tests
Preoperative laboratory evaluations were performed to ensure patient readiness and identify potential risks. A complete blood count (CBC) was obtained to assess hemoglobin levels, white blood cell count, and platelet counts; results were interpreted relative to institutional normal ranges (e.g., hemoglobin ≥12 g/dL for non-pregnant adults) to screen for anemia or infection. Basic metabolic panel (BMP) testing evaluated electrolyte balance (sodium, potassium, chloride), renal function (blood urea nitrogen, creatinine), and glucose levels, with abnormalities (e.g., potassium <3.5 mmol/L) prompting consultation with internal medicine to guide correction before surgery. Coagulation studies (prothrombin time [PT], international normalized ratio [INR], activated partial thromboplastin time [aPTT]) were reviewed to detect coagulopathies; an INR >1.5, hemoglobin <10 g/dL, or platelet count <100,000/µL necessitated delaying surgery until values normalized or corrective measures were administered. Liver function tests (alanine transaminase, aspartate transaminase, total bilirubin) were analyzed to assess hepatic synthetic capacity, with elevations (e.g., bilirubin >1.2 mg/dL) triggering further evaluation for liver disease. All laboratory results were documented in the electronic health record (EHR) and discussed in preoperative conferences to determine eligibility for surgery. - Imaging studies
Graft integrity was evaluated by magnetic resonance imaging (MRI), meniscal pathology, and chondral damage. Sagittal T2-weighted sequences were used to identify residual ligament fibers and synovitis. Computed tomography (CT) with 3D reconstruction was used to quantify tunnel widening (>12 mm diameter indicating staged bone grafting and determine new tunnel trajectories to avoid convergence with prior tunnels (minimum 2 mm bone bridge). Long-leg weight-bearing radiographs were used to assess mechanical axis deviations (>3° varus/valgus), which, if present, mandate concurrent osteotomy planning. - Clinical assessments
Kellgren-Lawrence grading was applied to exclude advanced osteoarthritis (grade ≥3)15; The International Knee Documentation Committee (IKDC) and Lysholm scores were used to establish baseline function.
2. Surgical procedure for revision ACL reconstruction using synthetic ligament
Single-step procedure was chosen if adequate bone stock (tunnel diameter ≤12 mm) was available and no tunnel overlap or active infection existed. A two-step procedure was applied if there was severe tunnel widening (>12 mm) or osteolysis, convergent tunnels, infection, or previous septic failure.
- Anesthesia and positioning
General anesthesia was administered via endotracheal intubation, with neuromuscular blockade to facilitate tourniquet application (50 kPa). The patient was placed in supine position with a lateral post and foot roll to maintain 90° knee flexion during arthroscopy. - Surgical site preparation
Aseptic skin was prepared using chlorhexidine-alcohol solution, with sterile draping isolating the limb. - Incision and portal placement
Standard anterolateral and anteromedial arthroscopic portals were established with a 4 cm longitudinal incision over the tibial tubercle for graft passage. Outside-in drilling was facilitated by a lateral femoral incision. - Bone tunnel planning
Preoperative CT/MRI data-guided tunnel placement was applied to avoid prior tunnels. The tibial guide was positioned at the ACL footprint midpoint, and femoral drilling targeted the anatomic center. - Operative steps
- Arthroscopic joint preparation
Arthroscopic exploration and debridement were performed to prepare the joint for ligament reconstruction. Hyperplastic, hypertrophic, or villous synovium was debrided using a shaver to remove abnormal tissue and improve visualization. Meniscal tears or degeneration were addressed based on their type, location, and severity-partial tears were trimmed, while full-thickness tears required repair or resection depending on stability. Ligament continuity, tension, and morphology were assessed by probing the native ACL remnant; residual ruptured ligament tissue was debrided to eliminate mechanical interference. The intercondylar notch was evaluated for osteophytes or bony impingement, and a notchplasty was performed with a burr if necessary to create adequate space for graft passage. Articular cartilage was inspected for wear, delamination, or softening, with noted defects documented for postoperative management. Finally, the patellofemoral joint was examined for alignment abnormalities, cartilage wear, or subluxation to ensure proper tracking and minimize postoperative stress. - Bone tunnel creation
Bone tunnel creation involved precise arthroscopic guidance to establish femoral and tibial tunnels. For the tibial tunnel, the tibial guide was positioned under arthroscopic visualization at the midpoint between the medial meniscus and the intercondylar eminence. A guide pin was drilled through the guide, followed by reaming with a 7.5 mm reamer to create the tibial tunnel. On the femoral side, the tunnel was created anatomically within the native ACL footprint using an outside-in technique to enhance positional accuracy. Key anatomical landmarks, including the resident's ridge and lateral intercondylar ridge, were identified under arthroscopic guidance. A 2.4 mm guide pin was then drilled through a high anteromedial portal at an angle of 110°-120°, targeting the center of the ACL footprint (~8-10 mm anterior to the posterior cartilage margin). A tunnel measuring 7.5-8.5 mm in diameter was reamed to a depth of 25-30 mm, with care taken to preserve 1-2 mm of posterior wall integrity to avoid iatrogenic injury. - Graft placement
Ligament placement was performed by passing the synthetic ligament through the prepared tunnels under continuous arthroscopic visualization. The graft was advanced through the tibial tunnel, across the joint, and into the femoral tunnel until the entire length was seated within the femoral tunnel, with free strands remaining visible in the joint cavity to confirm proper positioning. Rotational tension was applied to the graft to align it with the native ACL anatomy and prevent kinking. - Graft fixation
Ligament fixation was achieved using metal interference screws on both the femoral and tibial sides. On the femoral side, the graft was fixed with a 9 mm metal interference screw at 30° of knee flexion under controlled tension to avoid over-constraint. Excess graft material beyond the screw was trimmed to prevent impingement. Similarly, on the tibial side, the graft was fixed with a 9 mm metal interference screw at 30° of knee flexion, with tension adjusted to match the femoral fixation and restore native ACL kinematics. - Final intraoperative assessment
Final assessment of the reconstruction involved verifying graft stability and absence of impingement using arthroscopic probing. Graft tension was tested dynamically throughout the knee range of motion (0° to 120°) to ensure no excessive laxity or tightness. Any adjustments, such as repositioning the graft or tightening screws, were made at this stage to optimize outcomes. - Surgical closure and postoperative immobilization
Closure was completed by inserting a small drainage tube into the joint cavity to reduce fluid accumulation and minimize the risk of postoperative hemarthrosis or infection. Incisions were closed meticulously using No. 1 absorbable sutures to promote optimal healing and reduce scarring, with subcuticular sutures used for cosmesis. A sterile dressing was applied, and the leg was immobilized in a hinged knee brace set to 0°-90° of flexion to protect the reconstruction during the initial recovery phase.
- Arthroscopic joint preparation
3. Postoperative care
- Drain Management
The drainage tube was removed when the output was <50 mL/day, typically within 24 h. - Antibiotic prophylaxis
Antibiotic prophylaxis was administered to reduce surgical site infection (SSI) risk, aligned with institutional guidelines and the Surgical Care Improvement Project (SCIP) protocols. Cefazolin (2 g intravenous [IV]) was selected as the first-line agent for clean-contaminated procedures; for patients with penicillin allergy, clindamycin (600 mg IV) or vancomycin (1 g IV) was substituted based on allergy severity and local resistance patterns. Dosing adjustments were made for patients with renal impairment (cefazolin reduced to 1 g IV if creatinine clearance <30 mL/min), or morbid obesity (vancomycin loading dose of 15 mg/kg followed by 10-15 mg/kg every 12 h). Antibiotics were administered within 60 min of surgical incision by the anesthesia care team, with verification via a preoperative checklist to confirm patient identity, drug name, dose, route, and timing. For prolonged surgeries (>4 h), a repeat dose of cefazolin (1 g IV) was given intraoperatively to maintain therapeutic levels. Postoperative antibiotic continuation was avoided unless clinically indicated (e.g., evidence of active infection), adhering to SCIP guidelines to minimize resistance. All antibiotic selections, dosages, and administration times were recorded in the EHR and cross-checked with the surgical and pharmacy teams to ensure compliance. - Early mobilization
Ambulation was encouraged within 24 h to reduce lower extremity venous thrombosis risk. - Rehabilitation
A structured rehabilitation program was implemented and supervised by a physiotherapist. - Follow-Up
Regular evaluations were scheduled to monitor recovery, including functional assessments, imaging, and laboratory tests.
4. Statistical analysis
All statistical analyses were performed using SPSS (Version 27.0), with continuous variables (e.g., VAS, IKDC, Lysholm scores) expressed as mean ± standard deviation (SD) and categorical variables (e.g., graft integrity) as frequencies and percentages. Normality was assessed via Shapiro-Wilk test, and within-group comparisons of preoperative versus postoperative outcomes used paired-sample t-tests (p < 0.05).
Results
A total of 28 patients (mean age: 32.4 years ± 6.8 years; 18 males, 10 females) underwent synthetic ligament revision ACL reconstruction during the study period, with a mean follow-up duration of 12.3 months ± 2.1 months (range: 6-18 months). Preoperative functional assessments revealed significant knee impairment, with mean VAS pain scores of 6.8 ± 1.2, IKDC scores of 45.3 ± 7.5, and Lysholm scores of 52.1 ± 8.9. Postoperatively, all patients exhibited marked improvements: VAS scores decreased to 1.5 ± 0.8 (p < 0.001), IKDC scores improved to 82.6 ± 6.4 (p < 0.001), and Lysholm scores increased to 88.7 ± 5.1 (p < 0.001) at 12-month follow-up.
Imaging studies confirmed optimal graft positioning and integrity in 26/28 cases (92.9%). Postoperative MRI at 3 days and 2 months follow-up demonstrated well-incorporated synthetic ligaments without evidence of synovitis or graft elongation (Figure 1). Radiographic evaluation revealed stable tunnel placement with no signs of osteolysis or screw migration (Figure 1). One patient developed transient joint effusion, resolved with aspiration and antibiotics, while two cases exhibited mild residual anterior laxity (side-to-side difference: 3-4 mm on KT-1000 arthrometer), managed non-operatively with targeted rehabilitation. No instances of graft re-rupture, infection, or hardware failure were observed.
A suboptimal outcome occurred in one patient with preexisting tunnel widening (>12 mm diameter), requiring bone grafting prior to synthetic ligament fixation. Postoperative CT scans confirmed adequate tunnel consolidation, though functional scores (IKDC: 70.2; Lysholm: 76.5) lagged behind the cohort average, highlighting the impact of severe bone loss on outcomes.
DATA AVAILABILITY:
Raw data is available in Supplementary File 1.
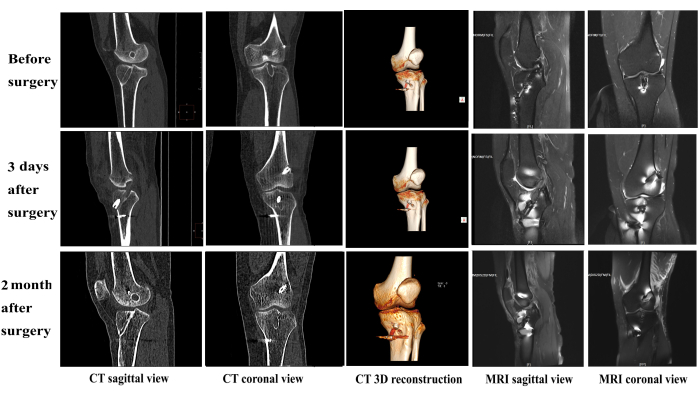
Figure 1: Preoperative and postoperative imaging of a 39-year-old male patient undergoing ACL reconstruction revision. Sagittal and coronal CT views, 3D reconstruction images, and sagittal and coronal MRI images were obtained before surgery, and at 3 days and 2 months postoperatively. Follow-up MRIs demonstrated well-incorporated synthetic ligaments without signs of synovitis or graft elongation. Radiographic evaluation showed stable tunnel placement with no evidence of osteolysis or screw migration. Please click here to view a larger version of this figure.
Supplementary File 1: Raw data for preoperative and postoperative functional scores. Please click here to download this File.
Discussion
The current study demonstrates that synthetic ligament-based revision ACL reconstruction provides reliable clinical outcomes, with significant improvements in knee stability and function (IKDC: 45.3 -82.6; Lysholm: 52.1- 88.7; p < 0.001) and low complication rates. The findings of this study underscore the technical feasibility and clinical efficacy of synthetic ligament-based revision of anterior cruciate ligament (ACL) reconstruction in addressing postoperative re-rupture. This approach demonstrated significant improvements in knee stability, pain reduction, and functional recovery by integrating meticulous surgical planning, advanced arthroscopic techniques, and structured rehabilitation. These outcomes align with emerging evidence supporting synthetic grafts as viable alternatives in complex revision scenarios, particularly when biological graft options are limited due to prior harvest or patient-specific contraindications16,17. The absence of graft re-rupture, infection, or major complications in the current cohort further challenges historical reservations regarding synthetic ligaments, such as synovitis or foreign body reactions18,19,20, suggesting that advancements in graft materials and surgical protocols may mitigate these risks.
Graft choice in revision ACL reconstruction
In revision ACL reconstruction, graft selection depends on patient factors, prior surgeries, and bone quality. Synthetic ligaments (e.g., LARS) offer immediate stability, no donor morbidity, and off-the-shelf availability, making them ideal for athletes or patients with exhausted autograft options. However, concerns remain about long-term durability, synovitis, and foreign-body reactions. Autografts such as quadriceps and patellar tendon provide biological incorporation and lower reinjury rates but require harvest, risking donor-site pain or weakness. Allografts avoid harvest complications but carry risks of delayed incorporation, immune response, and higher failure rates in young athletes. For severe bone loss, a two-stage approach with bone grafting may be needed before graft implantation. The optimal choice balances mechanical strength, biological integration, and patient-specific needs, with synthetic grafts excelling in expedited recovery and autografts/allografts preferred for long-term biological remodeling.
Biomechanical advantages and immediate stability
A critical advantage of synthetic ligaments lies in their inherent mechanical strength, which provides immediate stability post-implantation. Unlike biological grafts, which require a prolonged period of revascularization and remodeling to achieve load-bearing capacity, synthetic materials bypass the "ligamentization" phase, enabling aggressive early rehabilitation. This property is particularly advantageous in revision settings, where patients often present with residual instability or compromised tissue quality21,22,23. The synthetic ligament used in this study demonstrates mechanical stability through extensive biomechanical testing and clinical literature. Polyethylene terephthalate (PET) synthetic grafts, including the LARS (Ligament Augmentation and Reconstruction System) and similar designs, exhibit ultimate tensile strengths exceeding 2000-4000 N, surpassing the native ACL's strength (~1725 N) and maintaining consistent load-bearing capacity without the "ligamentization" phase required for biological grafts24,25.
In the current cohort, early mobilization, initiated within 24 h postoperatively, was instrumental in preventing arthrofibrosis and promoting functional recovery. The dual fixation strategy using metallic interference screws at 30° knee flexion further enhanced graft stability, a crucial factor given the altered biomechanics and potential tunnel misalignment inherent to revision cases. The biomechanical superiority of synthetic grafts, combined with precise fixation, likely contributed to the rapid improvements in functional scores (IKDC, Lysholm) and pain reduction (VAS) observed in this study.
Addressing anatomical challenges in revision surgery
Revision ACL reconstruction is inherently complex due to factors such as tunnel osteolysis, graft-tunnel mismatch, and scar tissue formation from prior procedures26. Preoperative imaging (CT and MRI) played a pivotal role in identifying tunnel position and integrity, allowing surgeons to strategize tunnel placement to avoid convergence with prior tunnels. In cases of moderate tunnel widening (<12 mm), synthetic ligament fixation with interference screws proved sufficient. However, one patient with severe tunnel expansion (>12 mm) required supplemental bone grafting to ensure adequate graft fixation. This highlights the importance of preoperative bone stock assessment and the need for adjunctive procedures in select cases. While lateral extra-articular procedures address persistent rotatory instability, particularly in high-risk patients with recurrent failures, severe pivot shifts, or generalized laxity, they have potential drawbacks such as the risk of over-constraint if improperly tensioned, added surgical time, and occasional lateral knee discomfort. Combining anterolateral procedures with ACL reconstruction reduces graft failure rates without increasing complications, as demonstrated in a recent meta-analysis27. The use of synthetic grafts in this context offers flexibility, as their modular design and lack of biological incorporation reduce dependency on optimal tunnel geometry compared to autografts28,29. Furthermore, arthroscopic debridement of scar tissue and residual graft material ensured a clean intra-articular environment, minimizing impingement risks and optimizing graft placement30.
Intraoperative challenges during synthetic ligament revision ACL reconstruction include tunnel misalignment, addressed by standardized tunnel planning-using pre-op CT/MRI to avoid prior tunnel convergence, streamlining intraoperative decision-making and intraoperative fluoroscopy to optimize positioning, and graft impingement, mitigated by notchplasty and dynamic arthroscopic range-of-motion testing before fixation. Postoperatively, transient joint effusion typically resolves with aspiration and NSAIDs, while persistent synovitis may require arthroscopic debridement and corticosteroid injection31. Graft failure is often associated with premature return to sport or severe tunnel widening (>12 mm), necessitating staged bone grafting in at-risk cases32.
Comparative analysis: synthetic vs. biological grafts
This study did not include a direct comparison to autograft or allograft revision cases due to its retrospective design and the inherent challenges of creating equivalent comparator groups in complex revision scenarios. The primary objective was to evaluate the feasibility and outcomes of synthetic ligament revision in a specific, high-risk population where biological graft options were often contraindicated or unavailable due to prior harvest or severe tunnel osteolysis. While we report significant within-group improvements in pain and function (p < 0.001), these results should not be interpreted as demonstrating superiority to biological grafts, but rather as evidence that synthetic ligaments represent a viable alternative when autografts/allografts are not suitable. The debate between synthetic and biological grafts in ACL reconstruction remains contentious. Autografts, while considered the gold standard for primary repairs, carry donor site morbidity such as patellar tendonitis, quadriceps weakness, and limited availability in revision settings33,34. Allografts, though avoiding harvest complications, pose risks of immune rejection and delayed incorporation. Synthetic ligaments circumvent these issues, offering "off-the-shelf" availability and eliminating donor site morbidity -- a critical advantage for patients with multiple prior surgeries. Additionally, the immediate mechanical stability of synthetic grafts allows for simplified tensioning and fixation compared to biological grafts, which require careful adjustment to account for future stretching during ligamentization. Results of the current study align with recent studies reporting comparable short-term outcomes between synthetic and biological grafts in revision cases35,36.
Histological and imaging studies of synthetic ligaments demonstrate variable but generally favorable host tissue integration, with limited inflammatory responses in modern graft designs. Previous histological analyses of retrieved PET-based grafts such as LARS show fibroblast infiltration into the graft's porous structure by 6-12 months, with collagen deposition along fibers mimicking native ligament architecture, though without complete ligamentization37. However, concerns persist regarding long-term durability. Synthetic materials, such as polyethylene terephthalate or ligament augmentation reconstruction systems (LARS), have historically been associated with wear debris, synovitis, and late-onset failures38. The absence of such complications in the current cohort over a mean 12.3-month follow-up may reflect advancements in graft design, such as improved fiber coatings or reduced abrasion profiles. Nevertheless, the limited follow-up period precludes definitive conclusions about long-term performance, underscoring the need for extended surveillance.
Limitations and clinical implications
While this study provides promising evidence for synthetic ligament use in revision ACL reconstruction, several limitations warrant consideration. First, the retrospective design introduces inherent biases, including selection bias and unmeasured confounding variables. The modest sample size (n = 28) and short follow-up period (mean 12.3 months) limit the generalizability of findings, particularly regarding rare complications like late-onset synovitis or degenerative joint changes. Ongoing, beyond 18 months, long-term follow-up of the patients could overcome such limitation. Second, the exclusion of patients with concomitant ligamentous injuries or advanced osteoarthritis restricts applicability to isolated ACL re-ruptures. Third, the technical demands of synthetic ligament implantation, requiring expertise in arthroscopy and tunnel planning, may limit its adoption in resource-constrained settings. Lastly, patient-reported outcome measures (PROMs), such as return-to-sport status or quality-of-life scores, would help acquire more comprehensive treatment results, which should be considered for future study design.
Despite these limitations, the clinical implications are significant. This study provides novel evidence supporting synthetic ligament-based revision ACL reconstruction as a viable solution for re-rupture cases, particularly when biological graft options are limited. The findings of this study underscore the technical feasibility and clinical efficacy of synthetic ligament-based revision anterior cruciate ligament (ACL) reconstruction in addressing postoperative re-rupture. By integrating meticulous surgical planning, advanced arthroscopic techniques, and structured rehabilitation, this approach demonstrated significant improvements in knee stability, pain reduction, and functional recovery. These outcomes align with emerging evidence supporting synthetic grafts as viable alternatives in complex revision scenarios, particularly when biological graft options are limited due to prior harvest or patient-specific contraindications.
This study differs from previous research in three key aspects: First, while most prior studies on synthetic ligaments focused on primary ACL reconstruction, the current study specifically evaluated their use in revision scenarios where anatomical challenges are greater. Second, unlike earlier reports that raised concerns about synthetic graft failure and synovitis, results of the current study with modern graft designs showed no such complications during follow-up, suggesting improved material properties, thus providing new evidence that updates historical perspectives on synthetic graft utility in complex revision cases.
The absence of graft re-rupture, infection, or major complications in the current cohort further challenges historical reservations regarding synthetic ligaments, such as synovitis or foreign body reactions, suggesting that advancements in graft materials and surgical protocols may mitigate these risks. Furthermore, the protocol's emphasis on preoperative imaging and bone grafting for severe tunnel defects provides a framework for managing complex cases.
Future directions
Prospective randomized controlled trials comparing synthetic and biological grafts in revision ACL reconstruction are urgently needed to establish comparative efficacy and safety. Long-term follow-up studies (>5 years) are essential to evaluate synthetic ligament survivorship, degenerative changes, and late complications. Additionally, biomechanical studies assessing synthetic graft behavior under cyclic loading could inform design improvements. Finally, cost-effectiveness analyses would clarify the economic impact of synthetic grafts, which may offset expenses related to prolonged rehabilitation or repeat revisions.
In summary, synthetic ligament-based revision ACL reconstruction represents a promising strategy for addressing postoperative re-rupture, combining technical precision with immediate functional restoration. While not a panacea for all revision scenarios-particularly those with severe bone loss -- it expands surgical options for complex cases and underscores the importance of individualized patient selection and technical rigor.
Conclusion
In conclusion, synthetic ligament revision ACL reconstruction represents a reliable solution for re-rupture cases, combining precise surgical technique with structured rehabilitation. While not universally applicable, particularly in severe bone loss scenarios, it expands the surgical toolkit for managing complex revisions, emphasizing the need for individualized patient selection and technical rigor.
Acknowledgements
The study was funded by the "Tian Chi Ying Cai" Young Doctors' Talent Introduction Program of Xinjiang Uyghur Autonomous Region, Xinjiang "Tianshan Talents" Medical and Health High-level Talent Program (TSYC202301B077), and the Major Scientific Research Project Cultivation Project of Xinjiang Medical University (No: XYD2024ZX09).
AUTHOR CONTRIBUTIONS:
QM led the clinical data collection, surgical execution, and drafting of the manuscript. LS and AM jointly oversaw study design, funding, ethical compliance, and final manuscript revisions. All authors read and approved the final version of the submitted manuscript.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 9 mm metallic interference screws | Arthrex | AR-1390E | 9 mm × 20 mm cannulated interference screw for emoral and tibial graft fixation |
| Arthroscopic burr | DePuy Mitek | www.jnjmedtech.com/en-US/product/vue-arthroscopic-equipment-solutions | Bone preparation |
| Arthroscopic shaver | Stryker System 8 | www.surgicaldirect.com/m_product_page.php?item=Stryker+System+8+LG | Model: 8205-000-000 (System 8 Dual-Trigger Rotary Handpiece) |
| Drill | Arthrex Drill Guide | AR-8956G-20 | 2.0 mm drill guide |
| Guide pins | Smith & Nephew | 410236 | Richards guide pin, 230 mm × 2.4 mm |
| Polyethylene terephthalate-based synthetic ligament | LARS Ligament (Corin) | www.coringroup.com/healthcare-professionals/products/lars | Graft material for revision ACL reconstruction |
| Reamers (7.5 mm) | Arthrex | AR-1407.5 | Cannulated headed reamer, 7.5 mm |
| SPSS | IBM | www.ibm.com/products/spss-statistics | Software; Version 27.3 |
References
- Floyd, E. R., et al. Evaluation of knee outcomes and anterior cruciate ligament graft failure when comparing medial collateral ligament reconstruction versus mcl repair in patients with multiple ligament knee injuries: A systematic review. Orthop J Sports Med. 13 (2), 23259671241302095(2025).
- Napolitano, J., Duerson, D., MacDonald, J. Anterior cruciate ligament injuries in female athletes. JAMA. 332 (8), 662-663 (2024).
- Balendra, G., et al. Factors affecting return to play and graft re-rupture after primary ACL reconstruction in professional footballers. Knee Surg Sports Traumatol Arthrosc. 30 (7), 2200-2208 (2022).
- Volz, R., Borchert, G. H. Re-rupture rate and the post-surgical meniscal injury after anterior cruciate ligament reconstruction with the Press-Fit-Hybrid-technique in comparison to the interference screw technique: a retrospective analysis of 200 patients with at least 3 years follow-up. Arch Orthop Trauma Surg. 143 (2), 935-949 (2023).
- D'Ambrosi, R., et al. Multiple revision anterior cruciate ligament reconstruction: not the best but still good. Knee Surg Sports Traumatol Arthrosc. 31 (2), 559-571 (2023).
- Legnani, C., et al. Anterior cruciate ligament reconstruction with synthetic grafts. A review of literature. Int Orthop. 34, 465-471 (2010).
- Kohn, M. D., Sassoon, A. A., Fernando, N. D. Classifications in brief: Kellgren-Lawrence classification of osteoarthritis. Clin. Orthop. Relat. Res. 474, 1886-1893 (2016).
- Sarraj, M., et al. Over-the-top ACL reconstruction yields comparable outcomes to traditional ACL reconstruction in primary and revision settings: a systematic review. Knee Surg Sports Traumatol Arthrosc. 27 (2), 427-444 (2019).
- Marx, J. S., et al. Revision ACL reconstruction has higher incidence of 30-day hospital readmission, reoperation, and surgical complications relative to primary procedures. Knee Surg. Sports Traumatol. Arthrosc. 30 (5), 1605-1610 (2022).
- Meena, A., et al. No difference in patient reported outcomes, laxity, and failure rate after revision ACL reconstruction with quadriceps tendon compared to hamstring tendon graft: a systematic review and meta-analysis. Knee Surg Sports Traumatol Arthrosc. 31 (8), 3316-3329 (2023).
- Meena, A., et al. Quadriceps tendon autograft with or without bone block have comparable clinical outcomes, complications and revision rate for ACL reconstruction: A systematic review. Knee Surg Sports Traumatol Arthrosc. 31 (6), 2274-2288 (2023).
- Ventura, A., et al. Revision surgery after failed ACL reconstruction with artificial ligaments: clinical, histologic and radiographic evaluation. Eur J Orthop Surg Traumatol. 24 (1), 93-98 (2014).
- Nukuto, K., et al. Current development in surgical techniques, graft selection and additional procedures for anterior cruciate ligament injury: A path towards anatomic restoration and improved clinical outcomes-a narrative review. Ann Jt. 8, 39(2023).
- Batty, L. M., et al. Synthetic devices for reconstructive surgery of the cruciate ligaments: a systematic review. Arthroscopy. 31 (5), 957-968 (2015).
- Gopinatth, V., et al. Consistent indications and good outcomes despite high variability in techniques for two-stage revision anterior cruciate ligament reconstruction: A systematic review. Arthroscopy. 39 (9), 2098-2111 (2023).
- Kentel, M., et al. Treatment results and safety assessment of the LARS system for the reconstruction of the anterior cruciate ligament. Adv Clin Exp Med. 30 (4), 379-386 (2021).
- Barrett, G. R., Brown, T. D. Femoral tunnel defect filled with a synthetic dowel graft for a single-staged revision anterior cruciate ligament reconstruction. Arthroscopy. 23 (7), 796.e1-796.e4 (2007).
- Di Benedetto, P., et al. Histological analysis of ACL reconstruction failures due to synthetic-ACL (LARS) ruptures. Acta Biomed. 91 (4-S), 136(2020).
- Tulloch, S. J., Devitt, B. M., Norsworthy, C. J., Mow, C. Synovitis following anterior cruciate ligament reconstruction using the LARS device. Knee Surg Sports Traumatol. Arthrosc. 27 (8), 2592-2598 (2019).
- Niki, Y., Matsumoto, H., Enomoto, H., Toyama, Y., Suda, Y. Single-stage anterior cruciate ligament revision with bone-patellar tendon-bone: a case-control series of revision of failed synthetic anterior cruciate ligament reconstructions. Arthroscopy. 26 (8), 1058-1065 (2010).
- Ciapini, G., et al. ACL replacement with synthetic vs. biological tendon grafts: Long-term follow-up comparison using objective evaluations. Surg Technol Int. 39, 369-374 (2021).
- Lubowitz, J. H. Editorial commentary: Synthetic ACL grafts are more important than clinical nonbelievers may realize. Arthroscopy. 31 (5), 969-970 (2015).
- Barnaś, M., Kentel, M., Morasiewicz, P., Witkowski, J., Reichert, P. Clinical assessment and comparison of ACL reconstruction using synthetic graft (Neoligaments versus FiberTape). Adv Clin Exp Med. 30 (5), 491-498 (2021).
- Mulford, J. S., Chen, D. Anterior cruciate ligament reconstruction: A systematic review of polyethylene terephthalate grafts. ANZ J Surg. 81 (11), 785-789 (2011).
- Codorean, I. B., et al. The Use of the Ligament Augmentation and Reconstruction System (LARS) in clinical practice. Key Eng Mater. 745, 111-123 (2017).
- McDermott, E., et al. Biomechanical comparison of anterior cruciate ligament reconstruction fixation methods and implications on clinical outcomes. Ann Jt. 8, 15(2023).
- D'Ambrosi, R., et al. Combining an anterolateral complex procedure with anterior cruciate ligament reconstruction reduces graft reinjury without increasing the rate of complications: A Systematic Review and meta-analysis of randomized controlled trials. Am J Sports Med. 52 (8), 2129-2147 (2025).
- Panagiotopoulos, E., Prodromidis, A. D., Zampeli, F. Synthetic versus biological grafts in anterior cruciate ligament reconstruction: A systematic review and meta-analysis. Knee Surg Sports Traumatol Arthrosc. 29 (3), 741-754 (2021).
- Legnani, C., Ventura, A. Synthetic grafts for anterior cruciate ligament reconstructive surgery. Med Eng Phys. 117, 103992(2023).
- Takashima, Y., et al. The influence of ruptured scar pattern of human anterior cruciate ligament remnant tissue on tendon-bone healing in vivo. J Orthop Res. 41 (3), 500-510 (2023).
- Özbek, E. A., et al. Failure rates and complications after multiple-revision ACL reconstruction: comparison of the over-the-top and transportal drilling techniques. Orthop J Sports Med. 11 (7), 23259671231186972(2023).
- Grassi, A., et al. What is the mid-term failure rate of revision ACL reconstruction? A systematic review. Clin Orthop Relat Res. , 2484-2499 (2017).
- Jackson, D. W., Heinrich, J. T., Simon, T. M. Biologic and synthetic implants to replace the anterior cruciate ligament. Arthroscopy. 10 (4), 442-452 (1994).
- Melinte, R. M., et al. Synthetic grafts in anterior cruciate ligament reconstruction surgery in professional female handball players-a viable option. Diagnostics. 14 (17), 1951(2024).
- Ostojic, M., et al. Graft selection in anterior cruciate ligament reconstruction: A comprehensive review of current trends. Medicina. 60 (12), 2090(2024).
- Gharpinde, M. R., Jaiswal, A. M., Dhanwani, Y. A Comprehensive review of graft choices and surgical techniques in primary anterior cruciate ligament reconstruction: An outcome analysis. Cureus. 16 (9), e68701(2024).
- Yu, C., et al. Application of nondegradable synthetic materials for tendon and ligament injury. Macromol Biosci. 23 (12), 2300259(2023).
- Yu, C., et al. Primary ACL reconstruction using the LARS device is associated with a high failure rate at minimum of 6-year follow-up. Knee Surg Sports TraumatolArthrosc. 27, 3626-3632 (2019).
Reprints and Permissions
This article has been published
Video Coming Soon