This article presents a protocol to differentiate vestibular migraine (VM) and Meniere's disease (MD) using cochlear-vestibular function assessments, including pure tone audiometry and videonystagmography (VNG), providing evidence for clinical differential diagnosis.
Method Article
Differences Between Vestibular Migraine and Meniere's Disease Based on Cochlear-Vestibular Function Assessment: A 6-Year Retrospective Clinical Study
* These authors contributed equally
In This Article
Summary
Abstract
Audiological and vestibular function tests are the most commonly used noninvasive evaluation methods for vertigo diseases. Preliminary studies have shown that detailed medical history, audiological, and vestibular function evaluation are effective methods to distinguish Meniere's disease and vestibular migraine diseases. This study retrospectively included 503 patients with vestibular migraine and 1,125 patients with Meniere's disease. Patients underwent pure tone audiometry and videonystagmography (VNG), including spontaneous nystagmus testing and the caloric test. In our study, we found that patients with Meniere's disease often exhibit abnormal unilateral weakness, while those with vestibular migraine show changes in vestibular function characterized by labyrinthine hyperactivity. Compared to vestibular migraine patients, Ménière's disease patients are more likely to experience unilateral full-frequency hearing loss. This study systematically compared the vestibular function and audiological characteristics of vestibular migraine and Ménière's disease, providing an evidence-based foundation for clinical differential diagnosis.
Introduction
Vestibular migraine (VM) and Ménière's disease (MD) are the two most common paroxysmal vertigo disorders encountered in clinical practice. Both conditions are classified as paroxysmal vestibular syndromes in the International Classification of Vestibular Disorders (ICVD)1. Epidemiological surveys indicate that the global prevalence of VM ranges from 1% to 2.7%2, which is significantly higher than that of MD, with a prevalence of 0.2% to 0.5%3. Although the Barany Society has developed diagnostic criteria for both VM and MD to facilitate standardized diagnosis worldwide4,5, both conditions share recurrent vertigo as their core symptom. The overlap of clinical symptoms, such as hearing loss and tinnitus, combined with the absence of highly specific biomarkers, still poses significant challenges for clinicians in distinguishing between the two disorders.
In recent years, advancements in neuroimaging and molecular biology have provided new insights into the mechanisms underlying VM and MD. For instance, functional magnetic resonance imaging (fMRI) has revealed that patients with VM exhibit abnormal functional connectivity within the vestibular cortical network, suggesting that central sensitization plays a key role in its pathogenesis6. In contrast, endolymphatic hydrops (EH), the pathological basis of MD, may be associated with abnormal expression of aquaporin (AQP) and local inflammatory responses7. Additionally, the differential expression of novel biomarkers, such as serum calcitonin gene-related peptide (CGRP) and interleukin-6 (IL-6), in VM and MD offers potential support for differential diagnosis8,9. While these methods show promise in distinguishing between VM and MD, they require expensive detection equipment and incur high diagnostic costs, which makes comprehensive clinical diagnosis and treatment challenging, particularly in primary healthcare settings.
At present, the clinical differentiation between VM and MD primarily relies on a detailed medical history, along with assessments of audiological and vestibular function. Previous studies10 compared the results of the video head impulse test (vHIT) and the caloric test (CT) in patients with VM and MD, revealing that the CT is particularly useful in distinguishing between these two conditions. However, these studies only evaluated the function of the horizontal semicircular canal using vHIT and CT, without assessing the intensity of nystagmus or the audiological characteristics triggered by the CT. Another study showed that patients with MD often exhibited a dissociation between the results of the vHIT and CT, while those with VM had a low incidence of abnormal findings in the CT11. Most previous research has focused on single-parameter analysis, such as the unilateral weakness rate in CT, while the comprehensive value of multiple parameters (including total labyrinth response, directional preponderance, audiological data, etc.) remains largely unexplored.
This study aims to establish an objective diagnostic framework for the differential diagnosis of VM and MD through a systematic analysis of vestibular-auditory functional differences, referencing the diagnostic criteria of the Barany Society4,5. The study uses Videonystagmography (VNG) and pure-tone audiometry as non-invasive assessment tools, which can quantify peripheral vestibular function and auditory damage, both of which have been corroborated by several studies12,13,14. Compared to MRI or biomarker testing, these functional assessments are more cost-effective, accessible, and particularly suitable for primary healthcare settings. Based on these findings, this approach is effective for rapid screening of newly diagnosed patients with vertigo, and when combined with the patient's history, can enhance diagnostic accuracy.
Protocol
The study was approved by the ethical review board of Sun Yat-sen Memorial Hospital of Sun Yat-sen University (No.SYSKY-2025-572-01). Written informed consent was waived because of this retrospective analysis.
A total of 1,628 patients diagnosed with VM and MD at the Vertigo Diagnosis and Treatment Center of Sun Yat-sen Memorial Hospital, Sun Yat-sen University, between August 1, 2018, and July 31, 2024, were included in this study. This cohort consisted of 1,125 cases of MD and 503 cases of VM.
1. Patient Selection
- Inclusion criteria
- VM group: Include patients who meet the diagnostic criteria for Meniere's disease as outlined by the International Barany Society in 20155.
- MD group: Include patients who meet the diagnostic criteria for vestibular migraine as outlined by the International Barany Society in 20154.
- Exclusion criteria
- Exclude patients with coexisting central nervous system disorders (e.g., stroke, multiple sclerosis).
- Exclude patients who are taking vestibular suppressants or anti-anxiety medications.
- Exclude patients with dual diagnosis (both VM and MD).
2. Audiometric testing
- Instruct patients to perform pure-tone audiometry (the hearing test): Seat patients comfortably in an acoustically insulated room complying with ISO 8253-1 standards (background noise ≤ 30 dB).
- Fit calibrated headphones, explain responding to audible tones (e.g., raise hand/press button when hearing beeps).
- Present tones at varying frequencies (125-8000 Hz) and intensities, starting at a faint level, adjust based on responses to determine the softest audible sound (audiometric threshold) for each frequency.
- Record thresholds systematically to generate an audiogram.
3. Videonystagmography (VNG) test
NOTE: Vestibular function and nystagmus were evaluated using VNG, including Spontaneous nystagmus (SN) test, Supine roll test, Dix-Hallpike test, and CT conducted with the VertiGoggles-M system (see Table of Materials).
- SN Test
- Instruct the patient to remain in a dark environment while wearing an eye mask. Keep the eyes open for 1 min to observe any spontaneous nystagmus.
- Record the direction and slow-phase velocity of the nystagmus. Measure the slow-phase velocity (SPV) in degrees per second (°/s). Define an abnormal result (SN+) as an SPV greater than 6°/s15. Calculate SPV using VNG software.
- Evaluate the rhythm of nystagmus (regular vs. irregular) and fixation suppression (reduced vs. enhanced).
NOTE: Peripheral nystagmus was defined as unidirectional with regular rhythm and reduced fixation suppression; central nystagmus was defined as direction-changing with irregular rhythm and enhanced fixation suppression.
- Dix-Hallpike and Supine roll test
- Dix-Hallpike test
- Instruct the patient to rotate their head 45° to the left, then recline backward with the head at a 30° angle to the horizontal plane. Observe for nystagmus using VNG in a dimly lit room (to minimize visual fixation). The VNG system tracks eye movements via infrared cameras, recording nystagmus direction, velocity, and duration automatically
- Next, instruct the patient to rotate their head 45° to the right and recline backward, maintaining the same 30° angle to the horizontal plane, and again observe for nystagmus. The nystagmus should be monitored for at least 2 min in each position.
NOTE: If nystagmus is observed in any of the aforementioned head positions, the result is considered positive.
- Supine Roll Test
- Instruct the patient to lie in the supine position, with the head elevated 30°; the supine position and then the head turned max to the left; the supine position and then the head turned max to the right. Observe the nystagmus for at least 2 min at each position.
NOTE: If there is no nystagmus in any of the above positions, it is judged as negative; If the patient's head position shows Direction-changing positional nystagmus on both the left and right sides, it is judged as positive.
- Instruct the patient to lie in the supine position, with the head elevated 30°; the supine position and then the head turned max to the left; the supine position and then the head turned max to the right. Observe the nystagmus for at least 2 min at each position.
- Dix-Hallpike test
- Caloric test
NOTE: We selected air calorics to improve patient tolerance and reduce the risk of dizziness. Although water calorics offers slightly higher accuracy, previous studies have shown that the diagnostic efficacy of air calorics is comparable to that of water calorics16, while also offering advantages such as ease of operation and a lower risk of infection. Additionally, this confirms its consistency with vHIT17.- Instruct the patient to lie in the supine position, with the head elevated 30°, keeping their eyes open.
- Irrigate the ear canal with cold air at 24 °C and warm air at 50 °C for 60 s.
- The perfusion order is as follows: Right ear cold air (RC), Left ear cold air (LC), Right ear warm air (RW), and Left ear warm air (LW).
NOTE: Each irrigation lasted 60 s. - After each perfusion, ensure the subject remains still until the nystagmus subsides before proceeding to the next irrigation.
Results
Baseline characteristics
A total of 503 patients with VM and 1,125 patients with MD were included in the study. The average age of onset for the VM group was 45.89 ± 18.16 years, whereas the average age of onset for the MD group was 51.63 ± 14.29 years. A significant difference was observed between the two groups (P < 0.001). The proportion of women in the VM group was 76.1%, significantly higher than the 59.3% in the MD group (P < 0.001) (Table 1, Figure 1).
Vestibular function test results
The Total Labyrinthine Response (TLR) formula is as follows:
SPV (all) = RC + LC + RW + LW (°/s)
where RW = right warm; LW = left warm; RC = right cool; LC = left cool.
For the cutoff related to hyperactivity, each cool irrigation should exceed 50°/s, or the SPV should be greater than 80°/s for each of the warm irrigations18.
The Unilateral weakness (UW) formula is as follows:
UW (%) = {[(RC + RW) - (LC + LW)]/ (RC + RW + LC + LW)} × 100%
where RW = right warm; LW = left warm; RC = right cool; LC = left cool.
The UW value ≥ 25% is considered abnormal18.
Based on the severity of UW, subjects are divided into four groups19: Group 1: 0-24% UW (normal calorific response); Group 2: 25-50% UW (mild unilateral weakness); Group 3: 51-75% UW (moderate unilateral weakness); Group 4: 76-100% UW (severe unilateral weakness).
The Directional preponderance (DP) formula is as follows:
DP (%) = {[(RC + LW) - (LC+ RW)]/ (RC + RW + LC + LW)} × 100%
where RW = right warm; LW = left warm; RC = right cool; LC = left cool.
The DP value greater than 30% is considered abnormal18.
In patients with positive SN, 9.3% (47/503) in the VM group and 27.2% (306/1125) in the MD group exhibited peripheral nystagmus (unidirectional, regular rhythm, with reduced fixation suppression). The positive rate in the MD group was significantly higher than that in the VM group (P < 0.001) (Table 2). No central nystagmus characteristics were observed in either group.
The average SPV in the VM group was 81.0 ± 49.3°/s, significantly higher than that in the MD group (P < 0.001) (Figure 2A). The abnormal rate of UW in the MD group (59.1%) was significantly higher than that in the VM group (29.8%) (P < 0.001) (Table 2, Figure 2B). Additionally, the incidence of labyrinth hyperactivity disorder was significantly higher in the VM group compared to the MD group (P < 0.001). (Figure 2B). Significant differences were observed between the MD and VM groups in the normal UW group. Furthermore, there were notable differences between the MD and VM groups in the mild heat test UW group (Group 2), as well as in the moderate and severe fever groups (Groups 3 and 4) (Figure 2C). The positive rate of DP in the MD group was 26.0%, significantly higher than the 11.7% in the VM group (P < 0.001) (Table 2). The differences in PTA results between the VM and MD groups of patients is shown in Table 3.
A multivariable analysis controlling for age and sex showed no significant gender differences in SPV (P = 0.36) (Table 4), which is consistent with previous studies indicating that air calorics do not exhibit gender-related variability in nystagmus intensity20 .
Audiological characteristics
According to the World Health Organization's revised standards in 2022, the average hearing threshold was classified as follows: (i) Normal hearing: Hearing level less than 20 dB; (ii) Mild hearing loss: Hearing level of 20-35 dB; (iii) Moderate hearing loss: Hearing level of 35-50 dB; (iv) Moderate to severe hearing loss: Hearing level of 50-65 dB; (v) Severe hearing loss: Hearing level of 65-80 dB; (vi) Very severe hearing loss: Hearing level of 80-95 dB; (vii) Complete hearing loss (total deafness): Hearing level greater than 95 dB. The following types of hearing loss are defined based on the frequency range in which the maximum deviation of the hearing threshold occurs: (i) Low-frequency drop type: Drop at 0.25 kHz, 0.5 kHz, and 1 kHz; (ii) Full-frequency drop type: Drop across the entire 0.25 kHz to 8 kHz range; (iii) High-frequency drop type: Drop at 4 kHz and 8 kHz.
A total of 265 patients in the VM group and 1,060 patients in the MD group underwent pure tone audiometry at our center. The abnormal hearing rate in the MD group was 90.4%, significantly higher than the 54.3% in the VM group (P < 0.001)(Figure 3A). There were no significant differences between the MD and VM groups in low-frequency and high-frequency hearing loss (P > 0.05), but the MD group had a significantly higher rate of full-frequency hearing loss compared to the VM group (P < 0.001) (Figure 3B).
In our study, we performed a multivariable logistic regression analysis, controlling for potential confounding factors such as age and gender. The results indicated no significant differences. The analysis confirmed no significant confounding effects of age or gender on vestibular and audiometric parameters (Table 4).
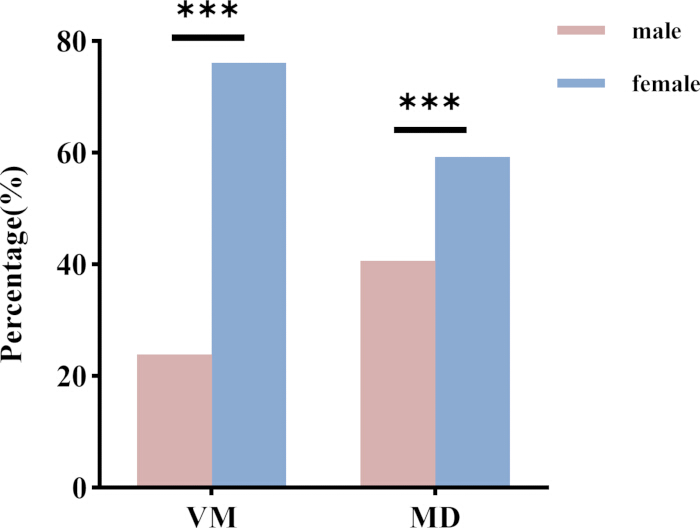
Figure 1: Comparison of results between male and female patients with VM and MD. VM: Vestibular Migraine, MD: Meniere's Disease. Please click here to view a larger version of this figure.
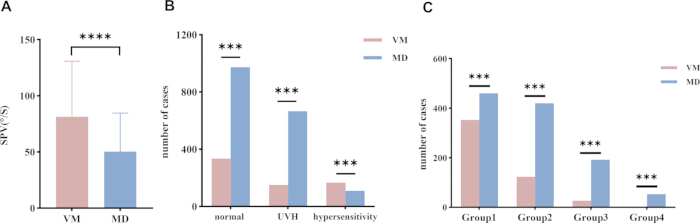
Figure 2: Caloric test-derived nystagmus and vestibular function comparisons between vestibular migraine (VM) and Meniere's disease (MD) patients. Please click here to view a larger version of this figure.
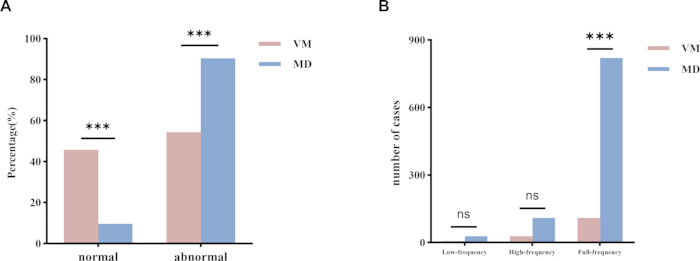
Figure 3: Pure tone audiometry test result comparisons between vestibular migraine (VM) and Meniere's disease (MD) patients. Please click here to view a larger version of this figure.
Table 1: Demographic information. Please click here to download this Table.
Table 2: VNG test results of the two groups of patients (n,%) Please click here to download this Table.
Table 3: Differences in PTA results between the two groups of patients (n,%). Please click here to download this Table.
Table 4: A multivariate model employed to analyze the confounding variables, such as age and gender. Please click here to download this Table.
Discussion
This study ensured result accuracy and reliability through key measures: pure tone audiometry in ISO 8253-1 compliant sound-insulated rooms (background noise ≤30 dB) with calibrated headphones; VNG using VertiGoggles-M to track eye movements in dimly lit Dix-Hallpike/supine roll tests. A notable modification was using air instead of water calorics, balancing accuracy with better operability, patient tolerance, and lower infection risk. Patient cooperation was ensured via instructions and training to avoid misjudgments. This enhanced result reliability, making VM and MD vestibular-auditory function differences clinically meaningful for differential diagnosis.
Based on the results of vestibular function and audiology, this study systematically compared the differences between VM and MD. Our findings indicate that women are more prevalent in both groups, with over three-quarters of patients with vestibular migraine being women, which aligns with previous research21,22,23,24. In this study, we also observed that the abnormal rate of spontaneous nystagmus in the MD group (27.2%) was significantly higher than in the VM group (9.3%). This difference may stem from the distinct pathogenesis of MD and VM. The pathological mechanism of VM primarily involves abnormal integration of central vestibular signals and trigeminal neurovascular regulation disorders, which are generally reversible and do not lead to fixed peripheral structural damage25. In contrast, MD is mainly caused by damage to the inner ear balance organs, resulting in irreversible damage to the peripheral vestibular system. Consequently, the central nervous system compensates for the imbalance through eye movements.
In the vestibular function test, our results indicated that the intensity of nystagmus induced by the CT was higher in VM patients compared to MD patients. Additionally, VM patients were more prone to labyrinthine reaction SPV hypersensitivity. Previous studies have also found that CT intolerance occurred more frequently in VM patients20,26,27. This mechanism may be linked to an increased VOR time constant due to hypersensitivity of the vestibular system28,29,30. Vestibular hypersensitivity may result from disinhibition of the sensorimotor and vestibular cortical networks26. Dieterich & Brandt suggested that central sensitization in VM might cause an overreaction of the vestibular nuclei to incoming signals, especially increased excitability in the brainstem and vestibular cerebellar network31. As a consequence, VM patients tend to experience labyrinthine hyperactivity during the CT, likely due to weakened central vestibular inhibitory function. Furthermore, we found that MD patients were more likely to show UW abnormalities (59.1%) compared to VM patients, which aligns with previous studies16,17. MD is a perivestibular lesion, with the primary pathological manifestation being membranous labyrinth hydrops, which alters the concentration of endolymphatic ions in the inner ear. This reduces the compliance of the membranous labyrinth, thereby decreasing its responsiveness to cold and warm stimuli. The generally accepted theories of VM include: (i) activation and sensitization of the trigeminal neurovascular system, leading to vasospasm of the internal auditory and cerebral arteries; (ii) destruction of brain ion channels; and (iii) cortical diffusion depression theory32. As a result, MD patients are more likely to exhibit abnormal UW performance during the CT.
In pure tone audiometry, our results revealed that MD patients experienced significantly higher hearing loss compared to VM patients (90.4% vs. 54.3%). This finding is consistent with the study by Fidan Balayeva et al.33. Additionally, we found that MD patients were more likely to suffer from unilateral full-frequency hearing loss than VM patients. This could be related to cortical spreading inhibition (CSD) and abnormal thalamic cortical information integration. Previous studies have reported that functional MRI reveals abnormal vestibular cortical network connectivity in VM patients, suggesting a central sensitization mechanism30,34. In contrast, the hearing loss in VM patients may involve abnormalities in the central auditory pathway, typically resulting in mild to moderate hearing loss, often characterized by low-frequency sensory hearing loss, which tends to be reversible35,36. The full-frequency hearing loss in MD patients is associated with damage to the outer hair cells due to cochlear basement membrane edema37. As numerous studies have indicated, significant progressive hearing loss and tinnitus are more common in MD patients38,39. In summary, auditory symptoms, particularly unilateral full-frequency hearing loss, are more frequently observed in MD patients.
Some limitations of this study include the fact that data were collected from a single center, and the sample size of patients in both the MD and VM groups is relatively small. Second, we excluded patients with comorbid VM and MD. In the future, we plan to continue including clinically important gray-zone cases to explore the clinical features of mixed diagnoses. Third, our study did not include neuro-orthoptic examinations, which are considered valuable for assessing oculomotor dysfunction particularly relevant for VM, which may present with subtle eye movement abnormalities. This omission limits the completeness of our diagnostic protocol, and Future studies should incorporate neuro-ophthalmological evaluations to enhance the differential diagnosis between central and peripheral vestibular disorders.
This study systematically analyzed the clinical characteristics of VM and MD using multiple parameters. The results showed that MD patients exhibited abnormal UW in the CT, while VM patients demonstrated vestibular function changes characterized by labyrinthine hyperactivity. Compared to VM patients, MD patients were more prone to unilateral full-frequency hearing loss. Therefore, we recommend that in the differential diagnosis of VM and MD, if UW ≥ 25% and there is unilateral full-frequency hearing loss, Ménière's disease (MD) should be prioritized. If each cool irrigation should exceed SPV > 50°/s, or the SPV should be greater than 80°/s for each of the warm irrigations, with normal hearing or low-frequency hearing loss, vestibular migraine (VM) should be considered first. Furthermore, in the clinical assessment of vertigo patients, vestibular-auditory testing is undoubtedly a fundamental and core method, effectively identifying abnormalities in peripheral vestibular function and auditory pathways. However, MRI, as an important supplementary imaging tool, plays an irreplaceable role in excluding CNS lesions or cerebellopontine tumors. Therefore, the judicious integration of MRI can significantly enhance the ability to differentiate CNS lesions or cerebellopontine tumors, preventing missed or misdiagnosed cases and optimizing clinical decision-making.
Disclosures
The authors declare no conflicts of interest for this article.
Acknowledgements
This work was funded by the Science and Technology Projects in Guangdong (No.2014A020212097); Clinical research project of Chinese Medical Association (No.07030480056).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Pure tone audiometer | Interacoustics | AC40 | |
| Sound-proof booth | Acoustic Systems | AS-2018 | |
| Video-nystagnography system | ZEHNIT Medical Technology | VertiGoggles-M system |
References
- Bisdorff, A., von Brevern, M., Lempert, T., Newman-Toker, D. E. Classification of vestibular symptoms: towards an international classification of vestibular disorders. J Vestib Res. 19 (1-2), 1-13 (2009).
- Beh, S. C. Vestibular migraine. Curr Neurol Neurosci Rep. 22 (10), 601-609 (2022).
- Alexander, T. H., Harris, J. P. Current epidemiology of Meniere's syndrome. Otolaryngol Clin North Am. 43 (5), 965-970 (2010).
- Lempert, T., et al. Vestibular migraine: diagnostic criteria. J Vestib Res. 32 (1), 1-6 (2022).
- Lopez-Escamez, J. A., et al. Diagnostic criteria for Meniere's disease. J Vestib Res. 25 (1), 1-7 (2015).
- Kim, S. K., Nikolova, S., Schwedt, T. J. Structural aberrations of the brain associated with migraine: a narrative review. Headache. 61 (8), 1159-1179 (2021).
- Wangemann, P. Supporting sensory transduction: cochlear fluid homeostasis and the endocochlear potential. J Physiol. 576 (Pt 1), 11-21 (2006).
- Flook, M., et al. Differential proinflammatory signature in vestibular migraine and Meniere disease. Front Immunol. 10, 1229(2019).
- Naples, J. G., Soda, D., Rahman, K., Ruckenstein, M. J., Parham, K. Evaluating the role of otologic biomarkers to differentiate Meniere's disease and vestibular migraine. Ear Hear. 43 (2), 699-702 (2022).
- Yilmaz, M. S., et al. Comparison of the results of caloric and video head impulse tests in patients with Meniere's disease and vestibular migraine. Eur Arch Otorhinolaryngol. 278 (6), 1829-1834 (2021).
- Mavrodiev, V., Strupp, M., Vinck, A. S., van de Berg, R., Lehner, L. The dissociation between pathological caloric testing and a normal video head impulse test helps differentiate between Meniere's disease, vestibular migraine, and other vestibular disorders: a confirmatory study in a large cohort of 2,101 patients. Front Neurol. 15, 1449261(2024).
- Goto, F., Wasano, K., Kaneda, S., Okami, K. Prognostic significance of vestibular examination results in patients with vestibular migraine. Front Neurol. 15, 1370940(2024).
- Phillips, J. S., Mallinson, A. I., Hamid, M. A. Cost-effective evaluation of the vestibular patient. Curr Opin Otolaryngol Head Neck Surg. 19 (5), 403-409 (2011).
- Yilmaz, M., et al. Comparison of perinatal, newborn, and audiometry results of COVID-19 pregnant women. Int J Clin Pract. 2022, 2699532(2022).
- Coats, A. C. The diagnostic significance of spontaneous nystagmus as observed in the electronystagmographic examination. Acta Otolaryngol. 67 (1), 33-42 (1969).
- Oliveira, L. N. R., Oliveira, C. L. A., Lopes, K. C., Gananca, F. F. Diagnostic assessment of patients with Meniere's disease through caloric testing and the video head impulse test. Braz J Otorhinolaryngol. 87 (4), 428-433 (2021).
- Hannigan, I. P., Welgampola, M. S., Watson, S. R. D. Dissociation of caloric and head impulse tests: a marker of Meniere's disease. J Neurol. 268 (2), 431-439 (2021).
- Shepard, N. T., Jacobson, G. P. The caloric irrigation test. Handb Clin Neurol. 137, 119-131 (2016).
- Honaker, J. A., Shepard, N. T. Performance of Fukuda stepping test as a function of the severity of caloric weakness in chronic dizzy patients. J Am Acad Audiol. 23 (8), 616-622 (2012).
- Vitkovic, J., Paine, M., Rance, G. Neuro-otological findings in patients with migraine- and nonmigraine-related dizziness. Audiol Neurootol. 13 (2), 113-122 (2008).
- Cass, S. P., et al. Migraine-related vestibulopathy. Ann Otol Rhinol Laryngol. 106 (3), 182-189 (1997).
- Dieterich, M., Brandt, T. Episodic vertigo related to migraine (90 cases): vestibular migraine. J Neurol. 246 (10), 883-892 (1999).
- Neuhauser, H., Leopold, M., von Brevern, M., Arnold, G., Lempert, T. The interrelations of migraine, vertigo, and migrainous vertigo. Neurology. 56 (4), 436-441 (2001).
- Neuhauser, H. K., et al. Migrainous vertigo: prevalence and impact on quality of life. Neurology. 67 (6), 1028-1033 (2006).
- Murofushi, T., Tsubota, M., Kitao, K., Yoshimura, E. Simultaneous presentation of definite vestibular migraine and definite Meniere's disease: overlapping syndrome of two diseases. Front Neurol. 9, 749(2018).
- Li, Z. Y., et al. Clinical characteristics of definite vestibular migraine diagnosed according to criteria jointly formulated by the Bárány Society and the International Headache Society. Braz J Otorhinolaryngol. 88 (Suppl 3), S147-S154 (2022).
- Sharon, J. D., Hullar, T. E. Motion sensitivity and caloric responsiveness in vestibular migraine and Meniere's disease. Laryngoscope. 124 (4), 969-973 (2014).
- Jeong, S. H., Oh, S. Y., Kim, H. J., Koo, J. W., Kim, J. S. Vestibular dysfunction in migraine: effects of associated vertigo and motion sickness. J Neurol. 257 (6), 905-912 (2010).
- King, S., et al. Self-motion perception is sensitized in vestibular migraine: pathophysiologic and clinical implications. Sci Rep. 9 (1), 14323(2019).
- Li, Z. Y., Si, L. H., Shen, B., Yang, X. Altered brain network functional connectivity patterns in patients with vestibular migraine diagnosed according to the diagnostic criteria of the Bárány Society and the International Headache Society. J Neurol. 269 (6), 3026-3036 (2022).
- Brandt, T., Dieterich, M. Thalamocortical network: a core structure for integrative multimodal vestibular functions. Curr Opin Neurol. 32 (1), 154-164 (2019).
- Espinosa-Sanchez, J. M., Lopez-Escamez, J. A. New insights into pathophysiology of vestibular migraine. Front Neurol. 6, 12(2015).
- Balayeva, F., Kirazli, G., Celebisoy, N. Vestibular test results in patients with vestibular migraine and Meniere's disease. Acta Otolaryngol. 143 (6), 471-475 (2023).
- Dong, L., et al. Impairments to the multisensory integration brain regions during migraine chronification: correlation with the vestibular dysfunction. Front Mol Neurosci. 16, 1153641(2023).
- Battista, R. A. Audiometric findings of patients with migraine-associated dizziness. Otol Neurotol. 25 (6), 987-992 (2004).
- Shi, S., Wang, D., Ren, T., Wang, W. Auditory manifestations of vestibular migraine. Front Neurol. 13, 944001(2022).
- Liberman, M. C., Kujawa, S. G. Cochlear synaptopathy in acquired sensorineural hearing loss: manifestations and mechanisms. Hear Res. 349, 138-147 (2017).
- Johnson, G. D. Medical management of migraine-related dizziness and vertigo. Laryngoscope. 108 (1 Pt 2), 1-28 (1998).
- Lempert, T., Neuhauser, H. Epidemiology of vertigo, migraine and vestibular migraine. J Neurol. 256 (3), 333-338 (2009).