近年来,猪在科研中的使用有所增加。然而,猪的气道解剖结构较为复杂。本实验方案通过演示如何进行内镜引导下的气管插管,旨在进一步提高实验动物的安全性,避免动物遭受痛苦和不必要的死亡。
需要JoVE订阅才能观看此内容。 请登录或开始免费试用
本文内容
勘误通知
Important: There has been an erratum issued for this article. View Erratum Notice
摘要
摘要
气管插管通常是猪模型转化研究中的基本要求,适用于需要确保气道通畅或实施高通气压力的各种干预措施。气管插管是一项具有挑战性的技术, 需要在理想条件下完成最低数量的成功经气管插管以达到较高的成功率,但这一要求对于非麻醉专业的研究人员而言往往难以实现。由于猪的气道解剖结构特殊,通常可视为困难气道。无法建立可靠的气道可能导致实验动物受伤、发生不良事件甚至死亡。通过前瞻性、随机、对照的评估方法已证实,与传统插管相比,纤维支气管镜辅助经气管插管虽然耗时较长,但首次通过成功率更高,且不会引起具有临床意义的血氧饱和度下降。本模型提供了一种内镜引导下经气管插管的标准化操作方案,可为经气管插管技术经验不足的研究人员建立可靠的气道保障。 通过 直接喉镜检查。该操作旨在尽量减少动物痛苦和不必要的动物损耗。
引言
对于需要确保气道通畅或高通气压力(如心肺复苏期间的通气1或急性呼吸窘迫综合征2)的各种干预措施,或需要避免声门上气道器械内部压迫影响脑血流3的研究而言,气管插管通常是猪模型转化研究中的基本要求。在预期猪存在困难气道的情况下,声门上气道器械有时被推荐作为替代方案4,5。
尽管猪的肺部生理特征与人类相似6,但由于猪的口咽气管解剖结构存在特定差异,气道建立有时会明显更加困难7。猪的吻部开口狭窄且舌头体积较大,喉部活动度极高,会厌相对较大,其游离端延伸至软腭。向尾侧观察,喉与气管之间形成一个钝角。杓状软骨体积较大8。气道最狭窄的部位位于声门下水平9,这与儿童的气道解剖结构相似10。由于猪的喉部活动度很高,气管导管前端可能已通过声门,但喉部被向尾侧推移数厘米,这种情况可能被误认为插管成功8,
访问受限。请登录或开始试用以查看此内容。
方案
本方案中的实验已获得州及机构动物护理委员会(德国莱茵兰-普法尔茨州科布伦茨地区检验局,批准号:G20-1-135)的批准。实验按照ARRIVE指南进行。本研究共使用10只麻醉的雄性猪(Sus scrofa domestica),平均体重为30 kg ± 2 kg,年龄为12至16周。
1. 动物准备
- 维持动物的正常环境以尽量减少应激。在计划实验前 6 小时禁食,以降低误吸风险,但可自由饮水。
- 通过肌肉注射(使用 20 G 针头)向臀部或颈部注射咪达唑仑(0.5 mg/kg)和阿扎哌隆(2–3 mg/kg)(参见材料表)对猪进行镇静。注射后让动物保持安静,直至镇静生效(15–20 分钟)。
注意:根据各国法规,镇静剂的使用可能受到监管,可能需要或不需要经过培训的兽医监督。在规划实验前,请咨询当地主管部门。 - 将已镇静的动物从畜舍转移至实验室。转运时间不得超过有效镇静持续时间(本实验中为 30–60 分钟)。确保采取充分保温措施,防止动物体温过低(即低于 38 °C),例如根据外界温度用毯子覆盖动物身体。
- 使用夹在耳部或尾部的传感器(参见材料表)监测外周血氧饱和度(SpO2)。
- 在耳缘静脉插入外周静脉套管(22 G)前,先用消....
访问受限。请登录或开始试用以查看此内容。
结果
在一项前瞻性、随机、对照研究中,对10只雄性猪(年龄12–16周,体重30 kg ± 3 kg)进行了气管插管。将猪随机分为两组:一组采用传统喉镜插管(CI组),另一组采用辅助插管 通过 根据方案中所述使用灵活插管内窥镜的一组(FIE组)。分组通过抽取密封信封完成。研究者每日随机分配。
该研究由两名具有3年以上麻醉经验、精通人类气道管理、且在猪的气管插管操作方面经验不足7个月的麻醉科实习生完成,由一名麻醉护士协助插管并评估数据(n = 2,年龄:33岁 ± 1岁,人类气管插管经验:>1,000例,人类清醒状态下纤维支气管镜插管经验:>100例)。
FIE组按照上述方案进行纤维光导辅助插管。CI组在操作上与FIE组一致,直至方案的第3.2步。此后进行如下更改:将喉镜插入会厌谷后,检查者使用一根已插入导丝的气管导管,从右侧梨状隐窝向左沿软腭作轻柔的弧形动作,将会厌推开。随后,将该气管导管经声韧带之间推进至气管内。助手撤出导丝,使用10 mL注射器充胀气管导管的气囊,并开始机械通气。
访问受限。请登录或开始试用以查看此内容。
讨论
在以往的研究中,我们的研究团队已详细阐述了猪模型在转化医学中的具体优势2,27,32,33。通常情况下,降低动物的应激水平和避免不必要的疼痛应成为任何研究方案中不可或缺的部分,这对于获得可靠且可重复的数据至关重要。因此,对预计存在困难气道的猪进行清醒状态下经内镜引导的气管插管并不可行。
必须指出,对大型动物模型实施和维持麻醉应仅由经过专门培训的人员操作,或在其直接监督下进行。在规划和开展此类实验时,若未遵守此规定,可能导致动物遭受相关伤害、疼痛、应激、焦虑甚至死亡。正确摆放猪的体位对于确保充分通气、顺利进行喉镜检查以及成功插管至关重要。仰卧位便于实施本气道管理方案,并可在必要时方便后续操作,而无需重新调整动物体位8。
尽管应避.......
访问受限。请登录或开始试用以查看此内容。
披露
该可弯曲插管内窥镜及其配件由制造商无偿提供,仅用于科研目的。作者声明不存在其他经济利益或利益冲突。
致谢
作者感谢 Dagmar Dirvonskis 提供的出色技术支持。
....访问受限。请登录或开始试用以查看此内容。
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| Ambu aScope 常规型 | Ambu GmbH,医疗器械,德国巴特瑙海姆 | 一次性光纤外径 5 mm | |
| Ambu aView 监护仪 | Ambu GmbH,医疗器械,德国巴特瑙海姆 | 监测 | |
| 阿曲库铵 Hikma 50 mg/5mL | Hikma Pharma GmbH,马丁斯里德 | 阿曲库铵 | |
| 阿扎哌隆(Stresnil)40 mg/mL | Lilly Deutschland GmbH,德国巴特洪堡 | azaperone | |
| BD Discardit II 注射器 2、5、10、20 mL | Becton Dickinson S.A. Carretera, Mequinenza Fraga, 西班牙 | 注射器 | |
| BD Luer Connecta | Becton Dickinson Infusion Therapy, AB 赫尔辛堡,瑞典 | 三通止流阀 | |
| BD Microlance 3 20 G | Becton Dickinson S.A. Carretera, Mequinenza Fraga, 西班牙 | 套管 | |
| Curafix i.v. classics | Lohmann & Rauscher International GmbH & Co. KG,德国伦斯多夫 | 导管固定敷料 | |
| 恩斯特öm Carestation | GE Healthcare,美国麦迪逊 | 呼吸机 | |
| 芬太尼-Janssen 0.05 mg/mL | 扬森-西拉格有限公司,诺伊斯 | 芬太尼 | |
| Fü搅拌棒,直径 4.3 | Rüsch | 气管插管导引器 | |
| IBM SPSS Statistics for Windows,版本 20 | IBM SPSS Statistics for Windows,版本 20.0。Armonk,NY:IBM Corp.) | 统计软件 | |
| Incetomat-线 150 cm | Fresenius, Kabi Deutschland, GmbH | 灌注管路 | |
| Intrafix Primeline | B. Braun Melsungen AG,德国美尔森 | 输液管路 | |
| JOZA 一次性丁腈检查手套 | JOZA, Mü德国南肯 | 一次性手套 | |
| 喉镜,45.48.50,KL 2000 | Medicon | 喉镜手柄 | |
| Littmann Classic III 听诊器 | 3M Deutschland GmbH,诺伊斯,德国 | 听诊器 | |
| 鲁尔锁 | 德国 B.Braun Melsungen AG | ||
| 受损的纱布敷料 | Maimed GmbH,德国诺因基兴 | 用纱布垫固定舌头 | |
| Masimo LNCS Adtx SpO2 传感器 | Masimo Corporation Irvine, Ca 92618 美国 | 尾部饱和夹 | |
| Masimo LNCS TC-I SpO2 耳夹式传感器 | Masimo Corporation Irvine, Ca 92618 美国 | 耳部饱和夹 | |
| Masimo Radical 7 | Masimo Corporation Irvine, Ca 92618 美国 | 外周血氧饱和度 | |
| 咪达唑仑 15 mg/3 mL | 德国哈梅林市,哈梅林制药有限公司 | 咪达唑仑 | |
| Midmark 小型犬用塑料面罩,带隔膜,FRSCM-0005 | 美国俄亥俄州代顿市 Midmark 公司 | 犬用通气面罩 | |
| Octeniderm 无色 | Schülke & Mayr GmbH,德国诺登施泰特 | 酒精消毒剂 | |
| 原装 Perfusor 注射器 50 mL | 德国 B.Braun Melsungen AG | 灌注器注射器 | |
| Perfusor FM Braun | 德国 B.Braun Melsungen AG | 注射泵 | |
| 丙泊酚 2% 20 mg/mL(50 mL 瓶装) | Fresenius, Kabi Deutschland, GmbH | 丙泊酚 | |
| RÜSCH Führungsstab für 气管插管(内径 5.6 mm) | Teleflex Medical Sdn. Bhd,马来西亚 | PVC涂层管导丝 | |
| Rüschelit Super Safety Clear >ID 6/6.5 /7.0 mm | Teleflex Medical Sdn. Bhd,马来西亚 | 气管插管 | |
| 不锈钢Macintosh喉镜öße 4 | Welch Allyn69604 | 喉镜片 | |
| Sterofundin | B.Braun Melsungen AG,德国美尔森 | 平衡电解质溶液 | |
| Ultrastop 防雾剂滴瓶 25 mL | Sigmapharm Arzneimittel GmbH,维也纳,奥地利 | 防雾剂 | |
| Vasofix Safety 22 G-16 G | 德国 B.Braun Melsungen AG | 静脉导管 | |
| VBM 气囊压力计 | 德国,明斯特兰地区苏尔茨,VBM 医疗技术有限公司 | 袖带压力计 | |
| 泽莱特 | Lohmann & Rauscher 国际有限公司 & Co. KG,德国伦茨多夫 | 组织拭子 |
参考文献
- Kleinman, M. E., Oh, W., Stonestreet, B. S. Comparison of intravenous and endotracheal epinephrine during cardiopulmonary resuscitation in newborn piglets. Critical Care Medicine. 27 (12), 2748-2754 (1999).
- Rissel, R., et al.
访问受限。请登录或开始试用以查看此内容。
重印与许可
勘误
Formal Correction: Erratum: Endotracheal Intubation Using a Flexible Intubation Endoscope As a Standardized Model for Safe Airway Management in Swine
Posted by JoVE Editors on 4/03/2023. Citeable Link.
An erratum was issued for: Endotracheal Intubation Using a Flexible Intubation Endoscope As a Standardized Model for Safe Airway Management in Swine. The Protocol, Representative Results, and Discussion sections were updated.
In the Protocol, step 1.5 was updated from:
Disinfect the skin with a disinfectant (alcoholic) before inserting a peripheral vein cannula (22 G) into an ear vein. Spray the area, wipe once, then spray again, and allow the disinfectant to dry.
to:
Disinfect the skin with a disinfectant (alcoholic) before inserting a peripheral vein cannula (22 G) into an ear vein. Spray the area, wipe once, then spray again, and allow the disinfectant to dry. Secure the ear cannula with a band-aid (See Table of Materials).
In the Protocol, step 3.7 was updated from:
While maintaining the position of the endoscope, advance the endotracheal tube until it becomes visible in the camera image.
NOTE: If the endotracheal tube cannot be advanced through the glottic plane, there is a possibility that it has become caught on the arytenoid cartilage. In this case, the endotracheal tube must be withdrawn 1 cm and rotated by 90° before gently advancing again. If necessary, this maneuver can be repeated. Similar calibers of flexible intubation endoscope and endotracheal tube can minimize the risk of this issue occurring. If the endotracheal tube cannot be advanced despite this maneuver, it is likely that the subglottic narrowness-the narrowest part of the porcine larynx-cannot be passed. In this case, a smaller endotracheal tube size needs to be selected. Regular commercially available endotracheal tubes in sizes 6.5 cm or 7.0 cm ID should be able to pass the glottis as long as no anatomic abnormalities are present.
to:
While maintaining the position of the endoscope, advance the endotracheal tube until it becomes visible in the camera image.
NOTE: If the endotracheal tube cannot be advanced through the glottic plane, there is a possibility that it has become caught on the arytenoid cartilage. In this case, the endotracheal tube must be withdrawn 1 cm and rotated by 90° before gently advancing again. If necessary, this maneuver can be repeated. Similar calibers of flexible intubation endoscope and endotracheal tube can minimize the risk of this issue occurring. If the endotracheal tube cannot be advanced despite this maneuver, it is likely that the subglottic narrowness-the narrowest part of the porcine larynx-cannot be passed. In this case, a smaller endotracheal tube size needs to be selected. Regular commercially available endotracheal tubes in sizes 6.5 cm or 7.0 cm ID should be able to pass the glottis as long as no anatomic abnormalities are present. Endotracheal tube size requirements vary depending on the piglet size and breed.
In the Representative Results, the sixth paragraph was updated from:
Statistical analyses were performed using commercially available software (see Table of Materials). Normal distribution was examined using the Kolmogorov-Smirnoff test28. If a normal distribution was determined, group differences were analyzed using t-tests of independent samples29 or the Mann-Whitney U test30 for the non-parametric version. Data are presented as mean (± standard deviation). Correlations of ordinal-scale data were examined using Spearman's correlation coefficient31. A significance level of p < 0.05 was assumed.
to:
Statistical analyses were performed using commercially available software (see Table of Materials). Normal distribution was examined using the Kolmogorov-Smirnoff test28. If a normal distribution was determined, group differences were analyzed using t-tests of independent samples29 or the Mann-Whitney U test30 for the non-parametric version. Data are presented as mean (± standard deviation). Correlations of ordinal-scale data were examined using Spearman's correlation coefficient31. A significance level of p < 0.05 was assumed. All tests were performed with exploratory intention; therefore p-values are descriptive. Nevertheless, p < 0.05 was accepted as indicative of statistical significance.
In the Representative Results, the legend for figure 1 was updated from:
Figure 1: Number of intubation attempts in group comparison. For the group that was intubated using a flexible intubation endoscope, every intubation attempt was successful; in the group that was conventionally intubated, it took an average of 1.4 attempts before the endotracheal tube could be placed correctly. Error bars show the standard deviation. Please click here to view a larger version of this figure.
to:
Figure 1: Number of intubation attempts in group comparison. For the group that was intubated using a flexible intubation endoscope, every intubation attempt was successful; in the group that was conventionally intubated, it took an average of 1.4 attempts before the endotracheal tube could be placed correctly. Error bars show the standard deviation. n = 5 (for each group). Please click here to view a larger version of this figure.
In the Representative Results, figure 2 was updated from:
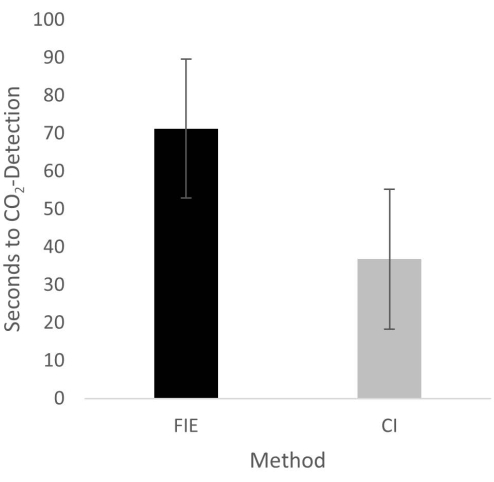
Figure 2: Time until CO2 detection in group comparison. For the group that was intubated using a flexible intubation endoscope, it took significantly longer until end-tidal CO2 could be detected, depicted as mean and standard deviation. Please click here to view a larger version of this figure.
to:
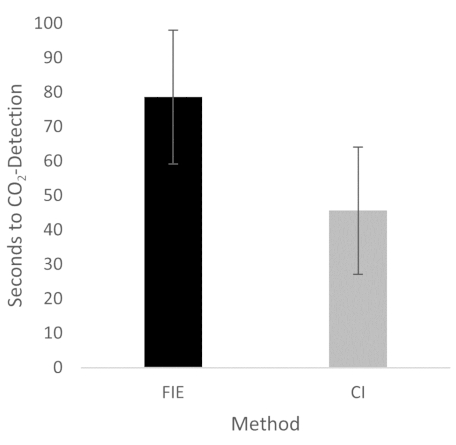
Figure 2: Time until CO2 detection in group comparison. For the group that was intubated using a flexible intubation endoscope, it took significantly longer until end-tidal CO2 could be detected, depicted as mean and standard deviation. n = 5 (for each group). Please click here to view a larger version of this figure.
In the Discussion, the fifth paragraph was updated from:
The increased duration had no clinical significance in this cohort. At no time was the termination criterion-a saturation of less than 93%-reached. This is shown in the results because a procedure change was unnecessary at any time. Prior adequate mask ventilation is a critical step to allow sufficient time for fiberoptic endotracheal tube placement to avoid rapid desaturation34. These results are consistent with previous studies comparing conventional intubation and endoscopically assisted intubations with inexperienced providers35.
to:
The increased duration had no clinical significance in this cohort. At no time was the termination criterion-a saturation of less than 93%-reached. This is shown in the results because a procedure change was unnecessary at any time. Prior adequate mask ventilation is a critical step to allow sufficient time for fiberoptic endotracheal tube placement to avoid rapid desaturation34. These results are consistent with previous studies comparing conventional intubation and endoscopically assisted intubations with inexperienced providers35. We attribute the prolonged duration of fiberoptic intubation to the fact that one must first reorient again after insertion, whereas with conventional intubation, one retains a view of the glottis. It is also important to avoid contact with the mucosa with the flexible intubation endoscope during advancement. This requires occasional corrective maneuvers. Last but not least, after successful placement, retraction of the relatively long endoscope is required, which increases the time to CO2 detection slightly.
