The present study shows the establishment of three different lung donation models (post-brain death donation, post-circulatory death donation, and post-hemorrhagic shock donation). It compares the inflammatory processes and pathological disorders associated with these events.
Method Article
Study of Experimental Organ Donation Models for Lung Transplantation
In This Article
Summary
Abstract
Experimental models are important tools for understanding the etiological phenomena involved in various pathophysiological events. In this context, different animal models are used to study the elements triggering the pathophysiology of primary graft dysfunction after transplantation to evaluate potential treatments. Currently, we can divide experimental donation models into two large groups: donation after brain death and donation after circulatory arrest. In addition, the deleterious effects associated with hemorrhagic shock should be considered when considering animal models of organ donation. Here, we describe the establishment of three different lung donation models (post-brain death donation, post-circulatory death donation, and post-hemorrhagic shock donation) and compare the inflammatory processes and pathological disorders associated with these events. The objective is to provide the scientific community with reliable animal models of lung donation for studying the associated pathological mechanisms and searching for new therapeutic targets to optimize the number of viable grafts for transplantation.
Introduction
Clinical relevance
Organ transplantation is a well-established therapeutic option for several serious pathologies. In recent years, many advances have been achieved in the clinical and experimental fields of organ transplantation, such as greater knowledge of the pathophysiology of primary graft dysfunction (PGD) and advances in the areas of intensive care, immunology, and pharmacology1,2,3. Despite the achievements and improvements in the quality of the related surgical and pharmacological procedures, the relationship between the number of available organs and the number of recipients on the waiting list remains one of the main challenges2,4. In this regard, the scientific literature has proposed animal models for studying therapies that can be applied to organ donors to treat and/or preserve the organs until the time of transplantation5,6,7,8.
By mimicking the different events observed in clinical practice, animal models allow the study of the associated pathological mechanisms and their respective therapeutic approaches. The experimental induction of these events, in most isolated cases, has generated experimental models of organ and tissue donation that are widely investigated in the scientific literature on organ transplantation6,7,8,9. These studies employ different methodological strategies, such as those inducing brain death (BD), hemorrhagic shock (HS), and circulatory death (CD), since these events are associated with different deleterious processes that compromise the functionality of the donated organs and tissues.
Brain death (BD)
BD is associated with a series of events that lead to the progressive deterioration of different systems. It usually occurs when an acute or gradual increase in intracranial pressure (ICP) happens due to brain trauma or hemorrhage. This increase in ICP promotes an increase in blood pressure in an attempt to maintain a stable cerebral blood flow in a process known as Cushing's reflex10,11. These acute changes can result in cardiovascular, endocrine, and neurological dysfunctions that compromise the quantity and quality of the donated organs, in addition to impacting post-transplantation morbidity and mortality10,11,12,13.
Hemorrhagic shock (HS)
HS, in turn, is often associated with organ donors, as most of them are victims of trauma with significant loss of blood volume. Some organs, such as the lungs and heart, are particularly vulnerable to HS due to hypovolemia and consequent tissue hypoperfusion14. HS induces lung injury through increased capillary permeability, edema, and infiltration of inflammatory cells, mechanisms that together compromise gas exchange and lead to progressive organ deterioration, consequently derailing the donation process6,14.
Circulatory death (CD)
The use of post-CD donation has been growing exponentially in major world centers, thus contributing to the increase in the number of collected organs. Organs recovered from post-CD donors are vulnerable to the effects of warm ischemia, which occurs after an interval of low (agonic phase) or no blood supply (asystolic phase)8,15. Hypoperfusion or the absence of blood flow will lead to tissue hypoxia associated with the abrupt loss of ATP and the accumulation of metabolic toxins in tissues15. Despite its current use for transplantation in clinical practice, many doubts remain about the impact of the use of these organs on the quality of the post-transplant graft and on patient survival15. Thus, the use of experimental models for a better understanding of the etiological factors associated with CD is also growing8,15,16,17.
Experimental models
There are various experimental organ donation models (BD, HS, and CD). However, studies often focus on only one strategy at a time. There is a noticeable gap in studies that combine or compare two or more strategies. These models are very useful in the development of therapies that seek to increase the number of donations and consequently decrease the waiting list of potential recipients. The animal species used for this purpose vary from study to study, with porcine models being more commonly selected when the objective is a more direct translation with human morpho physiology and less technical difficulty in the surgical procedure due to the size of the animal. Despite the benefits, logistical difficulties and high costs are associated with the porcine model. On the other hand, the low cost and possibility of biological manipulation favor the use of rodent models, allowing the researcher to start from a reliable model to reproduce and treat lesions, as well as to integrate the knowledge acquired in the field of organ transplantation.
Here, we present a rodent model of brain death, circulatory death, and hemorrhagic shock donation. We describe inflammatory processes and pathological conditions associated with each of these models.
Protocol
Animal experiments complied with the Ethics Committee for Experimental Animals Use and Care of the Faculty of Medicine of the University of São Paulo (protocol number 112/16).
1. Animal grouping
- Randomly assign twelve male Sprague Dawley rats (250-300 g) to one of three experimental groups (n=4) to analyze and compare the effects associated with the animal models.
- Assign animals to hemorrhagic shock group (HS, n=4): animals subjected to vascular catheterization with hemorrhagic shock induction + maintenance for 360 min + cardiopulmonary block extraction + sample preparation for analysis.
- Assign animals to brain death group (BD, n=4): animals subjected to brain death + maintenance for 360 min + cardiopulmonary block extraction + sample preparation for analysis.
- Assign animals to circulatory death group (CD, n=4): animals subjected to vascular catheterization + induction of circulatory death + suspension of ventilation + ischemia at room temperature for 180 min + sample preparation for analysis.
2. Anesthesia and presurgical preparation
- Place the rat in a closed chamber with 5% isoflurane for 1 - 4 min. Confirm proper anesthetization by checking the toe pinch reflex. In the absence of reflex reactions (no paw retraction), perform orotracheal intubation (14-G angiocath) with the aid of a pediatric laryngoscope.
- With a previously adjusted mechanical ventilator (FiO2 100%, tidal volume 10 mL/kg, 90 cycles/min, and PEEP 3.0 cmH2O), connect the tracheal catheter to the ventilator, and adjust the anesthetic concentration to 2%.
NOTE: All procedures related to animal models followed the same anesthetic protocol described in this section. - Remove fur from the regions of interest (head, neck, chest and abdomen). Then, using gauze, disinfect the surgical field and the animal's tail. Disinfection is performed with three alternating rounds of an alcoholic solution of chlorhexidine digluconate scrub.
- Cut the tip of the animal's tail, place the thumb and the index finger over the base of the tail, and then press and slide them away from the base. Collect a peripheral blood sample (20 µL) through the tail for the total leukocyte count8.
NOTE: This procedure must be performed before the start of the tracheostomy and immediately at the end of each protocol (BD and HS - after 360 min). - Use a precision pipette to dilute the collected blood in 380 µL (1:20) of Turk's solution (Glacial acetic acid 99%). Once diluted, pipette the blood sample into a Neubauer chamber and place it under a microscope (40x). Perform the total leukocyte count in the four lateral quadrants of the chamber.
3. Tracheostomy
- With the help of appropriate scissors and forceps, perform longitudinal dissection of the cervical trachea, starting from the middle third of the neck to the suprasternal notch (
 1.5 cm incision). After the incision of the skin and subcutaneous tissue, dissect the cervical muscles until the trachea is exposed.
- Place one 2-0 silk ligature beneath the trachea.
- Using microscissors, tracheostomize the upper third of the trachea to achieve uniform ventilation. Horizontally cut the trachea between two cartilaginous rings to accommodate the diameter of a metal cannula (3.5 cm).
- Insert the ventilation tube and fix it with prepared ligatures.
- Connect the ventilation tube to the small-animal ventilation system.
- Ventilate the rat with a tidal volume of 10 mL/kg, rate of 70 cycles/min, and PEEP of 3 cmH2O.
4. Femoral artery and vein catheterization
- Expose the femoral triangle through a small incision (1.5 cm) in the inguinal region. Identify and isolate the femoral vessels. For this procedure, use a stereomicroscope (3.2x magnification).
- Place two 4-0 silk ligatures beneath the blood vessels (vein or artery), one distally and the other proximally. Close the most distal ligature, then place a preadjusted knot in the proximal ligature and pull.
- Insert the catheter through a small, pre-formed incision in the vessels. Fixate the cannula to avoid dislocation.
NOTE: Make the catheters from a 20 cm neonatal extender welded by heating to a peripheral intravenous catheter suitable for the caliber of the animal's venous network, thus preventing regurgitation of blood contents. Lubricate the cannula with heparin, avoiding the formation of thrombi and complications during mean arterial pressure (MAP) measurement. - Connect the artery catheter to a pressure transducer and a vital sign monitoring system to record the mean arterial pressure (MAP). The transducer should be positioned at the level of the animal's heart. Record the MAP every 10-min period.
- Place the syringe catheter (3 mL) into the vein, aiming for hydration and exsanguination when necessary.
5. Hemorrhagic shock induction
- Through venous access and with a heparinized syringe, remove small volumes of blood until MAP values of 50 mmHg are reached, thus establishing hemorrhagic shock.
NOTE: Collect a 2 mL aliquot of blood every 10 min in the first hour of the experiment and every 30 min in the subsequent hours. - Keep the pressure stable at approximately 50 mmHg for a period of 360 min. To do so, remove or add aliquots of blood if the pressure increases or decreases, respectively.
- Put a source of heat nearby to avoid hypothermia.
NOTE: Here, a heat lamp is used. - At the end of the protocol, harvest the pulmonary block at the total lung capacity (TLC) and either flash freeze in liquid nitrogen or place it in a fixing solution for further studies.
NOTE: With the aid of a small animal ventilator, the ventilatory parameters can be accessed during the protocol. In the present study, these parameters were evaluated immediately before HS induction (Baseline) and 360 min later (Final).
6. Circulatory death induction
- To induce circulatory death, administer 150 mg/kg sodium thiopental through the venous line. Then turn off the ventilation system.
- Note the progressive decrease in MAP until it reaches 0 mmHg. From this point, consider the start of the warm ischemia period and begin the time count. The animal should remain at room temperature (approximately 22 °C) for 180 min.
- At the end of the protocol, reconnect the lungs to the mechanical ventilator and harvest the pulmonary block at TLC for collection. Either flash freeze using liquid nitrogen or place it in the fixation solution for further studies.
7. Brain death induction
- Place the rat in the prone position.
- Remove the skin from the skull using surgical scissors. Drill a 1 mm caliber borehole 2.80 mm anterior and 10.0 mm ventral to bregma and 1.5 mm lateral to the sagittal suture.
- Insert the entire balloon catheter into the cranial cavity and ensure that the balloon is prefilled with saline (500 µL).
- With the help of a syringe, rapidly inflate the catheter.
- Confirm brain death by observing an abrupt MAP elevation (Cushing's reflex), the absence of reflexes, bilateral mydriasis, and apnea. After confirmation, discontinue anesthesia and keep the animal on mechanical ventilation for 360 min.
- Place a source of heat nearby to avoid hypothermia.
- At the end of the protocol, harvest the pulmonary block at TLC for collection and either flash freeze in liquid nitrogen or place it in a fixing solution for further studies.
NOTE: With the aid of a small animal ventilator, the ventilatory parameters can be accessed during the protocol. In the present study, we evaluated these parameters immediately before BD induction (Baseline) and after 360 minutes (Final).
Results
Mean arterial pressure (MAP)
To determine the hemodynamic repercussions of BD and HS, MAP was evaluated across the 360 min of the protocol. The baseline measurement was collected after skin removal and skull drilling and before blood aliquot collection for animals subjected to BD or HS, respectively. Prior to BD and HS induction, the baseline MAP of the two groups was similar (BD: 110.5 ± 6.1 vs. HS: 105.8 ± 2.3 mmHg; p=0.5; two-way ANOVA). After catheter insufflation, the BD group experienced an abrupt increase in blood pressure levels (138. 7 ± 10.1 mmHg). The hypertensive peak is a peculiar event related to increased intracranial pressure and can be considered the first evidence of the establishment of BD. In addition, we observed the absence of reflexes, bilateral mydriasis, and post-inflation apnea in all animals. This peak pressure was followed by a rapid decrease in MAP (10 min - 81.2 ± 10 mmHg). Hypotension persisted for approximately 50 min, after which MAP levels returned to values close to those at baseline (120 min - 120.7 ± 7.5 mmHg) (Figure 1).
Unlike in the BD group, the decrease in MAP in the HS group is associated with the withdrawal of blood aliquots in the first 10 min of the experiment. Hypovolemic shock was maintained for 360 min (mean variation throughout the protocol 52.3 ± 1.2 mmHg). After the end of the protocol, the BD group showed a significantly different MAP pattern over the 6-h follow-up from the HS group (BD: 93.7 ± 4.5 vs. HS: 52.3 ± 0.5 mmHg; p<0.0001; Student's t test).
Pulmonary mechanics
To evaluate the elastic and resistive parameters of the respiratory system, an analysis of the lung mechanics of the animals subjected to BD and HS was performed. 360 min after onset and after hypotension maintenance, the HS group exhibited increased lung tissue resistance (G) (HS: Baseline - 0.26 ± 0.02 vs. Final - 0.51 ± 0.05 cmH2O.mL-1; p=0.03; two-way ANOVA), followed by reduced respiratory system compliance (Crs) (HS: Baseline - 0.64 ± 0.05 vs. Final - 0.23 ± 0.004 cmH2O/mL; p=0.001; two-way ANOVA) (Figure 2A,B).
Pulmonary edema
At the end of the protocol, the middle lobe of the right lung was collected for all groups, and its weight was measured to analyze the wet/dry weight ratio, which was used as the pulmonary edema index. The wet weight was assessed immediately after extraction of the organ, and the dry weight was measured after 24 h in an 80 °C oven. According to this ratio, the BD group (2.32 ± 0.1) showed greater edema than the HS (1.97 ± 0.03) and CD groups (2.04 ± 0.02) (Figure 3).
Systemic and tissue inflammatory parameters
At the end of the protocol, there was a significant increase in the total number of systemic leukocytes in the group that underwent HS (Baseline - 13888 ± 887.3 vs. Final - 35263 ± 4076 mm3; p=0.0189); two-way ANOVA) (Figure 4). The HS group also showed an increase in the number of leukocytes both when compared to the baseline values and in relation to the BD group (p = 0.0132).
Tissue inflammation was assessed by quantifying inflammatory markers in the lung tissue. For this purpose, lung tissue biopsy samples were homogenized in phosphate buffer and then sent for analysis for tumor necrosis factor alpha (TNF-α) and interleukin 1 beta (IL1-β) expression. IL1-β expression levels were greater in the BD group (304.4 ± 91 pg/mg) and HS group (327.5 ± 25.2 pg/mg) than in the CD group (8 ± 2.3 pg/mg; p=0.004; one-way ANOVA) (Figure 5B). The HS group also showed higher levels of TNF-α (4.7 ± 0.3 pg/mg; p<0.0001; one-way ANOVA) than the BD group (1.3 ± 0.3 pg/mg) and CD group (0.4 ± 0.2 pg/mg) (Figure 5B).
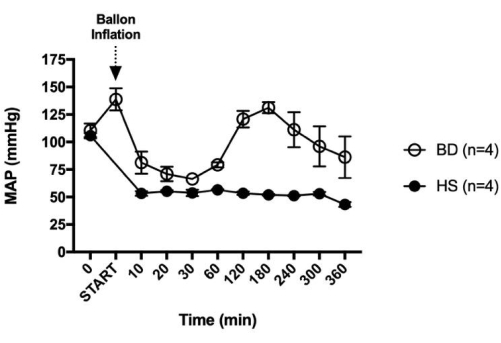
Figure 1: Time course of mean arterial pressure (MAP) in the brain death (BD) and hemorrhagic shock (HS) groups. The values for all of the measurements are expressed as the means ± standard errors of the means (SEMs). MAP, mean arterial pressure; BD, brain death; HS, hemorrhagic shock. Please click here to view a larger version of this figure.
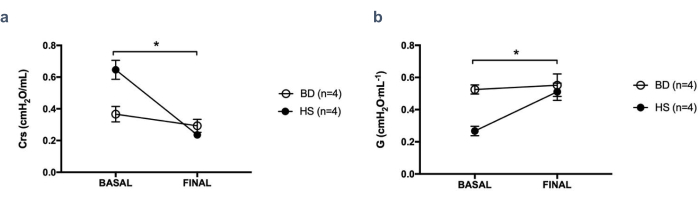
Figure 2: Lung mechanics. Lung mechanics as determined by (A) respiratory system compliance and (B) tissue resistance in the brain death (BD) group and the hemorrhagic shock (HS) group. * indicates significant differences between the baseline and final values in the HS group (p<0.05). The values for all the measurements are expressed as the means ± standard errors of the means (SEMs), and two-way ANOVA was used for comparisons. Crs, compliance of the respiratory system; G, tissue resistance; BD, brain death; HS, hemorrhagic shock. Please click here to view a larger version of this figure.
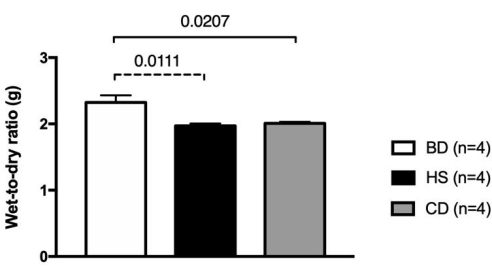
Figure 3: Lung edema determined by lung wet-to-dry weight ratio in the brain death (BD) group and the hemorrhagic shock (HS) group. The values for all the measurements are expressed as the means ± standard errors of the means (SEMs), and comparisons were made with one-way ANOVA. BD, brain death; HS, hemorrhagic shock; CD, circulatory death. Please click here to view a larger version of this figure.
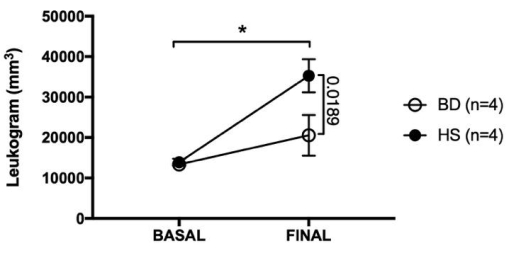
Figure 4: Leukogram of the hemorrhagic shock (HS) group and brain death (BD) group. * indicates significant differences between baseline and final values in the HS group (p<0.05). The values for all the measurements are expressed as the means ± standard errors of the mean (SEMs), and comparisons were made with two-way ANOVA. BD, brain death; HS, hemorrhagic shock. Please click here to view a larger version of this figure.
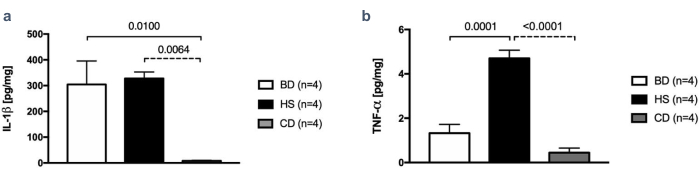
Figure 5: Local inflammatory responses were less prominent in the circulatory death (CD) group. (A) Lung tissue expression of IL-1β; (B) Lung tissue expression of TNF-α. The values for all the measurements are expressed as the means ± standard errors of the mean (SEMs), and comparisons were made with one-way ANOVA. BD, brain death; HS, hemorrhagic shock; CD, circulatory death. Please click here to view a larger version of this figure.
Discussion
In recent years, the increasing number of diagnoses of brain death has led to it becoming the largest provider of organs and tissues intended for transplantation. This growth, however, has been accompanied by an incredible increase in donations after circulatory death. Despite its multifactorial nature, most of the triggering mechanisms of the causes of death begin after or accompany trauma with extensive loss of blood content4,18.
In this context, experimental models of brain death, circulatory arrest, and hemorrhagic shock are important tools for the prospective study of complications associated with the cause of donor death and their impact on the viability of potential organs intended for transplantation6,8,10. Several animal lineages have been suggested for model establishment, such as swine, rabbit, rat and mouse. Rat and mouse models are more common in the literature because they are not very expensive and involve low logistical difficulty while satisfactorily reproducing the pathophysiological events under study8,13,14,15.
We would like to emphasize that recent guidelines and studies have endorsed the use of pre-anesthetic analgesia as an integral part of surgical protocols, even in acute situations, aiming for more comprehensive management of perioperative pain and animal well-being. We recommend that researchers evaluate such an approach in future studies.
Brain death (BD)
The BD model was found to be reproducible by means of an abrupt increase in ICP. The use of appropriate instruments and trained personnel allows surgical success and reproduction of the technique with a few weeks of training. During the development of the BD technique, trepanation should be performed with an appropriate motorized drill so that there is no slack in the catheter, thus preventing the projection of brain tissue out of the hole. In addition, during drilling, the forward movement of the drill should be stopped as soon as the initial resistance offered by the skull is overcome.
Researchers should remain alert and ensure rapid inflation of the catheter, as gradual inflation promotes distinct inflammatory and hemodynamic responses21. Blood pressure changes, in turn, should be monitored constantly throughout the protocol, especially during catheter insufflation, which should be accompanied by an abrupt increase in MAP and during the first hour after BD establishment (post-inflation hypotension period). These results are in agreement with the literature, which shows the establishment of a hypertensive peak immediately after catheter insufflation, followed by a decrease in pressure levels, in a likely response to the transient increase in circulating catecholamine levels22.
Maintaining the animal in BD for prolonged periods may lead to hypotension followed by circulatory death, making the experiment unfeasible. Accordingly, most protocols used in the literature establish a follow-up period that varies from 4 to 6 hours, after which vasoactive drugs must be administered12,13,21,22,23.
In addition to hemodynamic changes, cerebral infarction and ischemia promote an increase in the systemic circulation of proinflammatory factors, which, when they reach the lungs, contribute to lung parenchyma injury24,25,26.
In our study, BD was accompanied by a significant increase in tissue IL-1β expression (over CD) and the wet/dry weight ratio, an index of pulmonary edema. Previous studies have indicated an increase in circulating levels of proinflammatory cytokines after a BD event, which may ultimately favor the modulation of the expression of adhesion molecules, increased vascular permeability, and consequent leukocyte migration27,28,29,30.
Hemorrhagic shock (HS)
Established through the withdrawal or reinfusion of blood aliquots with the goal of prolonged hypotension maintenance (≤ 50 mmHg), the fixed pressure model of HS aims to mimic the decrease in blood volume caused by the hemorrhagic process and, consequently, the attenuation of the systemic filling pressure. These events lead to a decrease in MAP, accompanied by a decrease in pulmonary perfusion pressure31,32.
Among the advantages of this HS model is the possibility of controlling the degree and duration of hypotension, in addition to the greater reproducibility of the technique when compared to models based on a prefixed blood volume. Accordingly, most protocols used in the literature establish a protocol period that varies from 15 min to more than 180 min, with mean blood pressure levels ranging from 20-55 mmHg, depending on the analysis chosen in the study6,32. In the present study, hypotension was maintained for 3 hours, leading to increased tissue resistance, followed by decreased lung compliance in animals subjected to HS. Corroborating this, different studies in the literature have indicated a proportional relationship between the time spent in HS and the impacts of hypovolemia on airway resistance and lung compliance6,33,34.
In addition, in the present study, HS was accompanied by significant leukocytosis and increased tissue expression of IL-1β (with respect to CD) and TNF-α. Injury to the pulmonary microvasculature endothelium, induced by the release of reactive oxygen species from the primary process of hypoxia and established ischemia, will increase vascular permeability, which, together with the increase in pulmonary artery pressure, will act as a chemotactic factor for leukocytes and the subsequent release of inflammatory mediators6,20,31,35,36,37,38.
Circulatory death (CD)
The main difference between the marginal grafts originating from the BD and CD processes is the warm ischemia time (WIT) to which the graft will be subjected, defined by some researchers as the time between the absence of peripheral pulses and interruption of blood flow due to removal of life support equipment until cold or regional perfusion of the organ17,39,40.
In the present study, the organs and tissues of animals derived from the CD model were subjected to a WIT period of 180 min. Several studies in the literature have revealed a proportional relationship between the WIT and post-transplantation dysfunction, suggesting that the ischemia time should vary according to the particularities and integrity of each organ. In this context, lung grafts from rats have been shown to tolerate up to 3-h periods of warm ischemia41,42.
With evidence of tissue injury caused by the predominant sympathetic phase, hemodynamic instability, and systemic inflammation resulting from the BD process, donations after circulatory arrest have been reconsidered as a potential strategy to decrease complications associated with transplantation41,42,43. In this sense, our data indicate a dramatic decrease in IL-1β and TNF-α levels in the CD model with respect to the other two models studied. Corroborating this, Iskender et al.4 noted the low levels of tissue cytokines in a model of lung reperfusion in rats with tissues donated after the WIT through mechanisms that are still poorly understood.
Based on the above, the choice of methodology and its adaptations should depend on the objectives developed by the researcher. Once determined, these objectives should guide the type of donation model, the protocol time and the analyses to be performed. It is also possible to relate the type of donation with animal models of lung reconditioning and reperfusion.
Conclusions
In conclusion, the organ donor models described here are potential tools in the study of the changes associated with different graft harvesting methodologies and could provide means by which a full understanding of the impact of the quality of these organs on post-transplantation outcomes can be obtained, given the reproducibility and reliability of the methodologies presented here.
Disclosures
We wish to confirm that there are no known conflicts of interest associated with this publication and that there has been no significant financial support for this work that could have influenced its outcome.
Acknowledgements
We thank FAPESP (Fundação de Amparo à Pesquisa do Estado de São Paulo) for granting financial support.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 14-gauge angiocath | DB | 38186714 | Orotracheal intubation |
| 2.0-silk | Brasuture | AA553 | Tracheal tube fixation |
| 24-gauge angiocath | DB | 38181214 | Arterial and venous access |
| 4.0-silk | Brasuture | AA551 | Fixation of arterial and venous cannulas |
| Alcoholic chlorhexidine digluconate solution (2%). | Vic Pharma | Y/N | Asepsis |
| Trichotomy apparatus | Oster | Y/N | Clipping device |
| Precision balance | Shimadzu | D314800051 | Analysis of the wet/dry weight ratio |
| Barbiturate (Thiopental) | Cristália | 18080003 | DC induction |
| Balloon catheter (Fogarty-4F) | Edwards Life Since | 120804 | BD induction |
| Neonatal extender | Embramed | 497267 | Used as catheters with the aid of the 24 G angiocath |
| FlexiVent | Scireq | 1142254 | Analysis of ventilatory parameters |
| Heparin | Blau Farmaceutica SA | 7000982-06 | Anticoagulant |
| Isoflurane | Cristália | 10,29,80,130 | Inhalation anesthesia |
| Micropipette (1000 µL) | Eppendorf | 347765Z | Handling of small- volume liquids |
| Micropipette (20 µL) | Eppendorf | H19385F | Handling of small- volume liquids |
| Microscope | Zeiss | 1601004545 | Assistance in the visualization of structures for the surgical procedure |
| Multiparameter monitor | Dixtal | 101503775 | MAP registration |
| Motorized drill | Midetronic | MCA0439 | Used to drill a 1 mm caliber borehole |
| Neubauer chamber | Kasvi | D15-BL | Cell count |
| Pediatric laryngoscope | Oxygel | Y/N | Assistance during tracheal intubation |
| Syringe (3 mL) | SR | 3330N4 | Hydration and exsanguination during HS protocol |
| Pressure transducer | Edwards Life Since | P23XL | MAP registration |
| Metallic tracheal tube | Biomedical | 006316/12 | Rigid cannula for analysis with the FlexiVent ventilator |
| Isoflurane vaporizer | Harvard Bioscience | 1,02,698 | Anesthesia system |
| Mechanical ventilator for small animals (683) | Harvard Apparatus | MA1 55-0000 | Mechanical ventilation |
| xMap methodology | Millipore | RECYTMAG-65K-04 | Analysis of inflammatory markers |
References
- Paterno, F., et al. Clinical implications of donor warm and cold ischemia time in donor after circulatory death liver transplantation. Liver Transplantation. 25 (9), 1342-1352 (2019).
- Yusen, R. D., et al. The registry of the International Society for heart and lung transplantation: thirty-third adult lung and heart-lung transplant report-2016; focus theme: primary diagnostic indications for transplant. The Journal of Heart and Lung Transplantation. 35 (10), 1170-1184 (2016).
- Jung, H. Y., et al. Comparison of transplant outcomes for low-level and standard-level tacrolimus at different time points after kidney transplantation. Journal of Korean Medical Science. 34 (12), e103(2019).
- Cypel, M., et al. The International Society for heart and lung transplantation donation after circulatory death registry report. The Journal of Heart and Lung Transplantation. 34 (10), 1278-1282 (2015).
- Drake, M., Bernard, A., Hessel, E. Brain death. Surgical Clinics of North America. 97 (6), 1255-1273 (2017).
- Nepomuceno, N. A., et al. Effect of hypertonic saline in the pretreatment of lung donors with hemorrhagic shock. Journal of Surgical Research. 225, 181-188 (2018).
- Menegat, L., et al. Evidence of bone marrow downregulation in brain-dead rats. International Journal of Experimental Pathology. (3), 158-165 (2017).
- Iskender, I., et al. Effects of warm versus cold ischemic donor lung preservation on the underlying mechanisms of injuries during ischemia and reperfusion. Transplantation. (5), 760-768 (2018).
- Cypel, M., et al. Normothermic ex vivo perfusion prevents lung injury compared to extended cold preservation for transplantation. American Journal of Transplantation. 9 (10), 2262-2269 (2009).
- Wauters, S., et al. Evaluating lung injury at increasing time intervals in a murine brain death model. Journal of Surgical Research. 183 (1), 419-426 (2013).
- Smith, M. Physiologic changes during brain stem death--lessons for management of the organ donor. The Journal of Heart and Lung Transplantation. 23 (9), S217-S222 (2004).
- Belhaj, A., et al. Mechanical versus humoral determinants of brain death-induced lung injury. PLoS One. 12 (7), e0181899(2017).
- Kolkert, J. L., et al. The gradual onset brain death model: a relevant model to study organ donation and its consequences on the outcome after transplantation. Laboratory Animals. 41 (3), 363-371 (2007).
- Rocha-E-Silva, M. Cardiovascular effects of shock and trauma in experimental models: A review. Revista Brasileira de Cirurgia Cardiovascular. 31 (1), 45-51 (2016).
- Manara, A. R., Murphy, P. G., O'Callaghan, G. Donation after circulatory death. British Journal of Anaesthesia. 108, i108-i121 (2012).
- Dhital, K. K., et al. Adult heart transplantation with distant procurement and ex-vivo preservation of donor hearts after circulatory death: a case series. The Lancet. 385 (9987), 2585-2591 (2015).
- Boucek, M. M., et al. Pediatric heart transplantation after declaration of cardiocirculatory death. The New England Journal of Medicine. 359 (7), 709-714 (2008).
- Kramer, A. H., Baht, R., Doig, C. J. Time trends in organ donation after neurologic determination of death: a cohort study. CMAJ Open. 5 (1), E19-E27 (2017).
- Reino, D. C., et al. Trauma hemorrhagic shock-induced lung injury involves a gut-lymph-induced TLR4 pathway in mice. PLoS One. 6 (8), e14829(2011).
- Pascual, J. L., et al. Hypertonic saline resuscitation of hemorrhagic shock diminishes neutrophil rolling and adherence to endothelium and reduces in vivo vascular leakage. Annals of Surgery. 236 (5), 634-642 (2002).
- Van Zanden, J. E., et al. Rat donor lung quality deteriorates more after fast than slow brain death induction. PLoS One. 15 (11), e0242827(2020).
- Shivalkar, B., et al. Variable effects of explosive or gradual increase of intracranial pressure on myocardial structure and function. Circulation. 87 (1), 230-239 (1993).
- López-Aguilar, J., et al. Massive brain injury enhances lung damage in an isolated lung model of ventilator-induced lung injury. Critical Care Medicine. 33 (5), 1077-1083 (2005).
- Catania, A., Lonati, C., Sordi, A., Gatti, S. Detrimental consequences of brain injury on peripheral cells. Brain, Behavior, and Immunity. 23 (7), 877-884 (2009).
- McKeating, E. G., Andrews, P. J., Mascia, L. Leukocyte adhesion molecule profiles and outcome after traumatic brain injury. Acta Neurochirurgica Supplement. 71, 200-202 (1998).
- Ott, L., McClain, C. J., Gillespie, M., Young, B. Cytokines and metabolic dysfunction after severe head injury. Journal of Neurotrauma. 11 (5), 447-472 (1994).
- Avlonitis, V. S., Wigfield, C. H., Kirby, J. A., Dark, J. H. The hemodynamic mechanisms of lung injury and systemic inflammatory response following brain death in the transplant donor. American Journal of Transplantation. 5 (4), 684-693 (2005).
- De Jesus Correia, C., et al. Hypertonic saline reduces cell infiltration into the lungs after brain death in rats. Pulmonary Pharmacology & Therapeutics. 61, 101901(2020).
- Kalsotra, A., Zhao, J., Anakk, S., Dash, P. K., Strobel, H. W. Brain trauma leads to enhanced lung inflammation and injury: evidence for role of P4504Fs in resolution. Journal of Cerebral Blood Flow & Metabolism. 27 (5), 963-974 (2007).
- Simas, R., Zanoni, F. L., Silva, R., Moreira, L. F. P. Brain death effects on lung microvasculature in an experimental model of lung donor. Journal Brasileiro de Pneumologia. 46 (2), e20180299(2020).
- Moore, K. The physiological response to hemorrhagic shock. Journal of Emergency Nursing. 40 (6), 629-631 (2014).
- Fülöp, A., Turóczi, Z., Garbaisz, D., Harsányi, L., Szijártó, A. Experimental models of hemorrhagic shock: a review. European Surgical Research. 50 (2), 57-70 (2013).
- Hillen, G. P., Gaisford, W. D., Jensen, C. G. Pulmonary changes in treated and untreated hemorrhagic shock. I. Early functional and ultrastructural alterations after moderate shock. The American Journal of Surgery. 122 (5), 639-649 (1971).
- Sprung, J., Mackenzie, C. F., Green, M. D., O'Dwyer, J., Barnas, G. M. Chest wall and lung mechanics during acute hemorrhage in anesthetized dogs. Journal of Cardiothoracic and Vascular Anesthesia. 11 (5), 608-612 (1997).
- Liu, X., et al. Inhibition of BTK protects lungs from trauma-hemorrhagic shock-induced injury in rats. Molecular Medicine Reports. 16 (1), 192-200 (2017).
- Maeshima, K., et al. Prevention of hemorrhagic shock-induced lung injury by heme arginate treatment in rats. Biochemical Pharmacology. 69 (11), 1667-1680 (2005).
- Gao, J., et al. Effects of different resuscitation fluids on acute lung injury in a rat model of uncontrolled hemorrhagic shock and infection. The Journal of Trauma. 67 (6), 1213-1219 (2009).
- Wohlauer, M., et al. Nebulized hypertonic saline attenuates acute lung injury following trauma and hemorrhagic shock via inhibition of matrix metalloproteinase-13. Critical Care Medicine. 40 (9), 2647-2653 (2012).
- Morrissey, P. E., Monaco, A. P. Donation after circulatory death: current practices, ongoing challenges, and potential improvements. Transplantation. 97 (3), 258-264 (2014).
- Snell, G. I., Levvey, B. J., Levin, K., Paraskeva, M., Westall, G. Donation after brain death versus donation after circulatory death: lung donor management issues. Seminars in Respiratory and Critical Care Medicine. 39 (2), 138-147 (2018).
- Iskender, I., et al. Effects of warm versus cold ischemic donor lung preservation on the underlying mechanisms of injuries during ischemia and reperfusion. Transplantation. 102 (5), 760-768 (2018).
- Yamamoto, S., et al. Activations of mitogen-activated protein kinases and regulation of their downstream molecules after rat lung transplantation from donors after cardiac death. Transplantation Proceedings. 43 (10), 3628-3633 (2011).
- Kang, C. H., et al. Transcriptional signatures in donor lungs from donation after cardiac death vs after brain death: a functional pathway analysis. The Journal of Heart and Lung Transplantation. 30 (3), 289-298 (2011).
Reprints and Permissions
